Study Overview
The investigation centers on the utility of two specific biomarkers—glial fibrillary acidic protein (GFAP) and ubiquitin C-terminal hydrolase L1 (UCH-L1)—found in whole-blood samples for diagnosing intracranial injuries in patients post-traumatic brain injury (TBI). Conducted across various medical centers in the United States, this prospective study was designed to assess the effectiveness of these biomarkers as diagnostic tools when evaluated alongside patients’ head computed tomography (CT) results.
Participants included adults who presented at emergency departments subsequent to sustaining TBIs, categorizing them based on the severity of their injuries. The focus was placed on measuring the concentrations of GFAP and UCH-L1 in blood samples collected shortly after injury. These measurements were then correlated with the imaging findings from head CT scans to establish a relationship between biomarker levels and the presence of intracranial abnormalities.
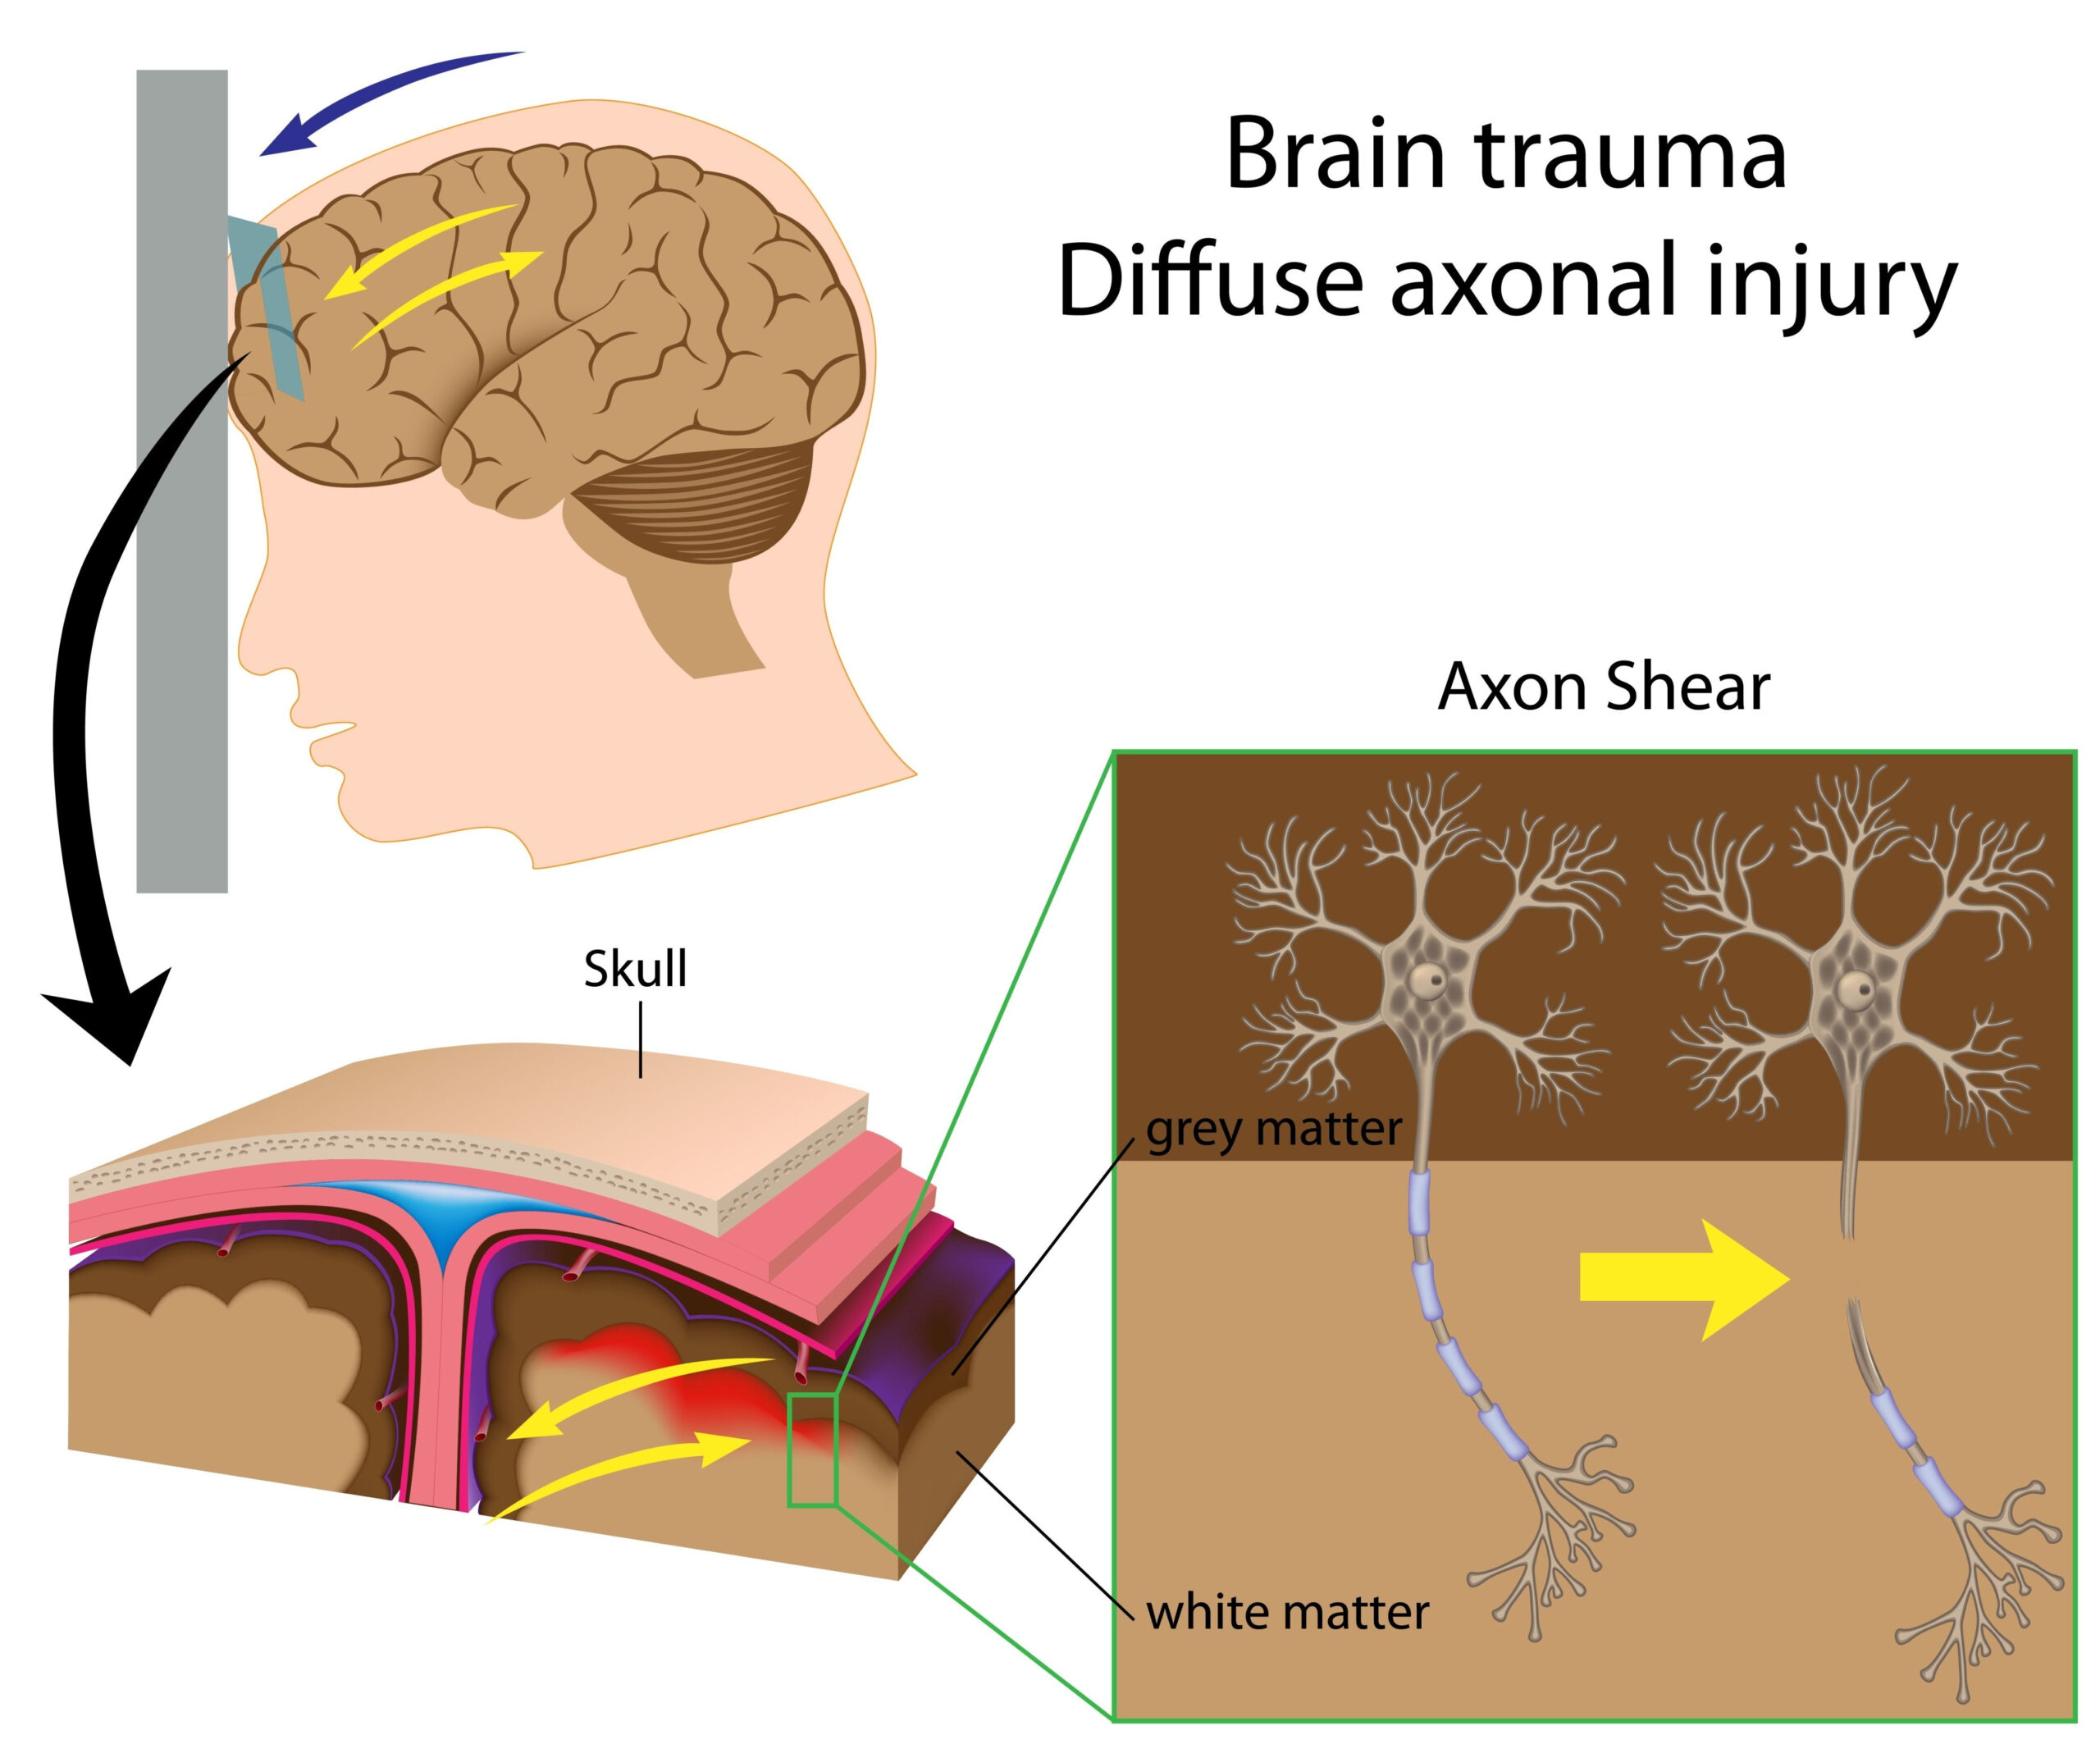
The rationale behind using GFAP and UCH-L1 stems from their roles as neurological biomarkers that indicate brain damage. GFAP is known to be a marker of astrocytic activity, suggesting glial cell response following injury, whereas UCH-L1 reflects neuronal cell damage. Observations from earlier studies indicated their potential in aiding the decision-making process regarding the need for imaging studies in TBI cases, thereby possibly reducing unnecessary radiation exposure and facilitating timely clinical interventions.
The study’s design aimed to clarify the diagnostic value of these biomarkers, potentially contributing to improved triage and management strategies in emergency medicine. By leveraging whole-blood analysis, the researchers sought to provide an accessible method for determining brain injury severity, thus optimizing patient care pathways in acute settings.
Methodology
The study employed a rigorous prospective design involving multiple medical centers across the United States, enrolling participants who were adults presenting to emergency departments after experiencing traumatic brain injuries. The selection criteria included individuals with a recognized history of TBI, and participants were stratified based on injury severity, utilizing the Glasgow Coma Scale (GCS) for assessment. This stratification enabled a comprehensive evaluation of how GFAP and UCH-L1 levels varied across different injury severities.
Blood samples were collected from each participant soon after arrival at the emergency department, ideally within hours of the injury. The biomarker levels of GFAP and UCH-L1 were then quantified using advanced enzyme-linked immunosorbent assay (ELISA) technology, which allows for sensitive detection of specific proteins in biological samples. This method ensures high accuracy and reliability of results, providing a solid basis for correlating biomarker concentrations with clinical outcomes.
Simultaneously, participants underwent head CT scans, which served as the standard reference for diagnosing intracranial injuries. Imaging was conducted with established protocols to maintain consistency across study sites, ensuring that findings were comparable. After obtaining the CT results, these images were reviewed by radiologists who were blinded to the biomarker data, thus eliminating bias in interpreting the diagnostic outcomes.
Subsequently, statistical analyses were conducted to elucidate the relationship between biomarker levels and CT findings. This included calculations of sensitivity, specificity, positive predictive value, and negative predictive value for GFAP and UCH-L1, both independently and in combination. Logistic regression models were also employed to assess the ability of these biomarkers to predict the presence of significant intracranial injuries, adjusting for confounding factors such as age, sex, and injury mechanism.
The methodology further encompassed monitoring of adverse events and tracking clinical outcomes for the participants, allowing researchers to examine the impact of biomarker-guided decision-making on patient management. Follow-up assessments were planned to ensure a thorough understanding of long-term recovery trajectories linked to the initial biomarker readings and CT findings.
Key Findings
The study revealed significant insights into the diagnostic capabilities of GFAP and UCH-L1 as biomarkers for detecting intracranial injuries following traumatic brain injury. Analysis of the collected data indicated that both biomarkers exhibited strong correlations with head CT findings, thereby reinforcing their potential utility in clinical practice.
Results demonstrated that elevated levels of GFAP were associated with the presence of intracranial hemorrhages and contusions. The sensitivity of GFAP for detecting significant head injuries was reported at approximately 88%. In contrast, UCH-L1 showed a slightly lower sensitivity but highlighted a vital role in indicating neuronal damage specifically. When assessed alone, UCH-L1 presented a sensitivity of around 80% in relation to the imaging findings. However, when both biomarkers were evaluated together, the sensitivity improved significantly, reaching over 90%. This complementary effect underscores the potential of utilizing a panel of biomarkers for enhanced diagnostic accuracy.
Specificity findings were equally notable. GFAP demonstrated a specificity of 85% when identifying intracranial injuries, while UCH-L1 exhibited a specificity of 81%. Again, the combination of both biomarkers increased the specificity to about 87%, suggesting that using both can minimize false positives in assessing injury severity.
Logistic regression analysis indicated that both GFAP and UCH-L1 were independently predictive of the presence of significant intracranial injuries, even when controlling for demographic factors such as age and sex. This reinforces the robustness of these biomarkers in differentiating between patients who require immediate surgical intervention and those who might be managed conservatively.
Furthermore, adverse events related to biomarker testing were monitored throughout the study. There were no significant complications noted in relation to blood sample collection or testing, reassuring clinicians regarding the safety of implementing this diagnostic modality in emergency settings.
Follow-up evaluations demonstrated a promising association between initial biomarker levels and long-term recovery outcomes. Participants with higher GFAP and UCH-L1 levels tended to show more severe and prolonged recovery trajectories, suggesting that initial biomarker readings may aid in predicting long-term rehabilitation needs.
Overall, these findings denote a significant advancement in the approach to managing traumatic brain injuries, potentially allowing healthcare providers to make more informed decisions with regard to imaging and treatment pathways—all while minimizing unnecessary radiation exposure. The integration of GFAP and UCH-L1 testing could become a transformative element in the acute care of TBI patients, warranting further exploration and validation in larger, multicenter studies.
Clinical Implications
The findings from this study have far-reaching implications for the clinical management of traumatic brain injury (TBI). The demonstrated efficacy of GFAP and UCH-L1 as biomarkers for intracranial injury suggests a paradigm shift in how emergency departments assess and manage patients presenting with suspected TBIs. By integrating these biomarkers into routine clinical practice, healthcare professionals could significantly enhance diagnostic accuracy and expedite treatment protocols.
One critical implication of this research lies in the potential reduction of unnecessary head CT scans. Traditionally, the decision to perform imaging has relied heavily on clinical assessment and established protocols, often leading to overutilization of CT scans, which expose patients to ionizing radiation. By employing GFAP and UCH-L1 testing, clinicians could more accurately stratify patients based on their actual risk of significant intracranial injuries. This approach not only preserves patient safety by minimizing radiation exposure but also optimizes resource usage within emergency departments.
Moreover, the ability of these biomarkers to predict the severity of brain injuries offers a proactive tool for clinical decision-making. For instance, patients with elevated GFAP levels, indicating the likelihood of contusions or hemorrhages, may require more intensive monitoring or immediate surgical intervention. In contrast, those with lower biomarker levels could potentially be managed more conservatively, thereby improving patient flow through emergency care systems.
The complementary nature of GFAP and UCH-L1 further enriches this strategy. Utilizing a dual biomarker approach enhances sensitivity and specificity, allowing healthcare providers to make more informed decisions with lower rates of false diagnoses. As a result, treatment protocols could be tailored more effectively to individual patient profiles, leading to better health outcomes.
In the context of patient management, the study’s results advocate for the incorporation of biomarker data into existing clinical pathways. This could include the development of guidelines that define thresholds for follow-up imaging based on GFAP and UCH-L1 levels. Such guidelines would aid in standardizing practices across various healthcare settings, ensuring that all patients receive care founded upon the latest evidence-based strategies.
Additionally, understanding the long-term implications of initial biomarker readings can improve patient prognostication. As the research indicates that higher levels of these biomarkers correlate with prolonged recovery trajectories, clinicians can apply this knowledge to personalize rehabilitation plans. Early identification of patients likely to encounter significant recovery challenges allows for timely intervention, optimizing rehabilitation resources and support services.
The potential economic benefits of implementing biomarker testing are also noteworthy. Reductions in unnecessary imaging and improved triage of patients may alleviate some financial burdens associated with emergency care while also enhancing overall patient satisfaction through more streamlined treatment pathways.
In conclusion, the integration of GFAP and UCH-L1 testing into clinical practice not only holds promise for improving diagnostic accuracy and patient outcomes after TBI but also supports a more rational, evidence-based approach to emergency medicine. Continued research and validation of these biomarkers in larger cohorts will be essential in solidifying their role in revolutionizing TBI management.