Clinical Presentation
In cases of chronic hyponatremia following mild traumatic brain injury, the clinical presentation can vary widely among individuals, but certain symptoms often emerge as notable indicators. Patients may initially report headaches, confusion, or alterations in mental status, which can be subtle and easily attributed to other post-injury symptoms. One of the hallmark signs of hyponatremia is a decline in cognitive function; individuals may experience difficulties with attention, memory, and decision-making. In some situations, this can escalate to more severe neurological symptoms such as seizures or even loss of consciousness, particularly if sodium levels drop dramatically.
Additionally, physical manifestations such as nausea, vomiting, and fatigue are commonly observed. The presence of these symptoms may lead to misdiagnosis or delay in treatment, as they closely resemble other conditions that can occur after a traumatic brain injury. Patients may also exhibit signs of fluid overload, including peripheral edema, hypertension, and in some instances, respiratory distress, due to the excess fluid associated with the syndrome of inappropriate antidiuretic hormone secretion (SIADH).
Furthermore, the timing of symptom onset can also play a critical role in the clinical picture. In many cases, symptoms of hyponatremia can arise weeks to months following the initial injury, which makes it imperative for clinicians to maintain a high index of suspicion when evaluating patients with a recent history of mild traumatic brain injury. Laboratory tests typically reveal a significantly low serum sodium concentration, which, when correlated with the clinical signs, may aid in establishing the diagnosis of SIADH secondary to the injury. Patient histories often reveal a lack of signs of dehydration or other causes of hyponatremia, further supporting the diagnosis. Collectively, the amalgamation of cognitive, physical, and laboratory findings provides a comprehensive understanding of the clinical presentation observed in these patients.
Pathophysiology of SIADH
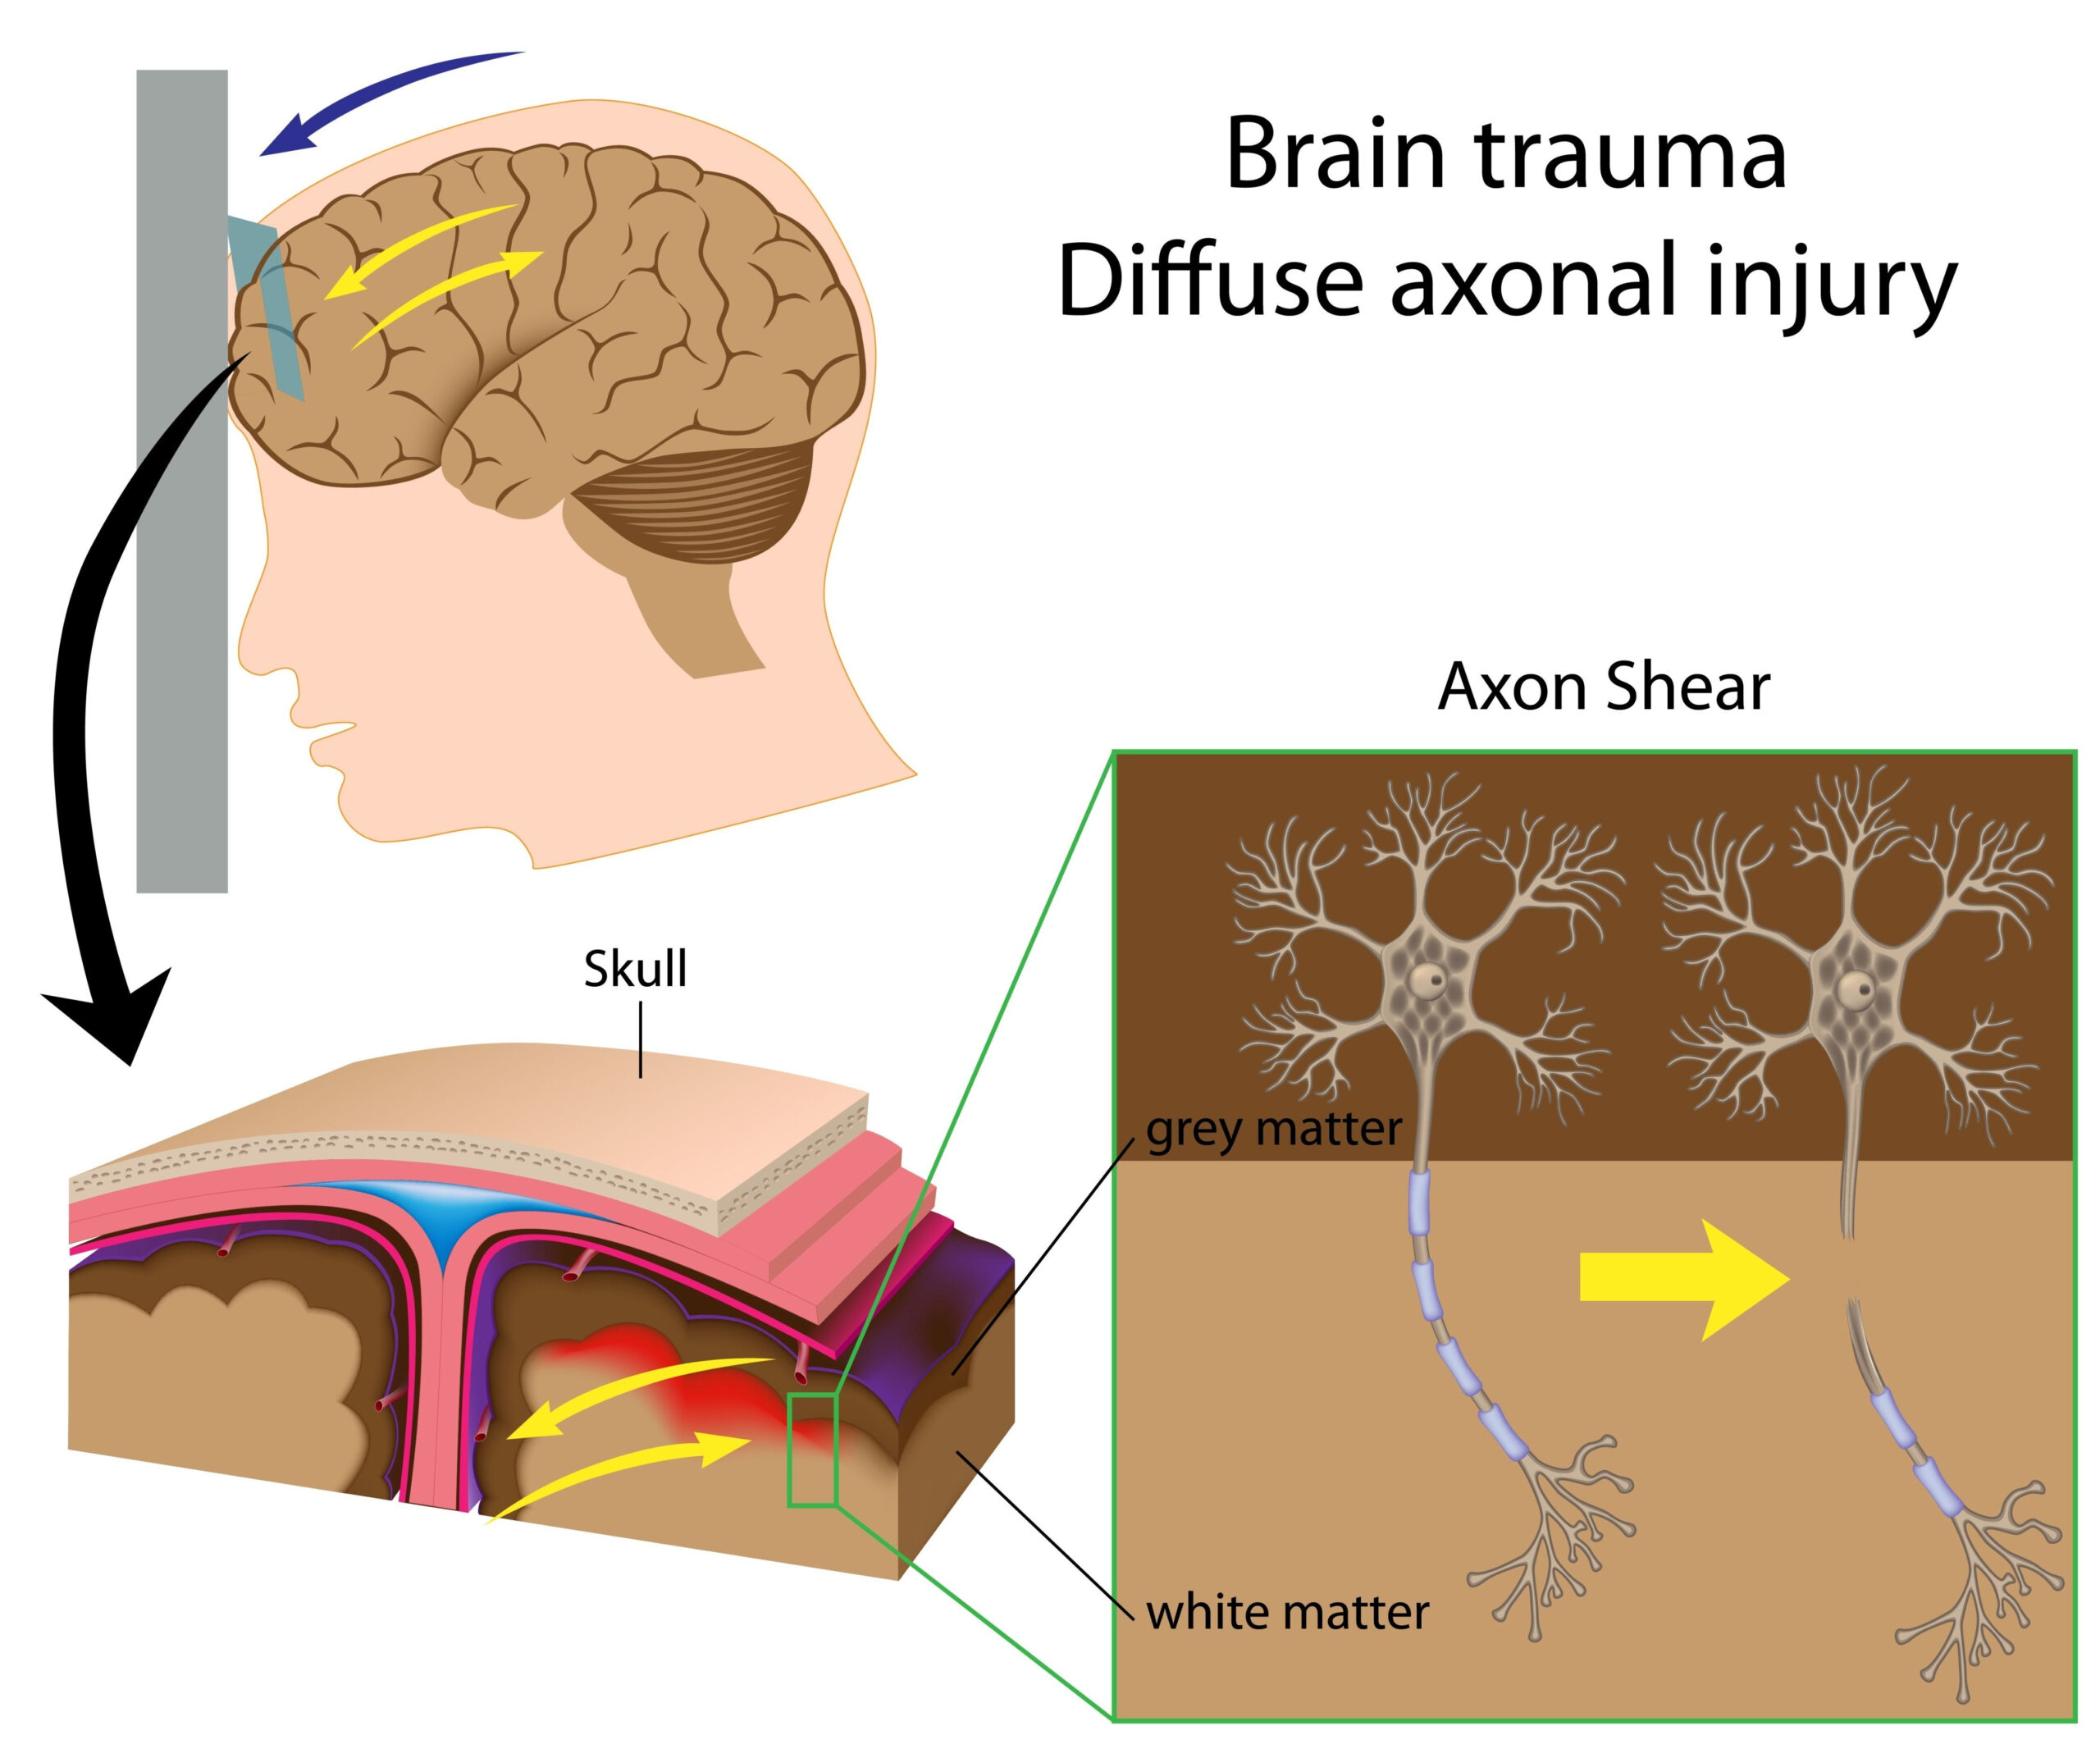
The pathophysiology of the syndrome of inappropriate antidiuretic hormone secretion (SIADH) is complex and multifaceted, particularly in the context of chronic hyponatremia following mild traumatic brain injury (TBI). SIADH is characterized by the excessive release of antidiuretic hormone (ADH), also known as vasopressin, from the posterior pituitary gland, which leads to an inappropriate retention of water by the kidneys. This retention results in dilutional hyponatremia, as the excess water decreases serum sodium concentration.
Following a mild TBI, several mechanisms can trigger the dysregulation of ADH secretion. Firstly, direct trauma to the hypothalamus, where the regulation of ADH occurs, can impair the area responsible for the balance of fluid and electrolytes. This disruption may lead to an overproduction of ADH, as the normal feedback mechanisms that would typically reduce ADH levels in response to increased blood volume or decreased plasma osmolality are compromised. Furthermore, the inflammatory response elicited by the injury can also contribute to changes in ADH regulation, with cytokines and other mediators potentially stimulating its secretion.
Beyond direct effects of brain injury on ADH release, other neuroendocrine responses may also play significant roles. For instance, stress-induced responses can amplify the secretion of ADH, caused by various bodily stressors during the acute stages following an injury. Additionally, conditions such as pain and anxiety often associated with TBI can further promote the release of vasopressin. Furthermore, the presence of certain ‘extra-CNS’ factors, such as medications or electrolyte imbalances, may also influence the SIADH’s development in these patients.
The resultant water retention leads to a dilutional effect on sodium levels, with serum sodium typically falling below 135 mmol/L, which may cause a variety of neurological symptoms due to cellular swelling in the brain. This cellular effect arises because neurons are particularly sensitive to changes in osmolarity. In hyponatremic conditions, they may allow excess water to enter the cells, leading to cerebral edema, which can further exacerbate neurological manifestations and contribute to a spiral of dysfunction.
It is also notable that certain neurochemical changes in response to TBI can affect osmotic regulation. Alterations in brain osmoregulation and the balance between excitatory and inhibitory neurotransmitters, potentially influenced by the injury itself, can compound the inappropriate secretion of ADH. The persistence of these mechanisms long after the initial injury is what characterizes the chronic form of SIADH observed in some patients, making the management of fluid balance and serum sodium levels a key aspect of long-term recovery and treatment.
Diagnosis and Management
Long-Term Outcomes
The long-term outcomes for patients with chronic hyponatremia following mild traumatic brain injury (TBI) can be quite variable, influenced by factors such as the severity and timing of the injury, the efficacy of treatment strategies, and individual patient health characteristics. Understanding these outcomes is crucial for both patient management and rehabilitation strategies.
Patients may experience persistent cognitive deficits that can affect their quality of life. While many individuals see improvements over time, others may suffer from long-lasting cognitive impairments, including difficulties in memory, attention, and executive function. These deficits often interfere with daily activities and social interactions, leading to a significant psychosocial burden. The cognitive challenges may be compounded by mood disorders, such as anxiety and depression, which are not uncommon among individuals dealing with the aftermath of TBI and chronic hyponatremia.
Neuropsychological assessments have shown that deficits in executive function can significantly impact rehabilitation potential, as these cognitive skills are essential for planning, decision-making, and problem-solving. Moreover, the ongoing neurological implications of prolonged hyponatremia, including the risk of developing seizures, further complicate the clinical picture. As a result, patients may demonstrate an ongoing need for multidisciplinary interventions that include medical management, neuropsychiatric support, and occupational therapy to facilitate reintegration into normal life.
From a physiological perspective, the implications of chronic hyponatremia extend beyond mere cognitive deficits. Long-term effects on cardiovascular health, renal function, and bone density have been noted. For instance, persistent low sodium levels can lead to issues such as increased water retention and exacerbation of hypertension, which may predispose patients to cardiovascular conditions later in life. Furthermore, chronic dilutional hyponatremia can adversely affect bone metabolism, leading to a higher risk of fractures and osteoporosis.
Management strategies focus on correcting hyponatremia and adjusting the underlying causes, primarily addressing the inappropriate secretion of antidiuretic hormone. Sodium replacement therapy, fluid restriction, and the use of medications such as vasopressin receptor antagonists may offer significant relief and play a role in stabilizing sodium levels. However, careful monitoring is essential to prevent rapid shifts in serum sodium, which can precipitate osmotic demyelination syndrome, a serious condition that can lead to neurological complications.
Ultimately, successful management of chronic hyponatremia and its cognitive consequences hinges on a collaborative approach that addresses the medical, psychological, and social facets of recovery. Long-term follow-up with healthcare providers is essential to adapt treatment plans as necessary and to provide ongoing support as patients navigate the complexities of living with the aftermath of mild TBI and its sequelae.
Long-Term Outcomes
The long-term outcomes for individuals experiencing chronic hyponatremia following mild traumatic brain injury (TBI) can exhibit a diverse range of challenges and adaptations, largely determined by the specifics of each case, including the individual’s health background, the nature of the injury, and the interventions employed. It is critical to recognize how varying degrees of cognitive, psychological, and physiological effects can shape the recovery trajectory and overall quality of life for these patients.
Many individuals may face enduring cognitive challenges that manifest as deficits in memory, attention, and executive functioning abilities. While some patients may observe gradual improvements, others may encounter persistent areas of difficulty that interfere significantly with daily life, work, and social engagements. Cognitive impairments of this nature often necessitate extensive rehabilitation efforts and may require ongoing support systems to manage and adapt to these changes. Additionally, mood disorders, including anxiety and depression, frequently complicate recovery after TBI and can further diminish the psychosocial well-being of affected individuals.
Neuropsychological evaluations have corroborated that difficulties in executive function, which manage tasks such as planning, reasoning, and multitasking, can exert a marked influence on rehabilitation effectiveness. The repercussions of prolonged untreated hyponatremia can introduce further neurological risks, such as an increased likelihood of seizures, which significantly impact daily functioning and safety. Consequently, a multidisciplinary approach to treatment that incorporates medical management, psychological provision, and supportive therapies becomes indispensable for the thorough rehabilitation of these patients.
From a physiological standpoint, the ramifications of chronic hyponatremia extend beyond cognitive effects, introducing potential long-term implications for cardiovascular, renal, and bone health. Persistent hyponatremia can engender complications such as fluid overload and hypertension, leading to an increased risk of cardiovascular pathologies as patients age. Additionally, chronic low sodium levels may interfere with bone health, promoting conditions like osteoporosis and elevating the risk of fractures later in life, a concern particularly important for younger adults who wish to maintain an active lifestyle.
Addressing chronic hyponatremia involves not only the correction of sodium levels but also identifying and managing the underlying causes of inappropriate antidiuretic hormone secretion. Treatment strategies may include sodium supplementation, fluid restrictions, and medications such as vasopressin receptor antagonists that help normalize sodium levels. Vigilance is crucial during treatment, as rapid changes in serum sodium can result in serious neurological consequences, including osmotic demyelination syndrome.
The intricate management of chronic hyponatremia and its multifaceted cognitive repercussions requires a concerted effort among healthcare providers to ensure that medical, psychological, and social needs are all met. Ongoing monitoring and support are vital to adapt treatment plans over time and to assist patients in navigating the complex challenges associated with the aftermath of mild TBI and chronic hyponatremia. Ultimately, establishing a long-term support network can play an essential role in enhancing the quality of life and functional independence of these individuals.