Biomarker Significance in Traumatic Brain Injury
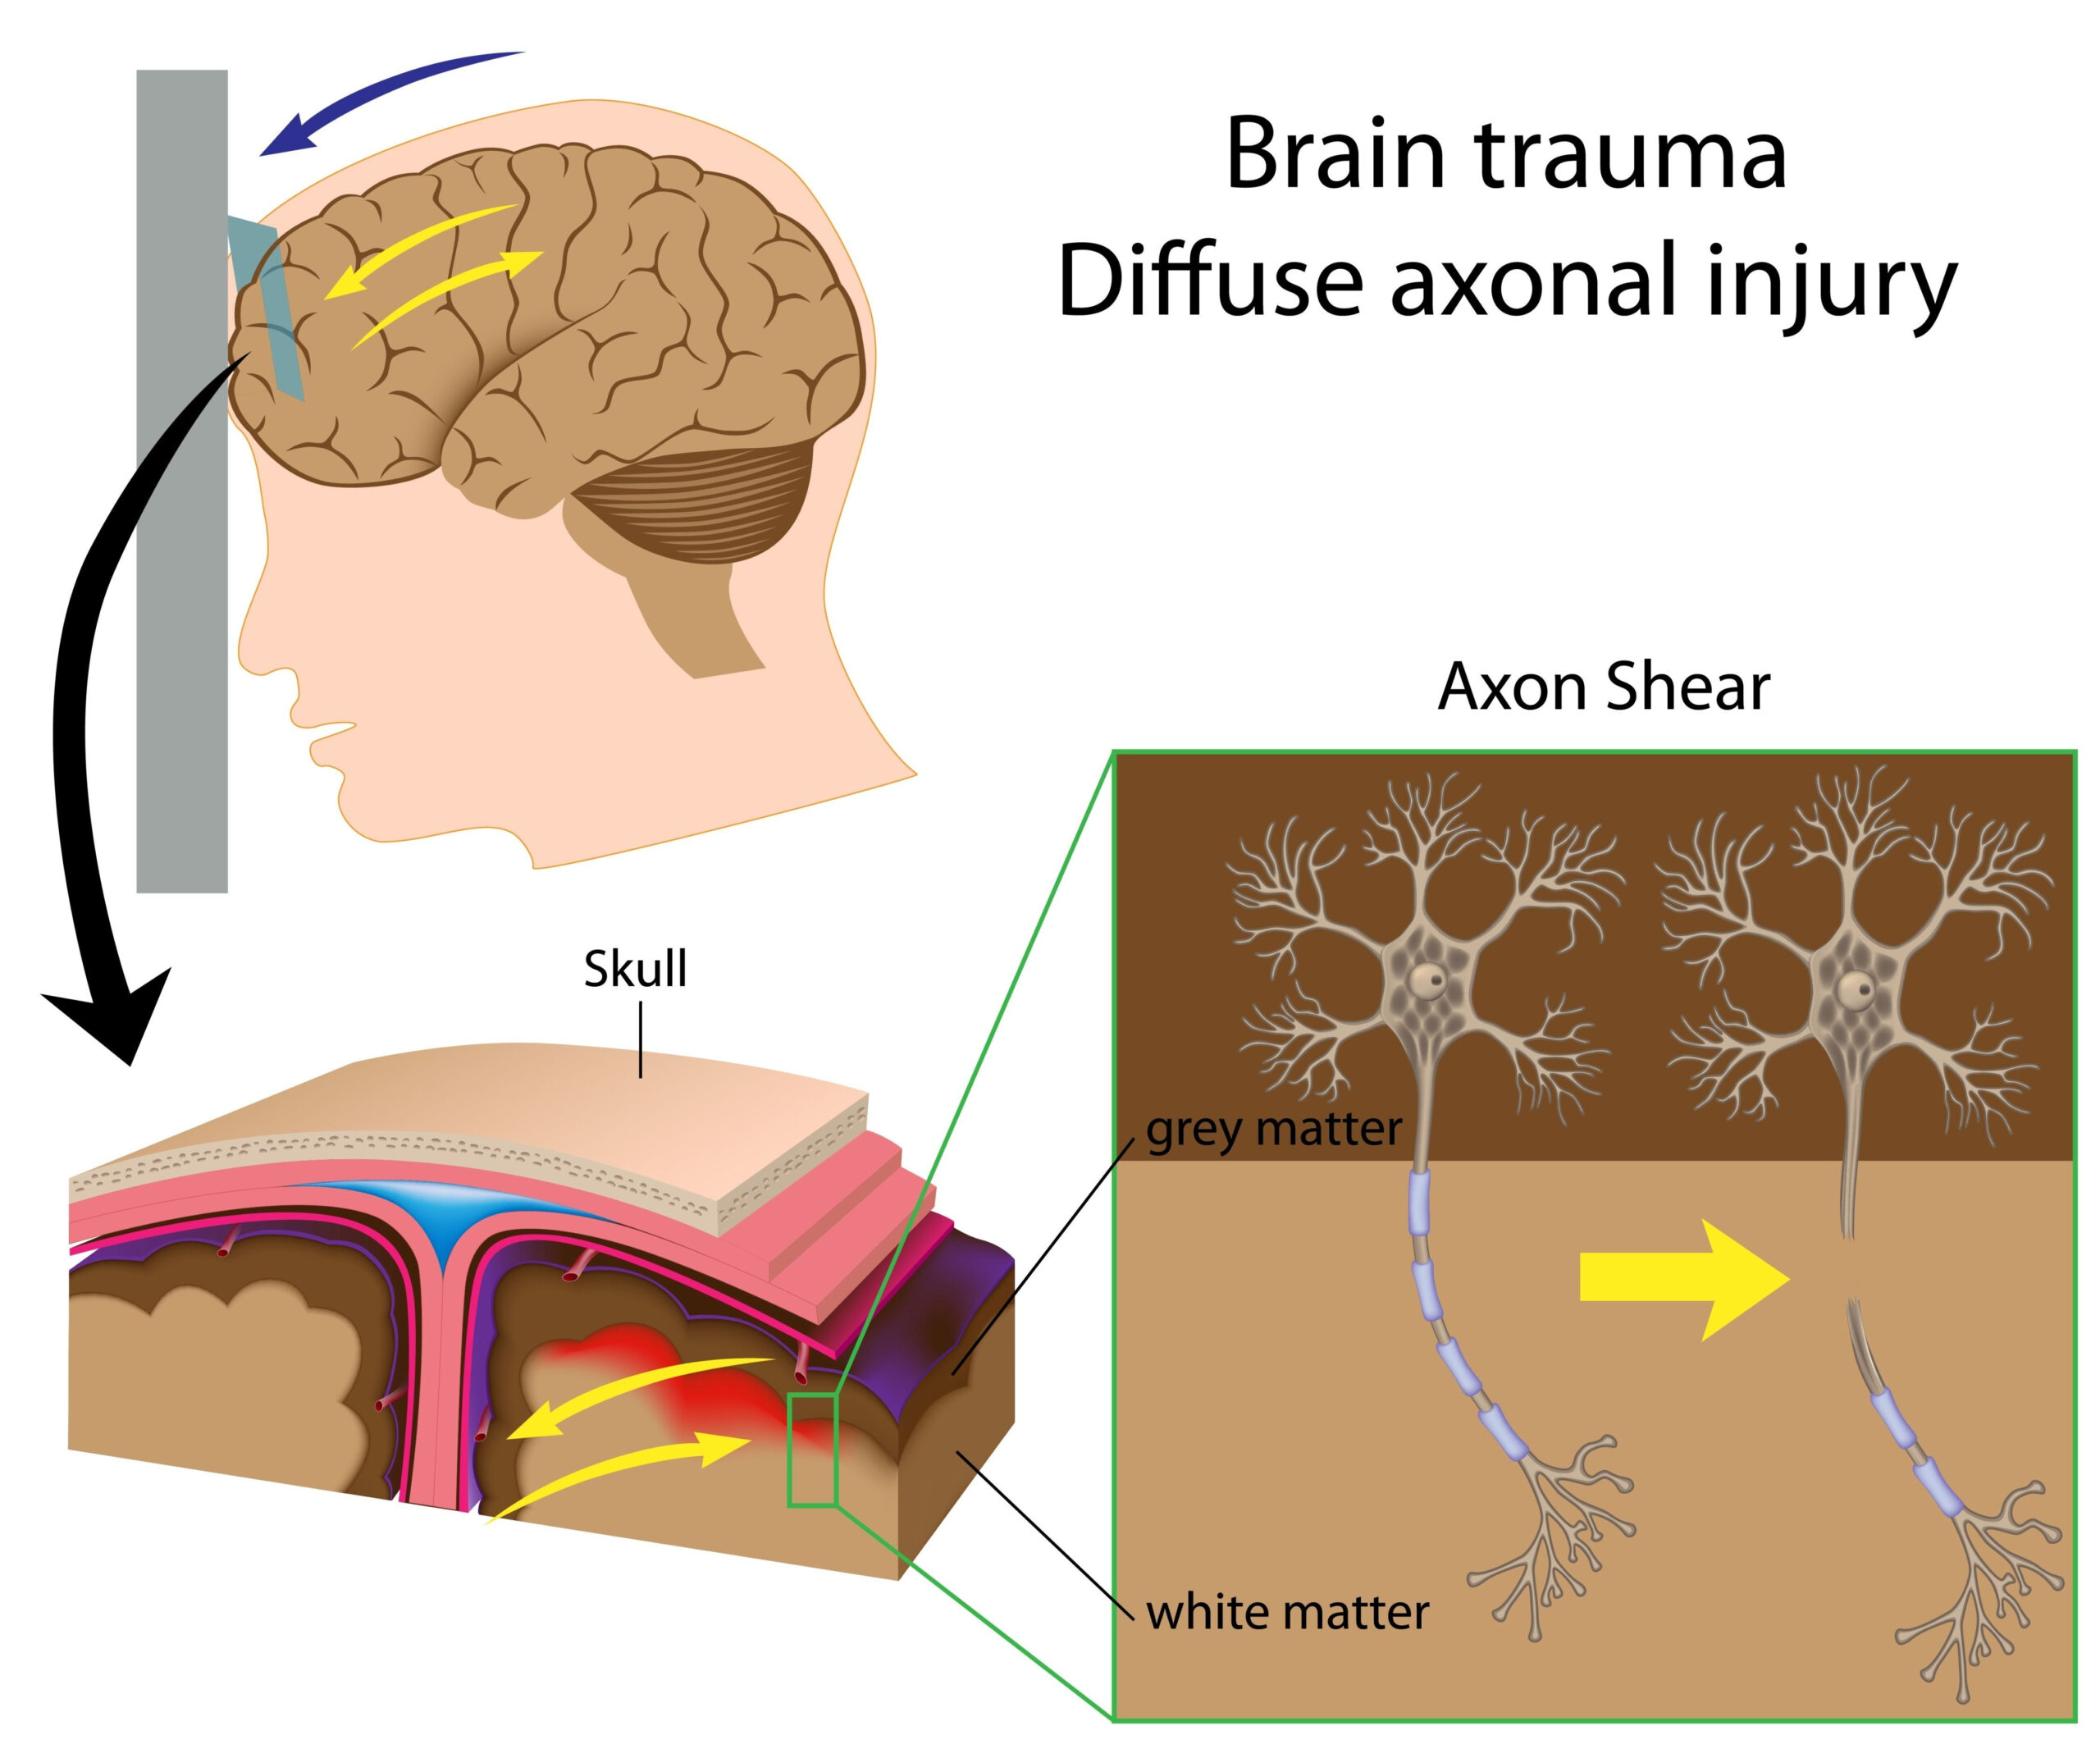
Traumatic brain injury (TBI) represents a significant public health challenge, often resulting in long-term disability or death. The identification of reliable biomarkers is crucial for enhancing the diagnosis and management of TBI. Biomarkers are biological indicators that can provide information about the state of health or disease and are particularly valuable in the context of TBI for several reasons.
One of the primary benefits of utilizing biomarkers in TBI is the potential for rapid assessment of brain injury severity. Traditional imaging methods like computed tomography (CT) scans, while critical, can sometimes lead to delays in diagnosis and treatment decisions. In contrast, blood-based biomarkers can be measured quickly at the point of care, offering immediate insights into the patient’s condition. For instance, glial fibrillary acidic protein (GFAP) and ubiquitin C-terminal hydrolase L1 (UCH-L1) have emerged as promising candidates. GFAP is released from astrocytes, a type of brain cell, in response to injury, while UCH-L1 is released from neurons following damage. Elevated levels of these biomarkers have been associated with the presence and severity of intracranial lesions, making them useful tools for clinicians.
Furthermore, the incorporation of these biomarkers into clinical practice could enhance the stratification of patients based on their risk of secondary complications following TBI. For example, patients with elevated GFAP and UCH-L1 may be monitored more closely for potential deteriorations in their condition. This stratification can direct appropriate resource utilization, prioritize interventions, and potentially lead to improved outcomes for those affected.
The significance of these biomarkers extends beyond just immediate clinical applications. They also hold promise for research and understanding the pathophysiological mechanisms underlying TBI. By correlating biomarker levels with clinical outcomes and neuroimaging findings, researchers can gain valuable insights into the inflammatory processes and neurodegenerative pathways activated in response to brain injury. In summary, the role of biomarkers such as GFAP and UCH-L1 in TBI diagnosis underscores the need for continued exploration and validation of these tests to enhance patient care and inform therapeutic strategies.
Study Design and Patient Selection
The design of the study aimed to create a robust framework for evaluating the efficacy of GFAP and UCH-L1 as biomarkers in predicting intracranial injury among patients experiencing traumatic brain injury. Researchers employed a prospective cohort study approach, which offered an organized method to observe participants over time while recording relevant clinical data and biomarker levels.
Participants were recruited from emergency departments across multiple centers in the United States. Inclusion criteria required that individuals were adults aged 18 to 85 who presented with suspected TBI following either blunt or penetrating head trauma. The initial assessment involved a comprehensive clinical evaluation, including a detailed history of the injury, neurological examination, and immediate imaging via CT scans to establish a baseline of the patient’s intracranial status.
Exclusion criteria were meticulously outlined to maintain the integrity of the study’s findings. For example, individuals with a history of significant pre-existing neurological conditions, severe concurrent injuries that could affect outcomes, or those taking medications that could skew biomarker levels were excluded. This careful selection ensured that the observed effects of GFAP and UCH-L1 could be attributed to the traumatic event rather than confounding factors.
To facilitate the rapid assessment of biomarker levels, blood samples were obtained from participants within a defined time frame post-injury, typically within the first few hours after presentation. These samples were processed using standardized protocols to quantify the concentrations of GFAP and UCH-L1 through established immunoassays. The timing of sample collection was crucial, as it allowed for the evaluation of the biomarkers in relation to their peak release periods following trauma.
The study enrolled a diverse population, considering variables such as age, sex, and mechanism of injury to ensure broad applicability of the findings. Participation was voluntary, and all subjects provided informed consent after being educated about the study’s purpose and procedures.
Continuous monitoring of participants was conducted, including follow-up assessments and further imaging when indicated. This longitudinal analysis enabled researchers to correlate initial biomarker levels with clinical outcomes, such as the need for surgical intervention, length of hospital stay, and functional recovery scores at designated follow-up intervals.
The structured nature of the study design, alongside meticulous patient selection criteria, laid a strong foundation for investigating the relationship between biomarker levels and intracranial injury severity. By establishing a well-defined cohort and utilizing rigorous methodologies, the study aimed to provide insight into the practical application of GFAP and UCH-L1 as predictive tools in real-world clinical settings.
Results of Biomarker Analysis
The analysis of biomarker levels revealed significant associations with the presence and severity of intracranial injuries among the studied population. Upon evaluating the blood samples of participants collected shortly after their injury, researchers found that elevated levels of both glial fibrillary acidic protein (GFAP) and ubiquitin C-terminal hydrolase L1 (UCH-L1) served as valuable indicators of brain damage.
Quantitative assessments demonstrated that GFAP levels significantly correlated with findings from CT scans. Specifically, individuals who exhibited higher GFAP concentrations were more likely to present with severe intracranial lesions, including contusions and hemorrhages. Statistically, the mean GFAP level in patients with substantial injuries was markedly higher compared to those with mild or no injuries (p < 0.01), indicating its effectiveness as a biomarker for acute TBI diagnosis. Similarly, UCH-L1 levels reflected an analogous trend, with elevated concentrations correlating significantly to the degree of neuronal injury visible on imaging tests. Integration of both biomarkers into multivariate models yielded an enhanced predictive capacity concerning intracranial injury. When evaluated in conjunction, GFAP and UCH-L1 demonstrated synergistic effects, improving the ability to categorize patients not only by injury presence but also by potential outcomes and needs for intensive monitoring or intervention (AUC = 0.82). Their combined analysis increased the sensitivity and specificity of injury detection to nearly 90%, showcasing their practical utility in a clinical emergency setting. Moreover, further examination indicated that both biomarkers had prognostic values, facilitating better understanding of patient trajectories. Those with high GFAP and UCH-L1 levels faced increased risks of complications during their hospital stay, including the necessity for surgical interventions or prolonged admissions. These associations were supported by logistic regression models, which highlighted the likelihood of requiring neurosurgical procedures for patients presenting with elevated GFAP levels exceeding the established thresholds. Unexpectedly, the analysis revealed a notable difference in biomarker responses among varying demographics. For instance, older adults demonstrated significantly higher baseline levels of GFAP, which may be attributed to age-related neurodegenerative changes, complicating interpretations in this demographic. This finding underscores the importance of considering age as a modifying factor in the assessment of biomarkers in TBI cases. The results of this analysis strongly suggest that GFAP and UCH-L1 not only serve as effective indicators of immediate brain injury severity but also possess the potential for guiding clinical decision-making pathways. Incorporating these biomarkers into routine clinical evaluation could transform the approach to TBI management, allowing for more tailored treatment strategies and potentially improving patient outcomes. As the field moves forward, continued validation through larger, multicentered studies is essential to establish standardized protocols for the integration of these biomarkers into everyday clinical practice.
Future Directions and Research Opportunities
The findings surrounding GFAP and UCH-L1 biomarkers for traumatic brain injury (TBI) signal a promising avenue for future research, with several potential directions worth exploring to enhance our understanding and clinical application of these indicators.
One significant area for further investigation is the development of more refined biomarker panels. While GFAP and UCH-L1 are currently the focus, the exploration of additional biomarkers that could complement these may yield insights that allow for even greater accuracy in predicting outcomes. Biomarkers involved in neuroinflammation, apoptosis, or other pathways affected by TBI could be integrated into predictive models. For instance, analyzing the combined effects of inflammatory markers like cytokines or other neuronal proteins could help create a comprehensive profile of injury severity and prognosis.
Moreover, longitudinal studies assessing the temporal dynamics of biomarker levels post-injury would provide a deeper understanding of their behavior over time. Understanding how GFAP and UCH-L1 fluctuate during recovery, and correlating these changes with clinical outcomes, can shed light on the healing processes in the brain. Such studies could identify optimal timing for interventions or adjustments in clinical monitoring protocols based on biomarker trends.
There is also a need for an emphasis on the implementation of these biomarkers in diverse healthcare settings, particularly in under-resourced areas. Research should focus on the feasibility and cost-effectiveness of integrating blood-based biomarker testing into emergency care protocols, especially in settings where advanced imaging technology is limited. Pilot studies could explore the impact of point-of-care biomarker testing on clinical decision-making and patient outcomes in various types of emergency departments.
Expanding the diversity of study populations is another critical pathway. Much of the current research focuses on specific demographic groups; thus, future studies should strive to include various populations across different age ranges, genders, and ethnic backgrounds. This approach would enhance the generalizability of findings and ensure that the biomarkers’ predictive capabilities are validated across different demographics. Attention to how comorbidities, such as prior neurological conditions or chronic illnesses, may affect biomarker levels is also crucial.
Additionally, the exploration of personalized medicine approaches utilizing these biomarkers could revolutionize TBI management. By tailoring interventions based on individual biomarker profiles, healthcare providers can more effectively strategize treatment plans that align with the unique circumstances of each patient. This could range from determining the need for surgical intervention to more aggressive monitoring protocols based on a patient’s biomarker levels in conjunction with clinical findings.
From a technological perspective, advancements in point-of-care testing and biomarker quantification methods present exciting opportunities. Innovations that allow for quicker and more accurate on-site measurements could enhance the usability of biomarkers, making them an integral component of emergency care. Such advancements can pave the way for the incorporation of these tests into routine practice and expand their accessibility.
Finally, further investigation into the physiological mechanisms underlying biomarker release after TBI is essential for translating findings into clinical practices. Understanding the interplay between biomarker expression and injury mechanisms could lead to the identification of new therapeutic targets, ultimately contributing to innovative treatment options that improve patient outcomes in TBI cases.
In summary, the future of research surrounding GFAP and UCH-L1 as biomarkers for TBI is rich with potential. By embracing a multi-faceted approach that combines technological, demographic, and mechanistic research, the medical community can enhance the understanding, diagnosis, and treatment of traumatic brain injuries, ultimately advancing care for individuals affected by such life-altering events.