Study Overview
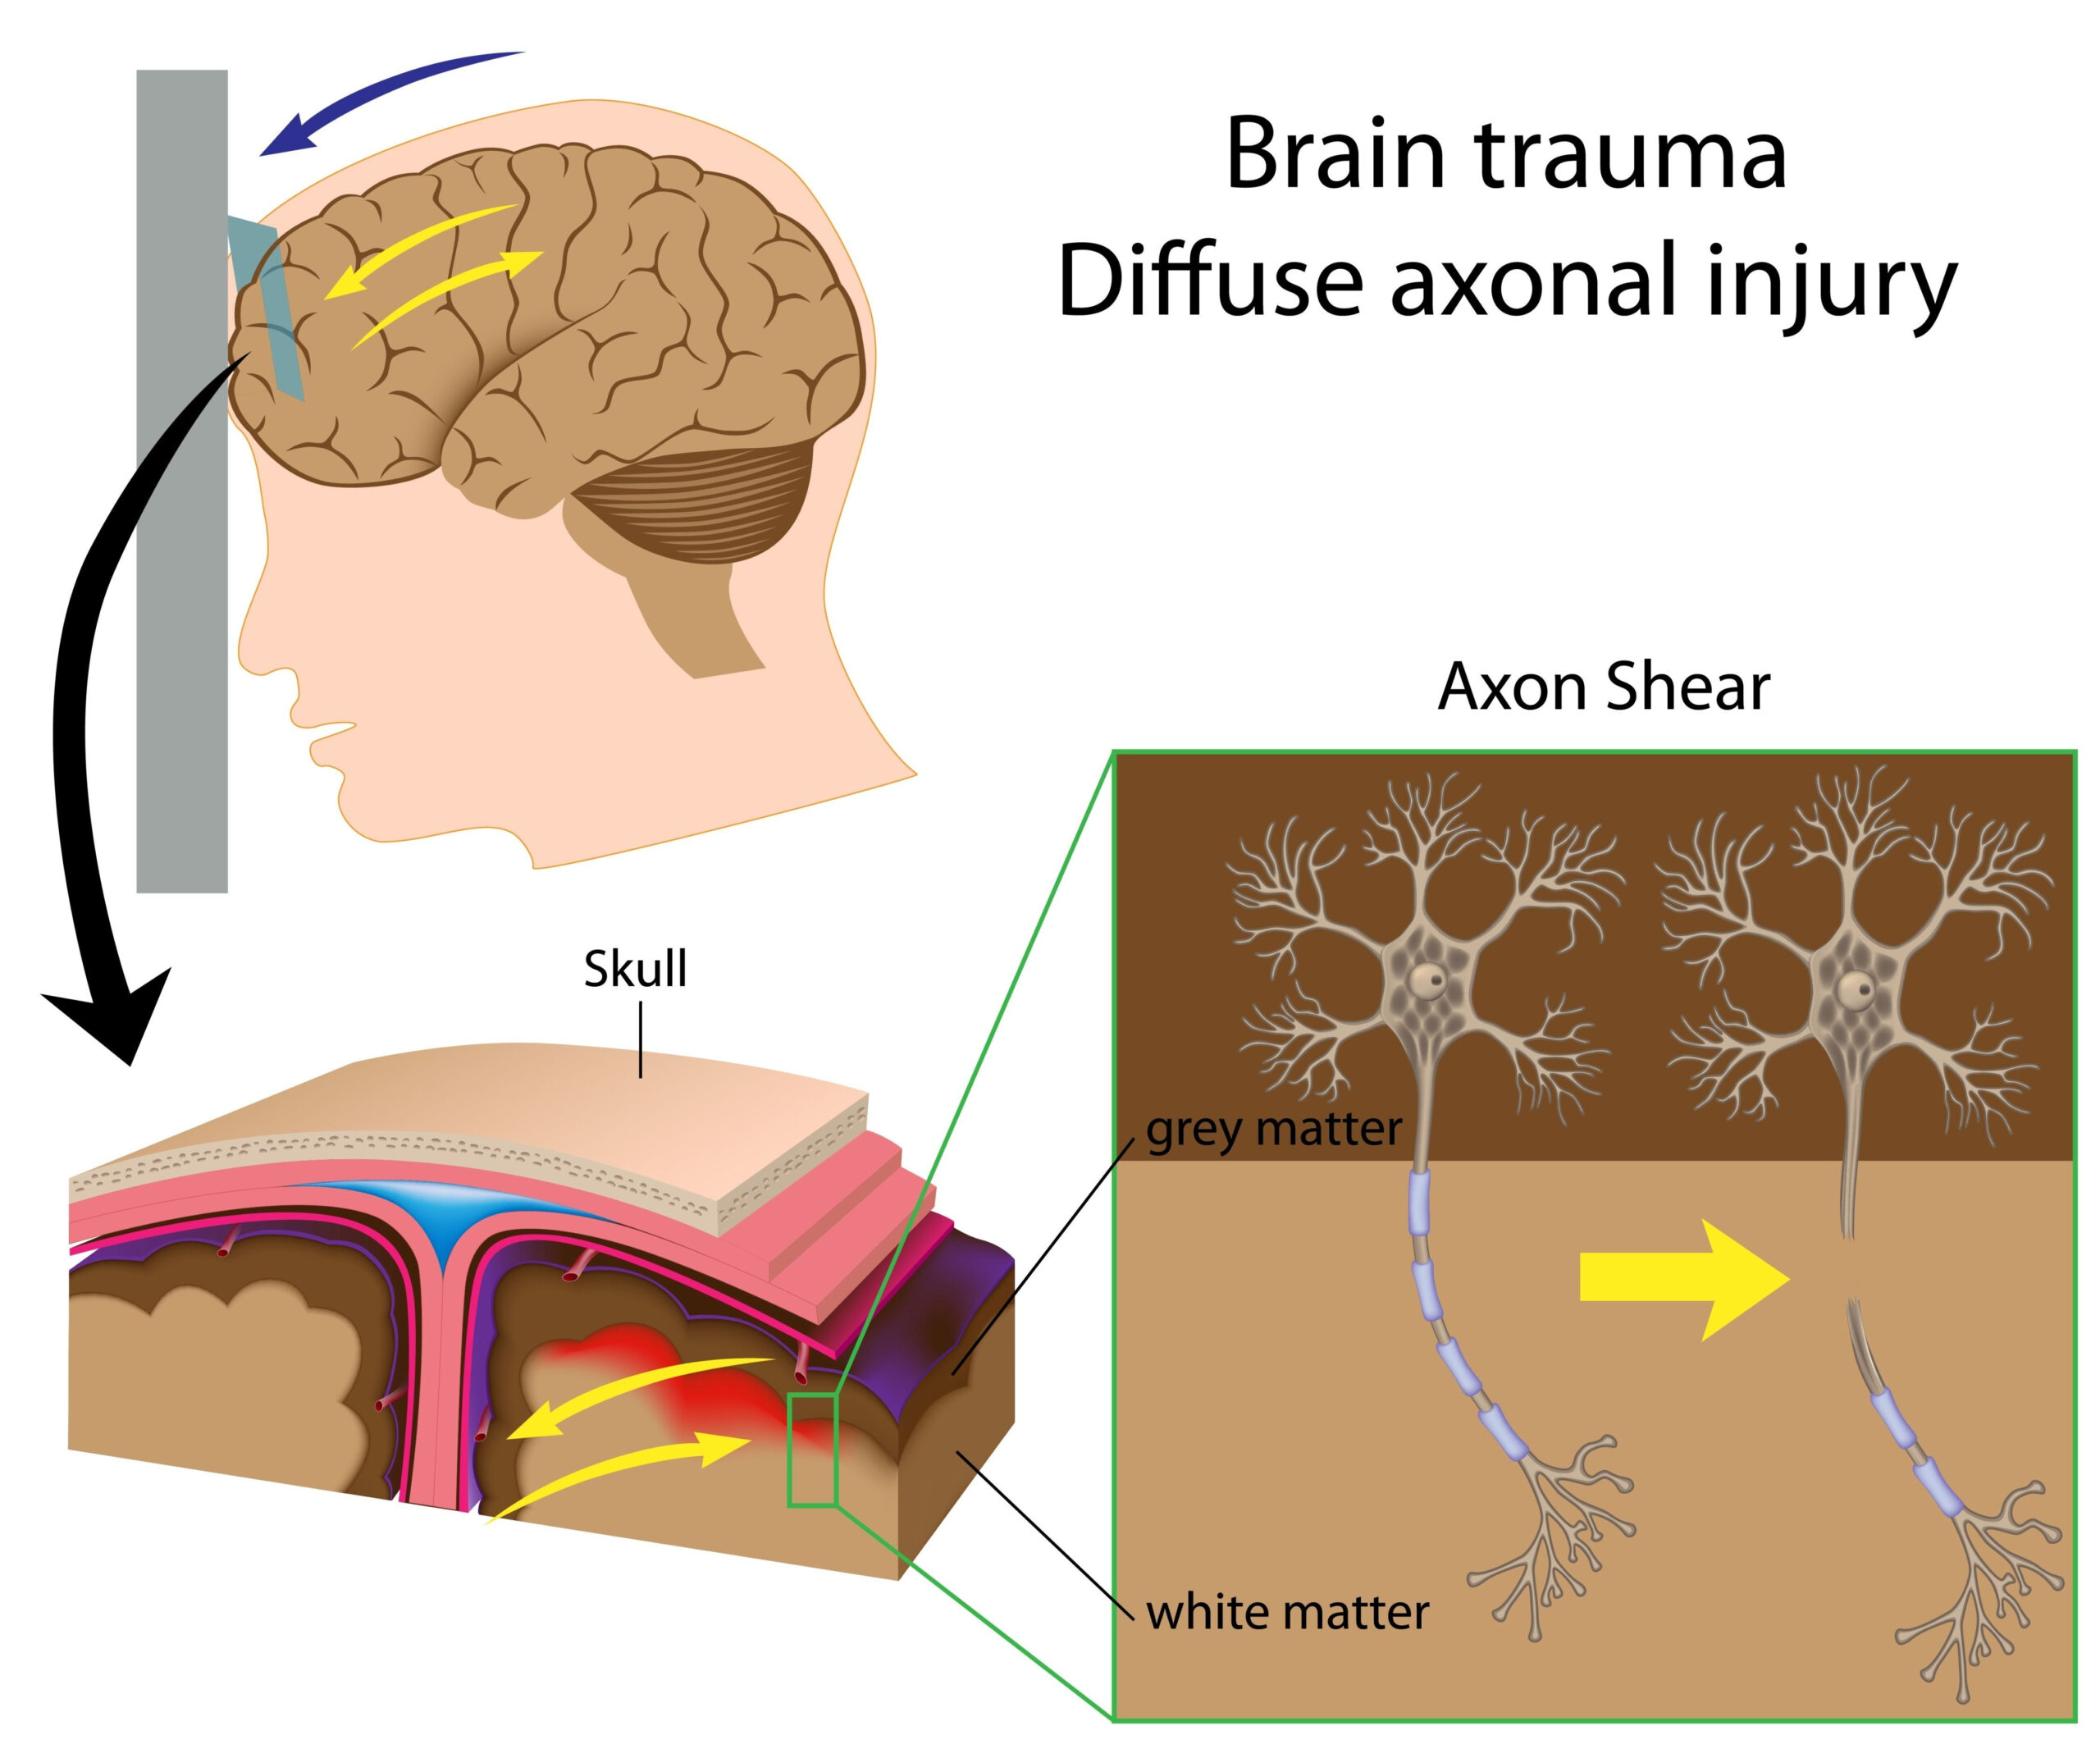
The research focuses on pediatric traumatic brain injury (TBI) and its association with healthcare-associated infections (HAIs). TBI in children is a significant public health concern, often leading to long-term neurological deficits and increased mortality. Understanding the factors influencing mortality rates in this population is crucial for improving clinical outcomes. The study aims to identify key determinants related to both TBI and HAIs, utilizing robust statistical methods such as least absolute shrinkage and selection operator (LASSO) regression.
The prospective nature of the study allows for real-time data collection and analysis, providing a fresh snapshot of the current landscape of pediatric TBI management and HAI prevalence. Data was gathered from multiple healthcare facilities specializing in pediatric care, ensuring a diverse representation of cases. This multi-center approach enhances the reliability of the findings and allows for generalization across different settings.
Particular attention is given to the interplay between the severity of the TBI, the presence of HAIs, and patient outcomes, including mortality. The research acknowledges that children with TBI are vulnerable to infections due to various factors such as compromised immunity, length of hospital stays, and invasive procedures. By identifying these relationships, the study aims to contribute valuable insights to clinical practice, guiding interventions that may reduce mortality and improve health outcomes for affected children.
Through comprehensive data analysis, this study hopes to delineate not only the immediate impacts of TBI and HAIs but also the long-term implications on health, thereby influencing future research directions and healthcare policies in pediatric trauma care.
Methodology
The methodology employed in this study is designed to rigorously assess the determinants of mortality in pediatric traumatic brain injury patients who develop healthcare-associated infections. A prospective cohort study format was selected to facilitate the gathering of real-time data from multiple pediatric healthcare centers, which ensures the capture of a broad spectrum of patient experiences and outcomes.
Data collection involved a combination of electronic health records and direct patient assessments. Participants included children aged 0 to 18 years who sustained a TBI, defined by the Glasgow Coma Scale (GCS) score at the point of admission. The study included various types of TBIs, such as concussions, contusions, and more severe injuries requiring surgical intervention. Patients were monitored for the development of healthcare-associated infections during their hospital stay, as well as for their overall recovery trajectory, including mortality rates.
To identify variables that might influence mortality, a wide array of clinical and demographic data was collected. These variables encompassed patient age, sex, the mechanism of injury, GCS scores, length of hospital stay, type of interventions received, and the specific healthcare-associated infections diagnosed. The methodology placed particular emphasis on capturing both infectious and non-infectious complications that could affect outcomes.
The statistical analysis employed the least absolute shrinkage and selection operator (LASSO) regression technique. This method is particularly well-suited for high-dimensional data where the number of predictors may exceed the number of observations. By applying LASSO, the study not only identifies potential predictors of mortality but also effectively shrinks the influence of non-informative variables, enabling a more precise understanding of the key factors at play. The regression model was calibrated to account for potential confounders and interactions among variables, providing a nuanced view of the determinants impacting mortality rates.
To validate the findings, the model underwent multiple phases of cross-validation. This process ensured the robustness and reliability of the results, enabling the researchers to confirm that their findings could be replicated in similar patient populations. In addition, ethical approval was secured from the institutional review board at each participating center, with informed consent obtained from guardians of the patients enrolled in the study.
By adhering to these methodological standards, this research aims to contribute meaningful insights into the complex interplay between pediatric TBI, healthcare-associated infections, and mortality, ultimately supporting healthcare providers in delivering targeted, evidence-based care for this vulnerable population.
Key Findings
The analysis of the data revealed several critical insights into the relationships between pediatric traumatic brain injury (TBI), healthcare-associated infections (HAIs), and mortality rates in affected children. First, the study highlighted that children with more severe TBIs, as indicated by lower Glasgow Coma Scale (GCS) scores at admission, experienced significantly higher mortality rates. This correlation reiterates the established understanding that the severity of TBI directly influences patient outcomes, emphasizing the need for prompt and effective management in these cases.
Moreover, the presence of healthcare-associated infections had a profound impact on mortality outcomes. Among the cohort, those who developed HAIs while hospitalized exhibited a mortality rate that was nearly double that of patients without infections. Notably, the types of infections encountered, including ventilator-associated pneumonia and central line-associated bloodstream infections, were identified as major contributors to complications that led to increased mortality. This underscores the importance of strict infection control measures in pediatric care environments, particularly for patients with compromised neurological status.
The study also identified specific demographics and clinical characteristics associated with higher risks of both severe TBI and subsequent HAIs. For instance, children under the age of five were found to be at a heightened risk for adverse outcomes, potentially due to their more fragile immune systems and greater susceptibility to infections in a hospital setting. Additionally, longer hospital stays were found to correlate with increased odds of developing HAIs, suggesting that extended periods in healthcare facilities may expose vulnerable patients to additional risks.
From the statistical analysis using the LASSO regression model, several key determinants of mortality were isolated. Apart from the severity of TBI and the presence of HAIs, factors such as the mechanism of injury (e.g., falls, motor vehicle accidents) and the depth of intervention required (such as surgical intervention versus conservative management) also emerged as significant predictors of outcomes. Interestingly, some traditional health determinants, like socioeconomic status and pre-existing health conditions, showed less influence on mortality than anticipated in this specialized cohort.
The model’s strength lies in its ability to delineate these complex interrelationships, offering a clearer picture of risk factors that can inform clinical practice. The findings suggest that enhanced monitoring and proactive management strategies should be adopted, particularly for high-risk patients identified through these predictors. Implementation of tailored interventions aimed at reducing infection risk among children with TBI could potentially improve survival rates and overall health outcomes.
Ultimately, the study’s findings underscore a critical necessity for ongoing education and training for healthcare professionals regarding best practices in managing pediatric TBIs and preventing HAIs. The insights gained not only reinforce existing clinical guidelines but also pave the way for future research endeavors aimed at further elucidating the pathways leading to mortality in pediatric populations affected by traumatic brain injuries.
Strengths and Limitations
The study’s strengths lie in its comprehensive design, which effectively captures a wide variety of data while addressing a critical healthcare issue in pediatric patients. By adopting a prospective cohort design across multiple centers, the research benefits from a richer dataset that reflects diverse clinical practices and patient demographics. This multi-faceted approach enhances the generalizability of results, allowing findings to be applicable across different healthcare settings. Furthermore, the utilization of LASSO regression provides a sophisticated analytical framework that helps elucidate complex relationships between variables, allowing the identification of key risk factors with greater accuracy.
Data collection from electronic health records, combined with direct observations of patient outcomes, ensures both objectivity and relevance. The algorithms used for data analysis are not only robust but also tailored to the unique challenges of high-dimensional data, making the analytic process adaptable to emerging trends in pediatric TBI and HAI research.
Conversely, the study is not without limitations. One potential concern is the observational nature of the research, which may introduce biases that can affect the interpretation of causal relationships. While the multi-center approach enhances diversity, it may also lead to variability in treatment protocols and infection control measures, complicating comparisons across locations. Differences in clinical practices could impact outcomes, meaning that while the study identifies associations, it may not fully establish causation.
Another limitation lies in the specific patient population studied. While focusing on children with TBI provides essential insights, the findings may not be broadly applicable to all pediatric patients or to those with different underlying health conditions. Additionally, the reliance on existing medical records for some data may introduce gaps or inaccuracies, as record-keeping practices can differ among institutions.
Future research would benefit from addressing these limitations by incorporating randomized controlled trials or multicentric interventions that could validate the effectiveness of identified predictors and interventions in real-world scenarios. Establishing continuity in data collection processes across diverse institutions could further enhance the validity of future findings, ensuring that they are not only robust but also actionable in shaping clinical practice.
Ultimately, recognizing the strengths and limitations of this study will inform ongoing efforts to enhance pediatric care for TBI patients and mitigate the risks associated with HAIs, contributing meaningfully to the field of pediatric health research.