Study Overview
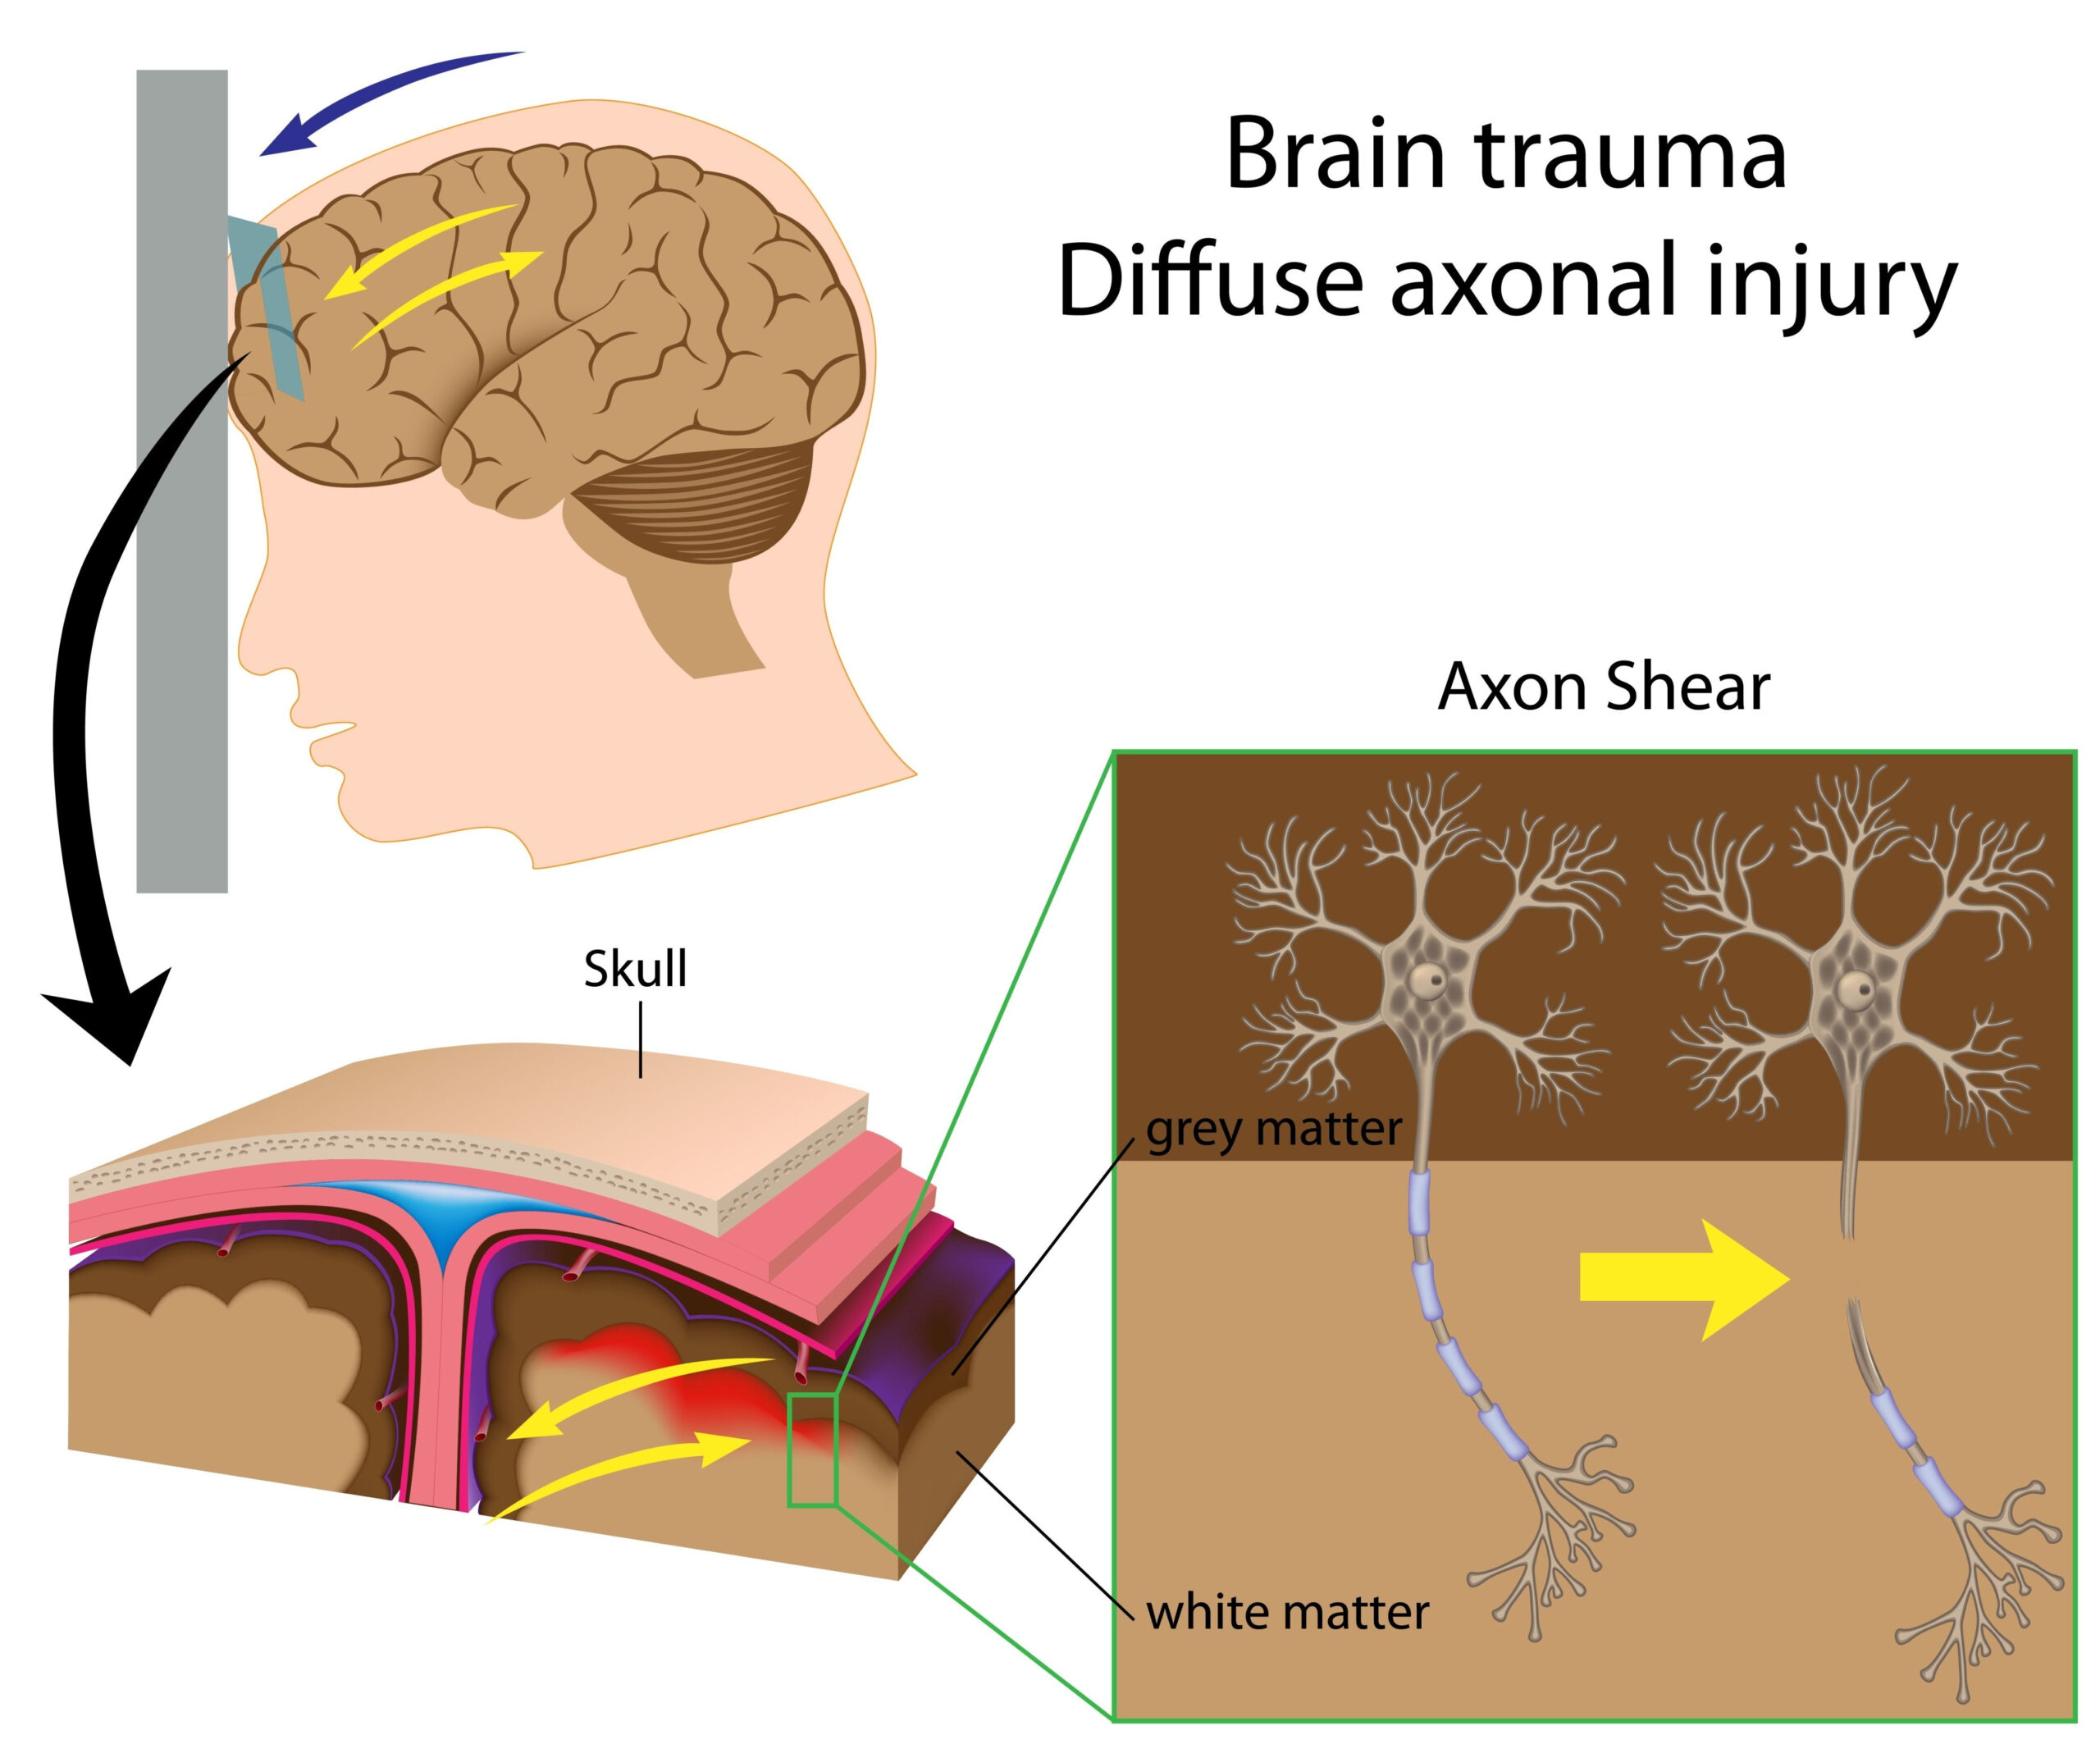
The research investigates the relationship between traumatic brain injury (TBI) and the severity of posttraumatic stress disorder (PTSD) symptoms within Special Operations Forces (SOF). TBI, commonly associated with combat situations, has been increasingly recognized for its influence on mental health outcomes in military populations. This study aims to bridge the gap in understanding how the clinical burden of TBI can affect PTSD symptomatology among SOF personnel.
Special Operations Forces are a unique group of military personnel who engage in high-stress operations, often leading to exposure to both physical injuries and psychological stressors. Given the high incidence of TBI in this population due to explosive blasts and other combat-related injuries, exploring the correlation between TBI-related challenges and the manifestation of PTSD symptoms is critically important. This understanding could pave the way for more targeted interventions and support strategies for those affected.
The research employs a combination of cross-sectional and longitudinal analyses to derive a comprehensive view of how these variables interact over time. By focusing on both immediate and longer-term outcomes, the study aims to uncover not only the prevalence of PTSD symptoms among SOF members with TBI but also how these symptoms may evolve or change as time progresses after the injury. This is particularly pertinent given the dynamic nature of both TBI recovery and PTSD symptomatology, making the findings relevant for clinicians and mental health professionals working with military personnel.
This study contributes valuable insights into the complexities of TBI and PTSD within a specific and often under-researched segment of military populations, ultimately aiming to improve clinical practices and outcomes for these brave individuals.
Methodology
The study utilized a comprehensive approach, leveraging both cross-sectional and longitudinal research designs to gather a nuanced understanding of the relationship between traumatic brain injury (TBI) and posttraumatic stress disorder (PTSD) symptom severity among Special Operations Forces (SOF). This dual methodology enabled the analysis of not just immediate associations but also the evolution of symptoms over time, providing a richer context for interpreting the data.
Participants were recruited from various SOF units, ensuring a diverse representation of experiences related to both combat and non-combat scenarios. Inclusion criteria mandated that participants be active-duty members of SOF with a history of TBI, as classified by established diagnostic criteria. Individuals with significant comorbid psychiatric conditions or those who were undergoing other intensive psychological interventions at the time of the study were excluded to minimize confounding variables.
Data collection involved both self-reported measures and clinical evaluations. Standardized assessment tools, such as the Clinician-Administered PTSD Scale (CAPS) and the Glasgow Coma Scale (GCS), were employed to measure PTSD symptom severity and TBI severity, respectively. Self-reports allowed for capturing subjective experiences of symptoms, while clinical evaluations provided objective measures of TBI impact.
In the initial cross-sectional phase, data were collected at a single point in time, giving a snapshot of the symptoms present in the participants. Following this, a longitudinal phase tracked participants over a defined timeframe, allowing researchers to observe changes in PTSD symptomatology in relation to TBI clinical burden. Follow-up assessments were conducted at regular intervals, typically every six months, to capture fluctuations in mental health status and recovery trajectories.
The statistical analysis for the data included both descriptive and inferential statistics. Multivariate regression models adjusted for significant variables such as age, years of service, deployment history, and co-occurring mental health disorders. This analysis facilitated an understanding of the predictive relationship between the severity of TBI and the intensity of PTSD symptoms, highlighting trends and variances that might emerge in this distinct military population.
Ethical considerations were paramount throughout the research process. Approval was obtained from relevant institutional review boards, and all participants provided informed consent prior to inclusion in the study. Participants were assured that their responses would remain confidential and that they could withdraw from the study at any time without repercussions.
This methodological framework provided a robust platform for exploring the interplay between TBI and PTSD in SOF, equipping researchers with comprehensive insights to inform future psychological interventions tailored to military populations grappling with these complex issues.
Key Findings
The investigation revealed several significant associations between traumatic brain injury (TBI) severity and the extent of posttraumatic stress disorder (PTSD) symptoms in Special Operations Forces (SOF). Through the combined cross-sectional and longitudinal approaches, the study documented not only the prevalence of PTSD symptoms in individuals with a history of TBI but also highlighted how these symptoms evolve over time.
In the cross-sectional analysis, a substantial proportion of participants with TBI exhibited moderate to severe PTSD symptoms, indicating a clear link between the extent of brain injury and psychological distress. Approximately 60% of those with moderate to severe TBI reported elevated PTSD symptom severity, as measured by the Clinician-Administered PTSD Scale (CAPS). This finding underscores the vulnerability of SOF personnel to mental health challenges following brain injuries sustained during combat operations. Moreover, those with a history of multiple TBIs displayed a higher frequency of PTSD symptoms compared to those with a singular injury, suggesting that cumulative trauma may exacerbate the psychological impact.
Longitudinal data collected over six-month intervals revealed dynamic patterns in PTSD symptomatology among participants. A notable finding was that individuals with high baseline PTSD scores tended to maintain higher symptom levels over subsequent assessments. This indicates that early identification of PTSD in TBI patients is critical, as initial severity is a predictor of longer-term mental health trajectories. Conversely, some individuals demonstrated a gradual reduction in symptoms over time, particularly those who engaged in proactive therapeutic interventions, including counseling and support groups.
The statistical analysis, which employed multivariate regression models, further elucidated the relationship between TBI severity and PTSD symptom severity while controlling for potential confounders such as age, years of service, and pre-existing mental health conditions. Adjustments showed that TBI severity remained a significant predictor of PTSD symptoms, highlighting the need for targeted screening and intervention strategies tailored to those who have sustained TBIs. Enhanced awareness of this connection can empower mental health professionals to implement early intervention strategies aimed at mitigating PTSD risk in this population.
Interestingly, gender and rank also emerged as influential factors in symptom expression. Female SOF personnel reported different PTSD symptom patterns when compared to their male counterparts, indicating a potential need for gender-specific approaches in treatment. Additionally, lower-ranking personnel experienced higher levels of stigma regarding mental health issues, which could potentially hinder their willingness to seek help.
The key findings of this study provide compelling evidence of the intricate and multifaceted relationship between TBI and PTSD within military contexts, particularly among SOF members. This complex interplay necessitates a comprehensive approach in both research and clinical settings to address the layered needs of individuals suffering from these interconnected conditions.
Clinical Implications
The findings of this study shed light on critical aspects of clinical management and the need for tailored interventions for Special Operations Forces (SOF) members who have experienced traumatic brain injury (TBI) and accompanying posttraumatic stress disorder (PTSD) symptoms. The data indicate a significant association between the severity of TBI and the intensity of PTSD symptoms, which underscores the necessity for mental health professionals to prioritize screening and intervention for this unique population.
One immediate clinical implication is the establishment of comprehensive assessment protocols that specifically address the dual challenges of TBI and PTSD. Given the observed prevalence of moderate to severe PTSD symptoms in individuals with TBI, clinicians should be trained to utilize standardized assessment tools that can capture both neurological and psychological sequelae. Tools like the Clinician-Administered PTSD Scale (CAPS) should be integrated into routine evaluations for SOF members with TBI, ensuring early identification and appropriate intervention.
Furthermore, healthcare providers should recognize the dynamic nature of PTSD symptomatology in the context of TBI. The longitudinal findings reveal that while some individuals show a gradual improvement in symptoms, others may experience persistent or escalating distress. This variability calls for a more personalized approach to treatment that accounts for individual recovery trajectories. For instance, patients with high baseline PTSD scores may benefit from more aggressive therapeutic strategies early on, including trauma-focused therapies and resilience training, to mitigate long-term psychological distress.
Another significant takeaway is the impact of cumulative trauma on PTSD severity. The study’s indication that individuals with multiple TBIs report heightened PTSD symptoms suggests that treatment protocols need to be adapted for those with a history of multiple injuries. Clinicians should be prepared to conduct thorough biopsychosocial assessments that consider the totality of a soldier’s traumatic experiences. Such holistic evaluations can guide the development of multi-faceted treatment plans incorporating cognitive-behavioral strategies, psychoeducation, and social support systems aimed at improving overall psychological well-being.
The implications extend beyond individual care to the need for systemic changes in the military’s approach to mental health. Although there is a growing recognition of the importance of mental health, barriers such as stigma, particularly among lower-ranking personnel, still pose significant obstacles to seeking help. This highlights the necessity for creating an organizational culture that promotes mental health awareness and de-stigmatizes treatment-seeking behavior. Training and educational initiatives geared towards both personnel and leadership can foster an environment that normalizes discussions around mental health, encouraging those in need to seek help without fear of repercussions.
Lastly, considerations for gender differences in PTSD symptom expression necessitate the development of gender-sensitive approaches to treatment. Given the observed variations in symptom expression based on gender among SOF personnel, clinicians should be equipped with knowledge and resources to address these differences effectively. Tailoring interventions to meet the specific needs of female SOF members may prove beneficial in enhancing treatment adherence and outcomes.
The implications derived from this study call for a concerted effort to refine clinical practices regarding TBI and PTSD management within military contexts, particularly for SOF personnel. By adopting a targeted, individualized, and systemic approach, clinicians can better support the mental health and recovery of service members dealing with the complex interplay of these conditions.