Coexistence of POTS and FND
Postural Orthostatic Tachycardia Syndrome (POTS) and Functional Neurological Disorder (FND) are two distinct yet often overlapping conditions that can significantly affect an individual’s health and quality of life. POTS is characterized by an abnormal increase in heart rate when transitioning from a supine to an upright position, leading to symptoms such as dizziness, palpitations, and fatigue. Meanwhile, FND encompasses a range of neurological symptoms that cannot be explained by structural or biochemical disorders of the nervous system. These symptoms can include movement disorders, seizures, and sensory issues, and they often occur in the context of psychological stressors or trauma.
The coexistence of POTS and FND poses a unique challenge for diagnosis and treatment. Patients presenting with symptoms typical of both conditions may initially find themselves misdiagnosed or under-treated. A clear understanding is required to differentiate whether the autonomic dysfunction seen in POTS is a primary condition or a secondary manifestation of FND. It has been observed that a subset of patients with FND may exhibit features consistent with POTS, suggesting that these disorders may share underlying mechanisms, such as dysregulation of the autonomic nervous system, heightened anxiety, or other psychological factors.
Recent studies indicate that the somatic symptoms experienced by individuals with FND can influence their autonomic responses. For instance, stress or anxiety may exacerbate the heart rate changes associated with POTS, creating a feedback loop where the autonomic symptoms worsen the neurological manifestations of FND. Consequently, effective management of patients exhibiting both conditions typically requires an interdisciplinary approach, integrating neurology, cardiology, and mental health support to address the full spectrum of symptoms.
This interplay between POTS and FND emphasizes the importance of a comprehensive clinical assessment. Clinicians must remain vigilant in recognizing the signs of both disorders in patients presenting with unexplained tachycardia or other autonomic fluctuations. By doing so, it may enhance the accuracy of diagnosis and optimize treatment strategies, providing a better quality of life for affected individuals.
Assessment Techniques
The assessment of Postural Orthostatic Tachycardia Syndrome (POTS) and Functional Neurological Disorder (FND) involves a combination of clinical evaluations and specialized testing. Given the overlapping symptoms of these two conditions, it is essential for practitioners to utilize comprehensive techniques that can effectively differentiate between them while also confirming their coexistence in patients.
One of the primary diagnostic tools for POTS is the tilt table test, which assesses changes in heart rate and blood pressure when a patient moves from a supine to an upright position. During this test, patients are secured on a table that tilts to simulate the gravitational challenges of standing. A sustained increase in heart rate of more than 30 beats per minute within ten minutes of standing, alongside symptoms such as lightheadedness or palpitations, is indicative of POTS. Traditional vital signs measurements, however, may not always capture the full spectrum of autonomic dysfunction; hence, additional monitoring techniques, including continuous heart rate variability analysis, can provide insight into the autonomic nervous system’s regulation.
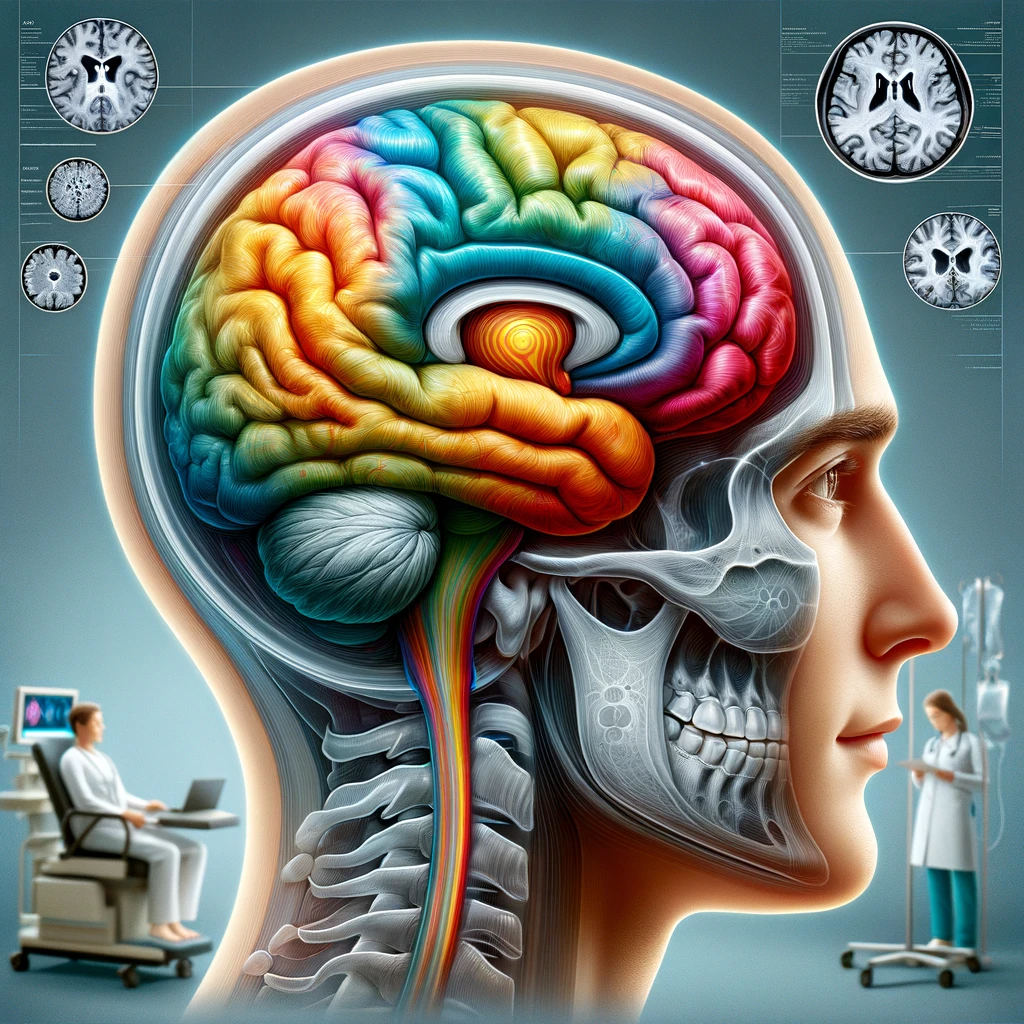
For the assessment of FND, the neurologic examination is paramount. Clinicians often employ various observation techniques to identify inconsistencies in motor or sensory symptoms that could suggest a functional rather than a structural cause. This nuanced evaluation might include testing for non-anatomical movement disorders or conducting tasks that reveal inconsistently observed cognitive or sensory deficits. Neuroimaging studies, such as MRI or CT scans, are typically unremarkable in FND cases, further supporting this functional diagnosis.
Moreover, autonomic reflex testing, which looks specifically at the body’s involuntary responses, can effectively highlight the interaction between POTS and FND. For instance, assessing baroreflex sensitivity and heart rate responses to deep breathing can illuminate dysregulations in autonomic control. Furthermore, the inclusion of questionnaires designed to evaluate the psychological impact of symptoms, including anxiety and depression scales, is critical in understanding the emotional context in which these disorders arise. These psychosocial assessments can help unravel the interplay between chronic health conditions and psychological well-being.
In clinical practice, a multidisciplinary approach is essential for accurately diagnosing and managing these overlapping conditions. Collaboration among neurologists, cardiologists, psychologists, and physiotherapists can facilitate a more comprehensive understanding of each patient’s unique presentation. The integration of physical examinations, diagnostic tests, and subjective questionnaires allows for a holistic evaluation, ultimately guiding personalized treatment plans that address not only the physiological but also the psychological dimensions of care.
Given the complexity of symptoms associated with both POTS and FND, it is imperative that healthcare providers remain vigilant and flexible in their assessments. The use of diverse diagnostic measures can enhance the detection of coexisting conditions, allowing for timely and effective interventions that improve patient outcomes.
Results Summary
Recent research has shed light on the prevalence and clinical features of Postural Orthostatic Tachycardia Syndrome (POTS) in patients diagnosed with Functional Neurological Disorder (FND). Data collected from a cohort of patients with overlapping symptoms revealed that a significant proportion, approximately 30-50%, displayed diagnostic criteria consistent with POTS. This finding underscores the necessity of thorough cardiovascular assessment in individuals presenting with FND symptoms.
The results also indicate that patients with both POTS and FND tend to report a more severe symptom burden compared to those with POTS alone. Commonly reported symptoms included debilitating fatigue, cognitive difficulties, and psychosomatic issues, all of which have been shown to exacerbate the overall clinical picture. Interestingly, evaluations of symptom severity demonstrated that anxiety and stress levels markedly influenced autonomic functioning, presenting a feedback loop that can aggravate both POTS and FND symptoms.
In terms of autonomic reflex testing outcomes, the analysis demonstrated reduced baroreflex sensitivity among those with combined diagnoses, suggesting a more pronounced autonomic dysregulation. Heart rate variability measurements further indicated that individuals with POTS and FND exhibited diminished parasympathetic activity, providing evidence that dysfunction within the autonomic nervous system may underlie the symptoms reported by patients. These findings raise awareness of the interconnected nature of these disorders, suggesting that managing one may benefit the other.
Furthermore, brief interventions that encompass aspects of cognitive-behavioral therapy (CBT) and physical rehabilitation spurred notable improvements in quality of life measures among participants suffering from both conditions. Patients reported enhancements in their daily functioning and symptom management, highlighting the potential benefits of an integrated treatment strategy that addresses both the psychological and physiological aspects.
The implications of these results support the necessity of recognizing POTS as a potential comorbidity in patients with FND, advocating for a tailored approach that enhances collaborative care among healthcare professionals. By fostering a comprehensive understanding of the overlap between these disorders, clinicians can provide more targeted interventions, aiming to alleviate the burden of symptoms experienced by affected individuals.
Future Directions
As research continues to evolve in the intertwined areas of Postural Orthostatic Tachycardia Syndrome (POTS) and Functional Neurological Disorder (FND), several future directions emerge that hold promise for enhanced understanding and management of these conditions. One key approach involves the establishment of standardized screening protocols to improve the identification of POTS in patients presenting with FND symptoms. The implementation of these protocols could facilitate timely diagnosis, allowing healthcare providers to address potential comorbidities more effectively.
Additionally, longitudinal studies are essential to unravel the relationships between symptom severity, autonomic dysfunction, and psychological factors in patients with both conditions. By recognizing how these aspects influence one another over time, researchers can develop more comprehensive treatment strategies that integrate both physiological and psychological interventions. Such studies would also contribute to a deeper understanding of the mechanisms at play in both POTS and FND, ultimately leading to targeted therapeutic techniques.
Incorporating patient-reported outcomes into research is another promising direction. Gathering qualitative data from patients regarding their experiences and symptomatology can inform clinical practice by highlighting patient perspectives. This approach ensures that the nuances of living with these conditions are considered in therapeutic decision-making and emphasizes the need for personalized medicine tailored to individual patient profiles.
Furthermore, exploring the role of interdisciplinary care models in managing POTS and FND offers valuable insights. Collaborative efforts among various healthcare providers, including neurologists, cardiologists, psychologists, and physical therapists, can foster a more holistic care environment. Research into these collaborative models may demonstrate improved patient outcomes through enhanced communication and coordinated care approaches that take into account the multifaceted nature of these disorders.
Lastly, advancements in technology, such as wearable devices and mobile health applications, may play a crucial role in monitoring and managing symptoms associated with both POTS and FND. The development of tools that can track heart rate variability, physical activity levels, and symptom fluctuations in real-time could empower patients to take an active role in their health management. These innovations could also facilitate data collection for research purposes, providing valuable information on daily symptom patterns and triggers.
The future of research and clinical practice surrounding POTS and FND lies in fostering collaborative, patient-centered approaches that utilize both innovative research strategies and technology. This integrated path may not only enhance the understanding of these complex disorders but also lead to the creation of more effective treatment frameworks that can significantly improve patient quality of life.