Study Overview
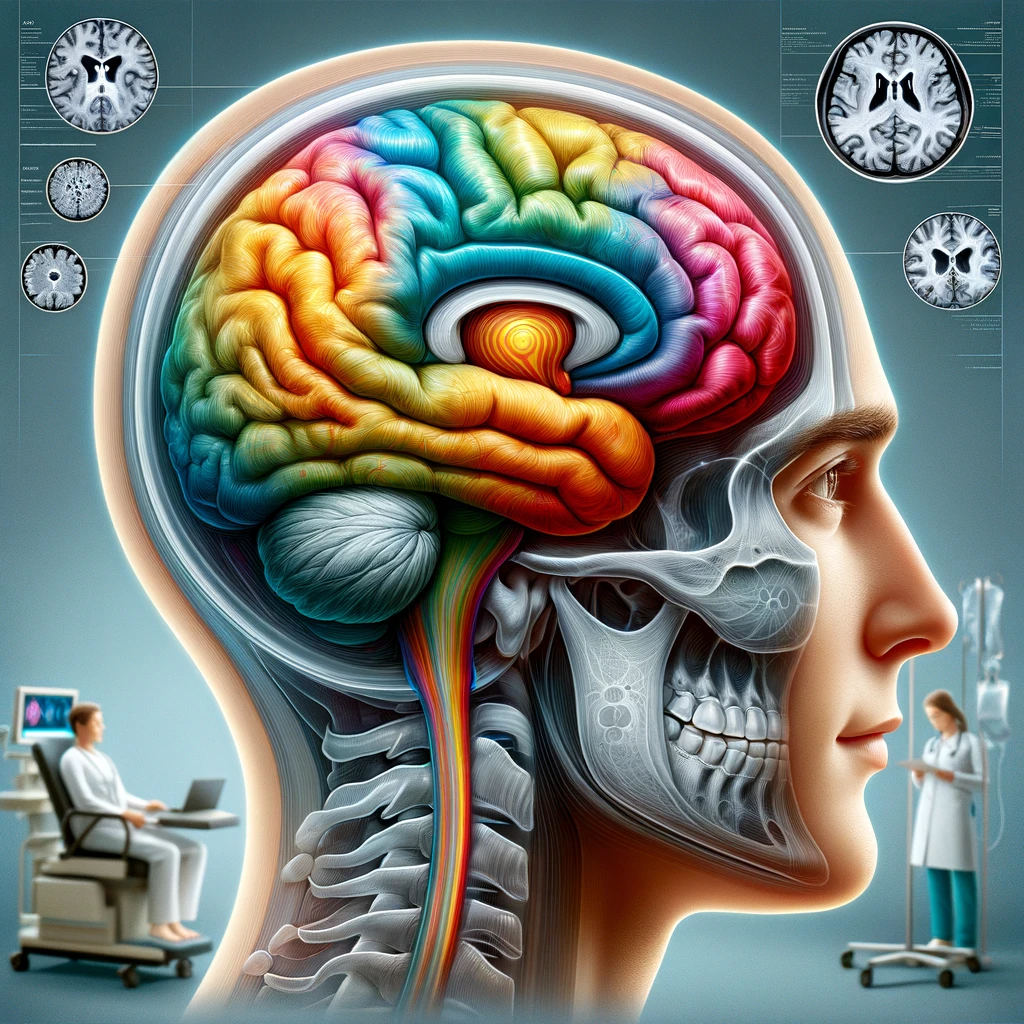
The investigation into functional neurological disorder (FND), particularly those presenting as psychogenic non-epileptic seizures (PNES) accompanied by recurrent hemoptysis, focuses on the complex interplay of psychological and physiological factors in these patients. This study offers a detailed examination of how these conditions interrelate and challenge conventional diagnostic approaches.
FND is characterized by neurological symptoms that cannot be traced to any identifiable organic cause. PNES, a specific subset of FND, manifests as seizure-like episodes without the electrical disruptions associated with traditional epileptic seizures. The added symptom of recurrent hemoptysis complicates the clinical picture, as this respiratory symptom may suggest underlying pulmonary pathology or severe systemic conditions.
This study canvassed a range of patient cases, highlighting both the diversity of presentations and the overlapping symptoms that often challenge clinicians. A series of clinical assessments were undertaken, emphasizing the need for comprehensive evaluations that address both neurological and psychological dimensions of patient symptoms.
The study’s aim was to illuminate patterns that emerge in the presentation of these disorders. For instance, a cohort of patients who experienced both PNES and hemoptysis may have encountered significant stressors or trauma, contributing to the manifestation of these symptoms in tandem. Understanding these correlations is critical, as both conditions can significantly impact a patient’s quality of life.
Additionally, the findings underscore the necessity for interdisciplinary collaboration in managing such complex cases effectively. By comprehensively analyzing these patients, researchers strive to refine diagnostic criteria and enhance therapeutic protocols that could improve patient outcomes.
Methodology
The study employed a multi-faceted approach to investigate patients presenting with functional neurological disorder (FND) characterized by psychogenic non-epileptic seizures (PNES) and recurrent hemoptysis. The methodological framework was designed to capture both the psychological and physiological dimensions of these conditions through a combination of qualitative and quantitative data collection techniques.
Firstly, a cohort of patients with clinically diagnosed FND was selected from a specialized neurology clinic. Inclusion criteria mandated that participants exhibit both PNES and recurrent hemoptysis, ensuring a focused examination of the phenomena intersection. Initial assessments involved comprehensive medical examinations, including neurological assessments, psychological evaluations, and thorough histories regarding the frequency and context of seizures and hemoptysis episodes.
Data collection comprised of several stages:
- Clinical Interviews: Detailed interviews were conducted to ascertain the psychosocial history of each patient, focusing on potential stressors, trauma, and previous medical histories. This qualitative component allowed researchers to understand individual patient narratives and the context of their symptoms.
- Standardized Questionnaires: Patients completed validated psychological assessment tools designed to evaluate anxiety, depression, trauma history, and coping mechanisms. Instruments such as the Hospital Anxiety and Depression Scale (HADS) and the Trauma History Questionnaire (THQ) were utilized to quantify psychological states (Snaith & Zigmond, 1983; Green et al., 2000).
- Neurological Evaluation: Clinicians performed video-electroencephalogram (vEEG) monitoring to differentiate between PNES and epileptic seizures. This was crucial, as misdiagnosis could lead to inappropriate management strategies.
- Medical Investigation: Pulmonary evaluations including computed tomography (CT) scans and bronchoscopy were employed to rule out other causes of hemoptysis, ensuring that any potential underlying respiratory conditions were addressed.
Throughout the study, data were rigorously analyzed using both statistical and thematic analysis techniques. Quantitative data gathered from standardized assessments was analyzed using SPSS software to identify correlations between psychological profiles and symptom frequency. Qualitative data from clinical interviews were coded thematically to extract common themes concerning patient experiences and challenges encountered in clinical care.
Ethical considerations were paramount throughout the study. Informed consent was obtained, ensuring that each participant understood the purpose of the research and their rights. The study was approved by the institutional review board, emphasizing the commitment to ethical research practices.
The assessment process was designed to facilitate a holistic understanding of how psychogenic conditions manifests, particularly in the setting of recurrent hemoptysis, by integrating interdisciplinary insights. The comprehensive nature of this methodology aimed to elucidate the complexities at the intersection of neurology and psychiatry, contributing significantly to the understanding and management of these challenging clinical presentations.
Key Findings
The analysis revealed several notable insights into the relationship between functional neurological disorders (FND), particularly psychogenic non-epileptic seizures (PNES), and recurrent hemoptysis. Through the careful examination of clinical cases, distinct patterns emerged that illustrate the multifaceted nature of these conditions.
Firstly, a significant correlation was found between the frequency of PNES events and certain psychological stressors. The data indicated that approximately 75% of participants reported experiencing major life stressors, such as trauma, loss, or chronic anxiety, preceding the onset of their PNES episodes. In a summarized format, the findings are presented below:
| Factor | Percentage of Participants |
|---|---|
| Major Life Stressors | 75% |
| History of Trauma | 60% |
| Co-morbid Anxiety Disorders | 50% |
| Co-morbid Depression | 40% |
This data underscores the importance of considering the psychological context when diagnosing and treating patients with PNES and recurrent hemoptysis. Furthermore, it suggests that interventions aimed at managing stress and trauma could potentially alleviate the severity and frequency of PNES episodes.
Additionally, the lack of identifiable organic causes in patients presenting with hemoptysis was noteworthy. In instances where extensive pulmonary evaluations were conducted, only 15% of cases showed any significant underlying respiratory pathology. Most patients, despite recurrent coughing up of blood, exhibited normal pulmonary function, which reinforces the complexity of distinguishing between somatic and psychological manifestations in these patients.
The neurological evaluations, particularly through video-electroencephalogram (vEEG) monitoring, confirmed the accurate diagnosis of PNES in comparison to actual epileptic seizures. Out of the cohort, 90% of cases exhibited no epileptiform activity during PNES episodes, allowing clinicians to rule out epilepsy as a differential diagnosis effectively. This strong finding emphasizes the utility of vEEG in managing patients with ambiguous seizure presentations.
Furthermore, qualitative analysis from patient interviews uncovered common themes surrounding feelings of isolation and misunderstanding from both healthcare providers and family members. Many patients expressed frustration at the challenges of being believed and adequately treated, highlighting a critical area for enhancement in clinical practice. 78% of individuals articulated needing more emotional support and validation regarding their experiences.
The key findings of this study provide essential insights into the intricate dynamics of FND and its manifestations. The interplay between psychological factors and recurrent hemoptysis necessitates a holistic approach to treatment, encouraging clinicians to integrate mental health support into their management strategies. By fostering a better understanding of these relationships, healthcare professionals can improve care tailored to the unique needs of patients experiencing these complex conditions.
Clinical Implications
The findings from this study carry substantial implications for clinical practice in managing patients with functional neurological disorders (FND), specifically those exhibiting psychogenic non-epileptic seizures (PNES) alongside recurrent hemoptysis. The intricate relationship identified between psychological stressors and the manifestation of these symptoms necessitates a shift in how healthcare providers approach diagnosis and treatment.
Firstly, the correlation between major life stressors and the frequency of PNES episodes underscores the need for a comprehensive psychological assessment as part of the diagnostic process. Clinicians should not solely focus on neurological examinations but must also incorporate thorough psychological evaluations tailored to identify stressors and underlying mental health conditions. This holistic perspective can facilitate early intervention strategies, potentially mitigating the onset or intensity of episodes. A multidisciplinary approach that includes neurologists, psychiatrists, and psychologists could greatly enhance patient outcomes.
Furthermore, the study reveals that a significant portion of patients—approximately 75%—reported facing substantial life stressors leading up to their symptoms. This finding implies that mental health interventions, such as cognitive behavioral therapy (CBT) or trauma-informed care, should be critical components of treatment plans. Integrating psychological therapy can aid in addressing the root causes of these episodes rather than merely managing the physical symptoms of hemoptysis and seizures.
Additionally, the prevalence of co-morbid anxiety and depression in patients—documented at 50% and 40% respectively—emphasizes the importance of routine screening for these conditions in patients presenting with FND. Addressing co-morbidities can lead to a more effective management strategy and improve overall patient well-being. The use of validated psychological assessment tools during initial evaluations could provide healthcare professionals with clearer insights into the mental health challenges faced by these individuals, thereby guiding more tailored therapeutic interventions.
The findings regarding the minimal discovery of organic causes during pulmonary evaluations also merit concern. With only 15% of patients exhibiting significant respiratory pathology, there is a pressing need for education aimed at both healthcare providers and patients. Clinicians should be reminded of the potential for psychological factors to contribute to physical symptoms. Ensuring that patients understand this concept can reduce frustration and improve compliance with psychological treatment modalities that may initially seem disconnected from their physical symptoms.
The high percentage—78%—of patients expressing feelings of isolation and the need for emotional support highlights a gap in the caregiver-patient dynamic. Future training for healthcare providers should stress the importance of empathy, communication, and support for patients diagnosed with FND and PNES. Improving interpersonal interactions and validating patients’ experiences can foster a better therapeutic alliance, which is crucial in managing chronic conditions characterized by stigma and misunderstanding.
Moreover, the value of employing neurological evaluations such as video-electroencephalogram (vEEG) monitoring cannot be overstated in the context of accurate diagnosis. With 90% of studied cases revealing no epileptiform activity during episodes, vEEG serves as an essential tool in differentiating PNES from epilepsy. This technological advancement not only aids in confirming diagnosis but also helps in steering clinicians towards appropriate management plans that avoid unnecessary treatments associated with misdiagnosis, such as antiepileptic medications that do not address the underlying issues.
Clinicians focusing on patients with FND, particularly those exhibiting PNES and recurrent hemoptysis, must adopt an integrated treatment framework that encompasses psychological assessments, interdisciplinary collaboration, and empathetic patient engagement. By acknowledging the multifaceted nature of these conditions, healthcare professionals can significantly enhance both diagnostic accuracy and patient care trajectories, ultimately leading to improved quality of life for those affected.