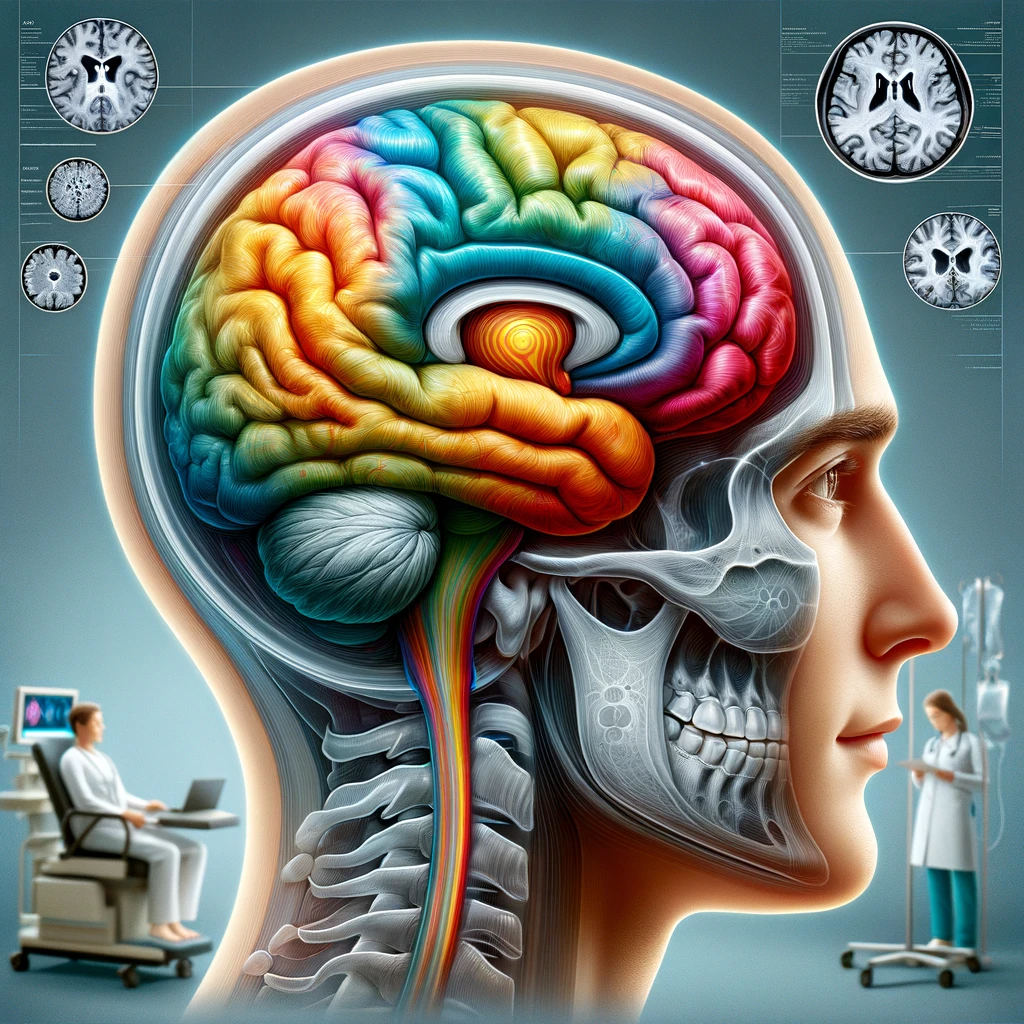
Understanding Hyperkinetic Movement Disorders
Hyperkinetic movement disorders encompass a diverse group of neurological conditions characterized by excessive, involuntary movements that can be either rhythmic or non-rhythmic. These disorders reflect a variety of underlying pathophysiological mechanisms, which complicate their diagnosis and treatment. The causes can range from genetic mutations and metabolic abnormalities to environmental factors, which make the clinical presentation quite heterogeneous.
The classification of hyperkinetic movement disorders includes several key categories. Tremors, characterized by oscillatory movements, are prominently seen in disorders such as essential tremor and Parkinson’s disease. Chorea, which involves rapid, unpredictable movements typically originating from voluntary muscle contractions, can occur in conditions like Huntington’s disease or as a consequence of certain medications. Dystonia, on the other hand, presents with sustained muscle contractions leading to abnormal postures or twisting movements, often classified by their distribution and timing.
In clinical settings, recognizing these disorders requires a nuanced understanding, as symptoms can overlap and evolve over time. For instance, a patient might present with chorea but later develop dystonic features, or vice versa. Notably, factors such as age of onset, symptom duration, and response to treatments can provide critical insights into the underlying cause. Furthermore, comorbid conditions are frequently observed, complicating the clinical landscape as patients may present with psychiatric symptoms or cognitive changes alongside their movement disorders.
The evaluation of patients with hyperkinetic movement disorders typically employs a combination of clinical observation and standardized rating scales. The employment of expert consensus in diagnosing these conditions is crucial, given the inherent subjectivity involved in interpreting movement patterns. Thus, clinical evaluations are often accompanied by video recordings and rating scales that allow for a more objective assessment of interrater agreement among specialists.
In summary, hyperkinetic movement disorders represent a complex interplay of involuntary movements and diverse clinical manifestations. The challenge lies not only in diagnosing these disorders accurately but also in understanding their variegated nature, which emphasizes the need for comprehensive clinical evaluation and collaborative expertise in neurodisability settings.
Study Design and Methods
The investigation into expert interrater agreement in hyperkinetic movement disorders necessitates a meticulously crafted study design to yield valid and reliable results. Central to this study is the recruitment of a cohort of clinicians with expertise in movement disorders, ensuring a robust sample of evaluators with varied backgrounds, including neurologists, movement disorder specialists, and psychiatrists.
The study utilized a multi-center approach, enhancing the generalizability of findings across different clinical settings. Participants were provided with a set of carefully curated video recordings depicting patients exhibiting various hyperkinetic movement disorders. These recordings were selected to represent a wide spectrum of clinical presentations, encompassing tremors, chorea, dystonia, and tics. The diversity in cases aimed to mimic the complexity encountered in real-world clinical evaluations and to address the subtleties that might be missed during a straightforward assessment.
Each clinician independently reviewed the video samples and was tasked with diagnosing the movement disorder according to established diagnostic criteria, such as those from the International Classification of Diseases (ICD) and the Diagnostic and Statistical Manual of Mental Disorders (DSM-5). Furthermore, raters were required to utilize standardized assessment tools, including the Abnormal Involuntary Movement Scale (AIMS) and the Burke-Fahn-Marsden Dystonia Rating Scale (BFMDRS), which provide structured methodologies for quantifying movement disorders.
The primary objective was to determine the degree of interrater agreement among experts. This was quantified using statistical measures such as Cohen’s kappa coefficient, which gauges the level of agreement beyond chance, thus offering a quantifiable insight into the reliability of clinical assessments. A kappa value above 0.75 indicates excellent agreement, while values between 0.40 and 0.75 suggest moderate to good agreement.
To ensure a rigorous process, raters underwent preliminary training and calibration sessions before the study commenced. This training focused on familiarizing them with the diagnostic criteria and the assessment scales, minimizing potential discrepancies in interpretation. Additionally, blinded evaluations were conducted to avoid bias, where raters were unaware of the clinical history or previous diagnoses of the patients featured in the videos.
Following the completion of the evaluations, the analysis included comparing diagnostic outcomes among raters to identify commonalities and discrepancies in diagnoses. These findings were then interrelated with the available clinical history and diagnostic criteria to evaluate how variations in interpretation might impact treatment decisions.
This approach is essential for elucidating the challenges faced in accurately diagnosing hyperkinetic movement disorders and reinforces the necessity of collaborative assessment to enhance diagnostic precision. Emphasizing these methods underlines the importance of structured evaluation in a field characterized by subjective judgment and diverse clinical manifestations.
Results and Interrater Agreement
The analysis of the study revealed noteworthy findings regarding expert interrater agreement in the diagnosis and assessment of hyperkinetic movement disorders. Upon reviewing a comprehensive array of video recordings, clinicians demonstrated varying levels of agreement in their diagnostic decisions, reflective of the complexity inherent in these disorders. The computed Cohen’s kappa coefficients served as a pivotal metric in assessing interrater reliability, with outcomes showcasing both strengths and weaknesses in consensus among clinicians.
In general, the results indicated moderate to strong interrater agreement across different movement disorders, with kappa values averaging between 0.60 and 0.80 for diagnoses such as chorea and tremors. In contrast, conditions with more intricate clinical features, such as dystonia, exhibited a lower kappa value of approximately 0.55, suggesting that variations in clinical interpretation may be more pronounced in these cases. Factors contributing to this variability included the overlapping symptomatology of disorders and the subjective nature of movement assessments.
Notably, expert raters exhibited a high degree of agreement in recognizing classical features of well-defined disorders, such as essential tremor and Parkinson’s disease. Specific movement characteristics—like the frequency and amplitude of tremors—were consistently identified, underscoring a shared understanding of these disorders among specialists. Conversely, the diagnosis of atypical or mixed presentations revealed significant discrepancies, where raters sometimes arrived at divergent conclusions based on subtle differences in movement patterns or contextual factors interpreted differently.
The analysis also identified particular challenges associated with assessing dystonia, which can manifest in a multitude of forms. The complexity of dystonic movements—often influenced by a patient’s posture, task, and emotional state—rendered clear-cut assessments challenging. As a result, raters occasionally reported reluctance in diagnosing dystonia without a comprehensive clinical history, reflecting concerns regarding the potential for misclassification.
Furthermore, the study illuminated the necessity for consistent and standardized diagnostic criteria in the field of hyperkinetic movement disorders. Through structured calibration sessions prior to the evaluations, raters demonstrated improved interrater reliability, indicating that enhanced training can bolster diagnostic accuracy. This finding underscores the importance of ongoing education and collaboration among clinicians to fortify diagnostic efforts, particularly in a landscape where movement disorders can present in multifaceted ways.
Feedback from participating clinicians also provided valuable insights into the diagnostic process. Many expressed the need for more robust guidelines and resources to support the evaluation of complex cases, acknowledging that even experienced specialists encounter uncertainty. Enhancing the availability of clinical tools that incorporate visual aids, detailed descriptions of movement patterns, and case examples could significantly improve diagnostic consistency.
Overall, while the results showcased a promising level of interrater agreement, the nuances of hyperkinetic movement disorders revealed areas for growth in clinical assessment practices. Understanding the dynamics at play in these evaluations fosters a foundation for future collaborative efforts aimed at refining diagnostic protocols and ultimately enhancing patient care in movement disorders.
Implications for Clinical Practice
The findings from the study highlight several critical implications for clinical practice in the diagnosis and management of hyperkinetic movement disorders. The moderate to strong interrater agreement observed among expert clinicians underscores the importance of collaborative evaluations in enhancing diagnostic accuracy. This collaboration is vital, as accurate diagnosis is foundational to effective treatment planning and management. The study’s outcomes suggest that structured training and calibration among clinicians can lead to improved consensus, providing a pathway for enhancing diagnostic capabilities in diverse clinical environments.
Implementing a systematic approach to the evaluation of hyperkinetic movement disorders can benefit practitioners by minimizing variability in assessments. This can be achieved through the adoption of standardized diagnostic criteria and rating scales, which are critical in ensuring that emerging clinicians align with best practices in the field. Educational initiatives that focus on the nuances of different hyperkinetic disorders, including their overlapping features, could empower clinicians to make more informed decisions in complex cases.
Furthermore, the study identifies the necessity of integrating comprehensive clinical histories with observational assessments. By understanding the full clinical context—including patient history, symptom onset, and comorbid conditions—clinicians can mitigate the risks of misdiagnosis, particularly in disorders with intricate symptomatology like dystonia. Encouraging thorough history-taking and contextual evaluation should become a standard practice in clinical settings.
The role of video recordings as diagnostic tools presents an opportunity to refine how movement disorders are assessed. The study demonstrated that video examples can significantly aid in teaching and calibrating clinicians, providing visual context to the often subtle movements associated with these disorders. Incorporating this technology into routine clinical practice could not only enhance evaluations but also serve as a valuable resource for ongoing education and training.
Moreover, fostering a culture of feedback among movement disorder specialists could lead to increased awareness of diagnostic challenges specific to hyperkinetic disorders. Establishing regular case discussions or multi-disciplinary meetings could allow for shared learning experiences, whereby clinicians can present challenging cases and collectively explore diagnostic interpretations. Such collaborative environments can help unify diagnostic perceptions, leading to more standardized practices.
As movement disorder specialists continue to encounter increasingly complex presentations, the implications of this study advocate for the development of enhanced clinical guidelines and resources. This may include creating comprehensive databases that catalog different hyperkinetic movement disorders with visual examples, symptom variations, and treatment responses. By sourcing a wide array of clinical scenarios and outcomes, practitioners can better contextualize their findings and make more informed treatment decisions.
Finally, ongoing research is vital in this area, as it provides avenues for exploring both novel treatment strategies and deeper insights into the pathophysiology of hyperkinetic movement disorders. A commitment to interdisciplinary collaboration and research will undoubtedly advance both clinical practice and patient outcomes, reinforcing the importance of sustained efforts in the field of movement disorders. In summary, leveraging the results of studies like this can significantly influence clinical practices, leading to improved diagnosis, patient care, and healthcare outcomes in individuals with hyperkinetic movement disorders.