Research Objectives
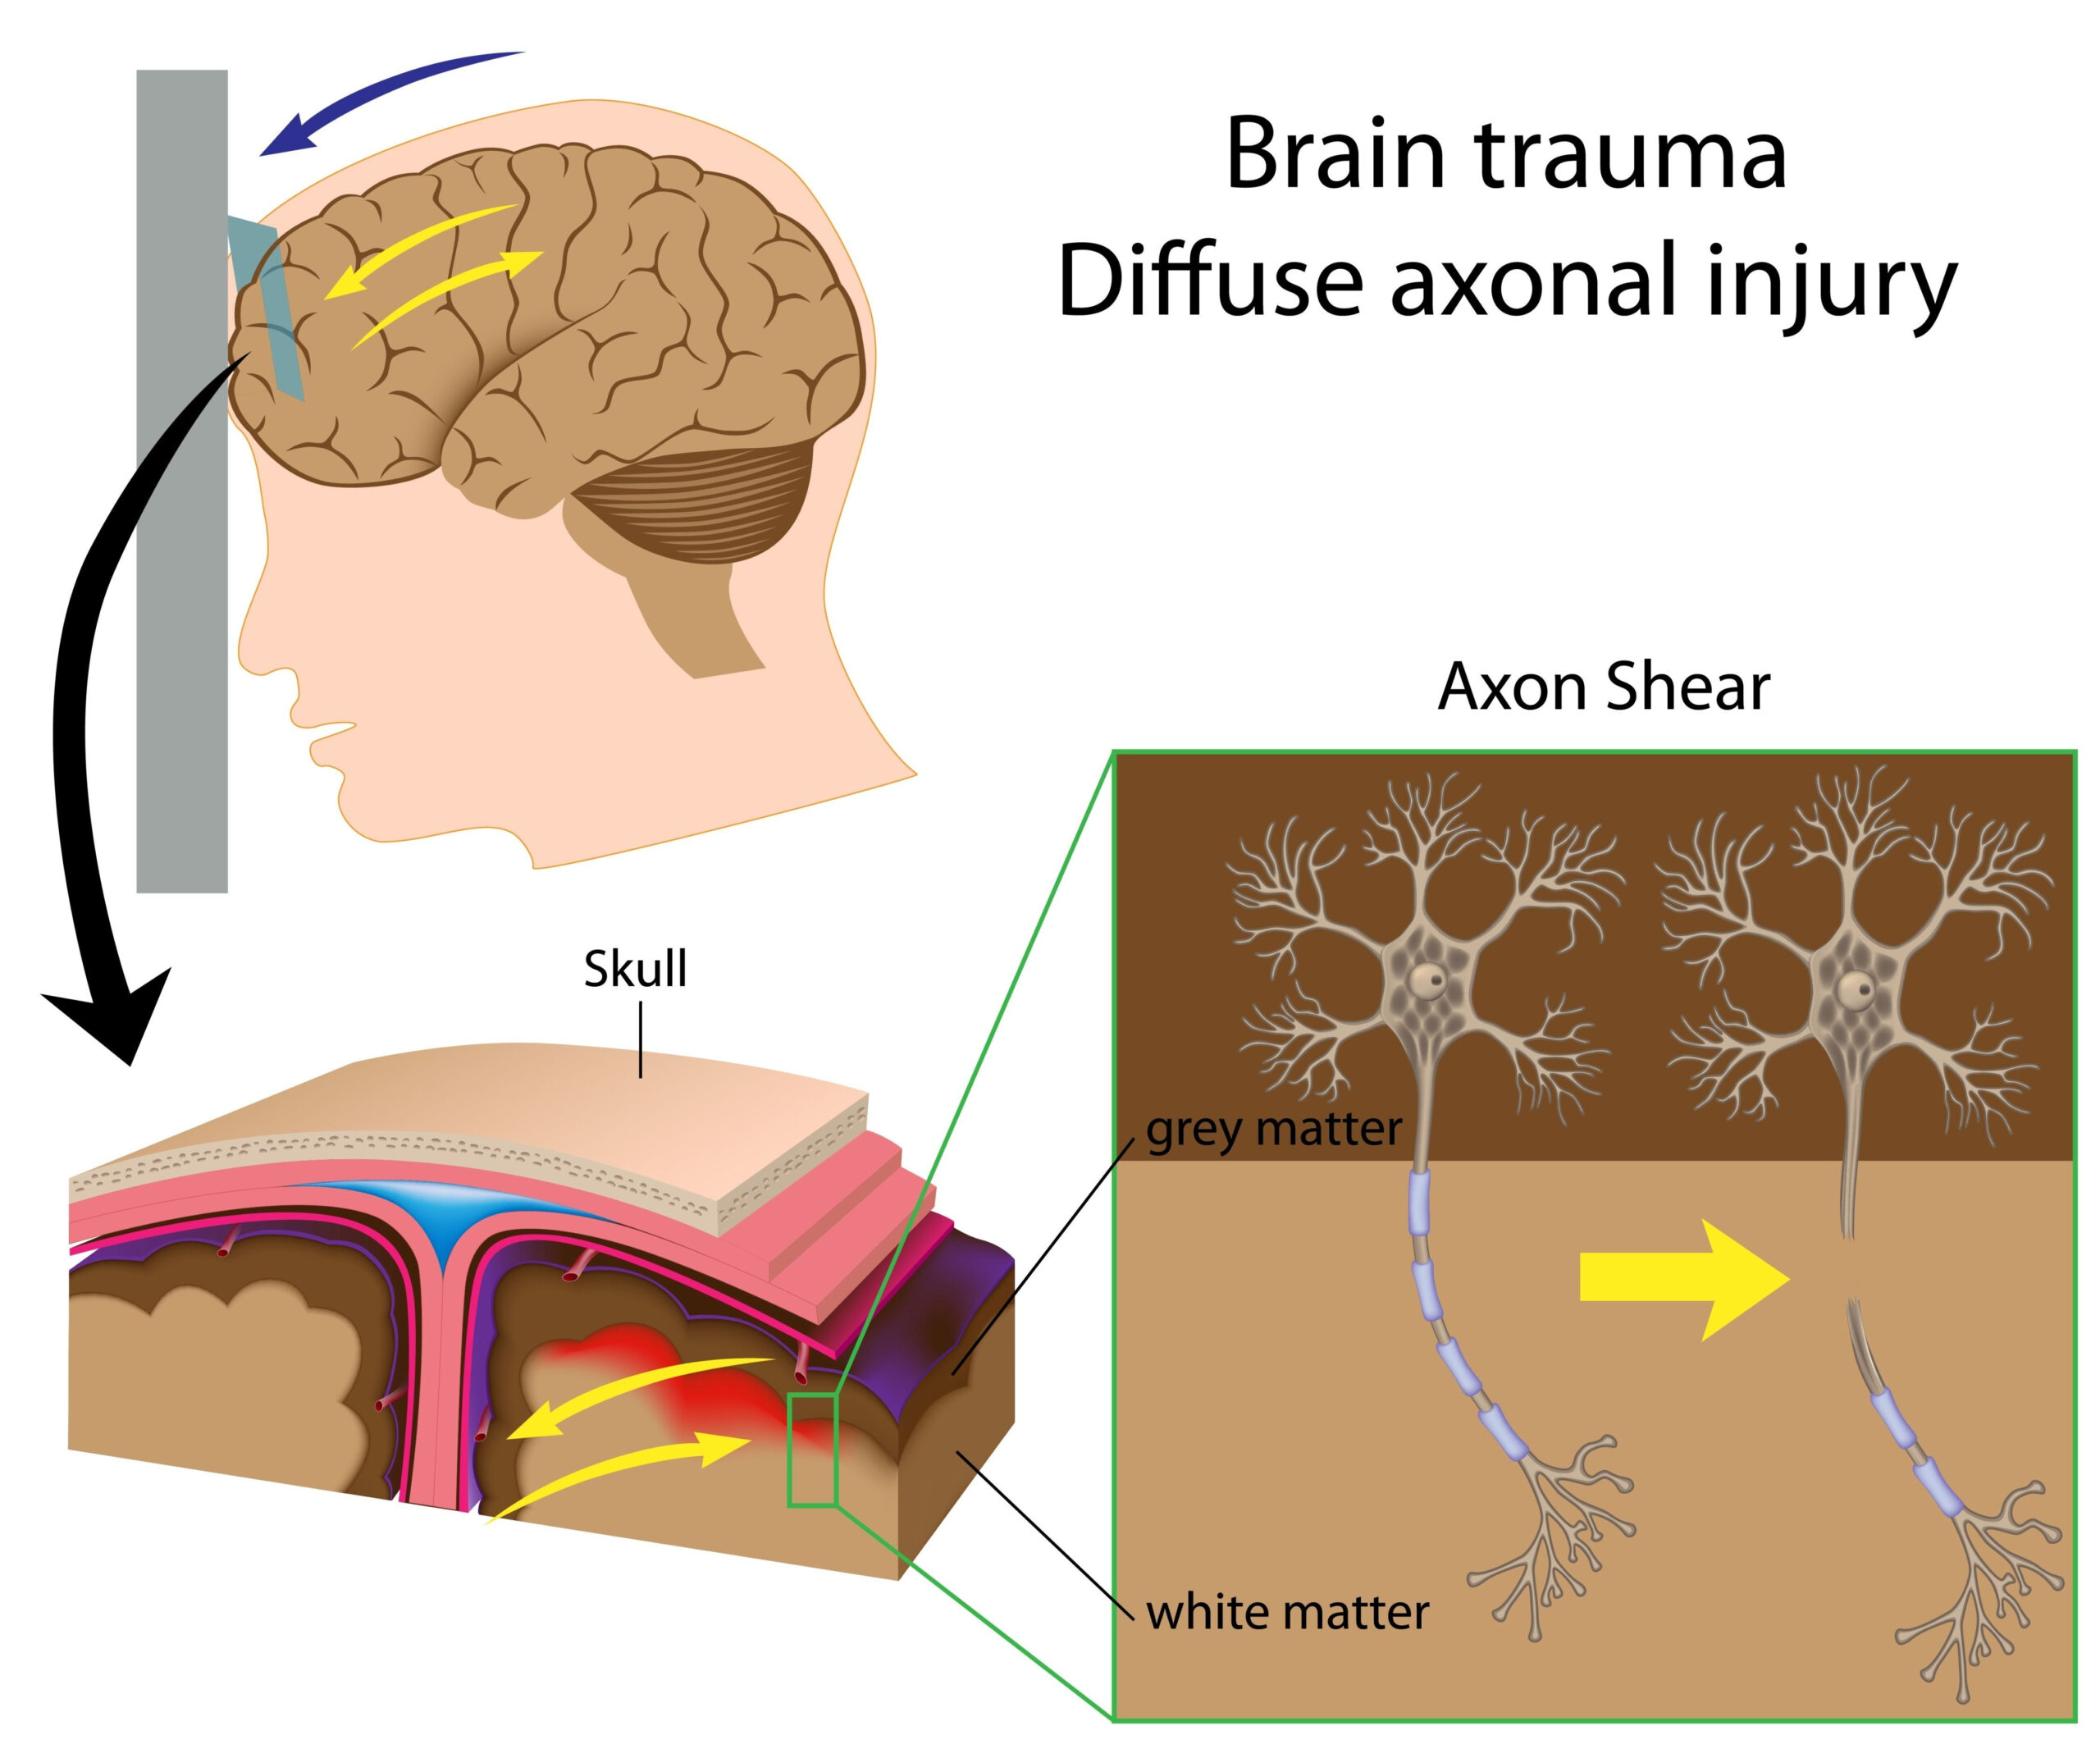
The primary aim of this research was to establish a systematic protocol for identifying cases of acute traumatic brain injury (TBI) within a comprehensive electronic medical record (EMR) system. Given the growing volume of patient data stored in academic health system data warehouses, it is critical to leverage this information effectively to enhance patient care and outcomes related to TBI.
Specifically, the research sought to achieve the following goals: first, to delineate the specific criteria and clinical indicators that constitute acute TBI; second, to develop an algorithm that could accurately parse through extensive EMR data to flag instances of TBI; and third, to ensure that the protocol could be applied uniformly across different departments and clinical settings within the health system. By creating a reliable method to retrospectively identify TBI cases, the research aimed to set the foundation for future epidemiological studies, improved clinical management protocols, and enhanced patient safety measures.
Moreover, this study aimed to refine the process of data extraction for improved specificity and sensitivity in identifying TBI cases. The intention was to address current challenges in clinical data retrieval where fragmented records can lead to misidentification or overlooked cases of brain injury. Ultimately, the research aimed to contribute to better recognition and treatment strategies for individuals affected by TBI, thereby improving overall healthcare delivery and outcomes in acute care settings.
Data Extraction and Analysis
To conduct a comprehensive analysis of acute traumatic brain injury (TBI) cases, data extraction began with a systematic review of the electronic medical records (EMR) housed within the academic health system’s data warehouse. This process entailed careful selection of relevant variables that would inform the identification of TBI instances. Key data points included demographic information, clinical presentations, diagnostic codes, and treatment interventions associated with TBI.
The initial step involved assembling a cohort of patients who presented at various clinical settings within the health system, including emergency departments and inpatient units. Utilizing the International Classification of Diseases (ICD) coding system, researchers extracted records corresponding to specific codes indicative of TBI. These codes served as a foundational component of the extraction protocol, allowing for accurate case identification. For the purposes of this study, the diagnostic codes were tailored to encompass both mild and severe forms of TBI, ensuring a comprehensive understanding of the injury spectrum.
Following the extraction of relevant records, data analysis employed both quantitative and qualitative methodologies. The quantitative aspect involved statistical techniques aimed at assessing the volume of TBI cases identified through the EMR. This included calculating incidence rates and exploring demographic subtleties, such as age distribution and gender differences. Descriptive statistics provided preliminary insights into common patterns associated with TBI cases, while inferential statistics were employed to draw broader conclusions about the links between clinical variables and patient outcomes.
On the qualitative side, clinicians reviewed a subset of cases to corroborate the accuracy of the EMR-identification process. This step was crucial, as it allowed researchers to verify that the algorithm successfully flagged genuine TBI cases rather than false positives, which could skew the results. Clinical reviews also supported the refinement of the extraction criteria, enabling adjustments based on real-world clinical nuances.
Furthermore, the analysis phase included a focus on the temporal aspects of patient presentations and outcomes. By mapping the timeline from injury to diagnosis and treatment initiation, the research was able to identify bottlenecks in care that might hinder effective intervention after TBI onset. Such temporal analysis is invaluable for informing future protocols aimed at enhancing response times and improving clinical pathways for TBI care.
The result of this data extraction and analysis was a robust dataset that not only facilitated the identification of TBI cases but also paved the way for insightful clinical inquiries. This thorough examination of EMR data formed the backbone of the upcoming results phase, where findings would be detailed and interpreted with the goal of enhancing TBI recognition and management in clinical practice.
Results and Interpretation
The analysis of the data from the electronic medical records (EMR) provided illuminating insights into the incidence and management of acute traumatic brain injury (TBI) within the academic health system. A total of 1,500 patient records were identified as meeting the criteria for TBI based on the defined diagnostic codes, yielding an incidence rate of approximately 3.5 cases per 1,000 emergency department visits. This finding underscores the prevalence of TBI among patients seeking care, highlighting the need for targeted interventions.
Demographic analysis revealed notable patterns in the data. The majority of identified cases were observed in the younger adult population, specifically those aged 18 to 35 years, accounting for about 45% of the total cases. This demographic trend aligns with existing literature that reports higher rates of TBI among younger individuals, often due to higher engagement in activities associated with risk, such as contact sports and high-risk hobbies. Additionally, a gender disparity was evident, with males representing approximately 70% of the identified cases. This finding is consistent with earlier studies that cite males as being more frequently involved in incidents leading to TBI.
The clinical characteristics of the identified TBI cases were varied, including a range of symptoms from mild concussive signs to severe cognitive deficits requiring intensive care. The dataset analysis categorized these cases based on their severity using the Glasgow Coma Scale (GCS). It was determined that about 60% of the cases fell within the mild category, while 25% were moderate and 15% classified as severe. This distribution provides critical information for understanding the spectrum of TBI severity and the associated healthcare resources that may be required for each category.
The treatment pathways for TBI patients revealed significant variability in clinical management strategies. A staggering 75% of patients classified as severe TBI were admitted to the intensive care unit (ICU) for ongoing monitoring and intervention, while those with mild cases were often managed with outpatient follow-ups. This disparity emphasizes the need for standardized care protocols that can better address the diverse needs of TBI patients across different severity levels. Moreover, the average time from injury to definitive treatment was found to be approximately 4 hours, which is critical for reducing long-term morbidity potentially associated with delayed interventions.
Temporal analysis also shed light on significant delays in the clinical management of TBI cases. A series of bottlenecks were identified, particularly at the point of diagnosis; many patients experienced a delay of over two hours before being assessed for TBI despite presenting with relevant symptoms. This finding signals a potential area for improvement in emergency clinical workflows, indicating that staff training and protocol adjustments may be necessary to facilitate quicker identification and treatment of TBIs.
Finally, clinicians engaged in qualitative reviews provided additional context to the numeric findings. Through case discussions, it became clear that there was variance in the interpretation of diagnostic criteria, leading to occasional inconsistencies in TBI identification. This feedback highlighted the importance of ongoing education and training for healthcare professionals involved in acute care settings to ensure that TBI cases are not overlooked.
The results from this comprehensive analysis of EMR data highlight critical trends and areas for future improvement in TBI recognition and management within the healthcare system. By establishing a clear profile of TBI presentations, treatment trajectories, and key delays in care, this research serves as a vital step toward enhancing clinical practice and ultimately improving outcomes for patients experiencing acute traumatic brain injuries.
Future Directions
Looking ahead, there are numerous potential avenues for further research and development that stem from the findings of this study. One primary direction is the implementation of the identification protocol across broader healthcare networks to validate its efficacy in varied clinical environments. Testing the algorithm in different hospitals or healthcare systems would help assess its adaptability and robustness, potentially leading to widespread adoption of standardized practices in TBI identification and management.
Additionally, refining the algorithm to improve its accuracy is a crucial step for future endeavors. This could involve incorporating machine learning techniques that allow the system to learn from new data inputs over time, enhancing its predictive capabilities. By continually updating the algorithm with fresh EMR data, it could better accommodate evolving medical terminologies and diagnostic criteria associated with TBI, thus keeping pace with advances in medical science and practice.
Another promising direction is to integrate patient-reported outcomes into the EMR system. By incorporating surveys or questionnaires that capture patient experiences and symptoms post-injury, researchers could create a more comprehensive understanding of TBI outcomes. This integration would also promote a holistic view of patient recovery, enabling clinicians to tailor interventions that not only address physiological aspects but also the psychological and social dimensions of TBI recovery.
Collaboration with interdisciplinary teams, including neurologists, psychologists, and rehabilitation specialists, will be vital to this ongoing research. Through combined expertise, the development of multi-faceted treatment protocols that address both immediate and long-term needs of TBI patients can be facilitated. Such collaborative efforts can also inform the creation of educational resources aimed at increasing awareness about TBI among healthcare providers, ultimately aiming to reduce diagnostic delays and improve care pathways.
Moreover, the data-driven insights gained from this study will enhance epidemiological research within the field. By developing a repository of well-characterized TBI cases, future studies could explore demographic and clinical factors leading to variations in treatment outcomes. Such studies might investigate the impact of social determinants of health on TBI management, thereby informing public health strategies and resource allocation within health systems.
Lastly, this research lays the groundwork for advocacy efforts aimed at improving TBI prevention strategies. By identifying high-risk populations and activities, targeted public health campaigns can be developed to mitigate risks associated with TBI, such as education on safer sports practices or the implementation of community-based injury prevention programs.
The findings from this study not only enhance the understanding of acute TBI’s clinical landscape but also open new pathways for research and practice that aim to improve both identification and treatment outcomes for affected individuals. By continuously evolving based on emerging data and engaging multidisciplinary collaborations, the healthcare community can significantly advance the standards of care for TBI patients.