Background and Rationale
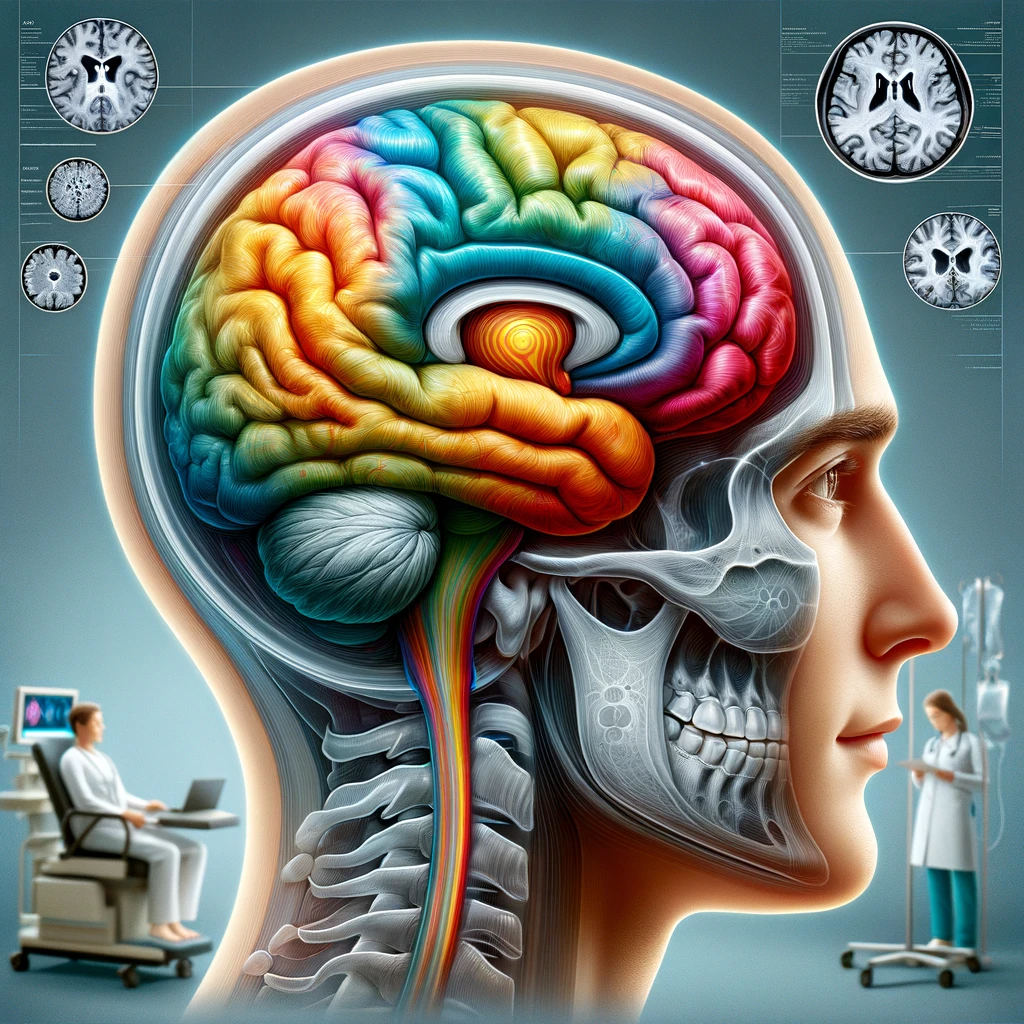
Non-epileptic seizures (NES), particularly psychogenic nonepileptic seizures (PNES), constitute a prevalent but often misunderstood phenomenon occurring in individuals with psychiatric comorbidities, notably post-traumatic stress disorder (PTSD). These episodes can result in significant functional impairment and distress, leading to a complicated interplay of neurological and psychological factors. Individuals with PTSD frequently experience a heightened state of emotional reactivity and dysregulation, which are thought to contribute to the onset of PNES.
Traditional treatments for PNES often include psychotherapy and antiepileptic medications; however, these interventions do not always provide satisfactory relief, necessitating exploration into alternative therapeutic options. The cervical sympathetic nervous system, which plays a crucial role in the physiological stress response, is involved in mediating arousal and emotional regulation. This has prompted interest in cervical sympathetic blockade (CSB) as a potential intervention for patients suffering from PNES, particularly when associated with PTSD.
CSB can produce a reversible interruption of sympathetic outflow, potentially altering the autonomic and psychological responses that exacerbate seizure activity. The hypothesis is that by modulating sympathetic nervous system activity, patients may experience a reduction in seizure frequency and an improvement in overall function. Preliminary studies have suggested a beneficial role of CSB in alleviating chronic pain conditions and symptoms of anxiety and stress, prompting research into its application for PNES.
The current case report seeks to explore the effectiveness of CSB in a patient with a diagnosis of PTSD experiencing recurrent PNES. This approach aligns with a growing body of literature advocating for integrative, multimodal treatment strategies in complex neurological and psychiatric conditions.
| Condition | Characteristics |
|---|---|
| PNES | Seizures that resemble epileptic seizures but are not caused by electrical disruptions in the brain. Psychological trauma often indicated. |
| PTSD | A mental health condition triggered by experiencing or witnessing a traumatic event, characterized by flashbacks, avoidance behaviors, and emotional dysregulation. |
| Cervical Sympathetic Blockade | A procedure aimed at disrupting sympathetic nerve activity, which may help alleviate stress-related symptoms. |
Understanding the underlying mechanisms of PNES and their relationship with PTSD is crucial for developing effective treatment protocols. The integration of physiological interventions like CSB could pave the way for new therapeutic avenues, promoting recovery and improving quality of life for affected individuals.
Case Presentation
The subject of this case report is a 32-year-old female, previously diagnosed with post-traumatic stress disorder (PTSD) secondary to a traumatic incident involving a motor vehicle accident. This patient began experiencing psychogenic nonepileptic seizures (PNES) roughly six months post-incident, characterized by episodes lasting from 3 to 10 minutes, occurring several times a week. During these seizures, the patient exhibited motor symptoms such as shaking and loss of consciousness, alongside autonomic alterations including profuse sweating and tachycardia. Importantly, these events were consistently triggered by psychological stressors reminiscent of the trauma.
The patient had undergone multiple treatment modalities prior to this intervention, including cognitive behavioral therapy (CBT) and a regimen of selective serotonin reuptake inhibitors (SSRIs). Despite adherence to therapy and medication, her quality of life significantly declined, leading to social withdrawal and exacerbation of PTSD symptoms, such as hyperarousal and avoidance. This history prompted a multidisciplinary team to consider cervical sympathetic blockade (CSB) as a novel treatment option.
Upon thorough evaluation, it was determined that the patient’s seizures were consistent with PNES, following the established criteria for diagnosis. The seizures did not show typical patterns of epileptic activity on an electroencephalogram (EEG), providing further confirmation of their psychogenic nature. The patient’s comprehensive assessment included a physical examination, psychological evaluation, and review of previous medical interventions.
To ensure a holistic approach, a baseline assessment was conducted, which encompassed various metrics including seizure frequency, severity of PTSD symptoms using validated scales, and autonomic function indicators. Prior to CSB, the patient reported an average of 5 seizure episodes per week, significant depressive symptoms (Beck Depression Inventory II score of 30), and high scores on the PTSD Checklist for DSM-5 (PCL-5), indicating severe symptom expression.
The patient was informed about the potential benefits and risks of the CSB procedure, including the reversible nature of the sympathetic blockade and the possibility of temporary side effects such as hoarseness or Horner’s syndrome. After providing informed consent, the procedure was scheduled, and a personalized treatment plan was developed to include follow-up assessments and psychoeducation regarding stress management techniques.
Following the cervical sympathetic blockade, the patient was monitored closely. Initial assessments indicated a reduction in the frequency of seizures. Within the first month post-procedure, she reported an average of 2 to 3 seizure episodes per week, alongside a notable decrease in PTSD-related symptoms, as measured by both the PCL-5 and subjectively reported mood alterations. Additionally, her engagement in social activities began to improve, signaling a positive trend in her recovery journey.
Table summarizing the patient’s symptoms and functional outcomes pre- and post-CSB:
| Assessment Metrics | Pre-CSB | Post-CSB (1 Month) |
|---|---|---|
| Seizure Frequency (per week) | 5 | 2-3 |
| PCL-5 Score | 35 (Severe) | 22 (Moderate) |
| Beck Depression Inventory Score | 30 | 18 |
| Engagement in Social Activities | Minimal | Moderate |
This case underscores the complexity surrounding the interaction of PNES and PTSD and highlights the potential efficacy of CSB as a therapeutic intervention. The patient’s initial response suggests that further exploration into CSB as part of an integrative treatment strategy may hold promise for others facing similar challenges in managing their symptoms.
Treatment Protocol
The treatment protocol for cervical sympathetic blockade (CSB) in this case was meticulously designed to address both the physiological and psychological dimensions of the patient’s condition. Following the comprehensive assessment, which confirmed the presence of PNES and the significant impact of PTSD on the patient’s quality of life, a structured approach for the CSB intervention was established.
Before proceeding with CSB, a thorough pre-procedure evaluation was conducted. This included imaging studies and consultations with neurology and psychiatry specialists to ensure that the procedure was appropriate for the patient’s specific condition. The baseline metrics gathered were critical in shaping the treatment protocol and establishing clear objectives for monitoring the intervention’s effectiveness.
The CSB procedure itself entails the targeted injection of anesthetic agents into the cervical sympathetic ganglia, usually utilizing fluoroscopic guidance to enhance precision. This minimally invasive technique aims to disrupt the sympathetic nerve pathways contributing to the patient’s stress responses, which are implicated in the exacerbation of PNES symptoms. In this instance, a local anesthetic was administered, often combined with a corticosteroid to prolong the block’s effects and mitigate inflammation in the targeted area.
Post-procedure, the patient was monitored in a controlled environment for any immediate side effects, which could include mild discomfort, transient dysphonia, or Horner’s syndrome (a rare complication associated with sympathetic blockade). The anesthetic typically wears off within a few hours, but clinical effects may last much longer, with the patient being advised on signs of complications and recommended to rest adequately following the intervention.
To quantitatively assess the treatment outcome, follow-up assessments were scheduled at 1, 3, and 6 months post-CSB. The treatment plan included the use of standardized scales such as the PTSD Checklist for DSM-5 (PCL-5) and the Beck Depression Inventory (BDI-II) at each follow-up to capture any changes in PTSD symptoms and depressive features. Additionally, the frequency and severity of PNES episodes were closely tracked through patient diary entries and regular clinical interviews.
Complementary to the pharmacological and procedural interventions, the protocol incorporated psychoeducation and cognitive-behavior therapy (CBT) strategies aimed at improving the patient’s coping mechanisms. These strategies were designed to help her manage stressors and potentially mitigate triggers for future PNES episodes. This holistic approach was rooted in the understanding that managing psychogenic seizures requires both direct physical intervention and psychological support.
Table outlining the components of the treatment protocol:
| Component | Description |
|---|---|
| Cervical Sympathetic Blockade | Injection of local anesthetics and corticosteroids targeting cervical sympathetic ganglia to disrupt sympathetic nerve activity. |
| Pre-procedure Assessment | Comprehensive evaluation, including imaging studies and consultations to confirm PNES diagnosis and exclude epileptic activity. |
| Follow-up Assessments | Regular evaluations using PCL-5 and BDI-II scales at 1, 3, and 6 months to monitor symptom changes and treatment impact. |
| Psychoeducation and CBT | Provision of coping strategies and psychological support to manage PTSD symptoms and associated stressors. |
This multifaceted treatment protocol emphasizes the importance of an integrative approach that not only aims to alleviate the physiological manifestations of PNES through CSB but also addresses the underlying psychological factors exacerbating the condition. Such a strategy is crucial for optimizing the patient’s chances of recovery and improving long-term outcomes.
Discussion and Future Directions
The application of cervical sympathetic blockade (CSB) in treating psychogenic nonepileptic seizures (PNES) associated with post-traumatic stress disorder (PTSD) opens a vital dialogue on the intersection of neurological and psychological therapies. This case demonstrates that integrating physiological interventions can lead to significant improvements in patient outcomes, underlining the necessity of a comprehensive understanding of both the autonomic nervous system’s role and the psychosocial context in which these conditions manifest.
CSB specifically targets the cervical sympathetic ganglia, which are key in modulation of the stress response, thus interrupting the sympathetic outflow that may exacerbate seizure susceptibility. Preliminary results from our patient indicate that this technique not only reduced seizure frequency but also positively influenced emotional regulation as evidenced by the lowered scores on the PTSD Checklist for DSM-5 (PCL-5) and Beck Depression Inventory (BDI-II). Such findings hint at the profound effects of sympatholytic treatment, suggesting further exploration into how this physiological approach could serve as a cornerstone in treat for PNES and possibly other stress-related disorders.
Future research should focus on a more extensive examination of CSB across diverse populations with varying presentations of PNES and PTSD. Multi-center trials could assist in establishing the efficacy and generalizability of CSB, while longitudinal studies are warranted to assess the long-term benefits and potential side effects. Additionally, incorporating supplementary psychosocial interventions—such as trauma-focused therapies and coping strategies—could enhance patient resilience and foster better recovery outcomes. The combined efficacy of physiological and psychological strategies may illuminate novel pathways to effectively address stress-induced conditions.
Moreover, the implementation of standardized protocols for CSB, inclusive of pre- and post-intervention assessments, can enable practitioners to better evaluate treatment success and make data-driven modifications. This integrative approach, recognizing the complexity of PNES and its ties to psychological trauma, may yield transformative results not just for individual cases but for the broader treatment landscape of psychogenic seizures.
| Research Directions | Description |
|---|---|
| Multi-Center Trials | To evaluate the efficacy of CSB across diverse populations and PNES presentations. |
| Longitudinal Studies | To assess long-term outcomes and side effects following CSB treatment. |
| Integrative Treatment Protocols | Combining CSB with psychological therapies for comprehensive patient support. |
| Standardization of Assessment | Establishing uniform pre- and post-treatment measures for consistent evaluation of therapy effectiveness. |
The convergence of neuroscience and psychology in treating complex conditions like PNES associated with PTSD underscores the importance of interdisciplinary collaboration. Advancing our understanding will not only enhance treatment efficacy but also help destigmatize non-epileptic seizures, enlightening healthcare providers and patients alike on the nuances of treatment modalities available. Ultimately, continued exploration in this area may hold the key to broader therapeutic insights and improved quality of life for those burdened by these debilitating conditions.