Significance of Mild TBI in Older Adults
Mild traumatic brain injury (TBI) in older adults often receives less attention compared to more severe forms of brain injury; however, its implications can be significantly profound. As the population ages, the incidence of mild TBI in older adults is on the rise, driven largely by an increase in falls, which are the leading cause of such injuries in this demographic. The Glasgow Coma Scale (GCS), which is commonly used to assess the severity of head injuries, classifies mild TBI as having a GCS score between 13 and 15. Although a “mild” designation suggests a lower risk of severe outcomes, this can be misleading, particularly among older adults who often present with comorbid conditions that can complicate recovery.
Numerous studies have shown that older adults with mild TBI are at a heightened risk for a variety of adverse outcomes, including prolonged hospitalization, cognitive decline, and even increased mortality rates compared to their younger counterparts. Aging can exacerbate the effects of even mild injuries due to factors such as decreased brain reserve, variations in the healing process, and the possible presence of neurodegenerative disorders. Research indicates that older patients may exhibit different clinical manifestations and complications that are not always immediately apparent at the time of injury.
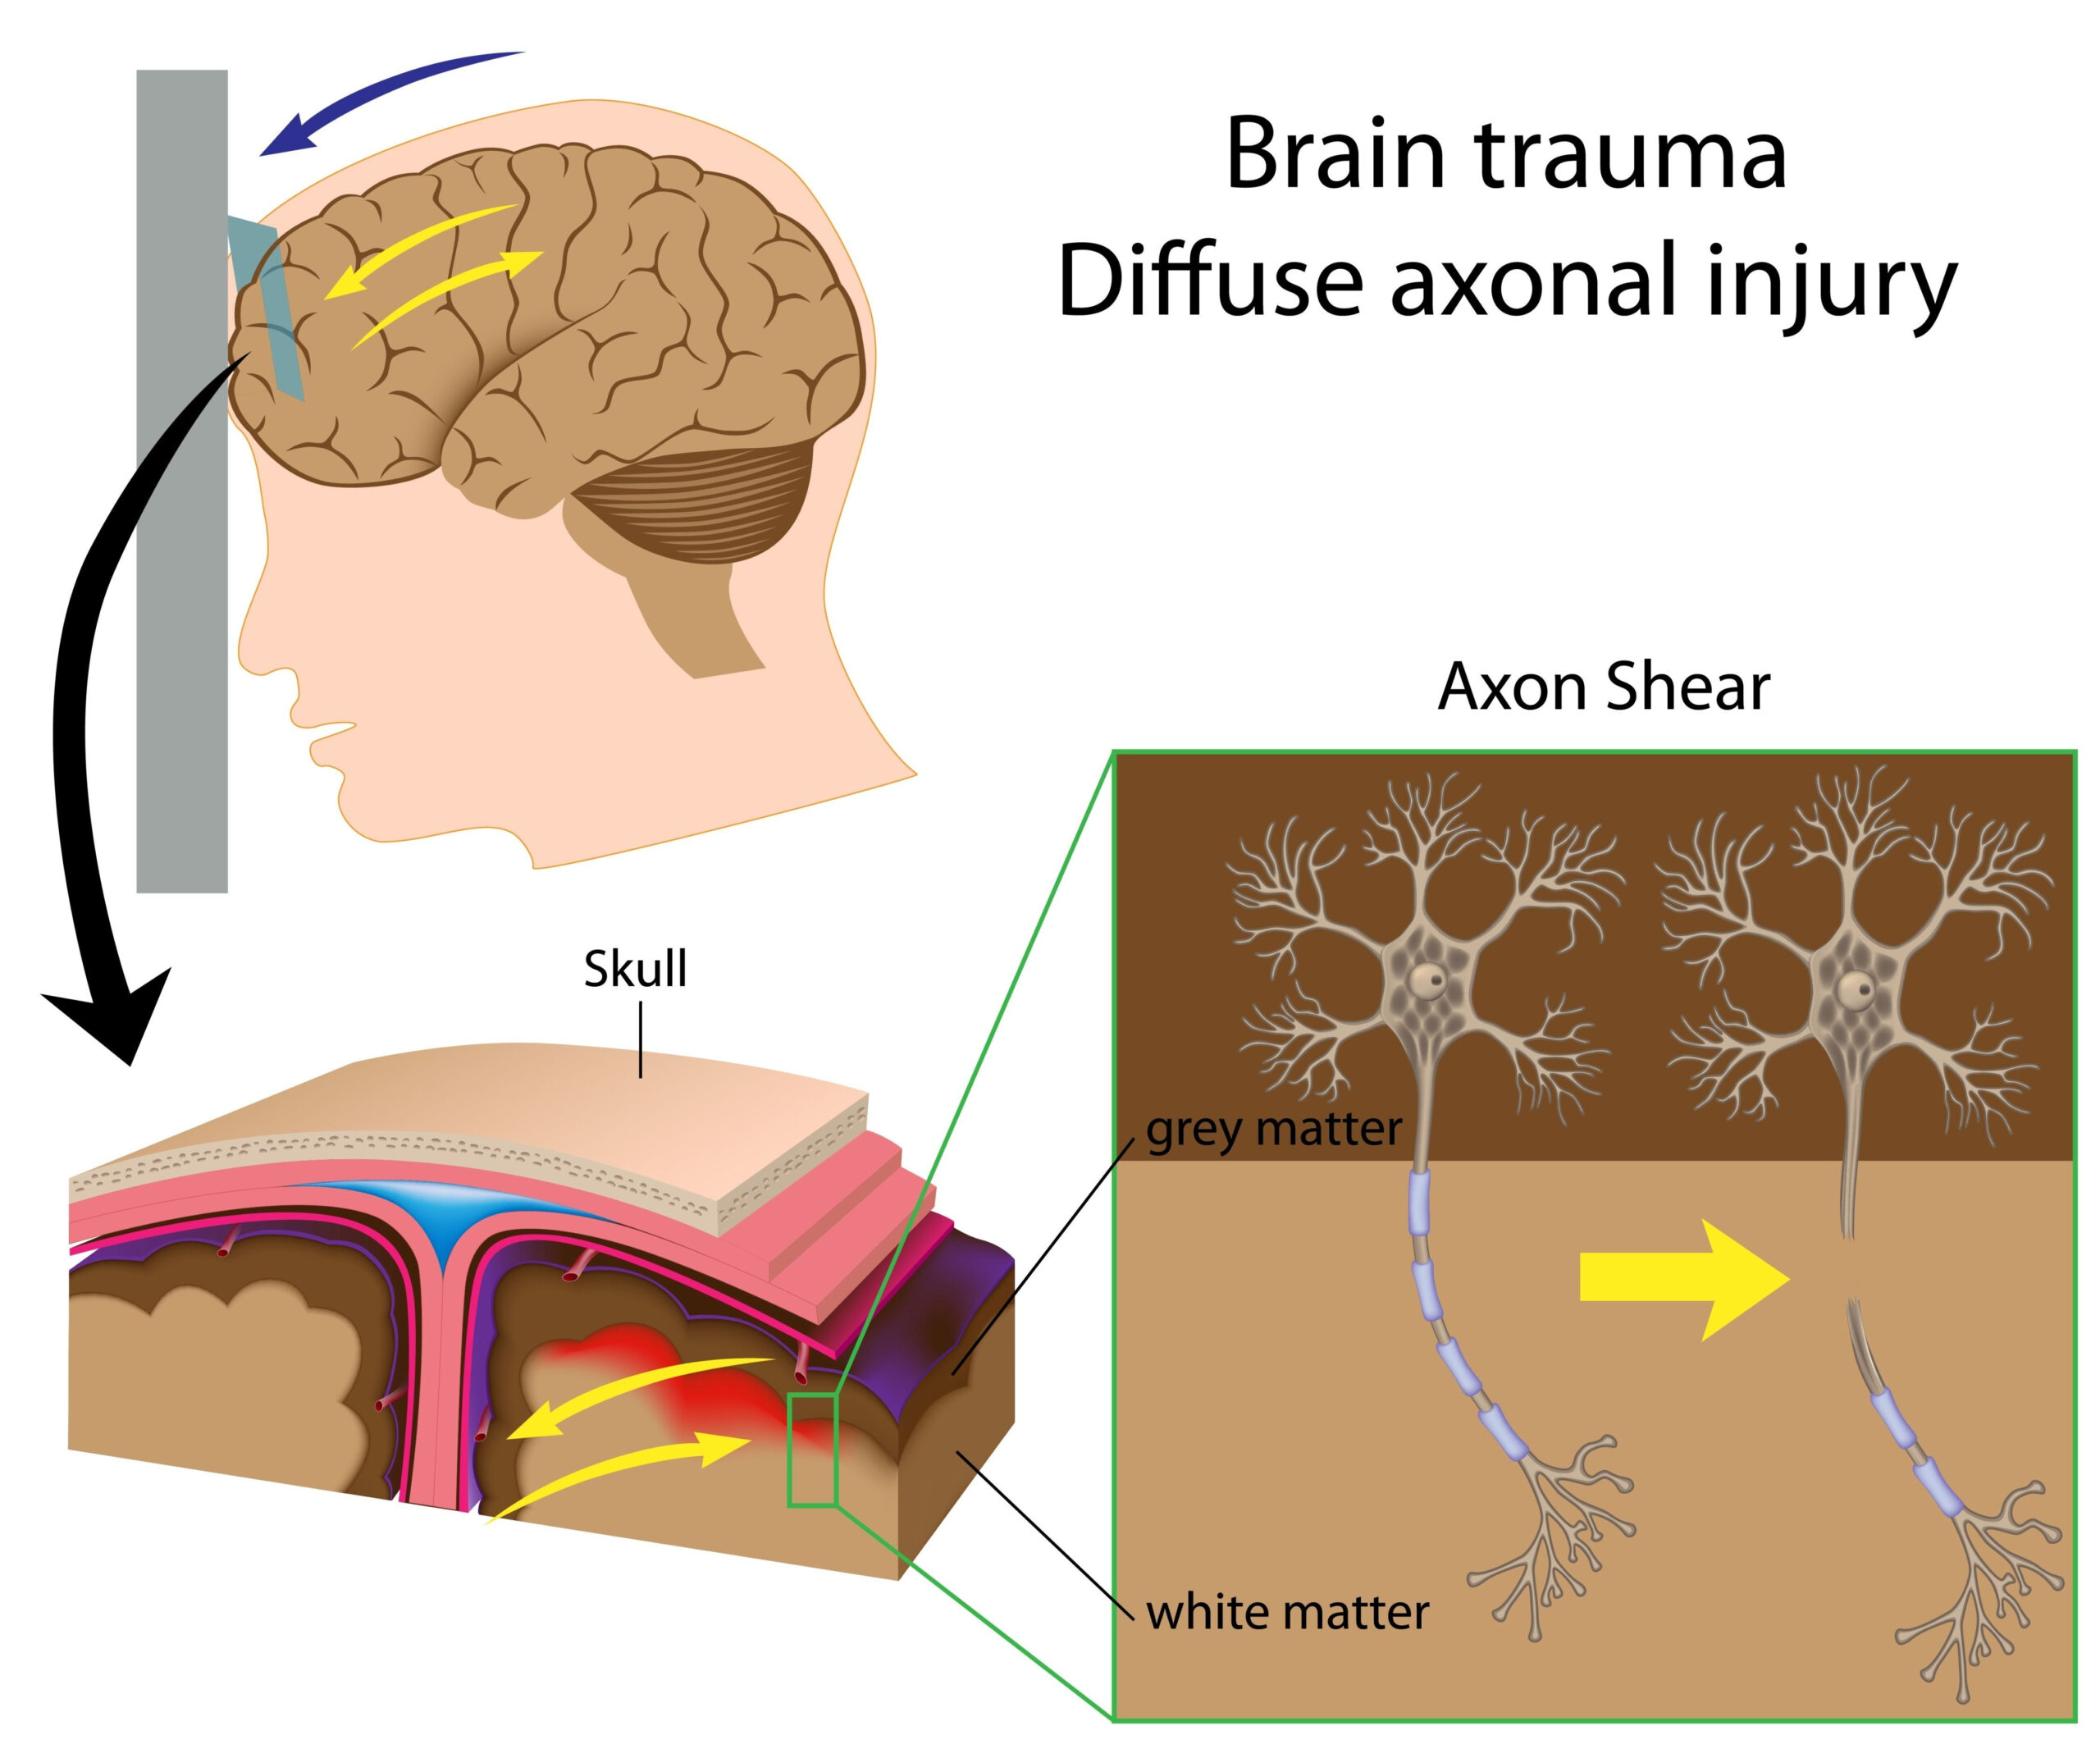
The presence of acute subdural hematoma—a condition where blood collects between the brain’s surface and its outer covering—often complicates the clinical picture for older adults. Despite the mild classification based on GCS, studies reveal that older patients with even minor traumatic events can develop acute subdural hematomas that significantly increase morbidity and mortality risks. This underscores the need for heightened vigilance and care in the management of mild TBI in older populations, as the seemingly benign nature of the injury can conceal serious underlying conditions that require immediate attention.
Collectively, the growing evidence suggests that classifying TBI solely based on GCS without considering the patient’s age and associated factors may lead to underestimating the potential risks. Thus, clinicians are urged to adopt a more nuanced approach when evaluating older patients with mild TBI. This perspective emphasizes the importance of comprehensive assessment protocols that take into account not only the injury’s severity as indicated by assessment scales but also the patient’s overall health status and life situation. Doing so can lead to improved outcomes and better resource allocation in clinical settings.
Patient Selection and Data Collection
The selection of patients for this study was a meticulous process, undertaken across multiple hospital sites to ensure a comprehensive understanding of the outcomes associated with mild TBI in older adults. The study focused on individuals aged 65 and above who presented to the emergency department following a mild traumatic brain injury. Participants were included based on criteria that indicated the presence of an acute subdural hematoma as confirmed through neuroimaging techniques such as CT scans. This particular focus was essential to unravel the complexities of mild TBI when comorbidities such as vascular conditions or neurodegenerative diseases are common.
Data collection was systematic and comprehensive, encompassing demographic information, clinical presentations, GCS scores at the time of admission, and subsequent management approaches. Detailed medical histories were captured, focusing on pre-existing conditions that are typically more prevalent in older populations, including hypertension, diabetes, and previous episodes of TBI. The goal was to construct a robust dataset that could facilitate the identification of patterns relating to demographics and clinical outcomes.
Furthermore, clinicians conducted follow-up evaluations that included cognitive assessments and functional outcome measures, utilizing established scales to track recovery trajectories over time. Importantly, the study team ensured that data collection adhered to strict ethical standards, obtaining informed consent from all participants or their legal representatives. This comprehensive framework allowed for a reliable analysis of not just immediate effects but long-term consequences associated with mild TBI and acute subdural hematoma in older adults.
Quantitative analysis methods were applied to evaluate the correlations between various risk factors and patient outcomes. This included statistical explorations of mortality rates, lengths of hospital stay, and potential complications, thereby addressing the multifaceted nature of how older adults respond to mild TBIs. By leveraging a multicenter approach, diverse clinical practices and patient management strategies could be examined, contributing to the overall validity and reliability of the findings.
Outcomes and Risk Factors
The outcomes arising from mild traumatic brain injury (TBI) in older adults, particularly those with accompanying acute subdural hematoma, present a complex interplay of factors that can significantly impact recovery and survival. Initial observations from the study indicate that even patients categorized as having “mild” injuries by the Glasgow Coma Scale (GCS) exhibit a concerning array of potential complications. Notably, older adults demonstrate higher rates of prolonged hospitalization, cognitive impairment, and elevated mortality risk when compared to younger individuals with similar GCS scores.
In particular, the presence of acute subdural hematoma in this cohort raises the stakes. While acute subdural hematomas are often associated with falls or minor head trauma, they often lead to detrimental outcomes in older patients. This condition can escalate the severity of symptoms and complicate the clinical course, primarily due to age-related physiological changes. Research has revealed that older adults frequently have diminished cerebral reserve and altered hemostatic responses, which can hinder the brain’s ability to cope with injury and recovery. As such, immediate and ongoing assessment procedures are essential for identifying those at highest risk for adverse outcomes.
The study identified several key risk factors correlating with poorer outcomes in older patients. Advanced age, particularly patients over 75 years, was consistently associated with negative prognoses. Comorbidities such as hypertension, diabetes, and previous cerebrovascular accidents were prevalent among patients, further complicating their clinical scenarios. The cumulative effect of multiple comorbid conditions can lead to a decline in cognitive function, mobility issues, and an overall reduced capacity for rehabilitation. These findings indicate that a multidimensional understanding of patient health is vital in predicting outcomes following a mild TBI.
Moreover, the length of hospital stay emerged as another crucial outcome indicator. Patients who presented with abnormal findings on neuroimaging—including but not limited to, subdural hematomas—often required extended hospitalization, primarily for monitoring and management of complications. Additionally, the nursing care provided during hospitalization has critical implications for recovery trajectories. The environment, combined with the attentiveness of healthcare professionals, influences rehabilitation outcomes profoundly.
Further complicating the scenario is the cognitive assessment performed during the follow-up of these patients. Existing literature suggests that older adults recovering from TBI may face accelerated cognitive decline, manifesting as memory issues or trouble with executive functioning, which could hinder their independence and overall quality of life. It is essential for clinicians to consider these cognitive outcomes seriously, as they often constitute a significant component in the long-term recovery process for older adults.
The outcomes of mild TBI alongside acute subdural hematoma in older adults indicate a need for focused intervention and monitoring strategies tailored specifically for this demographic. By acknowledging the various risk factors and recognizing the nuanced clinical presentations unique to aging populations, healthcare providers can develop more effective management plans aimed at improving patient trajectories and minimizing adverse outcomes.
Recommendations for Clinical Practice
Given the significant risks associated with mild traumatic brain injury (TBI) in older adults, clinicians must adopt a comprehensive and proactive approach to patient management. Immediate evaluation should extend beyond GCS scores, incorporating detailed patient histories and clinical assessments to identify individuals at higher risk for complications. The presence of acute subdural hematomas should be closely monitored, as even minor injuries can escalate into serious conditions, especially in older patients.
It is imperative that emergency departments implement standardized protocols for evaluating older adults presenting with mild TBI. This includes utilizing advanced neuroimaging techniques for timely identification of acute subdural hematomas and other concerning pathologies. Patients should receive thorough assessments of their comorbid conditions, as these can heavily influence outcomes and recovery trajectories. For instance, a comprehensive geriatric assessment that evaluates mobility, cognitive status, and functional independence should be integrated into the standard evaluation process for this demographic.
Furthermore, follow-up care is crucial. Older adults who experience mild TBI should be scheduled for regular cognitive and physical assessments to monitor recovery and identify any emergent issues promptly. Referral to rehabilitative services should be considered early in the treatment process, as timely interventions can help mitigate long-term cognitive decline and functional impairment. Occupational therapy and physical therapy can play key roles in facilitating the recovery of independence and quality of life.
Clinicians should also pay careful attention to patient education regarding fall prevention strategies, which is especially pertinent given that falls are a leading cause of mild TBI in the elderly. Providing resources and guidance on home safety modifications, balance exercises, and community resources tailored for older adults can greatly assist in reducing the incidence of future injuries.
Collaboration among healthcare teams is essential in managing these patients effectively. Multidisciplinary approaches that include neurologists, geriatricians, rehabilitation specialists, and nursing staff can enhance the quality of care. Regular case reviews and shared decision-making can ensure that all aspects of an older patient’s health are considered, optimizing treatment plans and post-hospitalization care.
Monitoring long-term outcomes is also vital. The collection of data on recovery trajectories, cognitive function, and quality of life should be an ongoing practice. This not only contributes to individual patient care but also aids in broader research efforts aimed at understanding the implications of mild TBI in older adults. Ultimately, fostering an environment of diligence, interdisciplinary cooperation, and patient-centered care can significantly improve prognoses for this vulnerable population.