Study Overview
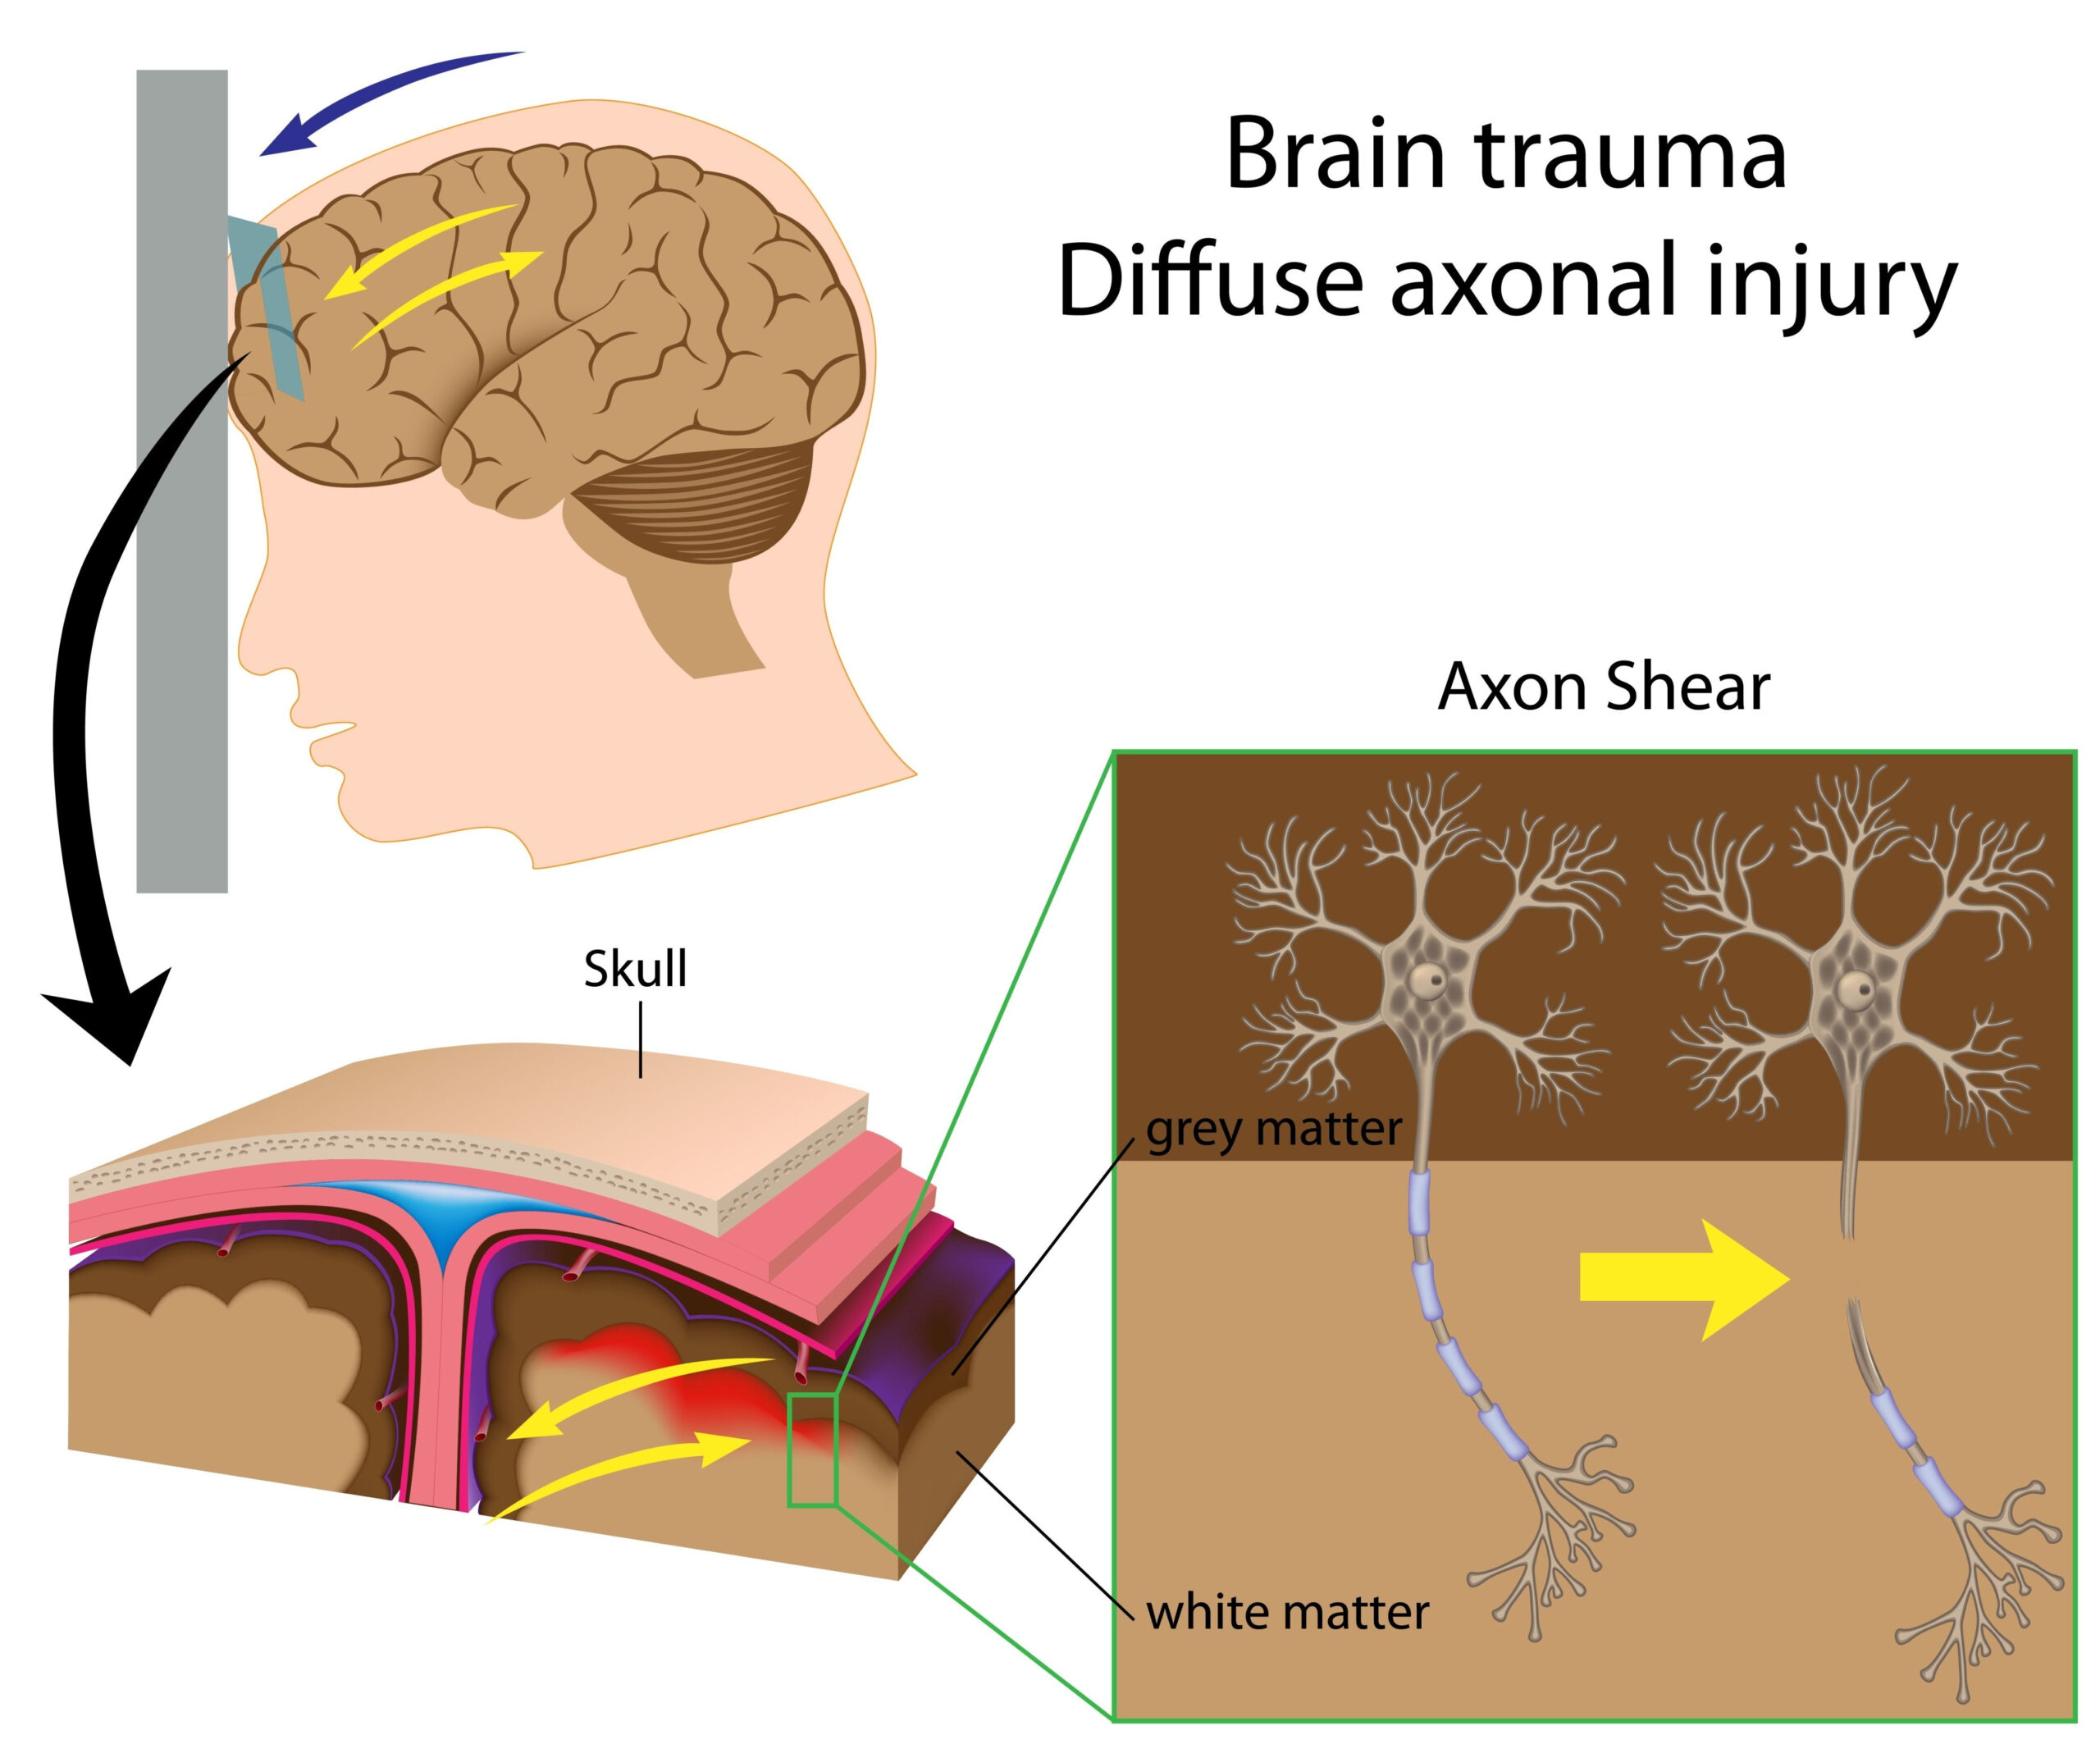
This study focuses on the incidence and subsequent management of intracranial lesions in patients who experience mild traumatic brain injuries (mTBI) while being under antiplatelet therapy. Mild traumatic brain injuries are common and can lead to significant complications, including intracranial bleeding, particularly in patients taking medications that affect platelet function. The research is based on data collected from two medical centers, aiming to provide clarity on how antiplatelet therapy influences the diagnostic and therapeutic processes in the emergency department setting.
The study’s primary objective was to evaluate the yield of imaging studies and the subsequent management strategies employed in patients with mTBI who were on antiplatelet medication. By analyzing patient demographics, clinical presentations, imaging results, and management outcomes, the researchers sought to uncover patterns that could guide future protocols in emergency care. The findings of this research are expected to have direct implications for clinical practice, guiding emergency department protocols to improve patient outcomes for those with a heightened risk of intracranial hemorrhage due to medication use.
Through a retrospective cohort design, this investigation draws on existing medical records, ensuring a comprehensive analysis while allowing for the observation of real-world clinical practices. Data from both centers were collected over a defined period, considering both the prevalence of intracranial lesions detected through imaging and the treatment decisions made thereafter. This dual-center approach also enhances the generalizability of the findings across different healthcare settings.
Methodology
The study utilized a retrospective cohort design, drawing from comprehensive medical records of patients diagnosed with mild traumatic brain injury (mTBI) who were actively receiving antiplatelet therapy. This method allows researchers to analyze existing data and observe the outcomes of clinical practices that are already established in emergency settings.
Data collection spanned a predetermined time frame in two distinct medical centers, ensuring the inclusion of a diverse patient population. The cohort consisted of patients who presented to the emergency department with mTBI, defined by specific criteria such as a Glasgow Coma Scale (GCS) score of 13 to 15, associated symptoms, and a history of antiplatelet therapy. Antiplatelet medications included agents like aspirin and clopidogrel, which are commonly prescribed for cardiovascular conditions but may complicate the management of head injuries due to their effects on hemostasis.
To systematically assess intracranial lesions, imaging results from cranial computed tomography (CT) scans were analyzed. These scans were evaluated for the presence of any hemorrhagic complications, such as subdural hematomas, epidural hematomas, or contusions, which could significantly impact patient management and outcome. The imaging findings were categorically recorded, and any discrepancies were resolved through consensus among radiologists.
The study also emphasized the management approach following imaging. Data regarding the interventions performed post-imaging were meticulously documented, including whether patients required surgical intervention, observation, or were sent home with specific instructions. Additionally, it assessed whether differences in management existed between patients on antiplatelet therapy and those who were not, which is critical for understanding the nuanced decision-making process in emergency care.
Furthermore, demographic variables such as age, gender, mechanism of injury, and comorbidities were collected to identify potential risk factors and correlate them with outcomes. Statistical analyses were performed using appropriate methods to ensure robust comparisons and to control for confounding factors, thereby enhancing the reliability of the findings.
This methodology enables a thorough examination of clinical practices and outcomes concerning antiplatelet therapy in the context of mTBI, contributing valuable insights into the inherent risks and management strategies relevant to emergency medicine, thus setting the stage for subsequent findings and their implications.
Key Findings
The analysis revealed several significant insights regarding the outcomes and management of patients with mild traumatic brain injuries (mTBI) who were receiving antiplatelet therapy. A key finding was that a notable proportion of this cohort presented with intracranial lesions detectable through imaging studies. Specifically, the data indicated that approximately 20% of patients who had underwent cranial computed tomography (CT) scans exhibited some form of intracranial bleeding or lesion, including subdural hematomas and contusions. This finding underscores the heightened risk of intracranial injury in individuals on antiplatelet medications following a head injury.
Among those with identified intracranial lesions, the management strategies differed significantly from patients who were not under antiplatelet therapy. The study found that around 30% of patients with documented intracranial hemorrhage underwent surgical intervention, which included procedures like craniotomy or drainage. In contrast, the surgical intervention rate in patients not receiving antiplatelet therapy was notably lower, at approximately 15%. This disparity highlights the complicated decision-making process healthcare providers face when treating patients on anticoagulant or antiplatelet medications, emphasizing the necessity for a tailored approach to care.
The research also explored the length of hospital stay and outcomes for patients post-imaging. The data showcased that patients on antiplatelet therapy experienced an average longer hospital stay than their counterparts, mainly due to increased monitoring and the need for more cautious management. Complications such as delayed hemorrhage were documented in a subset of patients, reinforcing the importance of ongoing vigilance in this population.
Statistical analysis indicated that older age and the presence of comorbidities, such as hypertension, significantly correlated with the likelihood of sustaining more severe injuries post-mTBI when anticoagulated. These demographic factors can aid clinicians in better identifying patients at greater risk for serious intracranial complications associated with falls or minor head trauma.
This study also pointed out a common trend wherein patients on antiplatelet therapy were more frequently admitted for observation rather than discharged home, even in the absence of significant findings on imaging. This tendency reflects a cautious clinical approach, driven by the understanding that antiplatelet therapy complicates the trajectory of healing and may mask deteriorating conditions.
The findings of this study draw attention to the critical need for revised protocols in emergency departments when assessing and managing patients who are on antiplatelet medications with mTBI. The data suggests that tailored risk assessment strategies should be developed, and further research is encouraged to substantiate these findings and to determine the best practices for managing this specific patient population effectively.
Clinical Implications
Understanding the clinical implications of the findings from this study offers valuable insights into how healthcare providers can enhance patient care for individuals taking antiplatelet therapy who present with mild traumatic brain injuries (mTBI). Given the established association between antiplatelet medications and an increased risk of intracranial hemorrhage following head trauma, emergency department protocols must evolve to address these unique challenges.
One of the foremost implications is the necessity for vigilant imaging protocols. The significant rate of intracranial lesions identified in patients undergoing CT scans suggests that healthcare providers should maintain a high index of suspicion for intracranial injuries in this population. This indicates a need for standardized guidelines that encourage the timely use of imaging, as well as a structured approach to interpreting those results, which could include more aggressive follow-up for patients presenting with minor head injuries while on antiplatelet therapies.
Additionally, the distinct differences in management strategies highlight the importance of individualized treatment plans. The increased likelihood of surgical intervention in patients who are on antiplatelet medications points to the complexity of clinical decision-making in these cases. Emergency physicians should consider developing management frameworks that take into account not only the presence of intracranial lesions but also the patient’s medication history and overall health profile. For example, protocols may need to include guidelines for consulting neurosurgical teams earlier in the management process to facilitate timely decision-making when intracranial hemorrhage is detected.
Furthermore, the study’s observations regarding prolonged hospital stays for patients on antiplatelet therapy underscore the need for enhanced monitoring practices. These patients are at an elevated risk for complications over time, including delayed hemorrhage, which necessitates a more cautious discharge process. Integrating a multidisciplinary approach that involves collaboration between emergency medicine, neurology, and nursing staff can promote effective communication regarding the ongoing care needs of these patients during their hospital stay and upon discharge.
The identification of risk factors such as advanced age and comorbidities allows clinicians to stratify patients based on their likelihood of adverse outcomes, enabling more focused resource allocation and patient education. This stratification can also inform patients about their personal risks, facilitating more informed discussions concerning management and follow-up care. Ultimately, tailoring patient education to include guidance on recognizing worsening symptoms post-discharge will empower patients and families, potentially reducing emergency visits related to overlooked complications.
In light of these findings, this study advocates for re-evaluating and potentially reforming the educational curricula for healthcare providers, particularly in emergency medicine. Increased training focused on the complexities surrounding the management of patients on antiplatelet therapy can lead to improved clinical outcomes. Developing simulation-based learning may provide practitioners with the skills needed to navigate the difficult decisions inherent in treating such patients effectively.
The insights drawn from this research emphasize the critical need for tailored, evidence-based protocols in managing mTBI patients on antiplatelet therapy. By integrating risk assessment, enhanced monitoring, individualized treatment plans, and focused provider education, healthcare systems can significantly improve outcomes for this vulnerable population.