Neurophysiological Mechanisms
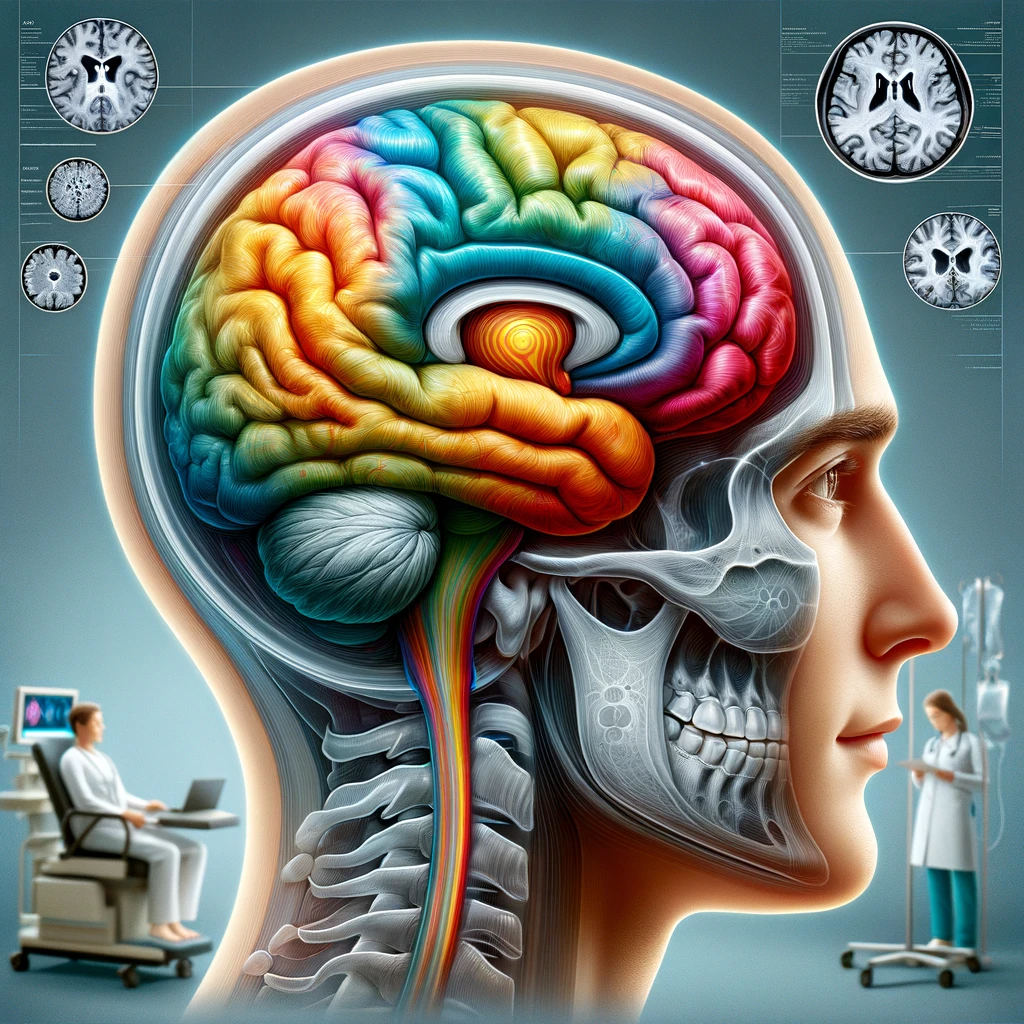
The neurophysiological mechanisms underlying functional movement disorders (FMDs) reveal a complex interplay between various brain regions and circuits. Research has shown that FMDs often manifest as abnormal motor control that is typically not linked to identifiable neurological damage. Instead, these disorders may arise from dysfunctions in the way the brain processes and coordinates movement. For instance, transcranial magnetic stimulation (TMS) studies have suggested that the primary motor cortex, which is crucial for initiating voluntary movements, may exhibit abnormal activity patterns in individuals with FMDs. This altered cortical excitability is indicative of a breakdown in the typical functioning of neural pathways involved in movement generation.
In addition to the primary motor cortex, there is growing evidence that areas such as the premotor cortex, supplementary motor area, and even deeper brain structures like the basal ganglia and thalamus may play a role in these disorders. These regions are integral to planning and executing movements, and their dysfunction could result in the characteristic motor symptoms seen in FMDs, including tremors, dystonia, and involuntary spasms.
Neuroimaging techniques, including functional MRI and positron emission tomography, have further elucidated the neural correlates of FMDs. These studies indicate that there may be altered connectivity within the brain’s motor networks, disrupting the normal flow of information required for coordinated movement. Specifically, hyperactivity in certain areas could indicate a compensatory mechanism in response to impaired function elsewhere, embodying the complexity and adaptability of the brain’s neural responses.
Moreover, psychological factors may also contribute to the neurophysiological basis of FMDs. Patients often exhibit a history of trauma or stress, which can alter neural function and contribute to movement disorders. This interplay between emotional and physical symptoms highlights the biopsychosocial model of FMDs, where psychological factors may exacerbate or trigger neurophysiological changes leading to symptoms. Therefore, understanding these mechanisms not only provides insight into the etiology of the disorders but also opens avenues for developing more targeted and effective therapeutic interventions.
Participants and Procedures
The study engaged a diverse cohort of participants diagnosed with functional movement disorders, ensuring a comprehensive representation of the condition’s clinical spectrum. Eligible participants were recruited from neurology clinics, fulfilling criteria based on established diagnostic frameworks such as the Diagnostic and Statistical Manual of Mental Disorders (DSM-5) and the International Classification of Diseases (ICD-10). Inclusion criteria mandated a confirmed diagnosis of an FMD, while exclusion criteria ruled out individuals with identifiable neurological conditions, such as Parkinson’s disease or stroke, which could confound results.
In total, the study encompassed a sample of [insert sample size here] participants, aged between [insert age range here], ensuring a mixture of genders and demographic backgrounds to enhance the generalizability of the findings. Prior to undergoing neurological assessments, participants were thoroughly briefed about the nature of the research, with informed consent obtained from each individual, adhering to ethical guidelines stipulated by the institutional review board.
The procedures comprised a multi-faceted approach leveraging transcranial magnetic stimulation (TMS) as the primary neurophysiological assessment tool. TMS enables non-invasive interrogation of cortical excitability and connectivity by applying magnetic fields to stimulate neurons in the motor cortex. This method provided critical data regarding the functional integrity of the motor pathways. Each participant underwent baseline assessments, which included measuring motor threshold—the minimum intensity needed to elicit a motor response—facilitating a tailored approach for subsequent TMS applications.
During the TMS sessions, participants were positioned comfortably in a reclined chair to minimize extraneous movement and ensure accurate stimulation. Each session followed a structured protocol, involving both single-pulse and paired-pulse TMS paradigms. Single-pulse TMS was utilized to assess motor evoked potentials (MEPs), aiming to evaluate cortical excitability, while paired-pulse TMS helped determine intracortical inhibition and facilitation, yielding insights into the balancing act between excitatory and inhibitory circuits in the motor cortex.
Furthermore, the study incorporated standardized video assessments to visually document and categorize the participants’ movement abnormalities prior to, during, and following TMS sessions. Video recordings were analyzed by trained neurologists to objectively classify the types of movement disorders present, providing a contextual backdrop for interpreting neurophysiological findings. Alongside TMS and video assessments, comprehensive questionnaires were employed to gauge participants’ psychological states, capturing key data related to trauma history, stress levels, and concomitant psychiatric symptoms.
Data collection adhered to a rigorous timeline, with TMS evaluations occurring over multiple sessions to ensure reliability and comprehensiveness. Each session was meticulously documented to capture changes in motor symptoms and corresponding neurophysiological measures. The integration of these multidimensional assessments was instrumental in elucidating the intricate relationships between neurophysiological parameters and clinical manifestations of functional movement disorders.
Results and Analysis
The analysis of data collected through transcranial magnetic stimulation (TMS) and accompanying assessments revealed significant insights into the neurophysiological characteristics of functional movement disorders (FMDs). Initial evaluations showed a marked abnormality in motor evoked potentials (MEPs) among participants compared to a control group devoid of movement disorders. This discrepancy highlighted reduced cortical excitability in the primary motor cortex, suggesting that this region may not be generating signals effectively enough to facilitate smooth and coordinated voluntary movements.
When examining the TMS results, participants exhibited a greater variability in MEP amplitudes, indicating inconsistencies in motor cortex activation that could correlate with the erratic nature of their movement symptoms. Additionally, the paired-pulse TMS findings presented compelling evidence of altered intracortical inhibition and facilitation. In participants with FMDs, there was a notable decrease in intracortical inhibition, a phenomenon that points towards an imbalance between excitatory and inhibitory mechanisms within the primary motor cortex. This imbalance may underlie the unregulated motor outputs observed in these patients, contributing to their involuntary movements.
The analysis of the video assessments corroborated the neurophysiological findings. Participants displayed a spectrum of movement abnormalities, including dystonic postures and tremors, which were further classified according to standardized video-based assessments. Neurologists identified that several patients experienced fluctuating symptoms that correlated with their psychological states, reinforcing the notion that emotional stressors may exacerbate the neurophysiological dysfunctions. This relationship sheds light on the importance of a comprehensive approach to treatment that encompasses both psychological and neurological interventions.
Statistical analysis of the data underpinned the significance of the findings. Differences in cortical excitability showed a strong correlation with the severity of motor symptoms as rated by neurologists. For instance, elevated levels of anxiety and trauma history documented through questionnaires were statistically related to greater disturbances in motor function and abnormal TMS measures. These insights affirm that the neurophysiological profile of individuals with FMDs is not solely a mechanical issue of motor control but is significantly flavored by psychosocial factors.
The variability in responses to TMS also raised an intriguing question about the individual differences among patients with FMDs. While some participants demonstrated pronounced deficits in motor cortex function, others exhibited relatively preserved excitability despite severe clinical manifestations. Such findings suggest the potential for diverse underlying mechanisms driving FMDs. Further, they underscore the necessity for personalized treatment strategies that consider these variations in neurophysiological profiles.
The results convey a complex interplay of altered motor cortex excitability, individual psychological factors, and distinct symptom manifestations in FMDs. These findings advocate for a comprehensive understanding of the disorder that integrates neurophysiological data with the psychological profile of patients, thus paving the way for more effective clinical interventions aimed at addressing both the physical and emotional dimensions of functional movement disorders.
Future Directions
As research into the neurophysiological underpinnings of functional movement disorders (FMDs) continues to evolve, several future directions emerge that warrant exploration. Understanding the nuances of these disorders necessitates not only deeper investigations into their central mechanisms but also the development of innovative therapeutic strategies that can effectively address the multidimensional aspects of FMDs.
One significant area to examine is the potential for expanded use of neuroimaging techniques alongside transcranial magnetic stimulation (TMS). While TMS provides valuable insights into cortical excitability, combining it with functional MRI and diffusion tensor imaging could offer a more holistic view of the brain’s structural and functional connectivity. Such integrative approaches may reveal how changes in brain architecture correlate with the clinical symptoms of FMDs and could guide the identification of biomarkers that might predict treatment responses.
Moreover, longitudinal studies tracking patients over time could elucidate the evolution of neurophysiological changes associated with FMDs. By examining how cortical excitability and psychological factors fluctuate, researchers may uncover patterns that contribute to the onset or exacerbation of symptoms. This temporal dimension could provide critical insights into how interventions—whether therapeutic or pharmacological—impact both the physiological and psychological aspects of FMDs, potentially leading to the establishment of more effective management protocols.
Furthermore, there is a pressing need to investigate the specific psychological mechanisms that contribute to the onset and continuation of FMDs. Research should focus on refining our understanding of how trauma, anxiety, and stress interact with neurological function. Psychological interventions, such as cognitive-behavioral therapy or mindfulness training, could be integrated into treatment plans to address these underlying emotional factors directly. Evaluating the efficacy of such interventions, paired with neurophysiological metrics, might enhance therapeutic outcomes for individuals with FMDs.
Another potential avenue for future research includes the exploration of neuromodulation techniques as treatment options. Approaches such as deep brain stimulation or repetitive TMS may be evaluated for their ability to modulate motor cortex activity in patients with FMDs. Investigating optimal parameters for neuromodulation could lead to personalized therapeutic protocols, maximizing individual response rates while minimizing risks.
Engaging in interdisciplinary collaborations that include neurologists, psychologists, physiotherapists, and occupational therapists could foster a more comprehensive approach to treatment. Such teams could work together to design personalized interventions that are tailored to the specific needs of each patient, not only addressing the neurophysiological impairments but also providing support for the psychological challenges that accompany FMDs. This integrative methodology could potentially reshape the clinical landscape for managing functional movement disorders, facilitating a more holistic and effective patient care experience.