Orthostatic Dysregulation
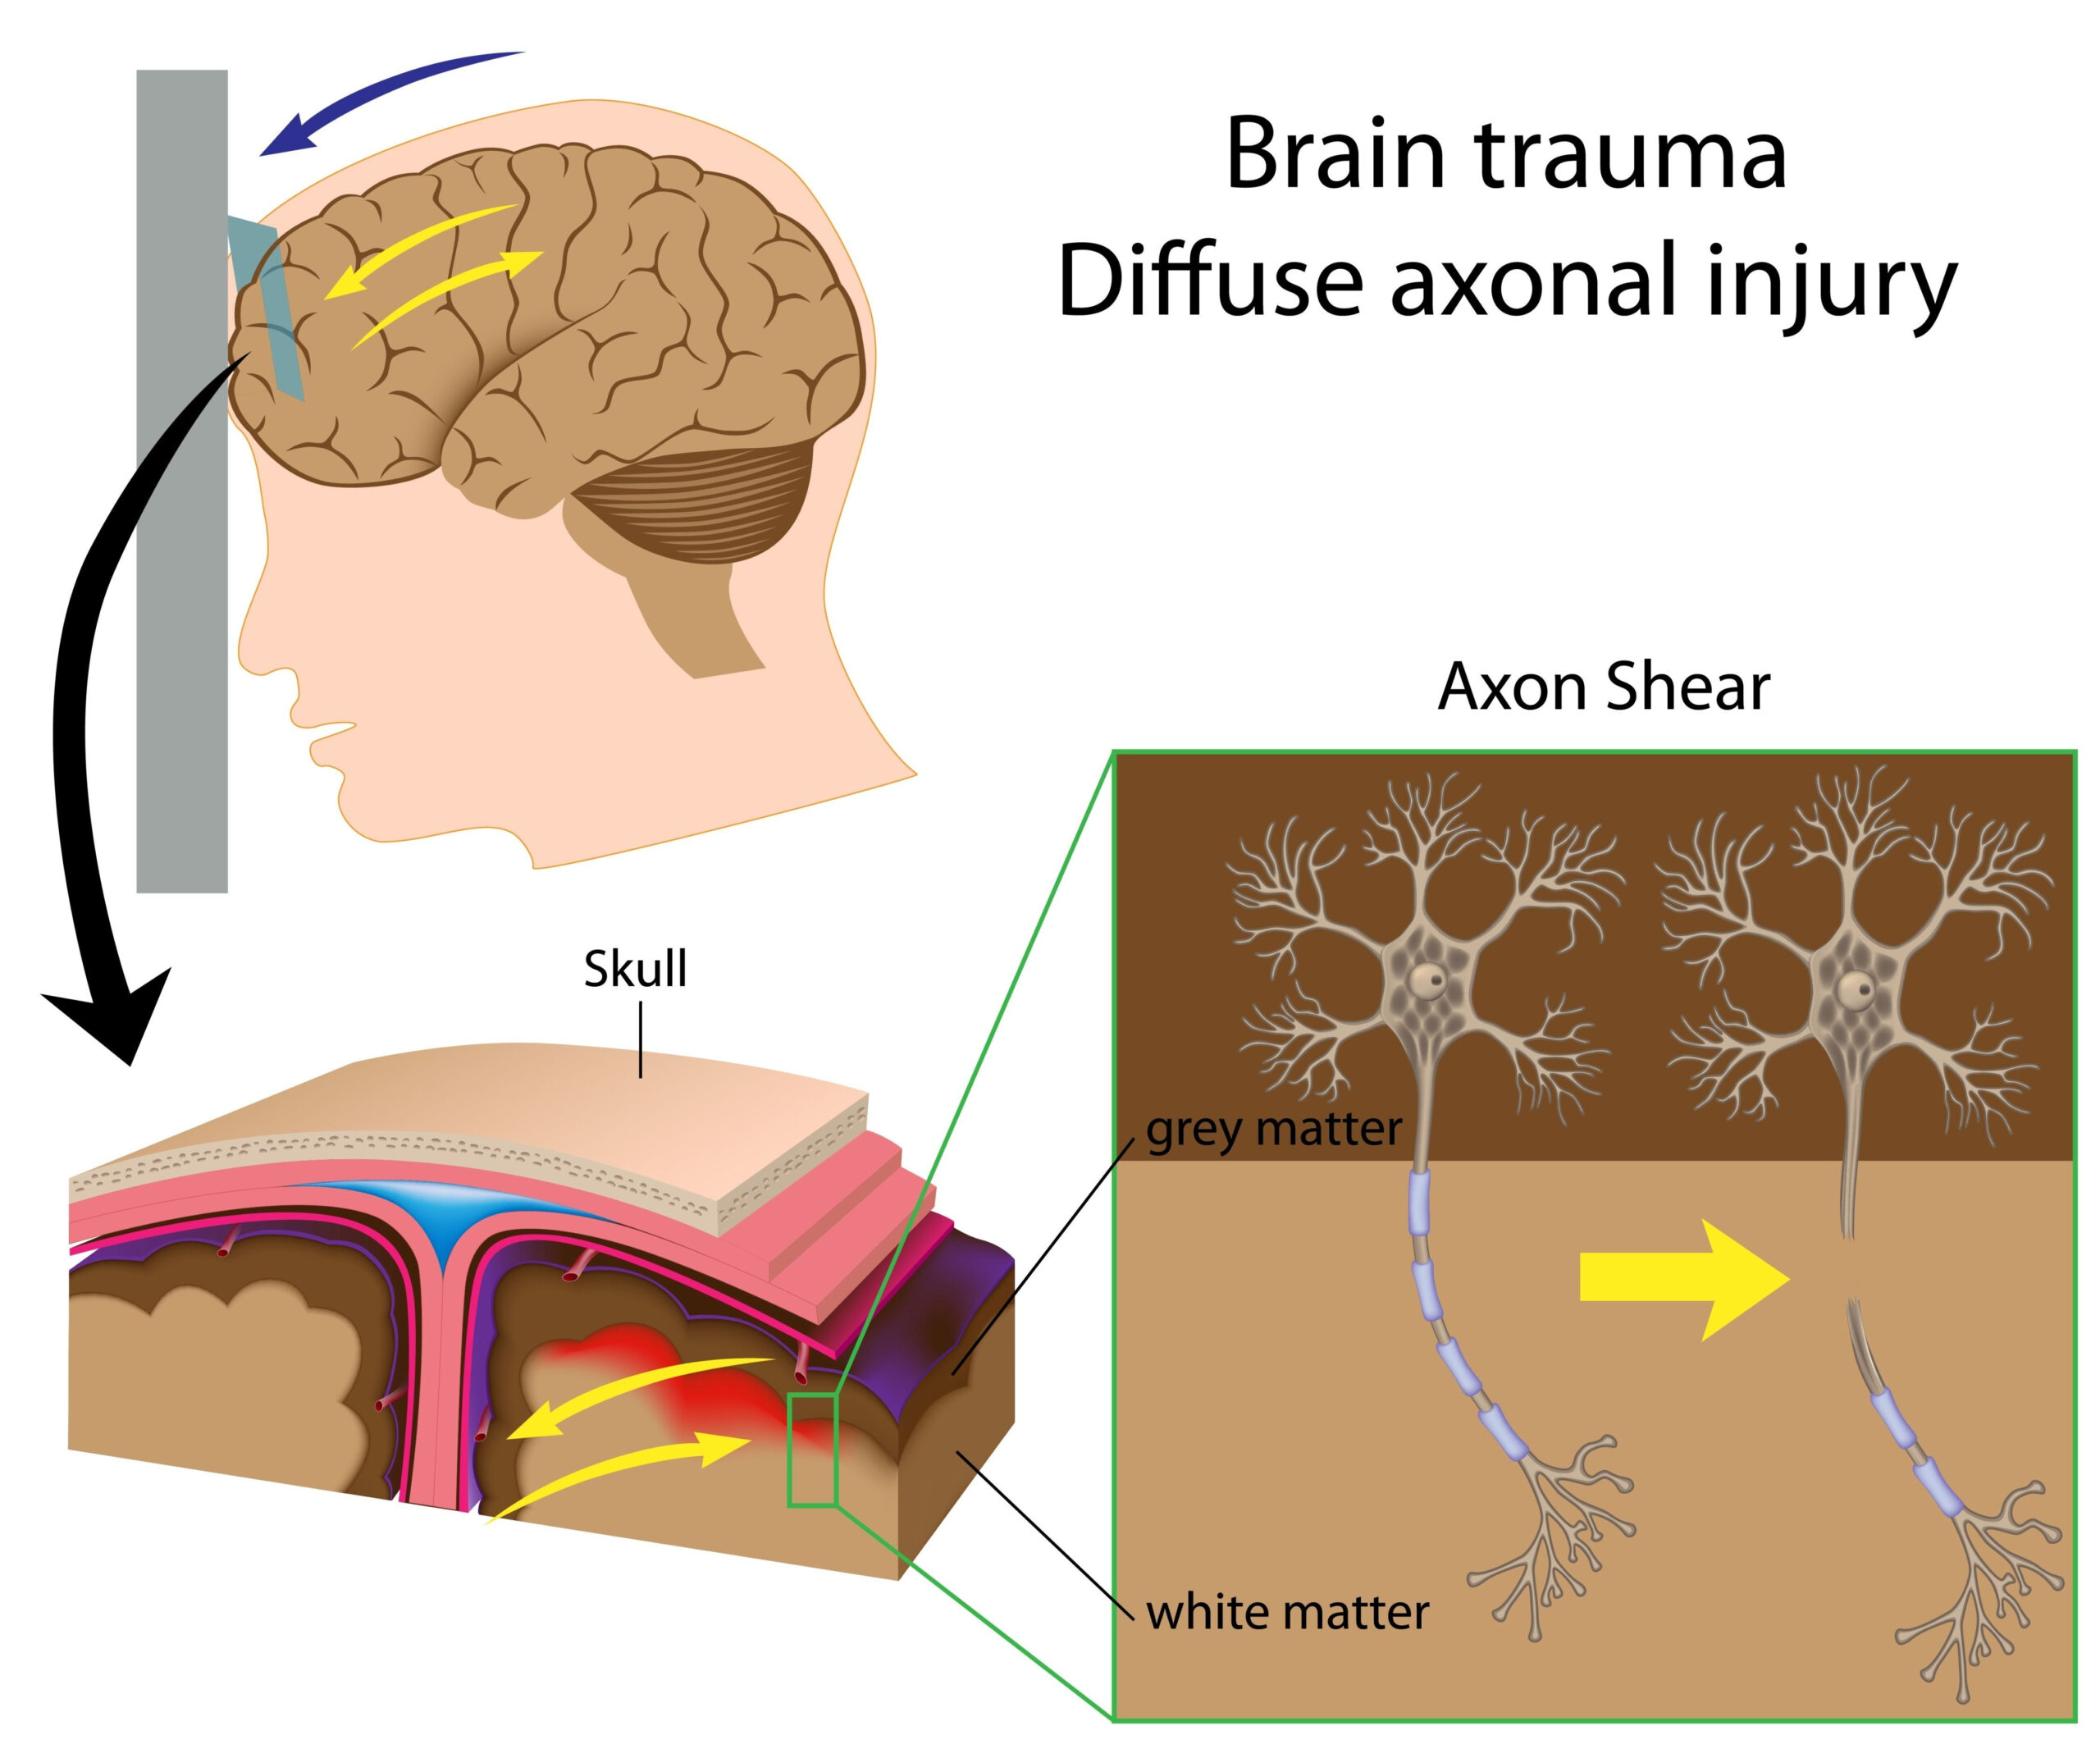
Orthostatic dysregulation is a condition characterized by an abnormal cardiovascular response when an individual changes posture, particularly from lying down to standing up. This dysregulation can be partially attributed to dysfunction in the autonomic nervous system, which plays a crucial role in regulating blood pressure and heart rate during positional changes. Following an adult concussion, patients may experience symptoms such as lightheadedness, palpitations, and even fainting due to compromised blood flow to the brain when they assume an upright position.
A detailed understanding of orthostatic dysregulation involves considering both the mechanisms at play and the range of clinical manifestations observed in individuals post-concussion. The autonomic nervous system can fail to respond adequately to the gravitational shift, leading to a drop in blood pressure (known as orthostatic hypotension) or an excessive heart rate response. In healthy individuals, standing up triggers compensatory mechanisms such as vasoconstriction and increased heart rate to maintain cerebral perfusion and prevent symptoms. However, in cases following a concussion, these compensatory responses may be impaired due to issues such as impaired baroreceptor sensitivity or autonomic imbalance, resulting in a heightened risk for orthostatic intolerance.
Research has shown that patients recovering from concussions may exhibit varying degrees of orthostatic dysregulation, with a notable proportion experiencing persistent postural orthostatic tachycardia syndrome (POTS). This condition is defined by an excessive increase in heart rate upon standing and is often accompanied by other symptoms, including fatigue, cognitive difficulties, and exercise intolerance. The dysregulation often poses a complex challenge for both diagnosis and management, as symptoms can overlap significantly with other post-concussion syndromes, requiring careful evaluation to ensure accurate identification.
It is essential for clinicians to recognize the signs of orthostatic dysregulation in patients recovering from concussions. Early intervention and tailored assessment are crucial not only for improving the quality of life for these patients but also for enabling the development of targeted treatment strategies that address the underlying autonomic dysfunction. Understanding the nuances of orthostatic dysregulation is vital for optimizing patient outcomes and reducing the long-term impact of concussions on daily functioning.
Assessment Techniques
Assessing orthostatic dysregulation following an adult concussion involves a combination of clinical evaluations, patient history, and specialized testing to accurately identify autonomic function deficits. A comprehensive assessment often begins with a thorough patient history, where clinicians gather information regarding the onset, duration, and severity of symptoms related to standing or posture changes. This initial evaluation is critical, as it provides context for further investigations and helps differentiate between typical post-concussion symptoms and those specifically linked to autonomic dysregulation.
Following the history assessment, physical examinations are conducted, focusing on orthostatic vital signs measurements. This involves taking blood pressure and heart rate in different postures: while lying down, sitting, and standing. A significant drop in blood pressure or an excessive rise in heart rate upon moving to an upright position can suggest orthostatic dysregulation. The commonly accepted criteria for identifying orthostatic hypotension include a decrease in systolic blood pressure of at least 20 mmHg or a drop in diastolic blood pressure of 10 mmHg within three minutes of standing. These measurements not only reveal the autonomic functionality but also provide insights into the cardiovascular system’s ability to adapt to postural changes.
In more complex cases, additional assessments are employed to evaluate heart rate variability and autonomic function more comprehensively. Techniques such as tilt-table testing may be utilized, where patients are positioned at various angles to provoke orthostatic responses in a controlled setting. This method helps to observe changes in cardiovascular responses in response to tilted positions and can aid in confirming diagnoses like postural orthostatic tachycardia syndrome (POTS) and other forms of dysautonomia.
Other diagnostic tools may include the active stand test, where the patient stands up from a seated position and vital signs are monitored for fluctuations. Continuous monitoring via specialized devices or wearable technology can also be beneficial, allowing for a more detailed analysis of heart rate and blood pressure changes throughout daily activities. This data can help healthcare providers develop a clearer picture of how daily postural changes affect the patient over an extended period.
Furthermore, integrating subjective symptom scales alongside objective measurements can enrich the assessment process. Tools such as the Orthostatic Grading Scale, which measures symptom severity when transitioning postures, provide valuable data that reflects the patient’s experience and can help inform treatment plans. This dual approach, combining objective lab tests with subjective reporting, is essential for capturing the multifaceted nature of orthostatic dysregulation.
Ultimately, accurate assessment techniques are vital for diagnosing individuals with orthostatic dysregulation following a concussion. A comprehensive understanding of the patient’s autonomic response through careful clinical evaluation enables targeted interventions, ultimately improving patient care and recovery trajectories. By employing a variety of assessment strategies, clinicians can effectively tailor treatment plans that best support patients facing the challenges of post-concussion orthostatic intolerance.
Symptomatology and Prevalence
Following an adult concussion, the presentation of symptoms linked to orthostatic dysregulation can be diverse and significantly impact daily functioning. Commonly reported symptoms include lightheadedness or dizziness upon standing, fatigue, palpitations, blurred vision, and in some cases, syncope. These symptoms can severely impair patients’ ability to engage in regular activities, thereby contributing to a reduced quality of life. The chronic nature of these symptoms often leads to additional psychological distress, including anxiety and depression, as patients struggle to adapt to their altered states of health.
The prevalence of orthostatic intolerance post-concussion varies among studies, but research indicates that a significant proportion of individuals may experience these symptoms. Estimates suggest that anywhere from 30% to 50% of individuals recovering from concussions report some degree of autonomic dysfunction, which may manifest as orthostatic intolerance. Specifically, conditions like postural orthostatic tachycardia syndrome (POTS) have garnered attention; studies show that a notable subset of post-concussion patients meets the diagnostic criteria for POTS, indicating that the prevalence of this syndrome may be higher than previously recognized.
Demographics also play a role in the manifestation of orthostatic symptoms. Younger individuals and women, in particular, may exhibit a higher incidence of these issues, possibly due to anatomical and physiological differences that influence autonomic responses to postural changes. Furthermore, the temporal aspect of symptom onset post-concussion can vary widely; while some patients may experience immediate symptoms following the injury, others may develop them over weeks or months as they progress through recovery.
Identifying the specific symptom profile associated with orthostatic dysregulation is crucial for accurate diagnosis and appropriate management. Symptoms can often overlap with other complications arising from concussions, such as migraine, cognitive fatigue, or vestibular disturbances, complicating the clinical picture. This overlap necessitates careful differentiation through a structured assessment approach, integrating both patient-reported outcomes and objective evaluation methods. Through this clarity, healthcare providers can better address the patient’s needs and tailor interventions that not only target the symptoms but also improve overall recovery trajectories.
Moreover, understanding the prevalence and spectrum of symptoms associated with orthostatic dysregulation aids in raising awareness among healthcare professionals. Increased awareness can lead to earlier recognition and intervention strategies, potentially mitigating the severe effects of this condition on rehabilitation outcomes. For patients, understanding that their symptoms may have a specific physiological basis offers validation and fosters a proactive approach to management, reinforcing the importance of seeking specialized care when experiencing these distressing symptoms following a concussion.
Treatment Approaches
Treatment options for individuals experiencing orthostatic dysregulation following a concussion are multifaceted and must be tailored to each patient’s unique symptoms and underlying pathophysiology. The primary goal of treatment is to alleviate symptoms, improve functional capability, and restore the body’s autonomic balance. Strategies often involve lifestyle modifications, pharmacologic interventions, and physical rehabilitation, combining these approaches to optimize outcomes.
One of the cornerstone interventions includes implementing lifestyle changes that address the symptoms of orthostatic intolerance. Patients are typically advised to increase fluid and salt intake, which can help elevate blood volume and improve blood pressure. In conjunction with dietary modifications, wearing compression garments, such as abdominal binders or compression stockings, can be beneficial. These garments assist in venous return, thereby reducing the likelihood of blood pooling in the lower extremities when the patient stands.
Education on gradual posture changes can also play a crucial role in treatment. Patients may be encouraged to take their time when transitioning from a supine or seated position to standing, allowing their body to adapt without triggering symptoms. Techniques such as tensing up the leg muscles before standing or moving to the edge of the bed and dangling the legs prior to rising can help facilitate a more stable shift in blood pressure and minimize symptoms.
For patients whose symptoms persist despite these lifestyle interventions, pharmacologic options may be considered. Medications such as fludrocortisone, midodrine, or beta-blockers can be utilized to manage blood pressure and improve autonomic responses. Fludrocortisone is a mineralocorticoid that helps to promote sodium retention, thereby supporting blood volume expansion. Midodrine, an alpha-agonist, can raise blood pressure by constricting blood vessels. Meanwhile, beta-blockers may be prescribed to moderate hyperadrenal responses characterized by increased heart rate during upright posture, especially in those with POTS.
Physical rehabilitation is another essential component of a comprehensive treatment plan. Tailored exercise regimens can significantly aid recovery by enhancing cardiovascular fitness and autonomic regulation. A gradual, supervised program focusing on aerobic conditioning can help improve tolerance to upright posture and decrease symptoms of orthostatic intolerance. Exercises should begin with recumbent or seated activities, slowly progressing to more upright exercises as tolerated. Additionally, functional training aimed at improving balance and coordination can further assist individuals in adapting to their symptoms in daily life.
Psychoeducation and mental health support are equally critical given the psychological burden often associated with persistent symptoms of dysautonomia. Cognitive-behavioral therapy (CBT) and other forms of psychosocial support can help patients manage anxiety and depression that may arise from chronic health issues and lifestyle limitations. By addressing both the physiological and psychological aspects of recovery, clinicians can provide a holistic approach to treatment.
Early identification and intervention remain essential for improving trajectories in patients experiencing orthostatic dysregulation post-concussion. A multidisciplinary approach, incorporating primary care providers, neurologists, rehabilitation specialists, and mental health professionals, can ensure comprehensive management that addresses both the symptoms and their root causes. Collaboration among various healthcare providers facilitates a cohesive treatment strategy that is critical to supporting patient recovery and enhancing overall quality of life. Through personalized and proactive care, many individuals can learn to manage their symptoms effectively, gaining autonomy and improving their ability to engage in daily activities.