Case Presentation
The patient in this case is a 34-year-old female who presented to the neurology clinic with a reported history of recurrent psychogenic non-epileptic seizures (PNES). Her symptoms began approximately six months prior, following a traumatic event where she experienced a severe emotional upheaval. Prior to the current presentation, the patient had a significant psychiatric history, including episodes of major depression and anxiety disorders.
During the neurological assessment, the patient described episodes characterized by loss of consciousness, muscle rigidity, and convulsions, which were reminiscent of epileptic seizures. However, unlike typical seizures, these episodes were associated with marked psychological distress and were often triggered by reminders of the trauma she had experienced. The patient’s family reported a dramatic increase in these episodes, influencing her daily functioning and leading to a withdrawal from social activities and her professional responsibilities.
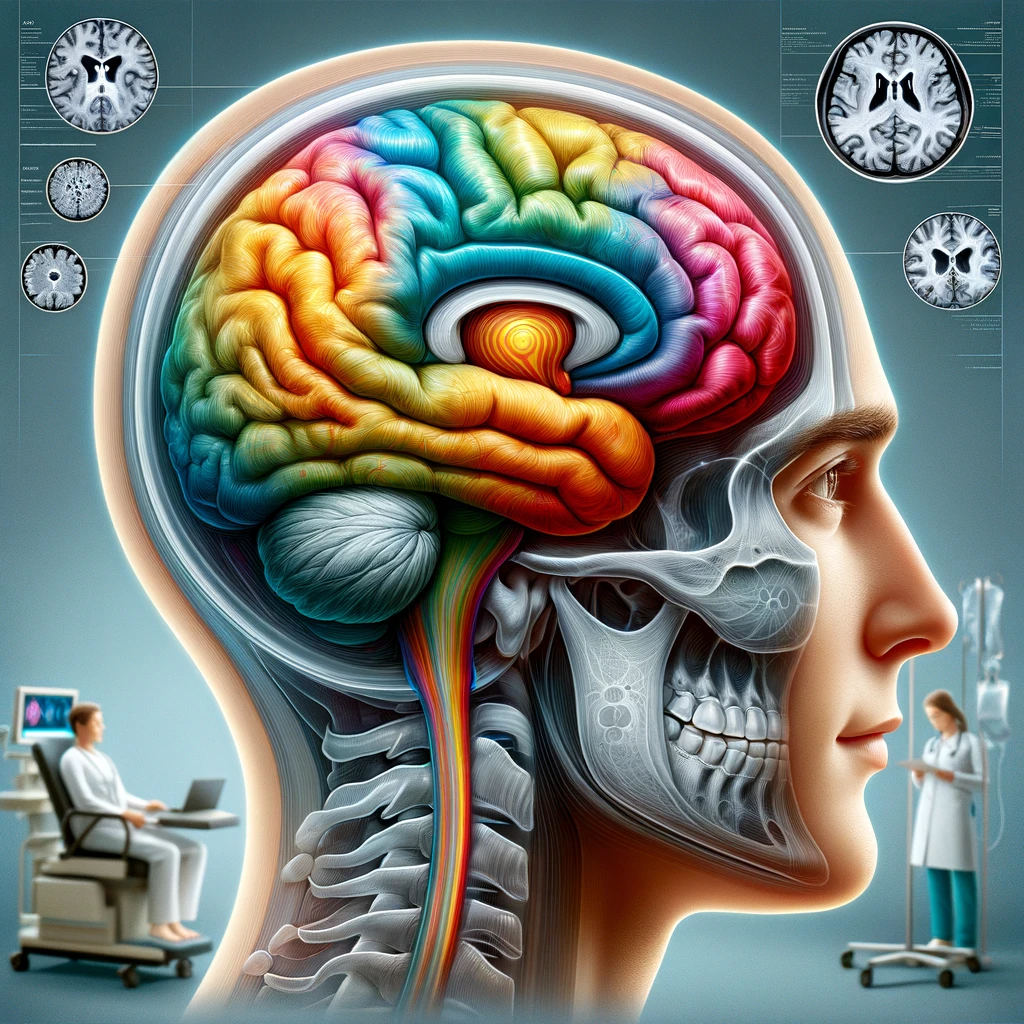
Neurological examinations, including an electroencephalogram (EEG) and neuroimaging, were performed to rule out any underlying neurological conditions. The EEG results during the episodes revealed no epileptic activity, reinforcing the diagnosis of PNES. Further evaluations highlighted the psychological aspects of her condition, revealing symptoms of complex post-traumatic stress disorder (C-PTSD), including re-experiencing her trauma, heightened emotional responses, and avoidance behaviors.
Upon her initial consultation, a comprehensive evaluation was undertaken. The patient was found to be non-epileptic, and it was determined that her seizure-like episodes were primarily psychogenic in nature. The interplay between her psychological trauma and the manifestation of her physical symptoms illustrated the complexity of her condition, requiring a multi-faceted approach to treatment.
Diagnostic Criteria
To accurately diagnose complex post-traumatic stress disorder (C-PTSD) and its manifestations, such as psychogenic non-epileptic seizures (PNES), certain diagnostic criteria must be met. C-PTSD is recognized in the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5), and is characterized by symptoms that extend beyond those of standard PTSD. The following criteria are pivotal in making a reliable diagnosis:
- Exposure to Traumatic Events: The individual must have experienced, witnessed, or been confronted with actual or threatened death, serious injury, or sexual violence. This may involve direct experience or indirect exposure through learning about violent acts involving a close relationship.
- Re-experiencing Symptoms: Patients frequently experience intrusive memories, flashbacks, or distressing dreams related to the traumatic event. These re-experiencing symptoms can induce psychological distress or physiological reactions, contributing to the episodes of PNES.
- Avoidance Symptoms: Individuals often engage in avoidance strategies to steer clear of reminders of the trauma. This may include avoiding conversations, thoughts, or activities that resemble the traumatic experience. Such avoidance mechanisms can further exacerbate feelings of isolation and anxiety.
- Negative Alterations in Cognition and Mood: Persistent negative emotions such as fear, guilt, or shame may arise. Additionally, feelings of detachment from others or a persistent inability to experience positive emotions can significantly impact the patient’s overall mental health.
- Alterations in Arousal and Reactivity: This includes symptoms such as irritability, hypervigilance, or an exaggerated startle response. These may manifest behaviorally as aggressive outbursts or reckless behavior, further complicating the clinical picture.
In the context of psychogenic non-epileptic seizures, it is vital to assess both the psychological and physical dimensions of the condition. The absence of electroencephalographic evidence of epileptic activity combined with the episodic nature of the seizures often aligns with the diagnostic criteria for PNES. The table below summarizes the relevant diagnostic criteria for C-PTSD and their links to the manifestation of PNES:
| Diagnostic Criterion | Description | Connection to PNES |
|---|---|---|
| Traumatic Exposure | Experiencing severe trauma such as abuse or violence | A trigger for episodes reflecting unresolved emotional distress |
| Re-experiencing Symptoms | Intrusive thoughts or flashbacks | Can precipitate PNES during recollections of trauma |
| Avoidance Symptoms | Efforts to avoid reminders of trauma | Leads to increased distress when faced with triggers, resulting in seizures |
| Negative Mood Alterations | Pervasive negative emotions and feelings of detachment | May heighten likelihood of PNES during episodes of emotional turmoil |
| Alterations in Arousal | Increased irritability, hypervigilance | May exacerbate physical symptoms linked to PNES episodes |
A comprehensive understanding of these criteria enables clinicians to differentiate between epileptic seizures and PNES effectively, forming the basis for targeted interventions. It is essential for clinicians to utilize these diagnostic frameworks not only for evaluating the symptoms but also to tailor a treatment plan that addresses both the psychological and physical manifestations of the disorder.
Treatment Approaches
Treating complex post-traumatic stress disorder (C-PTSD) and the associated psychogenic non-epileptic seizures (PNES) involves a multidisciplinary approach that integrates psychological therapies, psychiatric interventions, and supportive care. The treatment plan aims to address both the underlying trauma and the physical symptoms manifested as seizures, ensuring that the patient receives comprehensive care tailored to her specific needs.
One of the primary treatment modalities for C-PTSD is trauma-focused psychotherapy. This includes evidence-based approaches such as:
- Cognitive Behavioral Therapy (CBT): This therapy helps patients identify and modify negative thought patterns and behaviors related to the trauma. CBT is often effective in teaching coping strategies that can help the patient manage anxiety and reduce avoidance behaviors associated with C-PTSD, thereby decreasing the frequency and severity of PNES.
- Eye Movement Desensitization and Reprocessing (EMDR): EMDR is a specialized therapy designed to treat trauma by using bilateral stimulation (typically through guided eye movements). This approach allows patients to process traumatic memories in a safer context, reducing their emotional impact and associated seizure responses.
- Dialectical Behavior Therapy (DBT): DBT focuses on improving emotional regulation, distress tolerance, and interpersonal effectiveness. It helps patients develop skills to cope with intense emotions, which may be crucial for managing episodes of PNES triggered by emotional distress.
Pharmacological interventions may also play an essential role in the overall treatment strategy, particularly in addressing co-morbid psychiatric symptoms such as depression and anxiety. Commonly prescribed medications include:
- Antidepressants: Selective serotonin reuptake inhibitors (SSRIs) and serotonin-norepinephrine reuptake inhibitors (SNRIs) are often recommended for treating symptoms of depression and anxiety in C-PTSD, potentially ameliorating stress-related seizures.
- Anxiolytics: In some cases, short-term use of medications like benzodiazepines may be considered to manage acute anxiety symptoms; however, their long-term use is generally avoided due to the risk of dependence.
- Beta-Blockers: Certain beta-blockers may be beneficial in reducing physiological responses to anxiety, potentially decreasing the likelihood of seizure episodes triggered by stress.
The role of psychoeducation cannot be understated in this treatment approach. Educating the patient about the nature of her condition can foster a better understanding of how her psychological state interacts with her physical symptoms. This education can empower her to recognize triggers and potentially mitigate their impact by employing previously learned coping mechanisms.
The involvement of a supportive network is equally critical. Family therapy may provide a space for family members to understand the patient’s experiences better and enhance their capacity to support her during episodes. It can improve communication and also aid family members in learning how to respond appropriately when seizures occur, ensuring a calm and reassuring environment.
Finally, the incorporation of stress management techniques, such as mindfulness practices, yoga, or relaxation exercises, may also prove beneficial. These methods can help patients regulate their emotional responses and enhance their ability to cope with challenging situations, thus reducing the incidence of PNES.
Table 1 summarizes common treatment approaches for C-PTSD and PNES:
| Treatment Approach | Description | Potential Benefits |
|---|---|---|
| Cognitive Behavioral Therapy (CBT) | Focus on changing negative thought patterns and behaviors | Helps manage anxiety and increase coping skills |
| Eye Movement Desensitization and Reprocessing (EMDR) | Utilizes bilateral stimulation to reprocess trauma | Reduces emotional distress associated with memories |
| Dialectical Behavior Therapy (DBT) | Develops skills for emotion regulation and tolerance | Improves ability to cope with intense emotions |
| Pharmacological Interventions | Use of medications to address anxiety and depression | May improve symptoms of C-PTSD and reduce seizure frequency |
| Psychoeducation | Educating patient and family about the condition | Empowers patient and enhances family support |
| Stress Management Techniques | Incorporates mindfulness and relaxation strategies | Reduces stress and anxiety levels to limit PNES |
Future Directions
Future directions in the management of complex post-traumatic stress disorder (C-PTSD) and psychogenic non-epileptic seizures (PNES) will likely involve a greater emphasis on integrated care models that address both the psychological and physical aspects of these interconnected conditions. Research into the neurobiological underpinnings of C-PTSD and PNES is also essential for evolving treatment protocols and enhancing our comprehensive understanding of these disorders.
One promising avenue is the development of more personalized treatment plans. This could involve utilizing genetic and biomarker studies to identify which patients are most likely to respond to specific therapeutic interventions. By tailoring approaches based on individual biological profiles, treatments could be more effective, reducing the trial-and-error aspect common in current practice.
Another key direction is the incorporation of technology into treatment regimens. Digital mental health interventions, such as mobile applications focused on delivering cognitive behavioral therapy (CBT) techniques, mindfulness training, and stress management tools, can make therapy more accessible and individualized. Teletherapy and online support groups can also enhance patient engagement and maintain continuity of care, especially in underserved populations.
Moreover, research into the use of pharmacological agents that specifically target underlying mechanisms of C-PTSD can yield new treatment avenues. For example, there is ongoing exploration into the use of ketamine and other psychedelics for their rapid effects in reducing symptoms of trauma and anxiety. Preliminary studies suggest that these substances could provide relief from treatment-resistant cases, fostering further investigation into their application for PNES.
Collaboration among multidisciplinary teams, including psychologists, psychiatrists, neurologists, and physical therapists, will be integral in addressing the multifaceted nature of these disorders. This collaborative approach can facilitate comprehensive assessments and ensure that all aspects of a patient’s health are considered in the treatment plan.
Lastly, the importance of longitudinal studies cannot be overstated. Research that follows patients over longer periods can provide valuable insights into the natural history of C-PTSD and PNES, the effectiveness of various interventions, and long-term outcomes. This will help refine diagnostic criteria and treatment protocols, ensuring they remain evidence-based and centered on the patient’s evolving needs.
In conclusion, the future of managing C-PTSD and PNES lies in an adaptable, comprehensive, and evidence-based framework. By fostering innovation in treatment, enhancing interdisciplinary collaboration, and promoting research, we can hope to improve the quality of life for those affected by these challenging conditions.