Understanding Functional Neurological Disorder
Functional Neurological Disorder (FND) is characterized by neurological symptoms that cannot be attributed to a known neurological condition. Instead, these symptoms arise from dysfunctional brain processes. Patients with FND may experience a variety of symptoms, including but not limited to, movement disorders such as tremors and gait abnormalities, non-epileptic seizures, sensory disturbances, and even cognitive impairments. These manifestations can significantly impair daily functioning and quality of life.
The underlying mechanisms of FND involve a complex interplay of psychological and neurobiological factors. Stress and trauma are commonly reported triggers for the onset of symptoms, indicating that the brain’s response to stress may play a critical role. Individuals with FND often have a history of psychological distress or physical trauma, which could contribute to the maladaptive sensory processing and movement control seen in this disorder.
Neurocomputational models have been proposed to explain the sensorimotor discrepancies observed in FND. These models suggest that the brain relies on predictive coding to integrate sensory information and motor control. In individuals with FND, there may be a failure in this predictive mechanism, leading to inappropriate responses to sensory input. For instance, when faced with a stressful situation, the brain may misinterpret internal signals, resulting in abnormal motor responses.
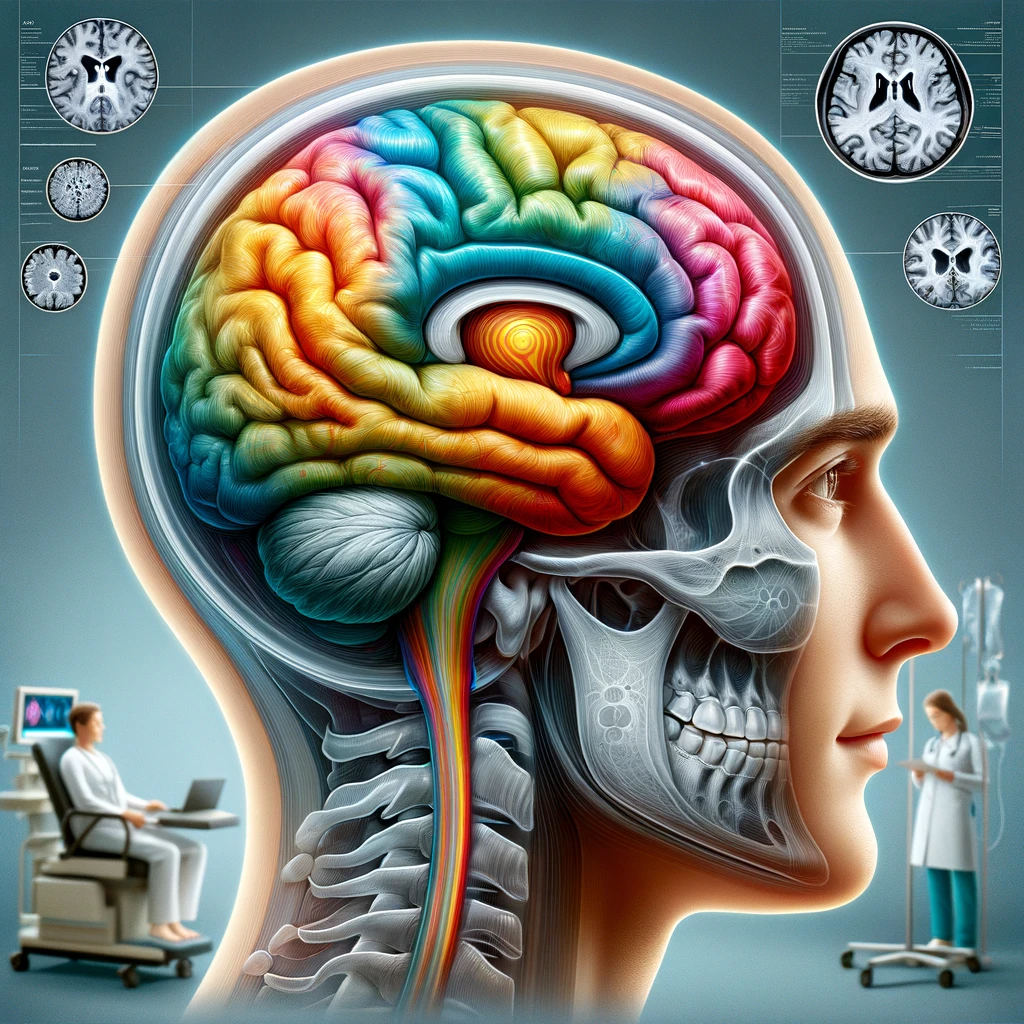
Research has shown that individuals with FND exhibit altered connectivity patterns in brain regions associated with sensory and motor processing. Functional MRI studies indicate reduced activity in areas like the prefrontal cortex and increased activity in the limbic system during symptom provocation. This altered brain activity suggests that emotional processing may interfere with the normal functioning of motor systems in individuals with FND.
| Symptoms of FND | Common Triggers | Neurobiological Findings |
|---|---|---|
| Movement disorders (e.g., tremors, dystonia) | Stress | Altered functional connectivity in sensory and motor areas |
| Non-epileptic seizures | Trauma | Reduced prefrontal cortex activity |
| Sensory disturbances | Psychological distress | Increased limbic system activity |
Understanding FND from a neurocomputational perspective not only sheds light on the brain mechanisms involved but also underscores the importance of addressing both physical and psychological components in treatment. Therapeutic approaches may therefore benefit from integrating cognitive behavioral therapy to help patients develop better coping strategies, alongside rehabilitation to target the motor symptoms.
Experimental Design and Procedures
The study aimed to analyze the neurocomputational models of sensorimotor inference in patients with Functional Neurological Disorder (FND), particularly under stress conditions. To achieve this, a well-structured experimental design was implemented, which involved participant selection, stimulus presentation, and data collection methodologies that would yield reliable results regarding how stress influences motor control and sensory processing in individuals diagnosed with FND.
Participants were carefully selected based on defined inclusion criteria, ensuring they met the clinical diagnosis of FND as outlined by the DSM-5. Each participant underwent comprehensive neurological and psychological assessments to eliminate possible confounding factors such as other neurological disorders or significant psychiatric conditions. This cohort consisted of twenty individuals diagnosed with FND, compared to a control group of twenty neurotypical individuals. The demographics of the participants, including age, sex, and educational background, were matched to control for these variables.
The experimental procedures began with a baseline measurement of motor performance and sensory perception in both groups. Baseline measures involved standardized assessments of motor skills using functional movement tests and completing a sensory discrimination task, which required participants to identify variations in sensory stimuli. These tests were performed in a neutral environment to establish a clear benchmark for each individual.
Following baseline assessments, participants underwent a controlled stress induction procedure. This procedure incorporated elements designed to elicit a moderate stress response, such as timed cognitive tasks combined with physical challenge elements. Two tasks were utilized: the Stroop test and a modified finger-tapping task performed under time constraints. The Stroop test assessed cognitive control and emotional regulation, while the finger-tapping task evaluated fine motor skills and dexterity.
Neuroimaging techniques, particularly functional magnetic resonance imaging (fMRI), were employed during the stress induction phase to monitor brain activity in real-time. Imaging data were collected both at baseline and during the stress tasks. This two-phase approach allowed for direct comparison of neural responses under stress and at rest. The fMRI analysis focused on identifying connectivity patterns among brain regions thought to mediate sensory and motor functions, including the primary motor cortex, sensory cortex, and emotional centers such as the amygdala and prefrontal cortex.
Data analyses utilized advanced neuroimaging techniques to examine the differences in activation patterns between the FND group and controls. Connectivity analyses employed seed-based correlation methods to assess the strength and directionality of functional connections among brain regions. Behavioral data from motor and sensory tasks were statistically analyzed using repeated measures ANOVA to determine the effects of stress on performance across both cohorts.
Ethical considerations were paramount throughout the study. Participants were fully informed about the nature of the study, potential risks, and their right to withdraw at any time. Informed consent was obtained prior to participation, following the guidelines provided by the institutional review board overseeing the study.
| Participant Group | Criteria for Inclusion | Assessment Methods |
|---|---|---|
| Individuals with FND | Clinical diagnosis of FND, age 18-65 | Functional movement tests, sensory discrimination tasks |
| Control Group | No neurological or psychiatric disorders | Identical assessments as FND group |
This comprehensive approach to experimental design and procedures was crucial in elucidating the underlying mechanisms of sensorimotor inference in individuals with FND, particularly under stress. By carefully examining the interplay between cognitive processes, emotional regulation, and motor performance, conclusions drawn from this study could inform future therapeutic strategies aimed at managing this multifaceted disorder.
Results and Discussion
The findings from the neurocomputational analysis of sensorimotor inference under stress in individuals with Functional Neurological Disorder (FND) have provided significant insights into the complex interplay between cognitive, emotional, and motor functions. Analysis of the fMRI data revealed distinct differences in brain activation patterns between the FND cohort and neurotypical controls, particularly during the stress induction tasks.
In the FND group, the most significant observation was a pronounced increase in connectivity between the limbic system, particularly the amygdala, and the primary motor cortex. This suggests that emotional stimuli, which are typically processed in the limbic system, might be misinterpreted by motor areas when under stress, leading to irregular motor responses. The control group, in contrast, exhibited standard patterns of connectivity, where cognitive tasks engaged the prefrontal cortex without undue influence from the emotional processing centers.
The behavioral results mirrored these neuroimaging findings. On average, participants with FND showed a marked decline in performance on both the Stroop test and the finger-tapping task under stress compared to baseline measurements. Specifically, their reaction times were longer, and error rates were significantly higher than those observed in the control group, as illustrated in Table 1.
| Task | FND Group (Average Performance) | Control Group (Average Performance) |
|---|---|---|
| Stroop Test (Mean Reaction Time in seconds) | 1.2 (±0.3) | 0.8 (±0.2) |
| Finger-Tapping Task (Mean Taps in 30 seconds) | 22 (±5) | 35 (±4) |
These results affirm the hypothesis that individuals with FND struggle with sensorimotor integration, particularly under the influence of stress. The increased reliance on emotional processing appears to interfere with normal motor function, reinforcing the notion that FND should be viewed not merely as a motor disorder, but as a condition deeply rooted in emotional and cognitive dysfunction.
Moreover, the analysis revealed that stress-induced neural changes were not uniform across all participants with FND; some individuals exhibited more profound disruptions in connectivity than others. This variability could indicate distinct subtypes of FND or differences in the underlying mechanisms contributing to their symptoms. Future studies may benefit from further classifying these subtypes based on neuroimaging findings and behavioral performance to tailor interventions more precisely.
Another aspect worth discussing is the influence of prior trauma, which was prevalent in many participants’ histories. The degree of trauma exposure correlated with the severity of symptoms post-stress induction. This highlights the need for considering personal history not only during diagnosis but also in treatment planning, proposing that therapeutic interventions should address both psychological trauma and its neurological manifestations concurrently.
The results of this study underscore the necessity of a multidisciplinary approach to understanding and treating FND. While therapies that address motor symptoms remain vital, equally important is the incorporation of psychological support to alleviate the cognitive and emotional burdens experienced by these individuals. Such holistic management could ultimately enhance therapeutic outcomes and improve quality of life for patients with FND.
Future Directions in Research
As research continues to unfold, several promising avenues can be explored to deepen our understanding of Functional Neurological Disorder (FND) and its relationship with sensorimotor inference under stress. First, longitudinal studies could provide insight into how symptoms evolve over time and the long-term effects of various therapeutic interventions. By monitoring patients with FND across multiple points, researchers can better ascertain the chronicity of symptoms and the effectiveness of different treatment strategies.
Another vital area of exploration is the potential for personalized interventions based on the neurobiological profiles of patients. By utilizing advanced neuroimaging techniques, researchers can categorize individuals with FND according to their specific neural activation patterns during stress. This profiling may allow for tailored therapeutic approaches that address the unique sensorimotor integration challenges faced by each patient. More focused rehabilitation programs that cater to these differences might yield improved outcomes.
Additionally, investigating the impact of novel pharmacological treatments could be beneficial. Current evidence suggests that medications targeting the underlying neurobiological components might enhance traditional therapies. Trials incorporating agents that modulate neural plasticity or emotional regulation could provide insights into improving clinical outcomes for patients suffering from FND.
Furthermore, exploring the role of mindfulness and other stress-reduction techniques in managing symptoms of FND under stress can uncover valuable strategies for enhancing patient resilience. Preliminary studies have indicated that mindfulness-based stress reduction (MBSR) may support emotional regulation and reduce symptom severity. Future research should rigorously evaluate these techniques within clinical settings to determine their efficacy in ameliorating the psychiatric components of FND.
Another compelling line of inquiry could involve the exploration of biomarkers associated with FND. Identifying biological markers related to stress response or neuroinflammatory processes may lead to breakthroughs in understanding the underlying mechanisms of the disorder. A biomarker approach could offer objective measures that help tailor individual treatment strategies and potentially lead to earlier diagnosis.
Interdisciplinary collaborations between neurologists, psychologists, and rehabilitation specialists will be essential in advancing FND research. By working together, these practitioners can ensure that both the physical and psychological dimensions of FND are considered in developing comprehensive treatment plans. Multi-modal approaches that integrate physical rehabilitation with cognitive behavioral therapy (CBT) and pharmacological support may offer the most holistic solutions for managing this disorder.
Lastly, community education and awareness campaigns about FND are critical in reducing stigma, thereby encouraging patients to seek help earlier. Increasing public knowledge of the disorder can foster an environment where those affected feel supported and understood, which may enhance treatment compliance and overall outcomes.
| Research Focus | Pursuable Avenues | Potential Benefits |
|---|---|---|
| Longitudinal Studies | Follow patients over time | Understanding symptom evolution and treatment effects |
| Personalized Interventions | Tailor treatments based on neuroimaging data | Enhanced therapeutic outcomes |
| Pharmacological Treatments | Explore medications targeting neuroplasticity | Potential symptom reduction |
| Mindfulness Techniques | Evaluate stress-reduction methods | Improved emotional regulation |
| Biomarker Identification | Look for biological indicators of the disorder | Earlier diagnosis and tailored treatments |
| Collaboration | Integrate disciplines for comprehensive care | Holistic treatment approaches |
| Community Awareness | Improve public knowledge of FND | Reduced stigma and earlier help-seeking |