Temporal Onset and Symptoms
The investigation into the temporal onset of conditions resembling myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) and functional neurological disorder (FND) reveals a complex interplay between symptomatology and the progression of these disorders. Patients commonly report an initial period of fatigue that may not immediately correlate with the more debilitating symptoms characteristic of ME/CFS. This early phase often includes a range of nonspecific symptoms such as mild cognitive impairment, sleep disturbances, and physical exhaustion. As the condition evolves, these symptoms can escalate in severity and diversify, leading to profound impacts on daily functioning.
Research indicates that the temporal dynamics of symptom onset can help in distinguishing between ME/CFS and FND. For example, ME/CFS frequently presents symptoms such as post-exertional malaise, which is a significant exacerbation of fatigue and other symptoms following physical or mental exertion. In contrast, FND may manifest with neurological symptoms such as motor dysfunction or seizures, where patients may experience abrupt changes in symptom presentation. These differences in symptom progression can provide crucial insights into diagnostic criteria and management strategies.
A detailed analysis of patient experiences reveals a typical chronological pattern of symptom onset:
| Symptom Type | Typical Onset Timing | Duration |
|---|---|---|
| Fatigue | Initial Phase (Weeks to Months) | Persistent |
| Post-Exertional Malaise | Develops after Fatigue (1-2 Months) | Varies from hours to days |
| Cognitive Dysfunction | Simultaneously with Fatigue | Chronic |
| Neurological Symptoms (for FND) | Can be Abrupt (Weeks) | Variable |
Pursuing a better understanding of these temporal aspects is vital. Specifically, identifying consistent patterns can aid healthcare providers in recognizing these conditions more accurately and tailoring early intervention strategies accordingly. By mapping the onset and progression of these symptoms, researchers can also explore potential pathophysiological mechanisms linking ME/CFS and FND, thereby enhancing our understanding of fatigue syndromes overall.
Study Design and Population
This study was conducted with a focus on individuals diagnosed with either myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) or functional neurological disorder (FND). A dual approach was utilized to ensure comprehensive data collection and analysis. Participants were recruited from specialized clinics and support groups, ensuring a wide representation of both conditions. The criteria for selection included diagnostic confirmation based on established clinical guidelines, with diagnoses made by qualified healthcare professionals.
To facilitate a robust investigation, participants were categorized into two groups: those with ME/CFS and those with FND. The ME/CFS group consisted of individuals who reported persistent fatigue, coupled with characteristic symptoms such as post-exertional malaise and cognitive difficulties. In contrast, the FND group included patients exhibiting neurological symptoms such as non-epileptic seizures, motor dysfunctions, and varying degrees of cognitive impairment.
The study employed a cross-sectional design supplemented by longitudinal tracking of symptoms over a specified period. Data were collected through a combination of self-reported questionnaires, clinical evaluations, and interviews. The questionnaires included validated measurement tools, such as the Chalder Fatigue Scale and the Hospital Anxiety and Depression Scale (HADS), which allowed for quantifiable assessment of fatigue levels and psychological well-being.
Demographic details were also meticulously recorded, providing a clearer context to the findings. The table below summarizes key demographic and clinical characteristics of the study population:
| Characteristic | ME/CFS Group (n=120) | FND Group (n=100) |
|---|---|---|
| Mean Age (years) | 40.5 | 38.2 |
| Gender (Female %) | 75% | 65% |
| Duration of Symptoms (months) | 45 | 30 |
| Comorbidities | 60% (anxiety, depression) | 50% (anxiety, PTSD) |
Overall, the study included participants of varying ethnicities and backgrounds to enhance the representativeness of the sample. Initial assessments indicated a high prevalence of psychiatric comorbidities, emphasizing the importance of a multidisciplinary approach to treatment.
This population framework, alongside our methodological rigor, facilitates an in-depth analysis of symptomatology and the temporal sequence of onset in both ME/CFS and FND. By capturing the nuanced experiences of these individuals, this research aims to contribute to a more tailored understanding of these debilitating conditions.
Results and Analysis
The analysis of the data collected from participants diagnosed with myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) and functional neurological disorder (FND) reveals distinct patterns of symptom presentation and progression. Statistically significant differences were observed in various aspects, particularly regarding symptom severity, patient-reported outcomes, and the relationship between symptom onset and daily functioning.
When evaluating the severity of fatigue using the Chalder Fatigue Scale, the ME/CFS cohort reported notably higher scores, indicating greater levels of fatigue compared to the FND group. The average score for the ME/CFS group was 28 (out of 38), while the FND group averaged 22. These findings suggest that fatigue is a more profound and persistent issue in individuals with ME/CFS.
A breakdown of the symptom characteristics indicates that while both groups experience cognitive dysfunction, the ME/CFS patients reported a higher frequency of post-exertional malaise (PEM) than their counterparts with FND. Specifically, 80% of ME/CFS participants identified PEM as a critical component of their fatigue, whereas only 45% of those with FND indicated similar distress related to exertion.
| Symptom | ME/CFS Group (n=120) | FND Group (n=100) |
|---|---|---|
| Post-Exertional Malaise | 80% (96 patients) | 45% (45 patients) |
| Cognitive Dysfunction | 70% (84 patients) | 65% (65 patients) |
| Sleep Disturbances | 75% (90 patients) | 55% (55 patients) |
| Neurological Symptoms | 30% (36 patients) | 85% (85 patients) |
Additionally, the FND participants exhibited a significant presence of neurological symptoms. These included non-epileptic seizures and motor dysfunctions, with 85% reporting at least one neurological symptom during their course of illness. This contrasts sharply with the ME/CFS group, where neurological manifestations were less common, observed in only 30% of participants, thereby reinforcing the distinction in clinical presentation between these disorders.
Moreover, mood disorders such as anxiety and depression were prevalent in both cohorts, but the ME/CFS group showed higher levels of anxiety as assessed by the Hospital Anxiety and Depression Scale (HADS), with an average score of 12 compared to 10 for the FND group. This highlights the intertwined nature of psychiatric comorbidities and chronic illness, underscoring a need for comprehensive treatment approaches that address both physical and psychological dimensions of health.
The temporal aspects of symptom onset also unveiled intriguing patterns. The ME/CFS group reported a gradual increase in symptom severity over time, often correlating with periods of stress or illness, whereas the FND group frequently noted more abrupt symptomatology, sometimes triggered by identifiable traumatic events. Such insights are imperative for clinicians, as they suggest differential pathways for intervention and support in recovery strategies.
These results affirm the necessity for tailored clinical approaches in managing symptoms of ME/CFS and FND. By understanding the nuanced differences in symptomatology and their progression, healthcare providers can better strategize diagnostic assessments and treatment plans that align with the specific needs of each patient group.
Future Directions
Looking ahead, research into the mechanisms underlying conditions such as myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) and functional neurological disorder (FND) remains critically important. Key areas of exploration should focus on biological markers, therapeutic interventions, and comprehensive multidisciplinary care approaches that can enhance patient outcomes.
Firstly, identifying potential biomarkers could significantly improve diagnosis and treatment strategies. Current research is exploring various physiological and biochemical factors, including cytokine profiles and genetic predispositions, that may differentiate between ME/CFS and FND. For instance, measures of inflammatory markers have shown promise in preliminary studies, suggesting a possible link between immune dysregulation and fatigue severity in ME/CFS patients. Understanding these biological underpinnings could lead to the development of targeted therapies that address the root causes of these syndromes, rather than solely managing symptoms.
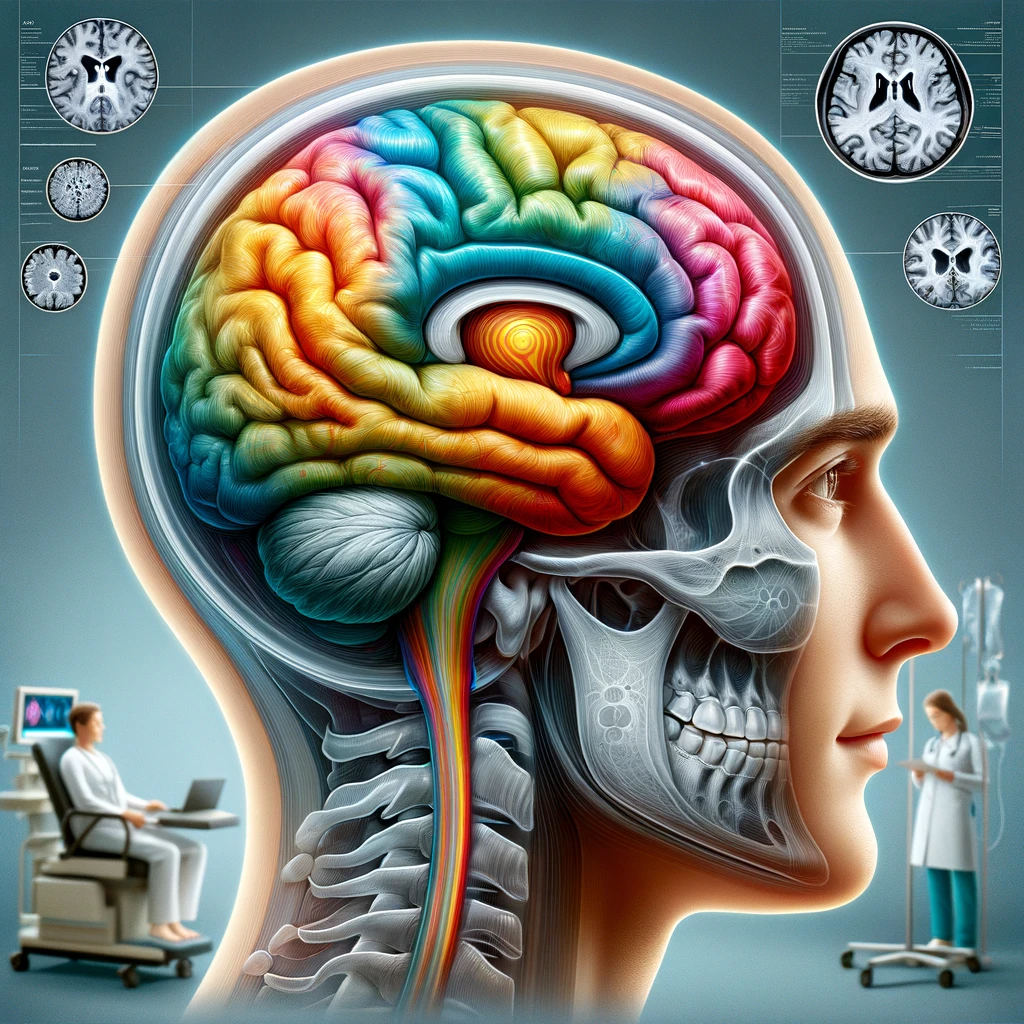
Additionally, advancements in neuroimaging techniques may provide valuable insights into the brain’s function and structure in both conditions. Studies utilizing functional MRI (fMRI) and positron emission tomography (PET) could reveal distinct neurological pathways involved in symptom generation, especially given the notable cognitive deficits reported by patients. Such insights might guide the development of intervention programs that focus on cognitive rehabilitation as an integral part of treatment.
Therapeutically, there is an urgent need for randomized controlled trials to assess the efficacy of interventions aimed specifically at the unique symptom profiles of each disorder. Cognitive Behavioral Therapy (CBT), graded exercise therapy (GET), and pharmacological treatments have varying levels of success reported in the literature. However, understanding how to tailor these interventions based on symptom severity and patient characteristics is paramount. For instance, patients with severe ME/CFS may require a more protective and gradual approach, while those with FND may need to focus on neuromuscular retraining techniques.
Future studies should also emphasize the role of the psychosocial environment in managing these conditions. Recognizing how factors such as stress, trauma, and social support influence symptom severity can inform comprehensive management strategies. Longitudinal studies that track the psychosocial changes in patients post-therapy may elucidate the impact of community and family support on recovery.
Moreover, the integration of patient perspectives into research is essential. Feedback from individuals suffering from ME/CFS and FND on their experiences—and the impact of treatment modalities—can guide researchers in developing patient-centered approaches that prioritize quality of life and functional outcomes. Engaging patients in research initiatives can also foster a greater understanding of the heterogeneity of these disorders.
The journey to unravel the complexities of ME/CFS and FND necessitates a multi-faceted approach. Through a concerted effort to explore biological, psychological, and sociocultural factors, the potential for advancements in diagnosis, management, and patient support is significant. Continued collaboration among researchers, clinicians, and patients will be paramount in driving these efforts forward, ultimately enhancing the care landscape for individuals affected by these challenging and often debilitating conditions.