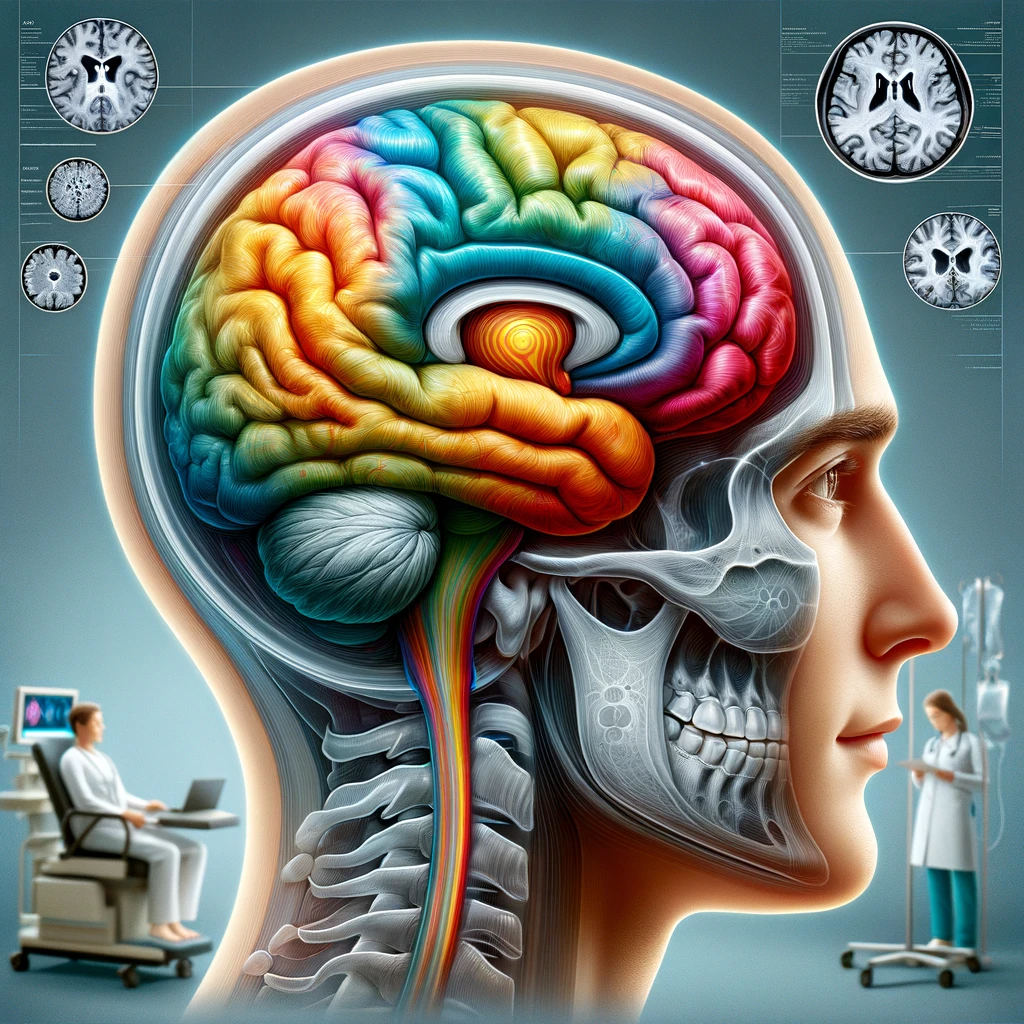
Case Presentation
The subject of this case study is a 32-year-old female presenting with symptoms indicative of complex post-traumatic stress disorder (C-PTSD) alongside episodes of psychogenic non-epileptic seizures (PNES). Her medical history includes several traumatic experiences, notably childhood abuse and a recent vehicular accident, which are believed to have contributed to the development of her psychological symptoms.
Upon initial evaluation, the patient reported experiencing recurrent intrusive memories related to past traumas, severe anxiety, and emotional dysregulation. These manifestations led to the development of avoidance behaviors, where she would actively steer clear of environments, individuals, or situations that reminded her of her traumatic experiences. This avoidance significantly impaired her daily functioning, affecting her capacity to maintain relationships and perform at her job.
During subsequent assessments, the patient demonstrated significant emotional distress, showing signs of hyperarousal, such as hypervigilance and exaggerated startle responses. Additionally, she experienced episodes that appeared consistent with seizures, accompanied by a loss of consciousness. However, these episodes differed from typical epileptic seizures; they did not yield any abnormal findings on electroencephalogram (EEG) testing, suggesting a psychogenic origin.
This clinical presentation highlights the intricate relationship between trauma and the manifestation of psychological and neurological symptoms. The patient’s condition underscores the complexity of diagnosing and treating C-PTSD, especially when it presents with non-epileptic seizure-like activities, which can further complicate the diagnostic landscape. A comprehensive medical evaluation, alongside thorough psychological assessments, is crucial in determining an accurate diagnosis and formulating a suitable treatment strategy.
As the case progressed, the patient was referred to a multidisciplinary team, which included a psychiatrist, psychologist, and neurologist, to address both her psychological and neurological symptoms holistically. The collaborative approach aimed to ensure a well-rounded treatment plan that incorporated therapy, medication, and supportive interventions tailored to her unique presentation.
Diagnostic Criteria
Establishing an accurate diagnosis for complex post-traumatic stress disorder (C-PTSD) coupled with psychogenic non-epileptic seizures (PNES) necessitates a thorough understanding of diverse diagnostic frameworks and criteria. For C-PTSD, the guiding principles are primarily outlined in the Diagnostic and Statistical Manual of Mental Disorders (DSM-5) and the International Classification of Diseases (ICD-11). The DSM-5 delineates post-traumatic stress disorder (PTSD) criteria, while C-PTSD is specifically addressed in the ICD-11, emphasizing symptoms that exceed the typical PTSD presentation.
According to the DSM-5, individuals diagnosed with PTSD must exhibit the following symptom clusters: re-experiencing the traumatic event, avoidance of reminders related to the trauma, negative alterations in mood and cognition, and marked alterations in arousal and reactivity. In the context of C-PTSD, additional symptoms may surface, including disturbances in self-organization, profound feelings of worthlessness, difficulty in maintaining interpersonal relationships, and persistent difficulty in regulating emotions. Such manifestations reflect the intricate layering of trauma that can compound over time.
Conversely, the ICD-11 expands on this profile by explicitly categorizing C-PTSD, which encompasses symptoms that arise in association with more complex trauma exposure, particularly in cases involving prolonged or repeated trauma. This classification facilitates recognition that these experiences often lead to pervasive and profound impairments in a person’s sense of self and relationships with others. The patient described in this case demonstrates several of these features, including pervasive feelings of hopelessness and disrupted emotional regulation, which align with C-PTSD criteria.
Diagnosis of psychogenic non-epileptic seizures (PNES) further complicates the clinical picture. PNES can mimic the physical symptoms of epileptic seizures, presenting challenges to clinicians. The diagnostic criteria for PNES emphasize the absence of neurological abnormalities upon electroencephalogram (EEG) testing, alongside a temporal relationship between seizures and psychological stressors. Clinicians must often distinguish between PNES and true epileptic seizures to ensure appropriate intervention strategies. In this case study, the patient’s EEG results indicated that episodes were not of an epileptic origin, thus reinforcing the diagnosis of PNES.
In assessing the patient, a comprehensive evaluation included both psychiatric assessments and neurological examinations to identify any underlying conditions contributing to her symptomatology. Collaboration with a multidisciplinary team allowed for a nuanced understanding of the relationship between her traumatic experiences and seizure-like episodes. This integrated approach highlights the necessity of evaluating both psychological and neurological factors in establishing a clear diagnosis. Employing tools such as clinical interviews, validated assessment scales, and standardized questionnaires proved beneficial in differentiating C-PTSD from other mental disorders and confirming the diagnosis of PNES.
Accurate diagnosis hinges on a careful assessment of the patient’s history, symptom presentation, and the integration of psychological and neurological evaluations. This ensures that the complexities of trauma-related disorders are fully understood and appropriately addressed, paving the way for effective treatment strategies moving forward.
Management Strategies
The management of complex post-traumatic stress disorder (C-PTSD) and psychogenic non-epileptic seizures (PNES) necessitates a comprehensive, individualized approach that integrates psychological therapies, medical treatments, and support services. Given the multifaceted nature of the patient’s symptoms, a collaborative strategy involving various healthcare professionals plays a crucial role in effective intervention.
Psychotherapeutic interventions are central to the treatment of C-PTSD. Therapeutic modalities such as trauma-focused cognitive behavioral therapy (TF-CBT) have shown efficacy in helping patients process traumatic memories and develop healthier coping mechanisms. This approach allows patients to reframe negative thoughts related to trauma and reduces symptoms of distress. Additionally, eye movement desensitization and reprocessing (EMDR) has been recognized as a beneficial treatment option for C-PTSD, facilitating emotional processing through guided bilateral stimulation while focusing on traumatic memories (Shapiro, 2014).
Alongside psychotherapeutic methods, supportive interventions such as group therapy can provide invaluable peer support, allowing the patient to connect with others who have had similar experiences. This communal aspect can foster a sense of safety and understanding which is often lacking in their daily lives. Psychoeducation is another key component; it empowers patients with knowledge about their condition, helping them recognize triggers for both their emotional and seizure-like episodes, thereby fostering greater self-management.
For managing PNES, it’s essential to utilize a multidisciplinary approach that may include neurologists, psychiatrists, and psychotherapists working in synchrony. Neurological evaluation focuses on confirming the absence of epileptic activity through EEG monitoring and ruling out other potential neurological disorders. Subsequent management might involve the use of physical grounding techniques during seizure-like episodes, aimed at helping patients develop skills to cope with and reduce the frequency of these occurrences (Reuber et al., 2003).
Pharmacotherapy can also be considered, although the mainstay treatment involves psychological strategies. Antidepressants or anxiolytics may be prescribed when there is a clear indication of accompanying mood or anxiety disorders. However, caution must be exercised because some medications may inadvertently exacerbate seizure-like episodes. A thorough evaluation is necessary to assess the risks and benefits of introducing these pharmacologic agents.
It is also critical to develop coping strategies tailored to the patient’s specific triggers. Mindfulness practices, relaxation techniques, and stress reduction strategies can assist in alleviating overall anxiety and improve emotional regulation. Introducing regular physical activity has shown improvements in mood and stress resilience, enhancing the overall quality of life for individuals diagnosed with C-PTSD and PNES.
Consistent follow-up and re-evaluation of management strategies are essential. Monitoring the patient’s progress allows the healthcare team to adjust treatments based on the evolving nature of symptoms and overall response to therapy. Building a strong therapeutic alliance based on trust and open communication between the patient and healthcare providers is paramount in fostering adherence to treatment plans and facilitating recovery.
Future Directions
Looking ahead, it is imperative to enhance our understanding of complex post-traumatic stress disorder (C-PTSD) and psychogenic non-epileptic seizures (PNES) through ongoing research efforts and the exploration of innovative treatment methodologies. One key area of potential advancement lies in the integration of neurobiological research with psychological paradigms. Understanding the neurobiological correlates of trauma and stress responses could lead to improved diagnostic techniques and personalized treatment options that are more effective for individuals experiencing these conditions.
Additionally, the interplay between trauma, psychological responses, and neurological symptoms necessitates a bi-directional exploration of treatment strategies. For instance, advancements in neuroimaging technologies could provide insights into how trauma alters brain structure and function, potentially informing targeted therapies. This could further enhance methods of neurofeedback and biofeedback, which hold promise in treating anxiety and seizure-like symptoms by helping patients gain control over their physiological responses (Hammond, 2005).
Another promising direction is the application of digital health interventions. The accessibility of mobile health technology offers opportunities for delivering therapeutic content and support via apps designed for trauma recovery and seizure management. These tools can provide real-time coping strategies, mindfulness exercises, and symptom tracking features, helping patients manage their conditions more effectively. Studies exploring the efficacy of such technologies are essential for validating their use within clinical practice.
Moreover, as societal understanding of mental health issues evolves, the reduction of stigma surrounding trauma-related disorders becomes increasingly important. Awareness campaigns highlighting the complexities of C-PTSD and PNES can lead to greater public understanding and encourage individuals to seek help. Advocacy for trauma-informed care within healthcare systems is crucial, ensuring that providers are trained to recognize and appropriately respond to the needs of trauma survivors while minimizing further psychological distress.
Ongoing longitudinal studies are necessary to assess the long-term outcomes of various treatment modalities. By following individuals with C-PTSD and PNES over extended periods, researchers can gather data on recovery trajectories, the effectiveness of different intervention strategies, and the impact of comorbid conditions. This robust data can inform clinical guidelines, facilitating evidence-based practices that are responsive to the diverse needs of affected individuals.