Clinical Characteristics of Focal Epilepsy
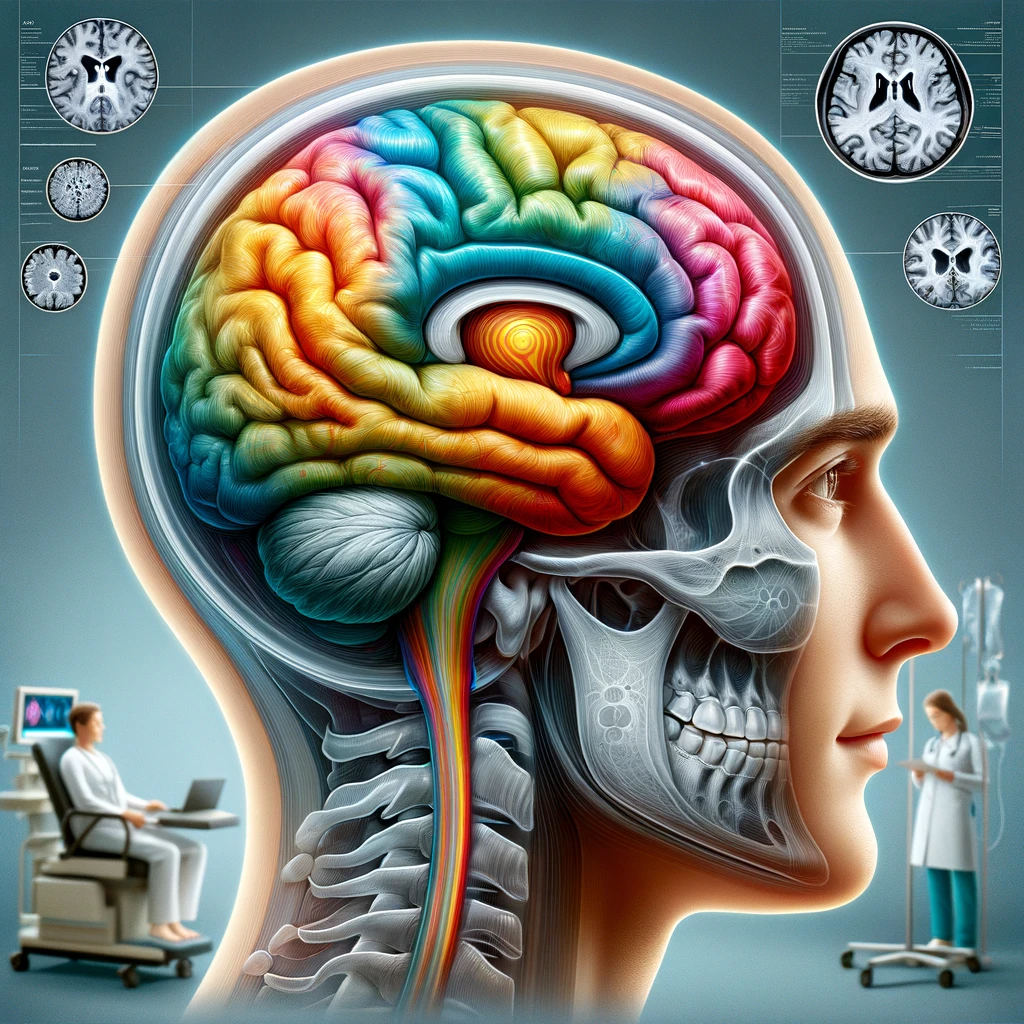
Focal epilepsy, characterized by seizures that originate in a specific area of one hemisphere of the brain, presents a variety of clinical features that can differ significantly among patients. These seizures are often classified based on whether they remain localized or spread to other brain regions, resulting in broader effects. The focal seizures can manifest in several ways, including motor, sensory, autonomic, or psychic symptoms, depending on the area of the brain involved.
Motor manifestations may take the form of repetitive movements or convulsions confined to one side of the body, reflecting the motor cortex’s involvement. In contrast, sensory focal seizures may lead to unusual sensations such as tingling, numbness, or auditory and visual hallucinations, indicating involvement of sensory pathways. Autonomic symptoms can comprise changes in heart rate, blood pressure, or gastrointestinal activities, evidencing the seizure’s impact on the autonomic nervous system.
Psychic symptoms, such as déjà vu or sudden emotional changes, highlight the role of limbic structures, particularly the temporal lobe, often implicated in temporal lobe epilepsy. The semiology of these seizures often provides valuable clues for diagnosis, although their presentation can be variable and sometimes misinterpreted.
An essential aspect of focal epilepsy is the concept of seizure thresholds; factors including stress, sleep deprivation, and metabolic disturbances can lower these thresholds, making seizures more likely to occur. In chronic cases, patients may develop an interictal state characterized by cognitive changes and emotional disturbances, which may coincide with the frequency of seizures.
Diagnosis typically involves an extensive history and a focused neurological examination, coupled with advanced neuroimaging techniques such as MRI and electroencephalograms (EEG). The latter is crucial for capturing the electrical activity during seizures, aiding in accurate localization of the epileptic focus. Despite these technological advancements, misdiagnosis can occur, particularly when symptoms overlap with other disorders, necessitating a nuanced understanding of the clinical features associated with focal epilepsy for effective management and treatment.
Distinguishing Features of Functional/Dissociative Seizures
Functional or dissociative seizures, often misattributed to epileptic events, represent a unique category of seizure-like episodes that are non-epileptic in nature. These seizures arise from psychological distress rather than direct neurological dysfunction, thus showcasing distinct clinical features that set them apart from focal epilepsy. Patients experiencing functional seizures often present with symptoms that may superficially resemble epileptic seizures but bear unique characteristics tied to their psychological context.
One of the primary distinguishing features is the variability in the patients’ awareness and responsiveness during an episode. In functional seizures, patients may exhibit altered awareness or might even appear fully conscious, engaging with the environment in ways that are atypical for epileptic seizures. This responsiveness can include following commands or engaging in purposeful movements, contrasting notably with the postictal state often seen after true epileptic seizures, where patients typically experience confusion and reduced responsiveness.
The duration and frequency of events can also provide diagnostic clues. Functional seizures tend to be longer in duration, often spanning several minutes to hours, whereas epileptic seizures usually last shorter, generally under two minutes. Additionally, the frequency of functional seizures can exhibit significant fluctuations, triggered by psychosocial stressors rather than a fixed neurological basis.
The semiology of these seizures is another critical differentiator. Functional seizures may present with atypical jerking movements or unusual postures that differ from the rhythmic and stereotypical movements observed in focal seizures. Features such as emotional distress, background stress, or traumatic experiences may often precede these episodes, indicating an episodic trigger rooted in psychological mechanisms.
Moreover, the presence of muscle tonicity can vary in functional seizures. Some individuals may demonstrate sudden loss of tone or jerky movements that would not typically be associated with classic seizure pathways. Such discrepancies are pivotal for clinicians when determining the nature of the seizure.
Even the context in which seizure episodes occur can aid in distinguishing these events. Functional seizures often manifest in environments or circumstances marked by emotional upheaval or psychological conflict, supporting the theory that they are deeply interwoven with the mental health of the individual. For instance, patients may report their episodes coinciding with specific life events or stresses, adding weight to the psychological components of these seizures.
Understanding the psychological underpinnings is crucial for treatment. Often, patients benefit from psychological interventions in addition to any necessary medical management, as addressing the root psychological issues can lead to significant reductions in seizure frequency. Recognizing dissociative seizures accurately is vital to prevent unnecessary medical interventions that target epilepsy, fostering a more effective treatment plan tailored to the underlying psychological aspects of the disorder. This nuanced approach not only improves patient outcomes but also enriches the healthcare provider’s comprehension of seizure disorders, bridging the gap between neurology and psychiatry in the management of these complex cases.
Comparative Analysis of Diagnostic Outcomes
In evaluating the diagnostic outcomes for patients presenting with focal epilepsy versus those with functional or dissociative seizures, significant disparities arise, reflecting the complex nature of these conditions. Accurate diagnosis is paramount, as it dictates the course of treatment and ultimately influences patient quality of life.
Studies show that the prevalence of misdiagnosis in patients experiencing functional seizures is notably high, often reaching up to 30%. This is largely attributed to the overlapping symptoms with focal epilepsy, where clinicians may misinterpret the semiological features due to insufficient awareness or understanding of the distinct characteristics of functional seizures. For instance, a patient exhibiting jerky movements may be quickly categorized under the epileptic spectrum without considering the psychological triggers that may be at play.
Conversely, patients diagnosed with focal epilepsy may feel the burden of unnecessary treatments if there is an underlying non-epileptic cause. The reliance on neuroimaging and EEG findings can sometimes lead to an overemphasis on structural or electrical brain abnormalities, which might not always be present in cases of functional seizures. This highlights the pivotal role of thorough clinical assessments including detailed patient histories and behavioral observations during seizure-like events.
Diagnostic methodologies continue to evolve, prompting adaptations that consider the personal context of the patient as well as the clinical presentation. For instance, assessing the patient’s background for psychosocial stressors can provide critical insights. Intriguingly, patients who experience functional seizures often recount their episodes coinciding with specific life stressors, suggesting that a psychosocial evaluation could enhance diagnostic precision.
Furthermore, quantitative measures, such as the frequency and length of episodes, provide objective benchmarks that can assist clinicians in distinguishing between these seizure types. While focal seizures tend to be shorter and more predictable, functional seizures typically demonstrate greater variability in duration and can be contextually influenced by emotional states. This variability should prompt healthcare professionals to adopt a more holistic approach to diagnosis, incorporating both quantitative data and qualitative reports from patients.
Integrating advanced diagnostic tools, such as video EEG monitoring, can also lead to more accurate outcomes. This technique allows for real-time observation of seizure episodes, helping to distinguish these complex events based on electrographic activity and correlating clinical features. Identification of an absence of epileptiform activity during events can be a crucial indicator of functional seizures, helping to prevent misdiagnosis.
An analysis of healthcare systems reveals that disparities in access to specialized care can also affect diagnostic outcomes. Patients in primary care settings may receive preliminary diagnoses that fail to capture the nuances of their symptoms, particularly in regions lacking resources for comprehensive neurological evaluations. This underscores the necessity for robust training for general practitioners, enhancing their ability to recognize atypical presentations of seizures.
In summary, the comparison between diagnostic outcomes for focal epilepsy and functional seizures illustrates a critical need for refined diagnostic strategies that account for the subtle yet significant differences between these conditions. Enhancements in clinical training, patient assessment techniques, and diagnostic technology can collectively improve the accuracy of initial diagnoses, ultimately leading to more effective management strategies tailored to the specific needs of each patient. The path forward lies in fostering collaboration between neurology and psychiatry, promoting a comprehensive understanding of seizures that transcends traditional medical boundaries.
Recommendations for Improved Diagnostic Accuracy
To enhance the accuracy of distinguishing between focal epilepsy and functional or dissociative seizures, several key recommendations should be implemented within clinical practice. The first step involves elevating clinician awareness and understanding of the defining characteristics that separate these seizure types. Training programs that focus on the semiology of seizures should incorporate case studies and practical examples of both epilepsy and dissociative disorders. Such programs can serve to illuminate the complexities of seizure presentations, enabling healthcare providers to recognize subtle differences during patient evaluations.
Standardized assessment protocols could also be instituted, requiring clinicians to conduct thorough and systematic histories that encompass not just the clinical features of the seizure episodes but also the psychosocial context surrounding them. Documentation of a patient’s emotional state, life changes, and potential stressors leading up to the events can provide valuable insights that may not be apparent through neurological examinations alone. Therefore, integrating a structured template for patient evaluation can ensure a more holistic approach, supporting clinicians in identifying essential factors that correlate with the patients’ seizure profiles.
Developing interdisciplinary collaboration stands as another pivotal recommendation. Healthcare providers in neurology, psychology, and psychiatry should work together to create a unified framework for diagnosis and treatment. Regular case discussions among professionals from these specialties can foster shared knowledge and approaches, reducing the risk of misclassification of seizure types. Such collaborations can promote the development of integrated care pathways, wherein both psychological support and medical management are offered concurrently.
The utilization of advanced technological tools must also be emphasized to bolster diagnostic confidence. Video EEG monitoring is particularly beneficial, allowing for real-time monitoring of seizure activity and the ability to correlate clinical observations with electrical brain activity. Implementing this technology widely within clinical settings can assist in identifying non-epileptic events more swiftly and accurately, thus reducing unnecessary treatments and anxiety for patients.
Furthermore, incorporating patient-reported outcomes into diagnostic processes can enhance understanding of individual experiences with seizures. The subjective descriptions of seizure events, including their triggers and associated sensations, can provide critical data, enabling clinicians to contextualize clinical findings within the patient’s reality. Engaging patients effectively through surveys or structured interviews may yield insights that quantitative measures alone might overlook.
Encouraging a culture of continuous education and professional development within the field is vital. Healthcare settings should provide ongoing training opportunities, enabling clinicians to keep up-to-date with the latest findings and methodologies related to seizure diagnosis. This commitment to education ensures that practitioners are always equipped with the most current tools and knowledge, ultimately benefiting patient care.
Moreover, fostering patient education regarding the nature of their condition can empower individuals to engage actively in their management. Information sessions about the distinctions between epilepsy and dissociative seizures can help patients better articulate their experiences to healthcare providers, leading to more focused assessments.
Lastly, promoting access to specialized diagnostic centers can mitigate issues related to misdiagnosis, especially in under-resourced areas. Creating a network of referral pathways can ensure that patients with ambiguous symptoms are directed to the appropriate specialists for comprehensive evaluation. This strategy would not only improve diagnostic accuracy across diverse clinical settings but also heighten collaboration among providers, benefiting overall patient outcomes.
In conclusion, implementing training and education, enhancing interdisciplinary collaboration, utilizing advanced diagnostic technologies, incorporating patient perspectives, and improving access to specialized care can significantly improve the diagnostic accuracy of focal epilepsy and functional/dissociative seizures. These strategies will lead to more tailored and effective patient care, increasing the likelihood of better clinical outcomes for individuals experiencing these complex conditions.