Study Overview
This case report delves into Functional Neurological Symptom Disorder (FNSD), a condition often characterized by neurological signs or symptoms that cannot be attributed to any underlying medical disorder. The primary focus is on how incomplete diagnostic communication can lead to a misinterpretation of symptoms, complicating the patient’s journey to an accurate diagnosis. In a clinical setting, effective communication among healthcare professionals is crucial for ensuring that patients receive appropriate care and treatment for their conditions. This case illustrates the significant impact that misunderstandings and vague diagnostic language can have on patient outcomes.
The report outlines the experience of a patient who presented with neurological symptoms that were not readily explained by traditional medical assessments. These manifestations can vary widely and may include weakness, paralysis, seizures, or other movement disorders, all of which can often mimic conditions such as stroke or multiple sclerosis. The case brings attention to how these symptoms can obscure the underlying functional nature of the disorder, leading to unnecessary tests and potentially harmful treatments.
By analyzing the diagnostic process followed in this particular case, the study seeks to uncover the discrepancies that arose from diagnostic communication lapses. This report underscores the importance of recognizing FNSD not as a purely psychological issue, but rather a complex interplay of neurological and psychological factors, necessitating thorough assessment, sensitivity, and awareness among healthcare providers. Highlighting this case will aid in paving a path toward improved strategies for diagnosis and management of FNSD, ultimately leading to better care for affected individuals.
Methodology
The methodology employed in this case report involved a detailed examination of a single patient’s clinical history, diagnostic evaluations, and treatment trajectory. The patient was initially seen in a neurology clinic after presenting with a collection of concerning neurological symptoms that included episodic weakness, non-epileptic seizures, and fluctuating sensory disturbances. Such manifestations were carefully recorded and categorized, documenting the onset, duration, and intensity of symptoms, as well as any triggering factors noted by both the patient and attending medical staff.
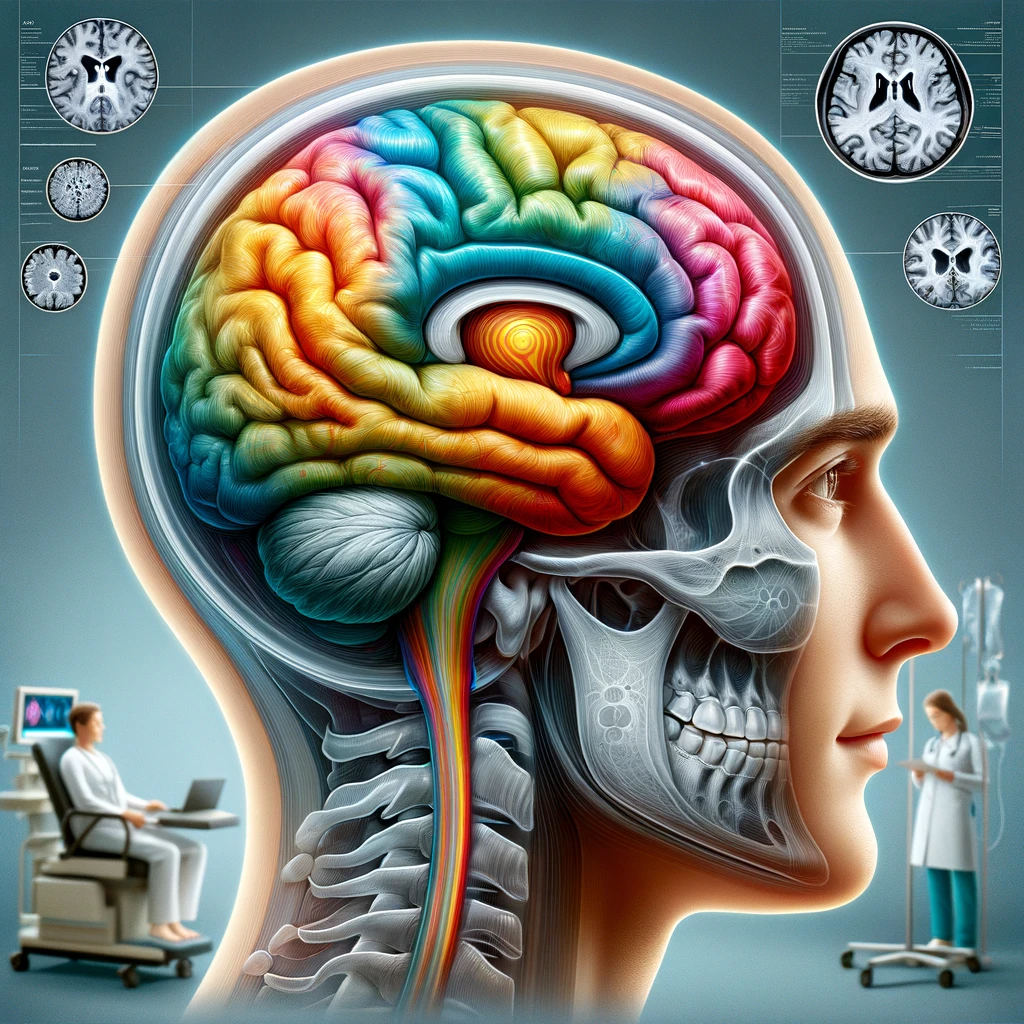
A multidisciplinary approach was taken, incorporating inputs from neurologists, psychiatrists, and physiotherapists to ensure a comprehensive evaluation of the patient’s condition. This collaboration aimed to rule out other possible neurological disorders that could account for the symptoms. Various diagnostic tests, including MRI scans, EEGs, and blood tests, were conducted to exclude conditions like stroke, multiple sclerosis, and epilepsy, which could present with similar symptoms. Importantly, all neuroimaging and electrophysiological findings were within normal ranges, aligning with the hypothesis of a functional disorder.
The assessment also included structured interviews and psychological evaluations to gauge the patient’s psychosocial history. The mental health assessment focused on any emotional stressors and coping mechanisms that could relate to the onset of symptoms, considering that psychological well-being often intersects significantly with functional neurological symptoms. Standardized questionnaires were administered to quantify anxiety and depression levels, which provided additional context to the symptom presentation.
Communication between clinicians was meticulously documented, revealing how lapses in the clarity of diagnostic language contributed to confusion regarding the nature of the symptoms. Case discussions among the healthcare team were recorded, highlighting instances where terminologies like ‘conversion disorder’ and ‘psychogenic seizures’ were utilized, which could unintentionally signal to the patient that their symptoms lacked a legitimate basis. This ambiguity likely affected the patient’s understanding and trust in the diagnostic process.
Throughout the study, careful attention was given to ethical considerations, ensuring the patient’s confidentiality and securing informed consent for the use of their medical information in this report. The overall goal of this methodology was to paint a comprehensive picture of the diagnostic journey, illustrating the complexities and challenges associated with recognizing FNSD in clinical practice. By chronicling this case meticulously, the report aims to contribute to a deeper understanding of FNSD and foster improvements in diagnostic communication strategies among clinicians.
Key Findings
The analysis of the patient’s case revealed several significant insights into the nature of Functional Neurological Symptom Disorder (FNSD) and the broader implications of diagnostic communication within clinical environments. One of the most striking findings was the recognition that despite the presence of clear neurological symptoms, the absence of identifiable organic pathology can lead to misinterpretations by healthcare professionals. This misinterpretation can ultimately result in delays in diagnosis and inappropriate treatments, contributing to patient distress and perpetuating their condition.
Throughout the course of diagnosis and treatment, the patient’s symptoms — which included episodes of weakness and non-epileptic seizures — were documented as fluctuating and often correlated with various psychosocial stressors. Importantly, the multidisciplinary assessment confirmed that all neuroimaging and EEG results were normal, implying that no structural abnormalities could be found to account for the clinical manifestations. This affirms the view that FNSD may arise from a complex interplay of neurologic and psychological factors rather than being rooted in purely mental illness.
Key observations also centered around the implications of diagnostic language. Use of terms such as “conversion disorder” and “psychogenic” was noted to inadvertently suggest to the patient that their symptoms were primarily psychological, which could undermine the validity of their experience. This language creates a potential barrier to openness, whereby the patient may perceive their suffering as less legitimate or serious, leading to hesitance in discussing their symptoms further. Consequently, this may create a vicious cycle where misunderstanding impedes the effective communication of symptoms, which is crucial for accurate diagnosis.
The report documented that following a more precise re-evaluation of terminology and diagnostic communication, the patient’s understanding of their condition improved notably. This change in approach facilitated a shift in the patient’s trust towards the medical team and fostered a collaborative dynamic, allowing for more effective management strategies to be implemented. The findings suggest that enhanced clarity and empathy in communication are vital for navigating the complexities associated with FNSD.
Lastly, the case underlines the necessity for ongoing education and training for medical professionals focusing on FNSD. Awareness and understanding of the psychological aspects of such disorders can encourage providers to adopt a more holistic perspective, which ultimately enhances patient care. Working towards improved interdisciplinary communication protocols can be essential in bridging gaps in understanding, ensuring a more integrated approach to patient diagnosis and management.
Clinical Implications
The implications for clinical practice stemming from this case report are profound, highlighting the urgent need for improved awareness and sensitivity surrounding Functional Neurological Symptom Disorder (FNSD). Recognizing FNSD as a legitimate diagnostic entity rather than a mere psychological phenomenon is essential for fostering an environment where patients feel validated in their experiences. Proper acknowledgment of the condition’s complexity can lead to more appropriate clinical responses and reduce the stigma that often surrounds functional disorders.
One of the critical areas for improvement is in the communication style of healthcare professionals. The case illustrates how the phrasing and terminology used can significantly impact a patient’s understanding of their condition. Terms like ‘conversion disorder’ can delegitimize patients’ experiences and contribute to a cycle of misunderstanding and mistrust. Training programs for medical staff should emphasize the importance of empathetic and clear communication, facilitating an atmosphere where patients feel comfortable discussing their symptoms without fear of being dismissed or misunderstood. This approach can encourage dialogue that captures the full scope of a patient’s experiences and promote collaborative decision-making in their care.
Moreover, the interdisciplinary nature of treating FNSD necessitates that various healthcare providers—neurologists, psychiatrists, physiotherapists—work closely together to deliver a cohesive treatment plan. Routine case conferences, where professionals can share insights and updates on patient progress, can help address the challenges posed by complex symptom presentations. These collaborative discussions can promote a unified understanding of the disorder and foster integrated care strategies that account for both the physical and psychological dimensions of the patient’s experience.
Education plays a vital role in addressing these clinical implications. Continual training focused on the biopsychosocial model of care can better equip clinicians to recognize the interplay of physical and mental health factors that contribute to FNSD. This educational approach should extend beyond initial training, incorporating ongoing professional development to keep healthcare workers abreast of emerging research and best practices in managing functional neurological symptoms.
The findings underscore that addressing the psychological components of FNSD should not overshadow the physical symptoms exhibited by patients. Providing a supportive therapeutic environment, where psychological health is taken into account without diminishing the patient’s physical experiences, can enhance treatment outcomes. Cognitive-behavioral therapies, tailored to help patients understand and manage their symptoms, can be particularly effective when combined with physical rehabilitation strategies.
Lastly, the report’s implications extend to policy-making within healthcare systems. Developing standard protocols that encourage clear communication about FNSD can foster consistency in the diagnostic process. These guidelines could cover acceptable terminology, interdisciplinary communication practices, and patient-centered approaches that prioritize understanding and empathy. By championing these changes, healthcare leaders can help create a system that is responsive to the unique challenges associated with functional neurological symptoms, ultimately improving patient care and satisfaction.