Case Presentation
A 34-year-old female presented to the neurology clinic with a series of unexplained neurological symptoms that began six months prior. She reported experiencing episodes of significant weakness in her limbs, which were intermittent and not consistent with typical neurological disorders. During these episodes, she described a profound inability to move her arms and legs, accompanied by a sense of disorientation and anxiety.
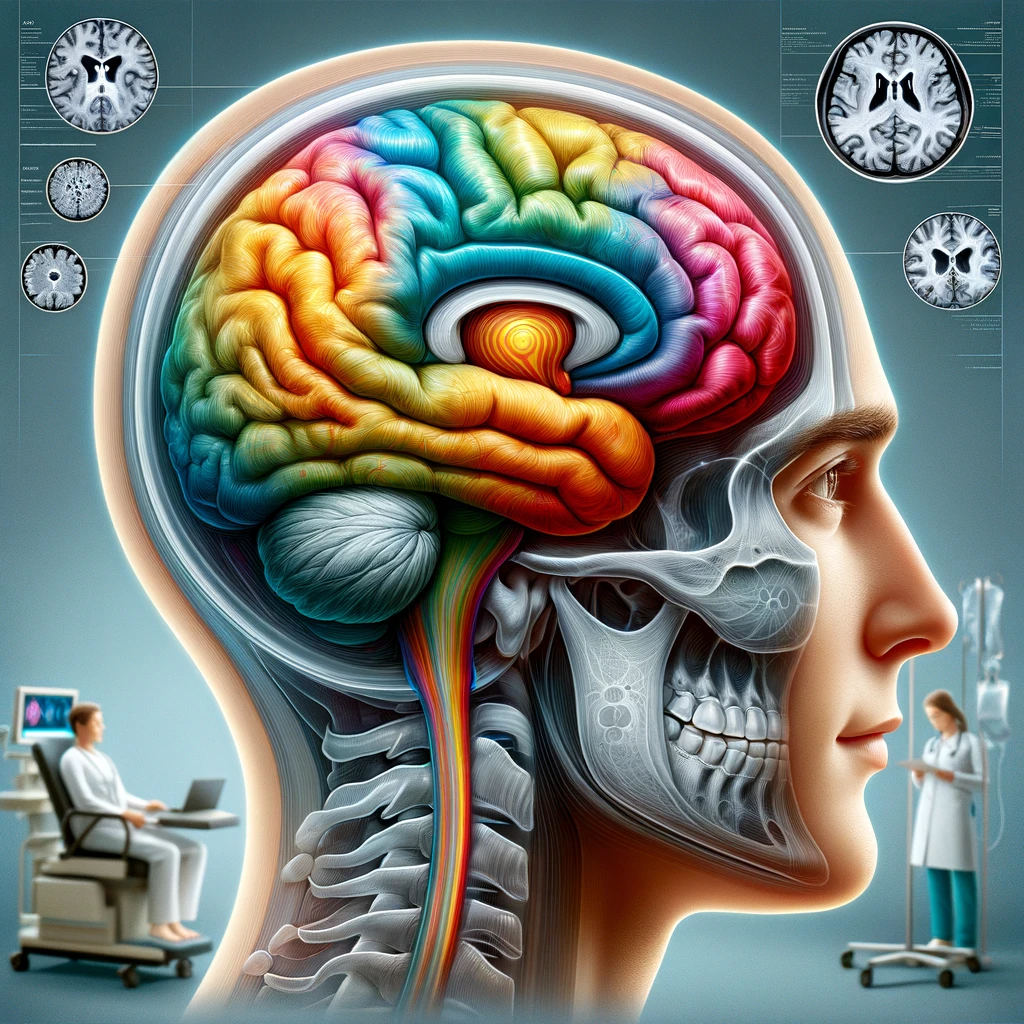
The patient’s medical history was notable for a previous diagnosis of anxiety disorder, which she managed with therapy but had not required medication. She experienced increased stress due to work difficulties and personal relationships, which seemed to coincide with the onset of her neurological symptoms. Neurological exams performed at several points showed no clear signs of organic disease, as imaging tests including MRI scans of the brain were unremarkable, revealing no structural abnormalities.
On closer investigation, her episodes were found to coincide with periods of significant psychological stress. During these occasions, she expressed feelings of being overwhelmed, which appeared to trigger the onset of her physical symptoms. Additionally, family members noted that her symptoms would often resolve during periods of distraction or when she was engaged in conversation, raising further questions regarding the nature of her condition.
Despite the myriad assessments performed, the patient was initially misdiagnosed with a somatoform disorder due to overlapping symptoms commonly associated with anxiety and panic disorders. This misalignment in diagnostic communication complicated her care, leading to inappropriate treatment strategies focused on pharmacological interventions instead of addressing the functional aspects of her condition.
The complexity of her situation was underscored by the patient’s persistent sense of humility mixed with frustration regarding her symptoms. The incongruence between her clinical presentation and diagnostic conclusions prompted further discussions among her healthcare providers, ultimately leading to a reevaluation of her condition through a multidisciplinary approach. This method considered not only her neurological symptoms but also the psychosocial factors likely contributing to her functional neurological symptoms.
Diagnostic Challenges
In the case of the 34-year-old female patient, the diagnostic process was riddled with complexities that often accompany conditions like Functional Neurological Symptom Disorder (FNSD). Initial assessments focused on standard neurological evaluations, given the patient’s adherence to a classical presentation of neurological symptoms. However, her symptoms—ranging from intermittent limb weakness to episodes of disorientation—were not consistent with recognized neurological disorders, which created a challenge for accurate diagnosis.
One significant obstacle was the lack of observable abnormalities in diagnostic imaging and laboratory tests. The unremarkable MRI scans and normal neurological findings led to difficulties in convincing both the patient and the healthcare team that her symptoms stemmed from functional rather than organic causes. This often manifests in a cycle wherein patients are subjected to multiple evaluations and unnecessary tests, incurring financial and emotional strain without achieving clarity regarding their condition.
Furthermore, the interplay between her psychological and physical symptoms complicated the diagnostic narrative. The patient’s pre-existing anxiety disorder likely contributed to an overlapping symptomatology, leading healthcare providers to consider diagnoses associated with somatoform disorders. This misdiagnosis can perpetuate a stigma that functional symptoms are “not real,” hindering the patient’s ability to procure empathetic and effective care. The initial focus on psychiatric management alone, without integrating a comprehensive approach that addressed both the psychological and functional dimensions, was a significant misstep in her treatment plan.
During interprofessional discussions, discrepancies in communication arose between the psychological and neurological frameworks for understanding her condition. The potential for diagnostic overshadowing became apparent: her history of anxiety potentially colored the perception of her current symptoms, which were dismissed as purely psychosomatic, rather than being considered as complex manifestations of FNSD that require a nuanced understanding of both psychological stressors and neurological presentations.
Additionally, the variability of her symptoms played a crucial role in diagnosis challenges. Episodes that resolved during distraction suggested an incomplete acknowledgment of FNSD’s core features, where neurological function may be influenced by psychological states. This inconsistency can often evade the notice of even seasoned practitioners, making a thorough understanding of the patient’s condition crucial to avoiding misdiagnoses.
As evidenced by her case, the necessity for effective communication among multidisciplinary teams cannot be overstated. Regular discussions were held not only to reassess her symptoms but also to ensure all providers were in sync regarding the evolving understanding of her condition. A united approach, integrating neurological, psychological, and social aspects, was essential in clarifying the diagnosis and transitioning towards more appropriate management strategies.
Management Strategies
Management strategies for the 34-year-old female patient with Functional Neurological Symptom Disorder (FNSD) necessitate a comprehensive, multidisciplinary approach that addresses both her physical and psychological symptoms. Recognizing the interplay between her neurological presentation and the underlying psychological factors is crucial to developing effective interventions.
Initially, a reorientation of treatment focus was required. Rather than continuing with solely pharmacological interventions, which had proven ineffective, the healthcare team prioritized a combination of cognitive-behavioral therapy (CBT) and physical therapy. CBT is well-supported by literature as an effective strategy for conditions where psychological factors play a significant role in symptomatology, such as FNSD. This therapy is designed to help patients develop coping strategies, challenge the negative thought patterns that may exacerbate their symptoms, and enhance their problem-solving skills, thereby increasing their overall resilience to stressors that could trigger symptom episodes.
Physical therapy was likewise integral to her management plan. Given the patient’s significant weakness during her episodes, a personalized physical rehabilitation program was devised to foster gradual improvements in strength and mobility. The physical therapist employed techniques aimed at encouraging functional movement patterns while assisting her in developing greater body awareness. Importantly, these sessions were structured to be supportive and non-threatening, allowing her to gain confidence in her physical abilities and reducing the focus on her symptoms. Incorporating mindful movement practices, such as yoga or tai chi, may also be beneficial, as they focus on building physical competence while simultaneously promoting relaxation and mindfulness, thus addressing both physical and emotional facets of her condition.
Furthermore, psychoeducation played an essential role throughout her treatment process. Educating the patient about FNSD, the nature of functional symptoms, and the relationship between stress and neurological function can help demystify her experience and validate her feelings. Understanding that her symptoms are real and not merely ‘in her head’ is vital for alleviating some of the guilt and frustration associated with her condition. Family involvement in this educational process also helps to foster a supportive home environment, which can reduce stress and facilitate faster recovery.
In addition to individual interventions, fostering open communication and regular check-ins among the multidisciplinary team is paramount. This team comprised neurologists, psychologists, physiotherapists, and occupational therapists, all working collaboratively to ensure that treatment approaches remained aligned with the patient’s needs as they evolved. Weekly meetings were held to discuss her progress, share observations from different perspectives, and adjust the treatment plan as necessary. This coordinated effort supports the understanding that FNSD is often multifactorial, requiring adaptability in management strategies.
Integration of lifestyle modifications also constituted a vital part of management. Addressing the patient’s stressors through wellness programs, relaxation techniques, and promoting a healthy lifestyle might contribute to better outcomes. Encouraging regular physical activity, balanced nutrition, and adequate sleep promotes overall well-being and resilience against stress, which can further aid in mitigating the intensity or frequency of her symptoms.
Finally, patient-centered care remained central to her management strategy. Involving the patient in her treatment decisions, thus enhancing her sense of agency, is essential for fostering engagement and adherence to the prescribed interventions. Building a trusting relationship with her healthcare providers further reinforced her commitment to the management plan, as she began to feel more understood and supported.
A holistic and flexible approach that incorporates psychological, physical, and social considerations can lead to significant improvements in patients with FNSD. By embracing the complexity of their conditions and employing multifaceted strategies, healthcare teams can better navigate the path toward recovery and improved quality of life for patients like the one discussed.
Conclusion and Future Directions
The journey of understanding and managing Functional Neurological Symptom Disorder (FNSD) in this patient highlights the multifaceted nature of such conditions and the necessity for a comprehensive management approach. Essential to addressing her needs was an acknowledgment that FNSD often entails an intricate interplay between neurological symptoms and psychological stressors. This understanding paved the way for targeted interventions that combine therapeutic modalities with lifestyle adjustments aimed at promoting overall well-being.
Key management strategies included tailored cognitive-behavioral therapy (CBT), which focuses on modifying unhelpful thought patterns and behaviors that exacerbate her symptoms. By equipping the patient with strategies to confront her anxiety and stress, CBT served to empower her in navigating the challenges posed by FNSD. It also facilitated the development of new coping mechanisms for dealing with stressful situations, which were instrumental in alleviating the psychological components of her condition.
Complementing CBT, physical therapy was integral in addressing her physical incapacities. This involved gradual rehabilitation aimed at restoring functional movement and enhancing her physical capabilities, critical amidst her symptomatic episodes. By employing techniques that promoted safe and supportive engagement with her body, the therapy helped her rebuild confidence, reinforcing the idea that improvement was possible. The incorporation of mindfulness practices into her routine fostered a holistic approach, merging physical and emotional healing.
Moreover, psychoeducation remained a cornerstone of her treatment. Educating both the patient and her family about the nature of FNSD played a crucial role in fostering understanding and support. This knowledge not only helped debunk myths surrounding the legitimacy of her symptoms but also encouraged family involvement, creating a nurturing environment conducive to her recovery. Informed families can significantly enhance a patient’s coping capacity and emotional resilience.
Continuous communication among the multidisciplinary team was vital in adapting management strategies to the patient’s evolving needs. Regular discussions involving neurologists, psychologists, physiotherapists, and occupational therapists ensured a cohesive approach tailored to the intricacies of her case. Such collaboration encouraged a dynamic and holistic treatment plan, capable of addressing the complexities of FNSD effectively.
Lifestyle modifications emerged as an essential component in her management strategy, addressing environmental and psychosocial elements that could trigger her symptoms. Encouraging regular exercise, balanced nutrition, and relaxation practices contributed to an overall improvement in her resilience and stability. By holistically addressing the interplay between mind and body, the management plan sought not just symptom relief but also the enhancement of her quality of life and functional status.