Understanding Coprolalia
Coprolalia is characterized by the involuntary utterance of inappropriate or obscene words and phrases, often associated with Tourette syndrome (TS). While it’s a well-known symptom in the general public’s perception of TS, it is important to note that not all individuals with TS exhibit coprolalia. In fact, reports suggest that coprolalia occurs in only a minority of those diagnosed with TS, with prevalence estimates ranging from 10% to 15% of affected individuals. This disparity leads to misconceptions about the disorder, emphasizing the need for a more nuanced understanding.
Many individuals with TS may experience other forms of involuntary speech that do not include coprolalia, such as echolalia (repeating others’ words) or palilalia (repeating one’s own words). The nature of these vocal tics can vary widely, and their expression may be influenced by various factors, including stress levels, environment, and individual experiences. Understanding the broader spectrum of tic manifestations is crucial for demystifying TS and addressing stigma associated with the disorder.
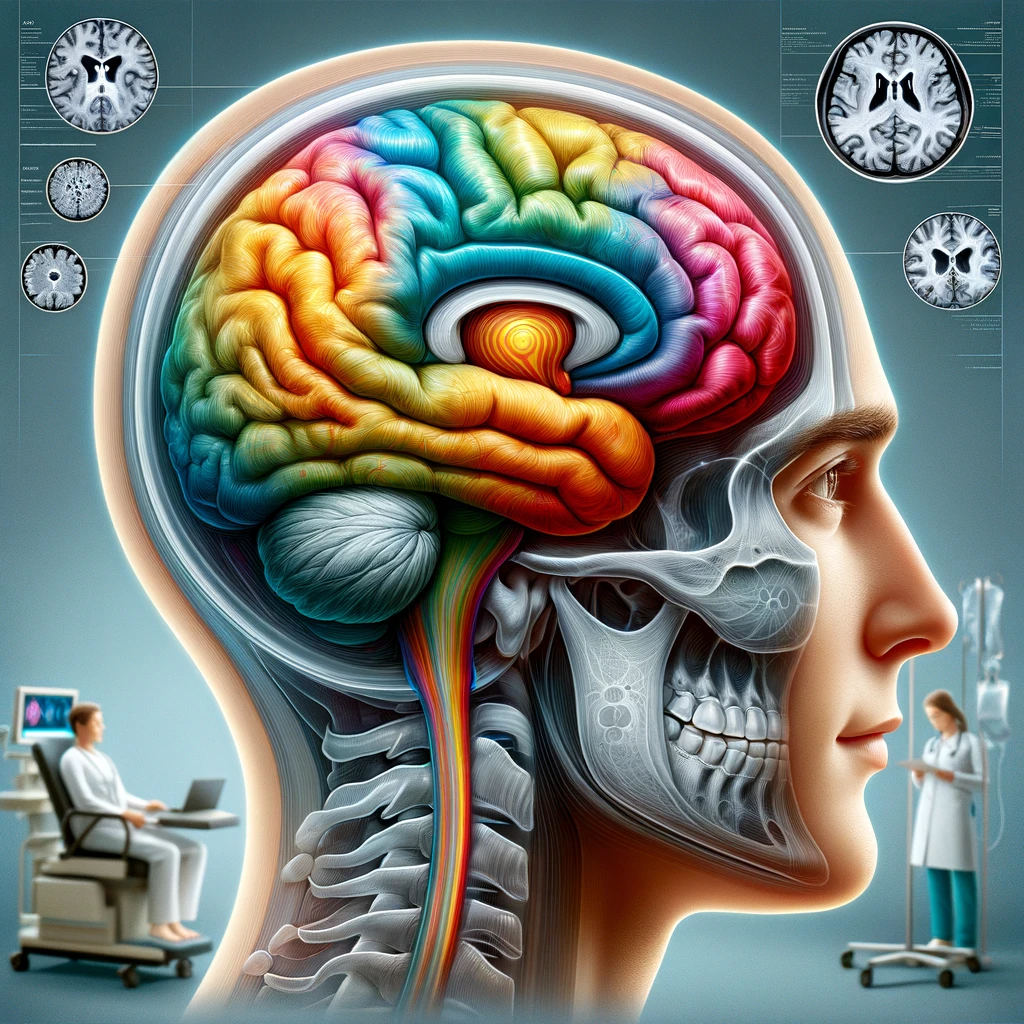
The mechanisms underlying coprolalia remain a subject of active research. Neurological studies indicate that abnormal activity in specific brain regions, particularly the basal ganglia, may contribute to the development of tics, including coprolalia. Neurotransmitters such as dopamine are thought to play a significant role in the expression of various tics, as they influence motor control and behavior regulation. Despite advancements in understanding these biological substrates, the precise pathways leading to coprolalia are not fully elucidated.
Psychological factors can also contribute to the expression of coprolalia. Emotional responses, social contexts, and individual personality traits may influence the occurrence and severity of vocal tics. Interestingly, some research suggests that anxiety and excitement levels can exacerbate tic expression. This interplay highlights the multifaceted nature of the disorder, where biological, psychological, and environmental components converge.
In sum, coprolalia represents a complex mosaic of involuntary speech behaviors that reflect the underlying intricacies of Tourette syndrome. By broadening our understanding of coprolalia beyond mere crude vocalizations, we can develop a more compassionate perspective on those affected and address the societal misconceptions that often accompany this neurological condition.
Research Methodology
The investigation into coprolalia within Tourette syndrome employed a mixed-methods approach, integrating quantitative data from clinical assessments with qualitative insights from patient interviews. This comprehensive methodology aimed to capture both the prevalence and the subjective experiences of individuals affected by TS, particularly those with coprolalia.
Initially, a cohort of participants diagnosed with Tourette syndrome was recruited from various clinical settings. The inclusion criteria focused on individuals aged 8–25, ensuring a diverse representation of age and developmental stages. Participants underwent standardized tic assessments using validated rating scales such as the Yale Global Tic Severity Scale (YGTSS), which quantitatively measures tic severity and frequency. This instrument allowed for reliable comparisons across the cohort regarding the prevalence of coprolalia among those with TS.
In addition to the quantitative analysis, semi-structured interviews were conducted to collect qualitative data. These interviews were designed to elicit personal narratives about the participants’ experiences with coprolalia, the contexts in which it occurs, and its impact on their social interactions and mental health. The semi-structured format provided flexibility, enabling participants to expand on relevant themes, such as the emotional toll of experiencing coprolalia and the strategies employed to manage it in daily life.
Data were analyzed using thematic analysis for qualitative responses, allowing researchers to identify recurring themes and patterns in participants’ accounts. This approach highlighted commonalities in personal experiences, revealing insights into triggers, coping mechanisms, and social ramifications associated with coprolalia. Complementary statistical analyses were conducted on the quantitative data to discern patterns in tic frequency and severity across the cohort, with particular attention to how these variables relate to the occurrence of coprolalia.
Moreover, the study sought to include a broader demographic by collaborating with Tourette syndrome support organizations, which facilitated outreach and recruitment. Engaging with these communities not only enhanced the sample size but also ensured that a variety of perspectives and experiences with coprolalia were represented, reflecting the diversity of the TS community.
Throughout the data collection process, ethical considerations were prioritized, with informed consent obtained from all participants, as well as parental consent for minors. Confidentiality was maintained by anonymizing data and ensuring that personal identifiers were removed from published findings. The aim was to foster a respectful environment where participants felt safe to share their experiences, thus enriching the study outcomes.
This multifaceted research methodology highlights the complexity of coprolalia in the context of Tourette syndrome and aims to contribute to a more profound understanding of its manifestations and implications in the lives of those affected. By combining rigorous quantitative measures with rich qualitative accounts, the study strives to illuminate the nuanced reality behind coprolalia and the broader spectrum of tic disorders.
Main Findings
The analysis of coprolalia in Tourette syndrome revealed several crucial insights regarding its prevalence, triggers, and the associated emotional impact on individuals. Despite the stigma often surrounding coprolalia, the study found that its occurrence is relatively rare among TS patients, affecting only about 10% to 15% of the diagnosed population. This statistic underscores the importance of differentiating coprolalia from the broader spectrum of tic disorders associated with Tourette syndrome.
Moreover, participants frequently reported that coprolalia was not an isolated phenomenon but rather interconnected with other tics. For instance, many individuals experienced a combination of both vocal and motor tics. The quantitative analysis from the tic severity assessments indicated that those with coprolalia often had a higher overall tic frequency compared to their counterparts without it. This relationship suggests a potential link between the severity of Tourette syndrome symptoms and the likelihood of exhibiting coprolalia, warranting further investigation into the mechanisms that drive these associations.
A detailed examination of the qualitative data shed light on the triggers and contexts in which coprolalia occurs. Participants described various scenarios in which their symptoms worsened, including high-pressure social situations or moments of heightened anxiety. Many noted that their environment significantly influenced the frequency and content of coprolalic outbursts. For example, some individuals reported that being in a calm setting reduced their episodes, while chaotic environments tended to exacerbate their symptoms. This highlights the interplay between external stimuli and the internal neurological processes at play in individuals with TS.
The emotional ramifications of coprolalia were profound, with many participants expressing feelings of embarrassment, anxiety, and frustration. In interviews, individuals recounted instances where their outbursts unexpectedly occurred in public, leading to negative social interactions and increased self-consciousness. Consequently, this emotional toll extended not only to those who experience coprolalia but also affected family members and peers, thus amplifying the need for social support and comprehensive coping strategies.
Interestingly, while coprolalia is often perceived as an uncontrollable urge, some participants revealed they could, to a degree, manage their vocal tics. Strategies included focusing on deep breathing or identifying specific situational triggers to preemptively cope with potential outbursts. Such insights reveal that although certain aspects of coprolalia may be involuntary, awareness and self-regulation techniques can be beneficial in mitigating its impact.
Ultimately, this study emphasizes the necessity for a paradigm shift in understanding coprolalia within the context of Tourette syndrome. By viewing coprolalia not merely as an undesirable symptom but as part of a complex interaction of disorders, better support systems and treatment approaches can be developed to improve the quality of life for those affected. Enhanced educational efforts aimed at dispelling myths surrounding coprolalia will also contribute to reducing stigma and fostering a more inclusive environment for individuals with Tourette syndrome.
Implications for Treatment
Addressing coprolalia within the framework of Tourette syndrome necessitates a re-evaluation of current treatment strategies to better support individuals experiencing this symptom. Traditional approaches, which often focus on symptom suppression, may not adequately consider the emotional and social complexities involved. Therefore, a more holistic treatment paradigm that encompasses behavioral therapies, psychoeducation, and community support is essential.
Behavioral therapies, particularly habit reversal training (HRT) and cognitive-behavioral therapy (CBT), have shown promise in managing tics, including coprolalia. HRT involves teaching patients to recognize the onset of tic behavior and substituting a competing response that is physically inconspicuous. For instance, when a person feels the urge to vocalize an obscenity, they might be encouraged to take a deep breath or engage in an inconspicuous physical action instead. This proactive engagement helps individuals gain a sense of control over their symptoms, fostering empowerment and reducing distress caused by unexpected outbursts.
Incorporating elements of CBT can also be beneficial in addressing the anxiety and emotional fallout associated with coprolalia. Through CBT, individuals can explore their thoughts and feelings surrounding their symptoms, learn coping mechanisms, and develop positive self-affirmations to counteract negative self-perceptions that often arise from social stigma. Moreover, by providing a toolset for managing anxiety, CBT can mitigate triggers that exacerbate tic severity, creating a feedback loop of symptom reduction and improved self-esteem.
Psychoeducation plays a crucial role in treatment as well. It is vital for both patients and their families to understand the nature of Tourette syndrome and the idiosyncrasies of coprolalia. Educational programs can help destigmatize the disorder, enabling families to approach the symptoms with compassion and understanding. Furthermore, equipping families with the knowledge of how to respond during coprolalic outbursts can foster a supportive home environment, reducing feelings of isolation for the affected individuals.
Engaging community support networks, such as Tourette syndrome associations and local support groups, can provide valuable resources for both individuals and families. These networks can offer a platform for sharing experiences and coping strategies, as well as providing access to workshops led by mental health professionals specializing in TS. Building a sense of community can alleviate feelings of loneliness, reinforcing the notion that individuals with coprolalia are not alone in their experiences.
Collaboration with school systems is also pivotal for effective management of coprolalia in young individuals. Educating teachers and peers about Tourette syndrome can create a more inclusive educational environment. Schools can implement accommodations that allow for discreet breaks or provide a safe space where students can manage tics without fear of ridicule or misunderstanding. This approach not only benefits the individual with TS but can also cultivate empathy and awareness within the classroom.
Finally, ongoing research into pharmacological treatments for Tourette syndrome is essential. While medications such as haloperidol and esterase inhibitors have been traditionally used, there is a growing interest in newer agents that may more effectively target the neural pathways involved in coprolalia. Personalized medicine approaches that consider individual responses to medication could lead to more effective symptom control with fewer side effects.
Redefining the approach to treating coprolalia in Tourette syndrome involves a multi-faceted strategy that addresses the neurological, psychological, and social dimensions of the condition. By embracing a comprehensive treatment model, healthcare providers can significantly enhance the quality of life for those affected, fostering resilience and promoting a better understanding of the complexities surrounding coprolalia.