Clinical Presentation and Diagnosis
Functional Neurological Disorder (FND) can manifest through a variety of symptoms, one of which may be psychogenic non-epileptic seizures (PNES). These episodes can often mimic epileptic seizures, leading to diagnostic confusion. Patients typically present with sudden, involuntary movements or loss of consciousness that occur without the typical electrical interruptions seen in epilepsy. Characteristics peculiar to PNES include prolonged duration, variable intensity, and the presence of psychological stressors around the time of the episodes.
In cases where hemoptysis—coughing up blood—coexists with neurologic symptoms, the diagnostic process becomes particularly challenging. Recurrent hemoptysis in such scenarios may raise concerns for underlying organic causes like respiratory diseases or cardiovascular issues. Therefore, a thorough medical history is essential to understand the sequence of events, triggers, and accompanying symptoms. Specific details regarding the onset, frequency, and context of the seizures, alongside triggers that could include emotional stress or trauma, help healthcare providers differentiate PNES from other seizure disorders.
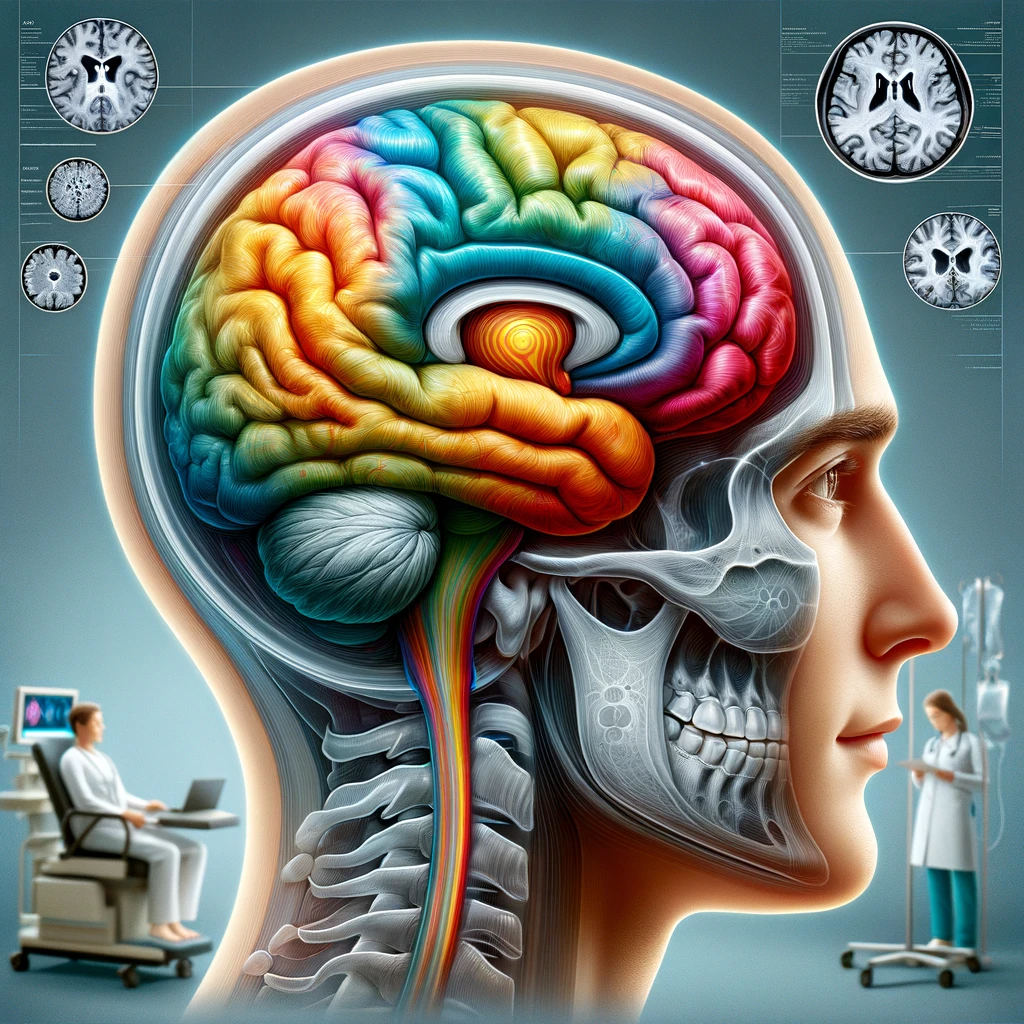
Diagnostic workup typically involves a comprehensive neurological evaluation, which may include an electroencephalogram (EEG) to rule out epilepsy. EEG results in PNES often show normal findings during seizure-like activity, while uncontrolled epilptic seizures would typically display abnormal electrical patterns. Additional investigations such as imaging studies (CT or MRI) may be employed to exclude structural brain anomalies or other organic diseases. Furthermore, multidisciplinary collaboration, including neurologists, psychiatrists, and other specialists, is vital to ensure a holistic understanding of the patient’s condition.
The clinical presentation of FND can sometimes include non-specific symptoms such as fatigue, cognitive difficulties, or changes in mood, complicating the diagnostic picture further. Patients often experience significant distress due to the unpredictable nature of their symptoms, which can affect their daily functioning and lead to social withdrawal. Understanding these multifaceted presentations is crucial in forming an appropriate treatment plan, as the psychological factors often intertwine with the physical manifestations of the disorder. Engaging in a shared decision-making process with the patient facilitates better outcomes, as patients become more active participants in managing their condition.
Pathophysiology and Mechanisms
Functional Neurological Disorder (FND), particularly when related to psychogenic non-epileptic seizures (PNES), presents a complex interplay of neurobiological, psychological, and environmental factors. The precise pathophysiological mechanisms underlying FND remain an area of active investigation, with several theories proposed to elucidate how psychological stressors can translate into physical symptoms without a discernible organic cause.
One prominent hypothesis suggests that psychological factors, such as stress or trauma, lead to dysregulation in brain networks responsible for motor control and body awareness. Neuroimaging studies have revealed that individuals with FND often exhibit altered activation patterns in brain regions associated with emotional regulation and motor function. For example, areas such as the insula and anterior cingulate cortex, which play crucial roles in integrating sensory and emotional information, may show atypical activity during episodes of PNES. This dysregulation might manifest as seizures or abnormal movements in response to psychological distress, reflecting a somatic expression of underlying feelings and experiences.
Another perspective on the pathophysiology of FND emphasizes the role of learned behaviors. Patients may inadvertently learn to associate particular stressors or emotions with seizure-like events, reinforcing a cycle where psychological triggers elicit physical responses. This learning can be conceptualized as a form of conditioning, whereby prior experiences shape the way the nervous system reacts to similar contexts in the future.
Additionally, neurobiological models have suggested that disruptions in the brain’s information processing pathways could be involved. Such disruptions might occur because of impairments in the integration of sensory inputs, resulting in a mismatch between external stimuli and internal perceptions. This mismatch can lead to a physical manifestation of distress that takes the form of non-epileptic seizures, as the brain attempts to communicate discomfort or conflict in a somatic way.
There is also a growing recognition of the biopsychosocial model in understanding the mechanisms of FND. This model posits that biological vulnerabilities (such as genetic predispositions), psychological factors (like cognitive distortions or personality traits), and sociocultural influences (including support systems or adverse life events) collectively shape the symptomatology of FND. The interaction of these factors can create a fertile ground for the emergence of symptoms such as PNES, where psychological stressors trigger neurologically driven responses.
Overall, the pathophysiology of FND is multifaceted, with diverse theories complementing one another to provide a more detailed understanding of how psychological and neurological processes interact. By appreciating the complexity of these mechanisms, clinicians can better approach diagnosis and treatment, recognizing that addressing both psychological and physiological aspects is essential for effective management of patients presenting with FND and PNES. Continued research into these pathways will hopefully yield more insights, paving the way for targeted interventions that can alleviate the burden of this disorder.
Management Strategies
Management of Functional Neurological Disorder (FND), particularly when it presents as psychogenic non-epileptic seizures (PNES) alongside symptoms such as recurrent hemoptysis, requires a multifaceted approach tailored to address both the neurological and psychological components of the disorder.
A crucial first step in management is educating patients about FND and PNES. Understanding that these conditions are rooted in the interplay between mind and body can help reduce stigma and anxiety surrounding the symptoms. Informing patients about the benign nature of PNES and emphasizing that their experiences are valid can often lead to improved patient engagement in treatment. This educational component should also extend to family members, fostering a supportive environment that reinforces a positive therapeutic outcome.
Psychotherapy stands as one of the cornerstones of treatment for patients with PNES. Cognitive Behavioral Therapy (CBT) is particularly effective, as it aids patients in recognizing and modifying unhelpful thought patterns and behaviors that may contribute to symptom exacerbation. For those who have experienced trauma, trauma-focused therapies such as Eye Movement Desensitization and Reprocessing (EMDR) may be beneficial. These therapeutic approaches should aim not only to alleviate symptoms but also to enhance coping strategies for managing stressors.
In addition to psychotherapy, physical rehabilitation can play a significant role in the management of FND. Physiotherapy, including exercises focused on motor control and coordination, can help restore motor function and improve overall physical health. Occupational therapy may also be essential in facilitating the patient’s reintegration into daily activities, enhancing their ability to manage tasks that may have become challenging due to their symptoms.
Pharmacological interventions may be considered in some cases, particularly when associated psychiatric disorders—such as anxiety or depression—are present. Selective Serotonin Reuptake Inhibitors (SSRIs) or other suitable medications can support mood stabilization while psychotherapy is concurrently employed. However, the focus should remain primarily on non-pharmacological methods due to the nature of the disorder and the potential complications arising from the use of antiepileptic medications, which are not indicated for PNES.
Multidisciplinary care is essential in managing patients effectively. Collaboration among neurologists, psychiatrists, psychologists, and physical therapists ensures a comprehensive treatment plan that addresses the various facets of the disorder. Regular meetings among specialists can enhance coordination of care and facilitate the sharing of insights about the patient’s progress, ensuring adjustments can be made as needed.
For patients experiencing recurrent hemoptysis, a thorough interdisciplinary approach will also involve pulmonologists or other specialists to investigate and address potential organic causes of hemoptysis. Appropriate management of any underlying respiratory issues should occur alongside the psychological treatment, as unresolved medical concerns can exacerbate neurological symptoms.
Finally, ongoing monitoring and follow-up are vital components of effective management. Regular check-ins allow healthcare providers to assess symptom progression and treatment efficacy, making it possible to modify intervention strategies as needed. Additionally, support groups can provide an invaluable resource for patients, enabling them to connect with others facing similar challenges, share coping strategies, and foster a sense of community.
In summary, effective management of FND and PNES involves a combination of patient education, psychotherapeutic approaches, physical rehabilitation, and collaborative multidisciplinary care. Addressing the biological, psychological, and social aspects of the disorder not only targets symptom relief but also promotes long-term recovery and improved quality of life for affected individuals.
Future Research Directions
Research into Functional Neurological Disorder (FND), particularly concerning its manifestation as psychogenic non-epileptic seizures (PNES), is rapidly evolving, and several key areas warrant further investigation to enhance understanding, diagnosis, and treatment of this complex condition.
One pivotal area for future exploration is the biomarker identification for PNES. Currently, the absence of objective diagnostic tests poses significant challenges in differentiating PNES from epilepsy and other neurological disorders. Research aimed at discovering blood markers or neuroimaging cues that could indicate dysfunctional neural pathways or psychological stress responses would be invaluable. Advancements in functional neuroimaging techniques, such as resting-state fMRI or PET scans, may yield insights into the specific neural networks involved in FND, potentially leading to more accurate diagnoses and targeted therapies.
Another promising avenue is the investigation of the psychosocial factors contributing to the onset and persistence of FND symptoms. Longitudinal studies that explore the relationship between stress, trauma exposure, and symptom development could provide insight into preventive measures and interventions. Furthermore, understanding the role of cognitive distortions or maladaptive behaviors in perpetuating these disorders can inform therapeutic approaches, tailoring specific psychotherapies such as CBT or acceptance and commitment therapy (ACT) to address these issues.
Exploration into the effectiveness of various treatment modalities also remains crucial. While existing evidence supports the utility of cognitive behavioral therapy and physical rehabilitation, more robust clinical trials are necessary to evaluate the comparative efficacy of different therapeutic avenues, including innovative interventions like virtual reality therapy and mindfulness-based strategies. These treatments could address both psychological and physical functions, potentially leading to improved patient outcomes.
Equally important is the need for increased awareness and education regarding FND among healthcare providers. Research efforts aimed at understanding gaps in knowledge and attitudes toward FND among neurologists, psychiatrists, and primary care doctors could shape educational initiatives that improve early recognition and intervention. Continued efforts in this realm may reduce the stigmatization and mismanagement of patients, facilitating quicker paths to effective treatment.
Finally, the exploration of technology integration in managing FND is gaining traction. The use of mobile health (mHealth) applications for self-tracking symptoms, mood, and triggers could empower patients to take an active role in their care. Research could focus on developing these tools to ensure they are user-friendly and effective in conjunction with conventional therapies, promoting self-management alongside professional support.
In summary, the future of FND research is poised for substantial advancements across various domains, including biomarker discovery, psychosocial factor analysis, treatment evaluation, provider education, and technology integration. By addressing these areas, the field can move toward more precise diagnostics, effective interventions, and ultimately, improved quality of life for individuals affected by FND and PNES.