Understanding Functional Neurological Disorder
Functional Neurological Disorder (FND) represents a complex and multifaceted group of disorders characterized by neurological symptoms that cannot be attributed to a recognized medical or neurological condition. These symptoms may manifest as seizures, tremors, abnormal gait, or even episodes of paralysis, leading to significant impairment in daily functioning. The condition arises from a disruption in the brain’s functioning rather than physical damage to the nervous system. As a result, it often poses diagnostic challenges, particularly as it may present similarly to more conventional neurological disorders.
Research indicates that FND is prevalent among individuals who seek neurological care, yet it often remains underdiagnosed or misdiagnosed. The mechanisms underlying FND are intricate and can involve various factors, including psychological stressors, previous trauma, or neurological maladaptive responses. In essence, these disorders can arise when the brain struggles to communicate effectively with the body, leading to symptoms that are real but not due to a traditional neurological pathophysiology.
Understanding how to identify and categorize FND is vital because it encompasses a range of disorders that present differently in each individual. Symptoms can vary in severity and frequency, and the impacts on quality of life can be profound. For many patients, these symptoms not only affect physical health but also contribute to psychological distress, including anxiety and depression. Studies indicate that a significant portion of individuals with FND have comorbid psychiatric conditions, which can complicate both diagnosis and treatment.
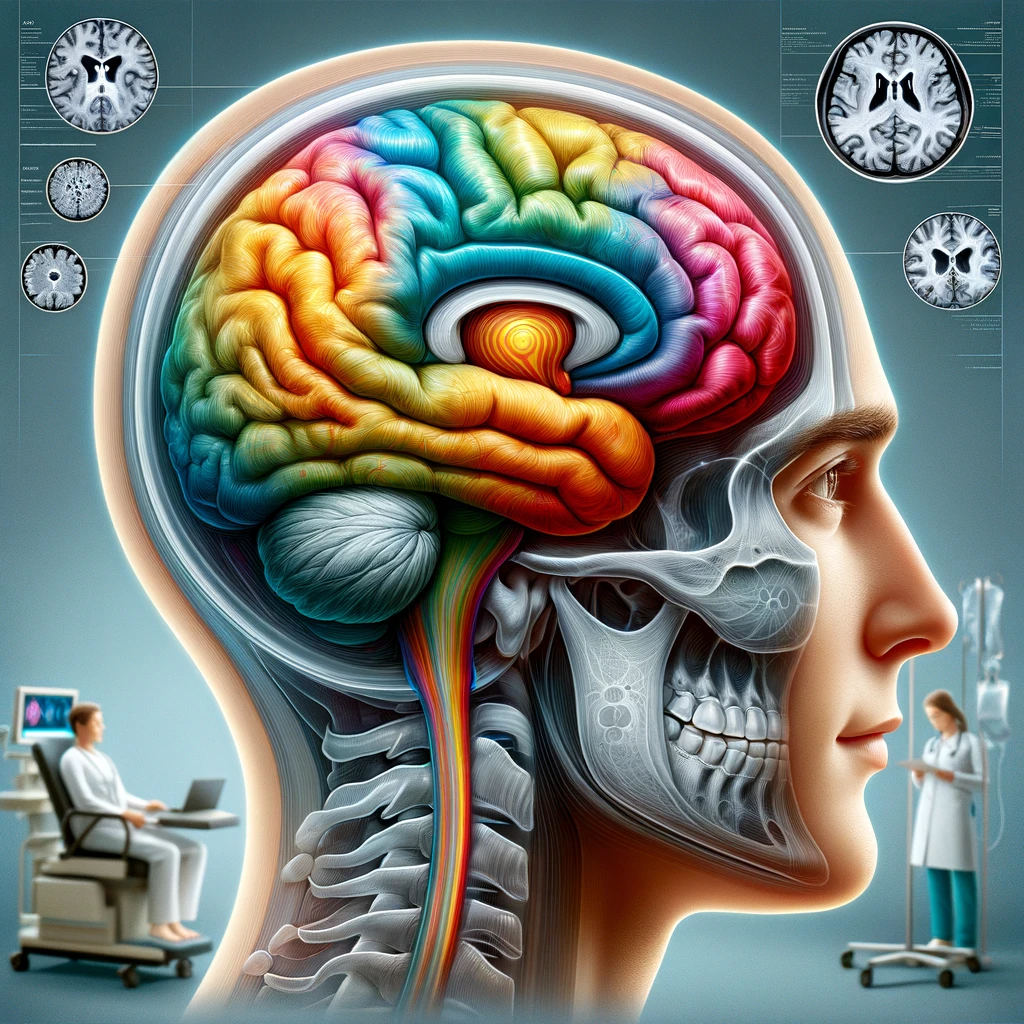
The diagnosis of FND is based primarily on clinical assessment and the identification of characteristic patterns in the symptoms presented. There is often an emphasis on the patient’s history during examination, as this can reveal important context about the onset of the disorder. Neuroscientific research has begun to illuminate the underlying brain mechanisms associated with FND; neuroimaging studies often show functional abnormalities in brain areas that govern the regulation of movement and bodily awareness.
Table 1 below summarizes key features of Functional Neurological Disorder as related to diagnostic considerations:
| Feature | Description |
|---|---|
| Symptoms | Varied, including seizures, motor dysfunction, and sensory disturbances. |
| Pathophysiology | Disruption in brain function rather than structural damage. |
| Comorbidities | Often associated with anxiety, depression, or histories of trauma. |
| Diagnosis | Clinical assessment with emphasis on symptom history; neuroimaging can support findings. |
Understanding Functional Neurological Disorder is crucial for both practitioners and patients. This understanding helps facilitate accurate diagnoses and tailor effective treatment strategies, ultimately improving outcomes for those navigating the complexities of this condition.
Diagnostic Criteria and Challenges
Diagnosing Functional Neurological Disorder (FND) poses significant challenges for healthcare professionals due to its non-specific symptoms and the overlap with various neurological and psychiatric conditions. The lack of identifiable organic pathology further complicates the diagnostic process. Diagnosis is primarily clinical, relying on established criteria and an in-depth understanding of the patient’s history and symptoms.
The diagnosis of FND is guided by the criteria set forth in the DSM-5 (Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition) and other standardized frameworks. Key features include:
- A presence of symptoms consistent with neurological dysfunction.
- Evidence that the symptoms are not explained by a recognized neurological or medical condition.
- Symptoms that cause significant distress or impairment in personal, social, or occupational functioning.
- Suggestive historical or contextual factors that may trigger or exacerbate symptoms.
Despite these guidelines, practitioners often find it difficult to arrive at an accurate diagnosis. The subjective nature of many symptoms, the prevailing stigma surrounding mental health and neurological disorders, and the tendency for patients to present with atypical manifestations contribute to this complexity. Furthermore, neurologists frequently report feeling pressured to identify a definitive physiological cause, leading to misdiagnosis or delayed diagnosis.
Table 2 provides a comparison of common symptoms associated with FND and those seen in typical neurological disorders, highlighting the diagnostic complexities:
| Symptom | FND Characteristics | Neurological Conditions |
|---|---|---|
| Seizures | Non-epileptic; often linked to stress or psychological triggers. | Epileptic; characterized by abnormal electrical activity in the brain. |
| Tremors | Variable during observation; can be inconsistent when a patient is distracted. | Consistent tremors; linked to identifiable neurological conditions like Parkinson’s disease. |
| Paralysis | May vary with context; patients often show movement upon distraction. | Stabilized paralysis due to structural damage or identified neurological conditions. |
| Sensory disturbances | Unpredictable and non-anatomical; not following typical patterns. | Defined sensory changes associated with specific nerve pathways or lesions. |
In addition, a patient’s medical history plays a crucial role in the diagnostic process. Conditions like anxiety, depression, or a history of trauma are often prevalent among those with FND, which can obscure the clinical picture. This intertwining of psychological and neurological factors necessitates a collaborative approach to diagnosis, often involving neurologists, psychologists, and other specialists who can evaluate all dimensions of a patient’s symptoms.
Advanced imaging techniques, such as functional MRI (fMRI) and PET scans, can sometimes provide supporting evidence by illustrating abnormalities in brain function. However, it’s essential to understand that these techniques do not provide a definitive diagnosis for FND, given the lack of organic pathology typically visible on structural imaging like CT or standard MRI scans.
Ultimately, navigating the diagnostic landscape of FND requires a nuanced understanding of its multifaceted nature. Clinicians must balance clinical experience, empirical evidence, and patient-specific factors to arrive at a diagnosis, which is vital to ensuring effective management and treatment pathways for individuals experiencing these complex disorders.
Case Presentation and Analysis
In this case, we present a 32-year-old female patient who was referred to our neurology clinic after experiencing recurrent episodes of hemoptysis accompanied by psychogenic non-epileptic seizures (PNES). The patient had a significant medical history, including episodes of heightened stress and anxiety due to personal circumstances, which she reported as a trigger for her symptoms.
Upon initial evaluation, the patient described her hemoptysis episodes as being sudden and unpredictable. During these episodes, she produced small amounts of blood-tinged sputum without any associated signs of infection or respiratory distress. Concurrently, she experienced episodes of involuntary movements resembling seizures that were not associated with the electrical abnormalities typically seen on EEG monitoring. These PNES episodes were characterized by a lack of postictal confusion, which is commonly observed in epileptic seizures, further suggesting their psychogenic origin.
As part of her diagnostic workup, the patient underwent comprehensive laboratory tests, pulmonary function tests, and imaging studies, including a high-resolution computed tomography (HRCT) scan of the chest, which ruled out significant pulmonary pathology. Her brain MRI showed no structural abnormalities, reinforcing the diagnosis of FND. Throughout this process, the patient expressed a growing sense of frustration and despair over her unpredictable symptoms, which compounded her anxiety and affected her overall quality of life.
Analysis of her case reveals the intricate interplay between her psychological state and the manifestation of physical symptoms. The timing of her hemoptysis and seizure-like episodes correlated with periods of increased emotional stress, further indicating a potential psychosomatic relationship. This aspect is crucial, as it underscores the importance of considering psychological factors when treating individuals presenting with complex syndromes involving both neurological and somatic complaints.
Table 3 summarizes the clinical features observed in this patient:
| Feature | Detail |
|---|---|
| Age | 32 years |
| Physical Symptoms | Recurrent hemoptysis, psychogenic non-epileptic seizures |
| Triggers | Increased stress and anxiety |
| Diagnostic Findings | No significant findings on MRI or HRCT; normal laboratory results |
| Psychological History | History of anxiety related to personal circumstances |
This case highlights the difficulty in delineating between functional disorders and organic pathology, as well as the need for a holistic approach that integrates neurological assessment with psychological evaluation. It is imperative to address the psychological comorbidities in patients like ours to mitigate symptom severity and improve overall outcomes. Further multidisciplinary management, including psychotherapy, may be indicated as part of her treatment strategy moving forward.
In exploring the complexities of FND as presented in this case, it is evident that a comprehensive understanding of both physical and psychological dimensions is crucial in providing effective care. This approach not only helps in formulating an accurate diagnosis but also in tailoring specific therapeutic interventions aimed at reducing functional impairments and enhancing the patient’s quality of life.
Treatment Approaches and Outcomes
The management of Functional Neurological Disorder (FND), particularly in cases presenting with psychogenic non-epileptic seizures (PNES) and recurrent hemoptysis, demands a multifaceted approach that integrates both neurological and psychological treatment modalities. Effective treatment is contingent upon a thorough understanding of the individual patient’s symptomatology, triggers, and associated psychological factors.
Initial management may involve educational interventions aimed at addressing misconceptions about the disorder. Educating patients about FND helps to demystify their experiences, reducing stigma and promoting a collaborative mindset towards managing symptoms. Providing reassurance that their symptoms have a legitimate basis in brain function rather than structural pathology is essential. This psychoeducation forms the groundwork for subsequent therapeutic strategies.
Therapeutic options for FND focus primarily on cognitive-behavioral strategies, aimed at addressing the underlying psychological components of the disorder. Cognitive Behavioral Therapy (CBT) is one of the most widely used psychological treatments. It assists patients in recognizing and modifying maladaptive thought patterns that may exacerbate symptoms. CBT can also enhance coping strategies, enabling individuals to manage stress more effectively and reduce the frequency and severity of episodes.
Physical therapy and occupational therapy may play crucial roles in managing the motor symptoms often associated with FND. In particular, a specialist physical therapist can work with patients to develop tailored movement and muscle activation strategies to regain voluntary control over their movements, which may be impaired during episodes of PNES. This physical reconditioning can facilitate both physical recovery and a greater sense of agency for the patient.
In cases where symptoms correspond closely with psychological distress, the incorporation of psychiatrist involvement may be beneficial. Pharmacotherapy may be indicated, particularly if the patient presents with co-morbid conditions such as anxiety or depression. Selective serotonin reuptake inhibitors (SSRIs) or other anxiolytics may aid in alleviating these symptoms, contributing indirectly to the management of FND. However, it is crucial to approach medication with careful consideration, as responses can vary significantly among patients.
In the context of our case, where recurrent hemoptysis and PNES co-exist, treatment may also necessitate a collaborative service model that includes pulmonologists if pulmonary symptoms persist. Despite the absence of significant findings on imaging, further evaluation to rule out other pulmonary causes of hemoptysis is still advisable, integrating a biopsychosocial approach to treatment. Regular follow-ups can help track the evolution of symptoms and responses to various modalities, allowing for ongoing adjustments to the treatment plan.
Table 4 below summarizes potential treatment modalities and their target outcomes:
| Treatment Modality | Focus Area | Expected Outcome |
|---|---|---|
| Psychoeducation | Understanding FND; addressing stigma | Improved patient insight and cooperation |
| Cognitive Behavioral Therapy (CBT) | Modify maladaptive thoughts; build coping strategies | Reduced anxiety; fewer episodes |
| Physical Therapy | Develop movement strategies; regain motor control | Improved physical function; greater autonomy |
| Medication (SSRIs, anxiolytics) | Manage co-morbid psychiatric symptoms | Alleviation of anxiety/depression; indirect symptom relief |
Holistic management strategies that address both the psychological and neurological aspects of FND ensure that treatment is not only effective in alleviating symptoms but also in improving overall quality of life. A supportive environment, a patient-centered approach, and a willingness to adapt treatment plans dynamically based on patient feedback and symptom evolution are integral to successful outcomes. By approaching FND comprehensively, we can significantly enhance recovery trajectories and the overall well-being of individuals affected by such complex disorders.