Study Overview
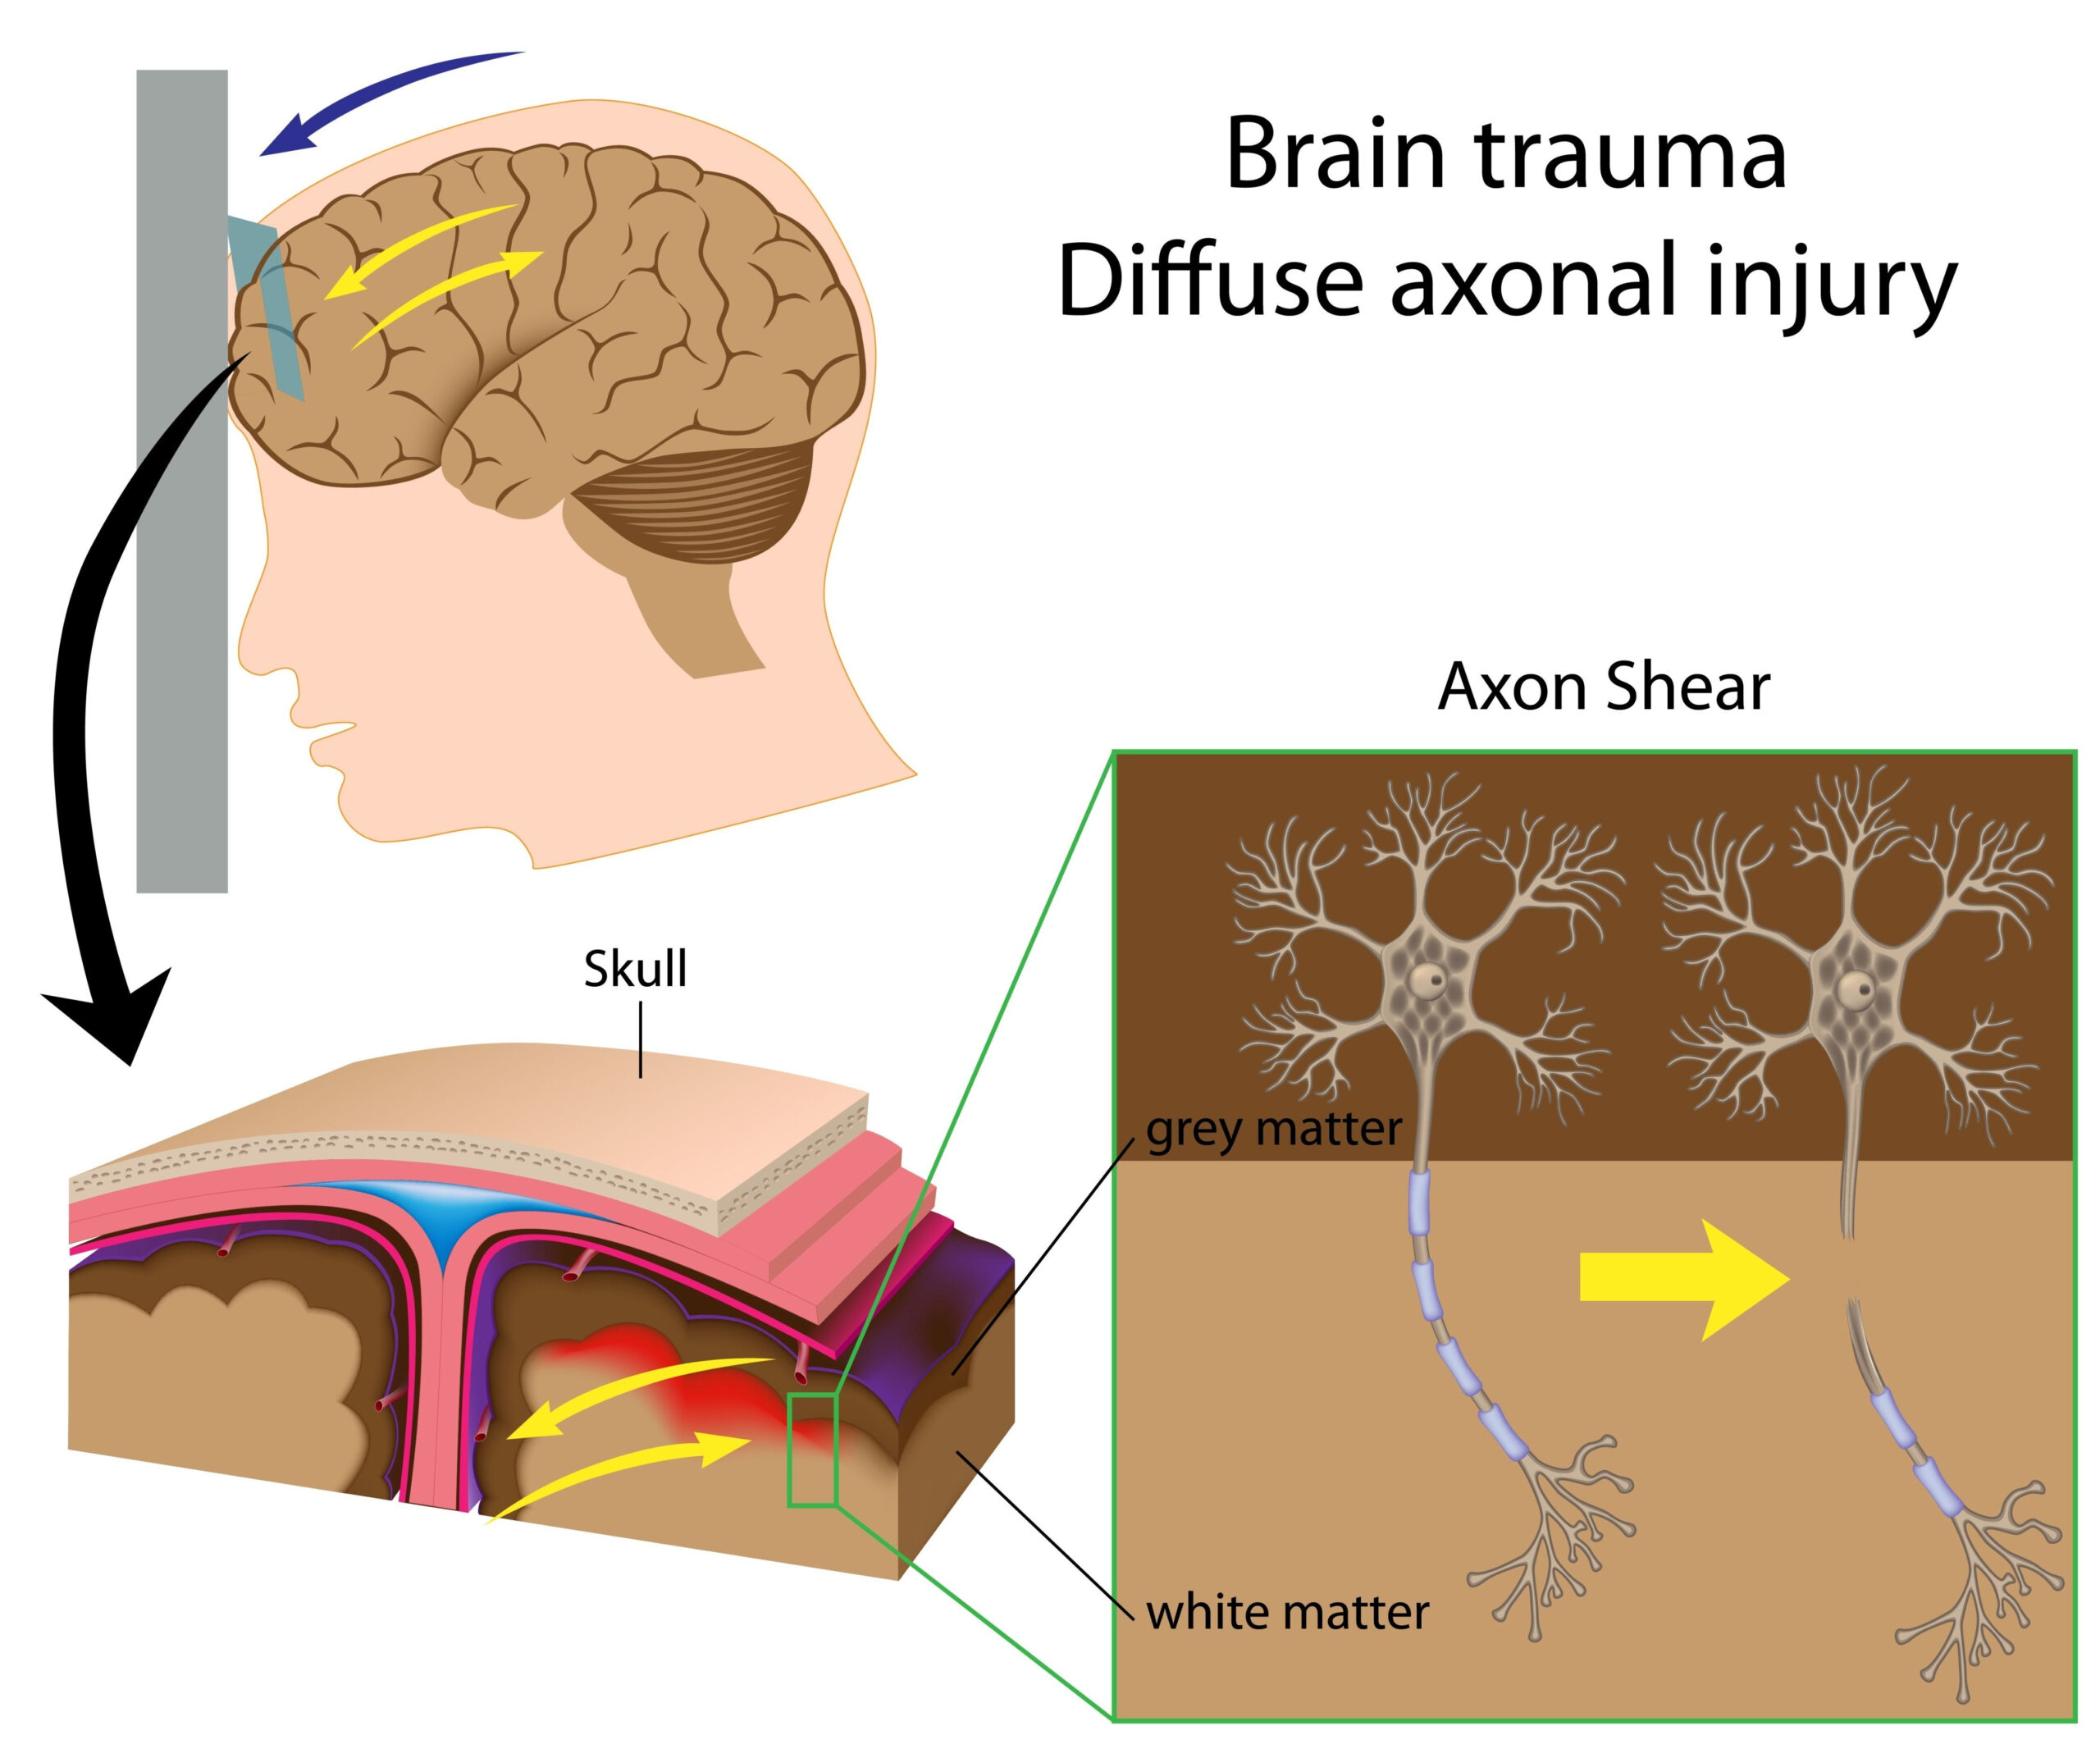
The investigation centered on the potential link between acute levels of glial fibrillary acidic protein (GFAP) and cognitive performance six months following a mild traumatic brain injury (mTBI). This exploratory study aimed to deepen the understanding of how GFAP, a protein that indicates glial cell activation in response to central nervous system injury, may serve as a biomarker for cognitive outcomes in individuals recovering from mTBI.
Researchers recruited a cohort of participants diagnosed with mTBI, focusing on their GFAP levels shortly after the injury occurred. The primary aim was to assess whether these initial GFAP levels could predict future cognitive performance measured at a six-month follow-up. The rationale behind this inquiry stemmed from prior research suggesting that elevated GFAP levels correlate with brain injury severity and functional impairment.
The study was designed to control for various confounding factors, including age, sex, and pre-existing conditions that might also influence cognitive recovery. Participants underwent a thorough assessment of their cognitive abilities at the six-month mark, employing standardized neuropsychological tests to evaluate aspects such as memory, attention, and executive function. This comprehensive approach aimed to establish a clearer picture of how acute GFAP status might interplay with cognitive trajectories post-injury.
By following subjects over an extended period, the researchers aimed to provide insights not only into immediate recovery patterns but also into longer-term implications of mTBI on cognitive health. Understanding the relationship between GFAP levels and cognitive outcomes may pave the way for targeted interventions and improved management strategies for individuals recovering from traumatic brain injuries.
Methodology
The study utilized a longitudinal design, incorporating a well-defined sampling strategy to gather data from individuals aged 18 to 65 who had sustained a mild traumatic brain injury within the previous week. A total of 100 participants were enrolled through referrals from emergency departments and outpatient clinics specializing in trauma care. Each participant was screened for eligibility based on a series of inclusion criteria, which included a confirmed diagnosis of mTBI, the absence of pre-existing neurological disorders, and the absence of severe psychological conditions that might interfere with cognitive assessment.
Upon enrollment, participants provided informed consent and underwent an initial evaluation that included a detailed medical history and demographic data collection. Critical to the study was the assessment of GFAP levels, which were measured from blood samples taken within 72 hours of the injury. These samples were processed using enzyme-linked immunosorbent assay (ELISA) techniques, ensuring the accuracy and reliability of GFAP quantity measurement.
Participants were then tracked over a six-month period, during which they received scheduled follow-up appointments. At the six-month mark, neuropsychological testing was conducted to evaluate cognitive performance. A battery of standardized assessments was employed, targeting various cognitive domains such as working memory, verbal and visual memory, attention, processing speed, and executive functions. Notable tests included the Wechsler Adult Intelligence Scale (WAIS-IV), the Rey Auditory Verbal Learning Test (RAVLT), and the Wisconsin Card Sorting Test (WCST).
To analyze the data, researchers implemented statistical methods that accounted for potential confounding variables. Multiple regression analyses were performed to evaluate the relationship between acute GFAP levels and cognitive outcomes while controlling for factors like age, sex, education level, and initial injury severity, measured by the Glasgow Coma Scale (GCS). This multifaceted approach provided a robust framework for evaluating whether GFAP could serve as a predictive biomarker for cognitive performance after mTBI.
Additionally, participants’ progress was monitored through self-reported measures of quality of life and subjective cognitive difficulties, utilizing established questionnaires such as the Quality of Life after Brain Injury (QOLIBRI) scale and the Cognitive Failures Questionnaire (CFQ). By integrating both objective cognitive testing and subjective reporting, the study aimed to gather a comprehensive view of cognitive recovery dynamics in this population.
Ethical clearance was granted by the institutional review board, ensuring adherence to ethical standards throughout the research process. The emphasis on participant safety and informed consent underscored the study’s commitment to conducting responsible and ethically sound research in the field of brain injury and cognitive health.
Key Findings
The findings of this exploratory study underscore the complex relationship between early GFAP levels and cognitive outcomes observed six months post-mTBI. Analysis revealed a statistically significant correlation between elevated GFAP levels shortly after the injury and poorer performance on cognitive assessments at the follow-up. Notably, participants with higher GFAP concentrations exhibited decreased scores in key cognitive domains such as memory, attention, and executive function, suggesting that greater glial activation is a potential indicator of prolonged cognitive impairment.
The study’s results highlighted that for every unit increase in acute GFAP levels, there was an associated decline in cognitive performance measured by the composite score derived from the neuropsychological tests conducted. This relationship remained robust even after adjusting for confounding factors such as age, sex, educational background, and baseline injury severity, as defined by the Glasgow Coma Scale. Furthermore, the data indicated that individuals with elevated GFAP were significantly more likely to report difficulties in daily cognitive functioning as reflected in their responses to the Cognitive Failures Questionnaire.
Interestingly, the association between GFAP levels and cognitive performance varied across different cognitive domains. For instance, working memory and processing speed appeared particularly sensitive to fluctuations in GFAP levels. Participants who scored in the lower percentiles on the Wechsler Adult Intelligence Scale (WAIS-IV) also tended to have higher GFAP levels, reinforcing the notion that acute glial responses may hinder recovery trajectories in cognitive functions that rely heavily on these capabilities.
In terms of self-reported quality of life, correlations with GFAP levels echoed the objective findings. Survey responses from the Quality of Life after Brain Injury (QOLIBRI) scale revealed that individuals with elevated GFAP levels not only struggled cognitively but also reported a diminished sense of well-being and quality of life. These findings indicate that the effects of mTBI may extend beyond measurable cognitive impairments, influencing participants’ overall life satisfaction and perceived cognitive difficulties.
Moreover, subgroup analysis suggested that demographic factors, including age and sex, may modulate the relationship between GFAP levels and cognitive outcomes; however, these interactions warrant further exploration in future research. The broader implication of these findings is that GFAP may not only serve as a biomarker for acute injury assessment but could also provide valuable insights into long-term cognitive recovery predictions following mild traumatic brain injuries.
Overall, this study elucidates the significant role that acute GFAP levels may play in shaping cognitive trajectories post-injury, which could inform clinical practice and the development of personalized rehabilitation strategies aimed at optimizing cognitive recovery in individuals affected by mTBI.
Clinical Implications
The implications of the findings from this study are profound for both clinicians and patients dealing with the aftermath of mild traumatic brain injuries (mTBI). As the research indicates, acute levels of GFAP can serve as a significant biomarker for predicting cognitive recovery over the months following an mTBI. This insight allows for a more nuanced understanding of both immediate and long-term care strategies for individuals affected by brain injuries.
One of the primary concerns following mTBI is the risk of chronic cognitive impairment, which can severely impact daily functioning and quality of life. The correlation between elevated GFAP levels and poorer cognitive performance suggests that monitoring GFAP could offer clinicians valuable information about a patient’s recovery trajectory from the onset. Early identification of individuals at higher risk for cognitive decline could facilitate timely intervention measures, such as cognitive rehabilitation programs aimed at improving memory, attention, and executive functioning.
In practice, clinicians may consider implementing routine GFAP testing as part of the standard evaluation protocol for patients who have sustained an mTBI. Such measures could enhance the ability to tailor rehabilitation strategies according to individual needs, potentially minimizing the risk of prolonged cognitive difficulties. For example, those with high GFAP levels might benefit from more intensive cognitive training and monitoring, whereas those with lower GFAP levels could engage in standard recovery protocols with less intensive oversight.
Moreover, these findings underscore the importance of a multidisciplinary approach in managing mTBI recovery. The incorporation of neuropsychologists, occupational therapists, and rehabilitation specialists into the care team can ensure that patients receive comprehensive services catered to their specific cognitive challenges. This collaboration not only fosters a holistic view of recovery but also aids in addressing the emotional and psychological aspects associated with cognitive impairments following mTBI.
Additionally, the impact of these results extends to patient education. Understanding that GFAP levels can predict cognitive outcomes empowers patients with knowledge about their condition and recovery process. This awareness may also encourage patients to comply with rehabilitation protocols and actively participate in their healing journey, knowing that their efforts can lead to improved cognitive function and overall quality of life.
Further, the association found between GFAP levels and self-reported quality of life emphasizes the need for ongoing support systems for individuals recovering from mTBI. Clinicians should be vigilant not only about cognitive assessments but also about the emotional and psychological well-being of their patients. Providing resources that support mental health, such as counseling services and community support groups, can help enhance resilience and coping strategies, ultimately fostering a better overall recovery.
In conclusion, the potential utility of GFAP as a predictive biomarker for cognitive outcomes offers novel pathways for clinical practice and research alike. Future studies should aim to refine the understanding of how GFAP levels can inform interventions and address the complex recovery challenges faced by individuals with mTBI, paving the way for personalized and effective care strategies in this vulnerable population.