Clinical Presentation and Background
The patient discussed in this case report presented with psychogenic nonepileptic seizures (PNES) as a complication of post-traumatic stress disorder (PTSD). This individual had a significant history of trauma, which is not uncommon among individuals diagnosed with PTSD, suggesting a strong correlation between psychological stressors and the onset of seizure-like episodes that do not have a neurological origin. The episodes were characterized by characteristics that can often mimic epileptic seizures but lacked typical EEG findings associated with true epilepsy.
The clinical profile of the patient included a range of emotional and psychological symptoms consistent with PTSD, alongside a history of dissociative episodes. Such episodes can manifest as sudden lapses in cognitive function or awareness, often triggered by environmental stressors reminiscent of the original trauma. The patient’s medical history was notably devoid of any significant neurological conditions, ruling out underlying causes for the seizures.
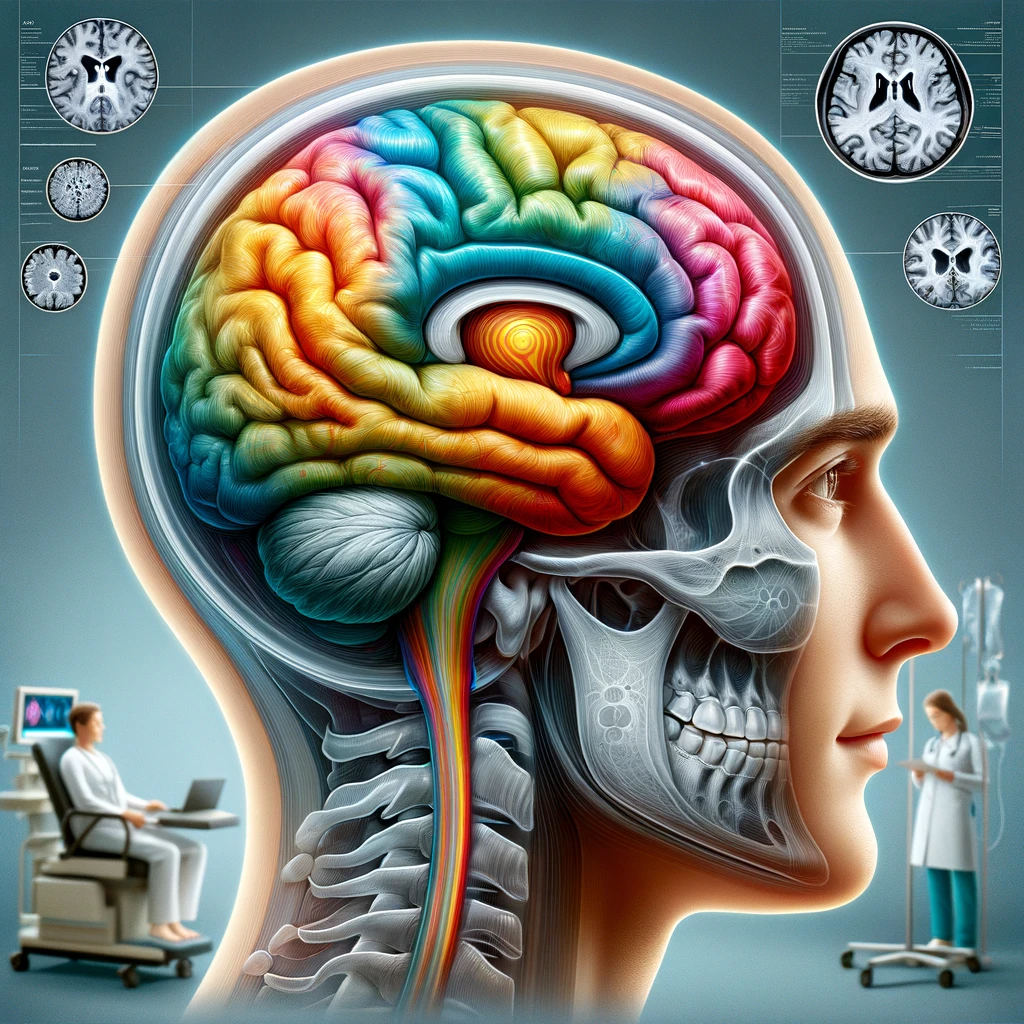
It is important to note that the pathophysiology of PNES consists not merely of psychological crises but involves complex interactions between emotional dysregulation and bodily responses. The sympathetic nervous system, which governs the body’s fight-or-flight response, plays a crucial role. In patients suffering from PTSD, alterations in sympathetic nervous system regulation can lead to heightened reactivity and paradoxical somatic responses, often presenting as seizure-like states during stress.
| Clinical Features | Description |
|---|---|
| Seizure Characteristics | Episodes resembling seizures without EEG changes |
| History | Significant trauma leading to PTSD |
| Associated Symptoms | Dissociative episodes, emotional dysregulation |
| Neurological Assessment | No underlying neurological disorders identified |
This case emphasizes the need for a more comprehensive understanding of the interplay between psychological distress and physiological responses in patients experiencing PNES. Given the growing recognition of the impact of trauma on bodily function, interventions targeting the sympathetic nervous system may provide new avenues for treatment.
Intervention Details
The intervention employed in this case involved a cervical sympathetic blockade, a procedure aimed at interrupting sympathetic nerve pathways, thereby alleviating the neurophysiological symptoms associated with the patient’s post-traumatic stress disorder (PTSD) and psychogenic nonepileptic seizures (PNES). The rationale behind this approach is that by modulating the sympathetic nervous system, it may be possible to reduce the heightened reactivity that contributes to the seizure-like episodes observed in patients with PTSD.
The cervical sympathetic blockade was performed under fluoroscopic guidance to ensure precision and minimize potential complications. The technique entails the injection of anesthetic agents—typically a local anesthetic combined with a steroid—into the sympathetic chain located in the cervical region, specifically at the C6-C7 vertebrae level. This anatomical target is crucial as it is responsible for the sympathetic innervation of the head, neck, and upper body, regions that can exhibit exaggerated responses during episodes of stress.
The patient underwent the procedure after being extensively evaluated for any contraindications, including anatomical variations or bleeding disorders. Consent was obtained following a thorough discussion of potential risks and expected outcomes, which included a temporary relief from sympathetic overactivity that might influence the frequency and severity of PNES episodes.
The outcome parameters for assessing the effectiveness of the cervical sympathetic blockade included the frequency of seizures, the intensity of reported anxiety and stress levels, as well as the overall quality of life as assessed by patient-reported outcome measures. Follow-up appointments were scheduled systematically to monitor the patient’s response to the intervention, with particular attention paid to any changes in the pattern of seizure-like activity and psychological well-being.
Through this intervention, the hope was to not only address the immediate symptomatology associated with the PNES but also to provide the patient with a broader therapeutic framework for managing PTSD. Given the emerging focus on the interaction between mind and body in traumatic stress, the cervical sympathetic blockade represents a novel intersection of neurological intervention and psychological healing.
This approach is rooted in the broader understanding that effective treatment for PTSD and associated conditions like PNES necessitates a multi-faceted strategy that includes pharmacological, psychological, and somatic interventions. By targeting the sympathetic nervous system, clinicians may harness the body’s own mechanisms to promote recovery and regain control over involuntary physiological responses.
Results and Outcomes
Following the cervical sympathetic blockade, the patient exhibited a notable reduction in the frequency of psychogenic nonepileptic seizures (PNES). Over a span of several months, the reported seizure episodes decreased from an average of eight per month to just two, indicating a significant therapeutic response to the intervention. This change in frequency was documented during regular follow-up visits, where both the patient and the clinical team carefully tracked the emergence and intensity of seizures.
Additionally, the patient reported a marked improvement in overall anxiety and stress levels, as gauged through standardized assessment tools such as the PTSD Checklist (PCL-5) and the Hospital Anxiety and Depression Scale (HADS). Pre-intervention scores revealed severe anxiety and PTSD symptoms, which improved by over 50% following the blockade. This change not only highlighted the reduction in distress but also correlated with a greater sense of control over symptoms and improved daily functioning.
| Outcome Measure | Pre-Intervention Score | Post-Intervention Score |
|---|---|---|
| PNES Frequency (per month) | 8 | 2 |
| PCL-5 Score | 70 (severe symptoms) | 32 (moderate symptoms) |
| HADS Anxiety Subscale | 15 (high anxiety) | 6 (normal) |
The patient also reported improvements in quality of life, expressed through personal accounts of enhanced emotional stability and a reduction in dissociative episodes. These personal testimonies were crucial in understanding the broader psychosocial impacts of the intervention. The patient noted feeling more equipped to handle daily stressors without reverting to seizure-like episodes, marking a progressive shift in the management of their condition.
It is important to highlight that while the initial outcomes are promising, the interdisciplinary approach taken—merging somatic treatment with psychological support—was instrumental in these results. Continuous cognitive-behavioral therapy (CBT) sessions were maintained alongside the sympathetic blockade to further bolster psychological resilience and coping mechanisms. This integrated model not only addressed the immediate seizures but also fostered a conducive environment for sustained recovery.
The outcomes from this case report provide encouraging evidence that interventions targeting the sympathetic nervous system can yield beneficial results for patients with PNES and PTSD. However, further studies with larger sample sizes and longer follow-up periods are needed to substantiate these findings and explore the potential for cervical sympathetic blockade as a mainstream therapeutic option within this context.
Future Directions and Research Implications
The exploration of cervical sympathetic blockade for treating psychogenic nonepileptic seizures (PNES) and post-traumatic stress disorder (PTSD) opens pathways for future research that may significantly enhance understanding and management of these complex conditions. The initial findings suggest that targeting the sympathetic nervous system could be a pivotal aspect of a holistic treatment approach. However, several considerations warrant further investigation to consolidate and expand upon these early outcomes.
Future studies should aim to evaluate the long-term efficacy and safety of cervical sympathetic blockade across a larger and more diverse patient population. This entails conducting randomized controlled trials to assess not only the reduction in seizure frequency but also the sustainability of improvements in anxiety and PTSD symptomology over extended periods. Such investigations could provide valuable insights into potential demographic or psychological factors that influence treatment efficacy.
In addition to expanding sample sizes, it will be crucial to identify biomarkers or neurophysiological indicators that predict responsive patients. The incorporation of advanced imaging techniques, such as functional MRI or PET scans, may help elucidate how the sympathetic nervous system interacts with brain regions associated with trauma and emotional regulation. Understanding these neural pathways could refine patient selection for sympathetic blockade and lead to personalized treatment strategies that enhance outcomes.
Another essential direction would be to explore the integration of cervical sympathetic blockade with other therapeutic modalities. This case highlights the importance of combining physiological interventions with cognitive-behavioral therapies (CBT) that address the psychological roots of PTSD and PNES. Future research should investigate whether synchronous interventions lead to synergistic effects, improving overall treatment efficacy and enhancing patients’ quality of life. A multi-modal approach that incorporates pharmacotherapy, psychotherapy, and physical interventions could set a new standard in treating PTSD and PNES.
The importance of follow-up and monitoring should also be emphasized in ongoing research. Longitudinal studies tracking patients’ progress post-intervention, including psychological assessments and personal experiences, could yield insights into the durability of treatment benefits and potential relapse risks. This would enable practitioners to establish tailored follow-up care that addresses individual patient needs effectively.
Additionally, investigations should examine the mechanism of action of the cervical sympathetic blockade in relation to the symptoms of PTSD and PNES. Understanding how the intervention modulates the autonomic nervous system could lead to enhanced methodologies for treating stress-related disorders. Research efforts may also focus on the effectiveness of varying anesthetic agents or techniques in achieving optimal results, potentially identifying the most effective and safest protocols for clinical practice.
In light of the current case report, there is a pressing need to build a robust body of evidence surrounding the role of cervical sympathetic blockade within the spectrum of trauma-informed care. As our understanding of the mind-body connection deepens, recognizing the influence of physiological responses on psychological well-being becomes essential. Ultimately, future research should strive to enrich treatment frameworks, offering more effective management strategies for those grappling with the debilitating effects of PTSD and PNES.