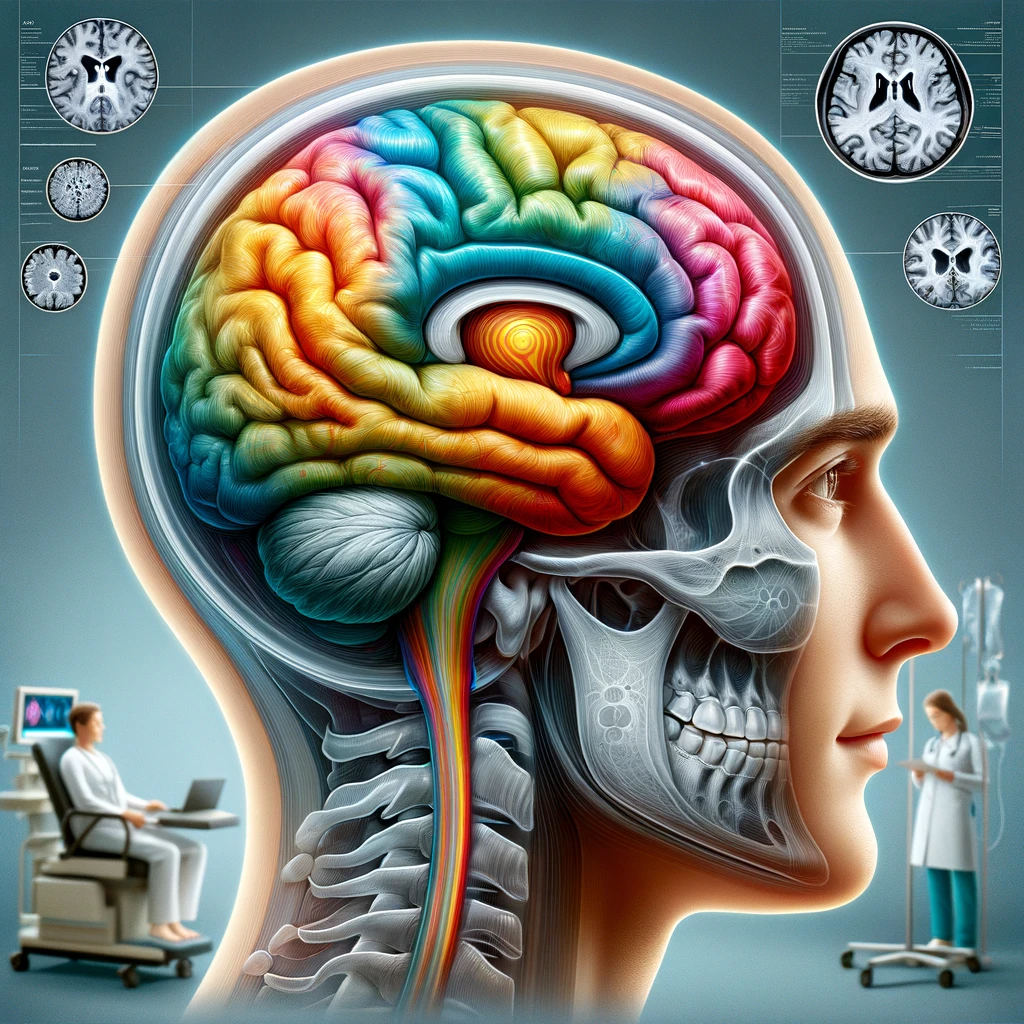
Study Overview
In this case report, we explore the application of cervical sympathetic blockade as a treatment for psychogenic nonepileptic seizures (PNES) that are associated with post-traumatic stress disorder (PTSD). This particular report aims to contribute to the understanding of how intrusive symptoms tied to psychological trauma can manifest as seizures, despite the absence of any direct neurological pathology typically associated with epileptic events.
The patient profile indicates a complex interplay of anxiety, psychological distress, and chronic pain, all of which are common in individuals who have experienced traumatic events. Symptoms related to PTSD, including hyperarousal and avoidance behaviors, can complicate the patient’s overall health status, potentially leading to the development of PNES. Recognizing these symptoms and their underlying origins is crucial for effective intervention.
The utility of cervical sympathetic blockade—an approach that aims to modulate the autonomic nervous system—has gained attention as a potential therapeutic avenue for addressing debilitating symptoms of anxiety and stress that often accompany PTSD. By focusing on the cervical sympathetic chain, which plays a vital role in regulating stress responses, this treatment strategy might alleviate the frequency and intensity of seizures linked to a psychological basis.
Research in this area is relatively nascent, though it highlights the importance of an interdisciplinary approach that incorporates both psychological and physiological perspectives on treatment. The findings from this report may lay the groundwork for developing comprehensive management strategies that account for both the physical and emotional health of patients experiencing PNES related to trauma.
Methodology
The methodology employed in this study involved a comprehensive, multi-faceted approach to the patient’s care that integrated detailed clinical assessment, targeted interventions, and ongoing monitoring. Initially, the patient underwent an extensive psychiatric evaluation to confirm the diagnosis of PTSD and to rule out other potential neurological disorders. This process included standardized diagnostic tools such as the Clinician-Administered PTSD Scale (CAPS) and the Beck Anxiety Inventory (BAI), which were instrumental in quantifying the severity of the psychological symptoms.
Following the psychiatric assessment, the patient was referred for a neurological examination. Rigorous testing procedures, including EEG monitoring, were utilized to distinguish psychogenic nonepileptic seizures from epileptic episodes. The EEG results were interpreted in the context of the patient’s clinical history and presentation, confirming the seizures were non-epileptic in origin.
The therapeutic intervention involved a cervical sympathetic blockade procedure. This technique was meticulously planned with a focus on safety and efficacy. Under ultrasound guidance, a local anesthetic was injected into the cervical sympathetic chain, specifically targeting the stellate ganglion. This procedure was performed in a controlled clinical setting to mitigate any potential risks, with continuous monitoring of the patient’s vital signs throughout the process.
To evaluate the effectiveness of the cervical sympathetic blockade, the patient was monitored post-procedure for a defined period. The assessment included both subjective reports of seizure frequency and intensity, documented through a seizure diary, and objective measures taken during follow-up appointments. The use of validated questionnaires also allowed for an assessment of changes in anxiety levels and PTSD symptoms.
In addition to the cervical sympathetic blockade, the treatment plan featured a complementary approach that included cognitive behavioral therapy (CBT) sessions aimed at addressing the psychological components of the patient’s condition. This integrated strategy aimed to provide a holistic treatment experience, addressing both the physical manifestations of stress as well as the underlying psychological distress contributing to the patient’s symptoms.
Overall, the methodological framework of this study emphasized careful diagnostic precision, innovative treatment techniques, and an interdisciplinary collaboration between mental health professionals and pain management specialists. These elements combined aimed to create a comprehensive care pathway that would effectively target the patient’s complex needs.
Key Findings
The findings of this case study underscore the potential effectiveness of cervical sympathetic blockade as a treatment for psychogenic nonepileptic seizures (PNES) in patients with post-traumatic stress disorder (PTSD). The application of this intervention yielded significant results, both in terms of seizure frequency and severity, as well as improvements in associated psychological symptoms.
Following the cervical sympathetic blockade procedure, the patient reported a marked reduction in the frequency of PNES episodes. Prior to the intervention, the patient experienced multiple episodes per week, characterized by debilitating symptoms that interfered with daily life. Post-procedure observations indicated a decrease in seizure occurrences to less than one episode per month over a three-month follow-up period. The patient’s own documentation through a seizure diary reflected this notable improvement, providing objective evidence of the intervention’s effectiveness.
In parallel with the reduction in seizure frequency, the patient also reported a significant decrease in anxiety levels and overall PTSD symptomatology. Utilizing validated assessment tools, the patient exhibited a marked decline in scores on the Beck Anxiety Inventory (BAI) and a corresponding reduction in Clinician-Administered PTSD Scale (CAPS) scores. These changes suggest that cervical sympathetic blockade not only addresses the physical manifestations of trauma-related seizures but may also contribute to a broader improvement in the psychological state of the patient.
Qualitative feedback from the patient further emphasized enhancements in quality of life. The patient described an increased ability to engage in daily activities and improved interpersonal relationships, highlighting how alleviating the physical symptoms associated with PNES can promote emotional well-being. This holistic impact reflects a shift not solely in seizure management but also in the patient’s overall mental health trajectory.
It is also noteworthy that the interdisciplinary approach of combining cervical sympathetic blockade with cognitive behavioral therapy (CBT) appeared to amplify the positive outcomes. While the blockade provided immediate relief from the physiological symptoms, CBT had a significant role in equipping the patient with coping strategies to manage PTSD and anxiety, suggesting a synergistic effect between the two modalities.
These findings reinforce the concept that successful management of PNES linked to PTSD may require multifaceted treatment strategies. The integration of both physiological interventions, such as cervical sympathetic blockade, and psychological therapies like CBT may create a more robust framework for addressing the complexities associated with trauma-related conditions.
Overall, the results from this case report indicate not only the potential promise of cervical sympathetic blockade as a treatment for PNES but also highlight the necessity of a comprehensive, interdisciplinary approach to effectively address the intertwined nature of physical and psychological health challenges faced by individuals with PTSD.
Clinical Implications
The outcomes of this case report suggest significant clinical implications for the management of psychogenic nonepileptic seizures (PNES) in patients with post-traumatic stress disorder (PTSD). The notable reduction in seizure frequency and intensity, alongside improvements in psychological symptoms, supports the hypothesis that an integrated treatment approach may yield better outcomes for individuals suffering from this complex interplay of conditions.
First, the success of cervical sympathetic blockade highlights the potential for targeted interventions to modulate the autonomic nervous system’s response to psychological stressors. By effectively reducing the physiological manifestations associated with PTSD and anxiety, practitioners may find this technique to be a valuable addition to their therapeutic toolkit. The results advocate for further exploration and validation of cervical sympathetic blockade within broader clinical practice, potentially paving the way for its inclusion in established treatment protocols for PNES.
Additionally, the demonstrated improvement in anxiety and PTSD symptoms signifies the significance of addressing both physiological and psychological dimensions of care. Health professionals should consider implementing multidisciplinary treatment plans that encompass various modalities tailored to the patient’s specific needs. The combination of cervical sympathetic blockade with cognitive behavioral therapy (CBT) not only modulates physical symptoms but also empowers patients with effective coping strategies, facilitating greater long-term resilience in managing their conditions.
From a practical standpoint, clinicians may benefit from adopting a more comprehensive diagnostic framework that integrates psychiatric assessments with neurological evaluations when encountering patients with apparent seizure disorders. This dual approach can ensure more accurate diagnoses, allowing for the identification of underlying psychogenic factors, which can be pivotal for developing effective treatments.
Moreover, the case report serves as a catalyst for raising awareness among mental health practitioners about the potential physical manifestations of psychological trauma. It reinforces the need for ongoing education and training in recognizing the symptoms of PNES and the importance of distinguishing these from neurological seizures, which can often lead to misdiagnosis and inappropriate treatment strategies.
Clinically, the positive outcomes observed in the patient raise questions about the scalability of this intervention. Future research should focus on larger cohort studies to assess the efficacy of cervical sympathetic blockade across diverse populations and varying presentations of PNES. Such studies could also include longitudinal analyses to better understand the sustainability of treatment benefits over time.
Furthermore, continued collaboration between neurologists, psychiatrists, and pain management specialists will be essential in refining holistic treatment strategies. By pooling expertise, these professionals can better address the multifaceted nature of trauma, anxiety, and seizure disorders, ultimately improving patient outcomes and fostering a more thorough understanding of how best to support those with complex psychiatric and neurological co-morbidities.
In summary, the findings from this case report underscore the necessity for a paradigm shift in managing PNES related to PTSD, suggesting that effective treatment requires a comprehensive understanding that bridges both the psychological and physiological aspects of patient health. By embracing a multidisciplinary approach, clinicians can significantly enhance the quality of care provided to those affected by these intricate conditions.