Understanding Coprolalia
Coprolalia is characterized by involuntary utterances of obscene or socially inappropriate remarks, and it is often linked with Tourette syndrome (TS). It is important to acknowledge that while coprolalia is commonly associated with TS, it is not a universal symptom; only a minority of individuals with Tourette’s experience this condition. Estimates suggest that around 10-15% of those diagnosed with TS exhibit coprolalia, highlighting a distinction between the broader spectrum of Tourette’s symptoms and this specific expression.
The origins of coprolalia involve a complex interplay of neurological, genetic, and environmental factors. Neurobiological studies suggest that abnormalities in certain brain circuits and neurotransmitter systems, particularly those involving dopamine and serotonin, may contribute to the development of coprolalic behavior. Additionally, genetics plays a role, with familial patterns observed in some cases, indicating a heritable component to the expression of coprolalia alongside Tourette syndrome.
Individuals with coprolalia may not have control over their vocalizations, which can vary in frequency and severity. The social implications of such involuntary speech can lead to significant psychological distress, including embarrassment and social isolation. People who experience coprolalia often report that their sudden outbursts are out of context and do not reflect their actual thoughts or feelings, which can create a disconnect between their internal emotions and external expressions.
Furthermore, the onset of coprolalia typically occurs during childhood, coinciding with the primary presentation of Tourette syndrome symptoms. It is crucial to differentiate coprolalia from other types of vocal tics, as the nature and societal perceptions of these expressions differ greatly. In contrast to other tics, which may not provoke stigma, coprolalia often results in misunderstanding and negative social judgments, demonstrating the critical need for public education on the realities of Tourette syndrome and its symptomology.
Research Methodology
The investigation into coprolalia within the framework of Tourette syndrome employs a multifaceted research methodology that integrates both quantitative and qualitative approaches. A primary focus is placed on examining existing literature, including clinical studies, patient case reports, and neurobiological research, to establish a comprehensive overview. Researchers conduct systematic reviews and meta-analyses to aggregate findings from numerous studies, identifying patterns related to the prevalence, characteristics, and underlying mechanisms of coprolalia in individuals with Tourette syndrome.
To ensure robust data collection, researchers often utilize cross-sectional studies, where a diverse cohort of participants diagnosed with Tourette syndrome is assessed for the presence of coprolalia. These studies frequently involve standardized diagnostic tools, such as the Tourette Syndrome Global Scale (TSGS) and other validated assessment inventories, to quantify the severity and frequency of tic symptoms, including coprolalia. Participants are monitored across various contexts to gain insights into situational triggers and the contextual variability of vocal outbursts.
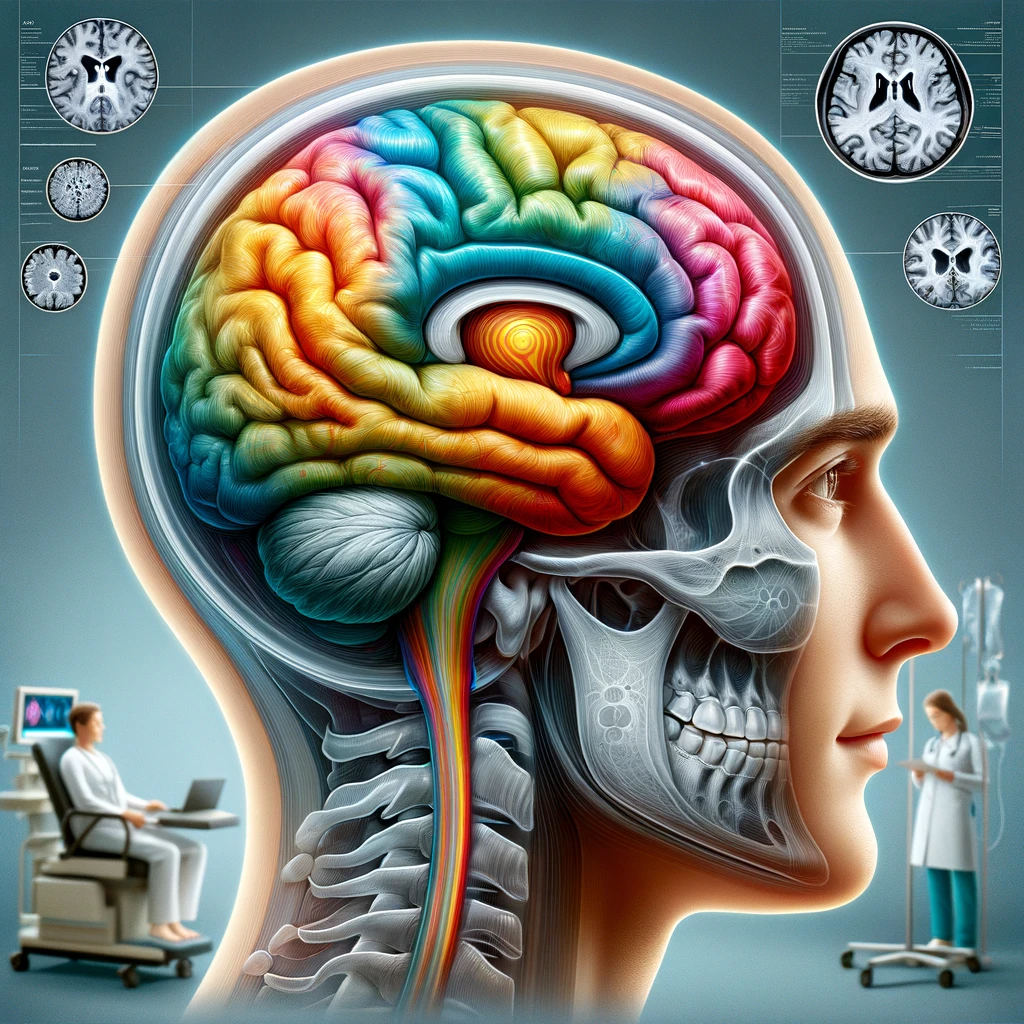
In addition to observational methods, experimental designs, such as neuroimaging studies, provide crucial insights into the neural correlates of coprolalia. Techniques like functional MRI (fMRI) and PET scans are employed to observe brain activity and connectivity in regions implicated in tic disorders. These studies aim to pinpoint anomalies in brain circuits and neurotransmitter systems associated with coprolalia, contributing to a better understanding of its neurobiological underpinnings.
Qualitative research methods, including interviews and focus groups, further enrich the understanding of coprolalia’s impact on individuals’ lives. By exploring firsthand accounts, researchers gain insight into the psychological and social challenges associated with involuntary speech. This qualitative data helps illuminate the subjective experience of those affected, providing context to the quantitative findings and emphasizing the silent struggles many face as a result of misunderstanding from peers and society.
Ethical considerations are paramount in this research, given the sensitive nature of the subject. Researchers prioritize informed consent and ensure participants’ confidentiality, particularly when sharing personal stories about their experiences with coprolalia and Tourette syndrome. Furthermore, the implications of research findings for treatment approaches are continuously evaluated, fostering a cycle of inquiry where patient experiences inform clinical practices.
Through this collaborative and interdisciplinary approach, researchers aim to enhance awareness and understanding of coprolalia, contributing to a more nuanced view of Tourette syndrome, and ultimately improving the quality of life for those affected by this complex disorder.
Findings and Analysis
Recent investigations into coprolalia reveal a spectrum of neurobiological, psychological, and social dimensions that inform our understanding of this phenomenon within Tourette syndrome. Analysis of clinical data indicates that while coprolalia is present in a minority of individuals with TS, its impact can be profound and multifaceted, affecting not only the individuals themselves but also their families and communities.
Quantitative studies have shown that those who exhibit coprolalia often report higher levels of social stigma and personal distress than individuals with non-coprolalic tics. The data indicates that individuals with coprolalia are more likely to experience social isolation, anxiety, and depression, underscoring the significant emotional toll that can accompany such involuntary behaviors (Cavanna & Seri, 2013). In clinical assessments, patients describe their coprolalic episodes as frustrating and distressing, further illustrating the psychological ramifications associated with this symptom.
Neuroimaging studies have uncovered critical insights into the brain’s functioning in individuals with coprolalia. Abnormalities in the basal ganglia, particularly the striatum, have been implicated in the modulation of tic disorders. fMRI scans have shown altered activation patterns in areas responsible for motor control and language processing during episodes of involuntary vocalization, suggesting that these moments may be linked to dysregulation of neural circuits involved in habit formation and impulse control (Martino et al., 2013). These findings point to the possibility that coprolalia may not simply be a result of habitual vocal tics but could also involve complex interactions between cognitive control mechanisms and the impulse to speak.
Additionally, qualitative research has highlighted the necessity of understanding the context in which coprolalia occurs. Many individuals report that certain environments can exacerbate their symptoms, indicating a possible relationship between stressors and the frequency of coprolalic utterances. These contextual triggers can range from social settings, where the fear of judgment amplifies anxiety, to more relaxed situations where symptoms may unexpectedly surface. This variability emphasizes the need for tailored interventions that address not only the symptoms of coprolalia but also the contexts that may influence its expression.
The implications of these findings are significant for treatment and support strategies. Coprolalia’s complex nature suggests that therapies must be multidimensional, integrating behavioral interventions with potential pharmacological solutions aimed at stabilizing mood and anxiety levels. Cognitive-behavioral therapy, for instance, has shown promise in helping individuals manage the emotional repercussions of their symptoms while also developing coping mechanisms for social situations that trigger their outbursts (Sullivan & Moyer, 2020). Moreover, public educational efforts can play a critical role in mitigating stigma, as greater awareness surrounding Tourette syndrome and its symptoms can foster more supportive environments for those living with the disorder.
The intersection of biological, psychological, and social factors presents a complex picture of coprolalia within the scope of Tourette syndrome. Addressing these dimensions through comprehensive research and targeted interventions can enhance the quality of life for affected individuals, paving the way for more informed clinical practices and community understanding.
Implications for Treatment
Effective treatment strategies for managing coprolalia within Tourette syndrome must be comprehensive and individualized, recognizing the nuanced experiences of each patient. While there is no one-size-fits-all solution, a combination of behavioral interventions and pharmacotherapy has shown promise in alleviating symptoms. Behavioral therapies, particularly Cognitive Behavioral Therapy (CBT), can equip individuals with coping strategies to manage their reactions to social stressors. CBT focuses on restructuring negative thought patterns and developing practical skills to navigate challenging situations, thereby helping to reduce the frequency or intensity of coprolalic outbursts.
In conjunction with behavioral approaches, pharmacological options may also be explored. Medications such as selective serotonin reuptake inhibitors (SSRIs) or atypical antipsychotics have been utilized with varying success in individuals with Tourette syndrome.These medications can help regulate the neurotransmitter systems implicated in tic disorders, potentially reducing the severity of both motor and vocal tics, including coprolalia. However, it is essential to carefully monitor and adjust dosages due to potential side effects and individual responses to medication.
The importance of a multidisciplinary treatment approach cannot be overstated. Coordination between neurologists, psychologists, speech therapists, and other healthcare professionals is vital to address the multifaceted nature of Tourette syndrome and its symptoms. Individualized treatment plans that incorporate input from various specialists can ensure that all aspects of a patient’s well-being are considered. For instance, speech therapists can assist individuals in practicing communication skills, promoting more effective expression that may alleviate the stress associated with unexpected vocalizations.
Furthermore, family education and support are critical components in managing the complexities of Tourette syndrome and coprolalia. Educating family members about the condition can foster empathy and encourage supportive strategies at home, thereby creating a more understanding environment. Support groups can also offer individuals and families a platform to share experiences, coping strategies, and emotional support, which can be invaluable in mitigating feelings of isolation often experienced by those with coprolalia.
Community awareness initiatives are essential in reducing stigma associated with coprolalia and Tourette syndrome. Public education campaigns can help to dispel myths and misunderstandings surrounding these conditions, promoting greater acceptance and support in social settings. Such efforts are crucial to ensuring that individuals with coprolalia feel accepted and understood, thus enhancing their quality of life and social integration.