Clinical Presentation
The clinical presentation of complex post-traumatic stress disorder (CPTSD) can be multifaceted, often varying between individuals. This condition typically arises after experiencing prolonged or repeated trauma, especially in situations involving interpersonal violence or severe neglect. Individuals may exhibit a range of symptoms that can significantly impair their daily functioning and quality of life.
One of the hallmark characteristics of CPTSD is the presence of intrusive thoughts or memories pertaining to the traumatic events. These can manifest as flashbacks, where the person feels as though they are reliving the trauma. Alongside these intrusive symptoms, individuals may experience persistent negative moods, such as feelings of hopelessness, detachment from others, and diminished interest in activities previously enjoyed. Heightened emotional responses can lead to irritability and difficulty regulating emotions, often resulting in outbursts or intense feelings of anger.
Another significant component of the clinical presentation involves alterations in perception related to one’s sense of self. Those with CPTSD often struggle with feelings of worthlessness or shame, which can exacerbate their emotional distress. Furthermore, individuals may become hyper-vigilant, exhibiting an exaggerated startle response and constant feelings of being on edge, which can lead to increased anxiety and sleep disturbances.
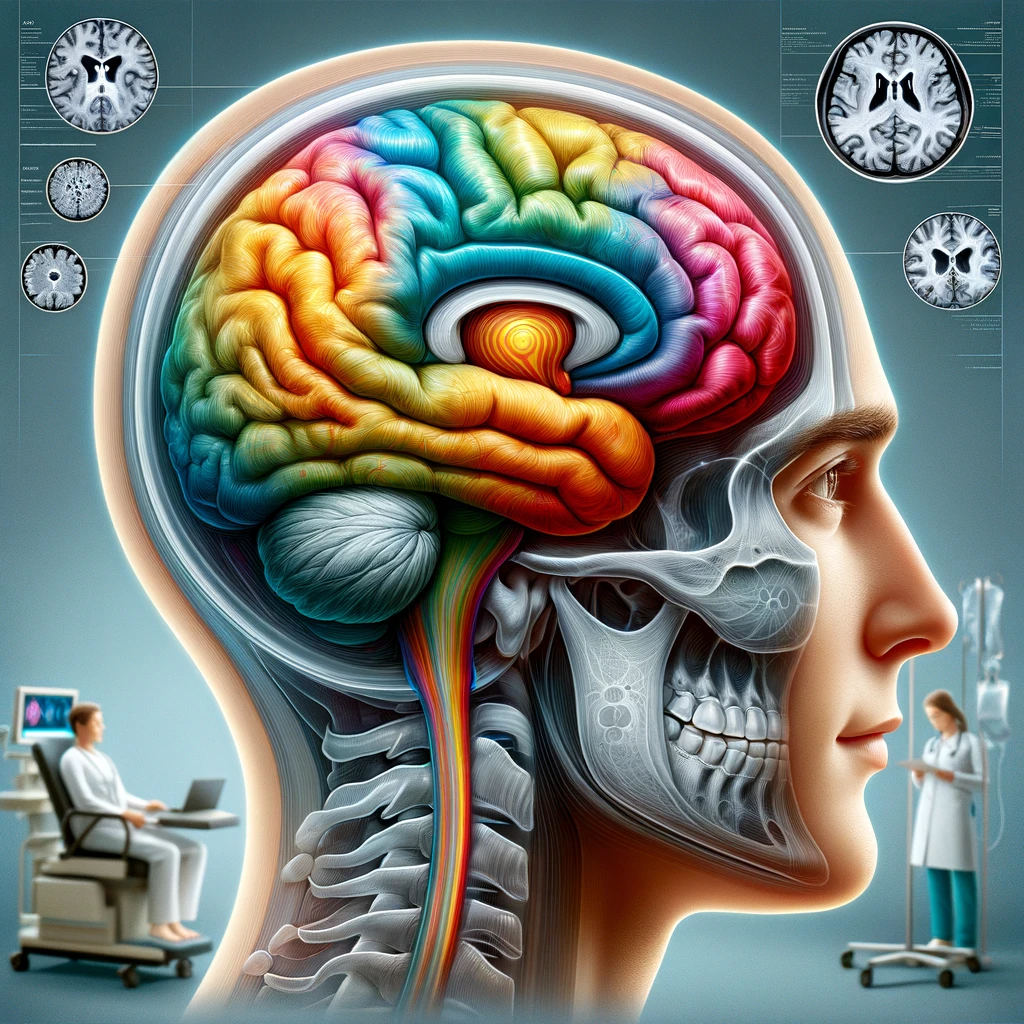
In some cases, individuals might also present with psychogenic non-epileptic seizures (PNES), a condition often linked with psychological stress rather than neurological issues. These seizures can be distressing and may confuse both the patient and healthcare providers. Distinguishing PNES from true epileptic seizures is crucial because the management and treatment approaches differ significantly.
Clinical assessments typically include comprehensive evaluations to detect symptoms associated with CPTSD, alongside tools that assess the frequency and type of dissociative and seizure-like episodes. Accurate documentation and a thorough history-taking process are essential to formulate an effective treatment plan.
A potential overview of common symptoms associated with CPTSD, including those leading to PNES, is presented in the following table:
| Symptom Category | Common Symptoms |
|---|---|
| Intrusive Symptoms | Flashbacks, intrusive memories, nightmares |
| Negative Mood | Feelings of hopelessness, guilt, emotional numbing |
| Alterations in Self-Perception | Shame, self-blame, feelings of worthlessness |
| Hyper-arousal Symptoms | Hyper-vigilance, increased startle response, sleep disturbances |
| Physical Manifestations | Psychogenic non-epileptic seizures, somatic complaints |
Understanding these varied presentations is critical for clinicians, as they formulate personalized treatment strategies that address the comprehensive needs of individuals suffering from CPTSD and related complications such as PNES.
Diagnosis and Assessment
The diagnosis of complex post-traumatic stress disorder (CPTSD) necessitates careful clinical evaluation due to its intricate symptomatology and overlap with other psychiatric disorders. Clinicians utilize several standardized assessment tools alongside clinical interviews to ensure an accurate diagnosis. Central to the diagnostic process is the recognition of the unique features of CPTSD compared to traditional PTSD.
Initial assessments typically begin with detailed clinical interviews that explore the patient’s trauma history, symptom onset, and the context of their experiences. The clinician examines the patient’s emotional and behavioral responses, emphasizing the persistence of symptoms and their impact on daily functioning. Specific attention is paid to dissociative experiences and the frequency of psychogenic non-epileptic seizures (PNES), as these may significantly complicate treatment.
In clinical settings, validated instruments such as the International Trauma Questionnaire (ITQ) or the Clinician-Administered PTSD Scale for DSM-5 (CAPS-5) may be employed. These tools assess trauma exposure, frequency and severity of symptoms, and functional impairment. Particularly, the ITQ allows for a nuanced exploration of the criteria distinguishing PTSD and CPTSD, considering symptoms such as difficulties with emotion regulation and persistent negative self-perception.
Additionally, diagnostic procedures include neurological evaluations to differentiate PNES from true epileptic seizures. This differentiation is critical, as management strategies vary significantly. For example, video EEG monitoring may be conducted to record brain activity during seizure-like episodes, aiding in the determination of their origin. Patients diagnosed with PNES will not display the expected electrical activity in the brain typically seen during epileptic seizures.
To further illustrate the assessment process, the table below summarizes various diagnostic tools and their respective focus areas:
| Assessment Tool | Description |
|---|---|
| International Trauma Questionnaire (ITQ) | Assesses trauma exposure and CPTSD symptoms, including self-perception and interpersonal difficulties. |
| Clinician-Administered PTSD Scale for DSM-5 (CAPS-5) | Captures PTSD and CPTSD symptom severity via a structured interview, with emphasis on functional impairment. |
| Video EEG Monitoring | Monitors and records brain activity during seizure events to distinguish between epileptic and non-epileptic seizures. |
| Dissociative Experiences Scale (DES) | Identifies the presence and severity of dissociative symptoms, frequently seen in CPTSD cases. |
Comprehensive documentation of the clinical findings is essential for ongoing assessment and treatment planning. It allows healthcare providers to track changes in symptomatology over time and adjust interventions as necessary. A multidisciplinary approach, involving mental health professionals, neurologists, and other specialists, is often advantageous in managing the complex interplay of symptoms presented by individuals with CPTSD and PNES.
Overall, a thorough diagnosis and detailed assessment processes serve as critical components in the management of CPTSD. Recognizing the individual variability in symptom presentation allows clinicians to tailor treatment plans effectively, enhancing outcomes for those affected by this challenging condition.
Treatment Approaches
Future Directions
The evolving landscape of treatment approaches for complex post-traumatic stress disorder (CPTSD) and associated conditions like psychogenic non-epileptic seizures (PNES) presents numerous pathways for future research and clinical application. Given the complexities involved in the diagnosis and treatment of CPTSD, an emphasis on personalized interventions tailored to individual needs will be crucial.
One promising avenue lies in the integration of trauma-informed care across various health service sectors. This approach not only acknowledges the widespread impact of trauma but also promotes practices that avoid re-traumatization, fostering a healing environment for patients. Training programs aimed at healthcare providers across disciplines—mental health, neurology, primary care—could enhance their ability to recognize trauma-related symptoms and provide appropriate referrals or interventions.
Emerging therapeutic modalities also warrant attention. For example, Eye Movement Desensitization and Reprocessing (EMDR) has shown effectiveness in reducing symptoms of PTSD, including those associated with CPTSD. Continued research exploring the efficacy of EMDR specifically tailored for CPTSD patients exhibiting PNES may yield beneficial outcomes. Additionally, there is growing interest in the application of psychedelics, such as psilocybin and MDMA, which have demonstrated promising results in clinical trials for PTSD treatment. Future studies could investigate whether these substances may also help alleviate symptoms in those with CPTSD.
Another significant research focus could involve the role of digital therapeutics and telehealth platforms in delivering interventions. These platforms provide accessibility and flexibility, which could improve engagement among patients. Novel applications can utilize real-time data collection on symptomatology, allowing for adaptive treatment strategies. For instance, mobile applications designed for mindfulness and emotional regulation skill-building could be integrated into traditional therapeutic modalities, fostering better coping mechanisms.
Furthermore, interdisciplinary studies incorporating neurobiological assessments may enhance our understanding of the biological underpinnings of CPTSD and PNES. Biomarkers associated with stress responses could lead to objective measures for diagnosing and monitoring treatment efficacy. This integrative approach, combining psychological, neurological, and physiological data, will provide a more comprehensive framework for understanding individual variability in symptom presentation and response to treatment.
Advancements in community and social support systems represent another critical dimension of future directions. Research into the efficacy of peer support networks and community-based interventions can augment psychological treatments, addressing the social isolation often experienced by individuals with CPTSD. Creating environments that foster connection and understanding can be instrumental in recovery processes.
In conclusion, broadening research efforts to encompass a multi-faceted understanding of CPTSD and PNES will be essential in developing effective treatment modalities. By combining innovative therapeutic approaches, integrating technology, and fostering community connections, we can enhance the overall care and support provided to individuals navigating these complex conditions. The path forward calls for a collaborative approach that not only addresses psychological symptoms but also considers the profound impact of trauma on the holistic well-being of affected individuals.
Future Directions
The ongoing exploration of treatment methodologies for complex post-traumatic stress disorder (CPTSD) and its associated manifestations, such as psychogenic non-epileptic seizures (PNES), points toward an array of prospective research avenues and clinical practices. As we deepen our understanding of these intricate conditions, emphasizing personalized treatment approaches will become increasingly vital for addressing the unique experiences and needs of individuals affected by CPTSD.
A key area for development is the promotion of trauma-informed care within various healthcare settings. This model seeks to recognize the extensive influence of trauma and create environments conducive to healing, minimizing the risk of re-traumatization. An effective strategy includes implementing comprehensive training programs for healthcare professionals across disciplines—such as mental health practitioners, neurologists, and primary care providers—enabling them to identify trauma-related symptoms and facilitate appropriate referrals or interventions.
In the realm of therapeutic techniques, emerging modalities merit significant attention. Eye Movement Desensitization and Reprocessing (EMDR) has garnered recognition for its efficacy in mitigating PTSD symptoms, including those endemic to CPTSD. Further investigation into the adaptation of EMDR techniques specifically catering to CPTSD patients who experience PNES may yield promising results. Moreover, the exploration of psychedelic-assisted therapies, including the use of substances like psilocybin and MDMA, presents an exciting frontier. Recent clinical trials have shown potential benefits in treating PTSD, suggesting that these approaches could also extend to alleviating complex symptoms in CPTSD.
The integration of digital health solutions into treatment paradigms offers additional promise for the future. Telehealth platforms and digital therapeutics can enhance accessibility and engagement for patients, enabling real-time monitoring of symptomatology. Applications designed for mindfulness practice and emotional regulation could be effectively incorporated into conventional therapeutic frameworks, providing patients with tools to manage distressing symptoms more efficiently.
Interdisciplinary research focused on the neurobiological dimensions of CPTSD and PNES is another prospective direction. Identifying biomarkers linked to stress responses may pave the way for more objective diagnostic criteria and tracking methods for treatment effectiveness. By synergizing psychological, neurological, and physiological insights, we can develop a sophisticated understanding of individual variability in symptom expression and treatment resonance.
Furthermore, enhancing community-based support networks is crucial for fostering resilience among individuals suffering from CPTSD. Investigating the viability of peer support programs and community-centric initiatives can provide complementary assistance to formal psychological interventions. Establishing connections and nurturing relationships can counteract social isolation, which is often experienced by those affected by CPTSD.
In summary, advancing research initiatives that encompass a multi-dimensional approach to CPTSD and PNES will be pivotal in crafting innovative and effective treatment methodologies. By synergizing cutting-edge therapeutic practices with technological solutions and supportive community frameworks, we can significantly improve the care and resources available to individuals navigating these complex disorders. The journey ahead will necessitate a collaborative effort that holistically addresses the ramifications of trauma while promoting the overall well-being of those affected.