Study Overview
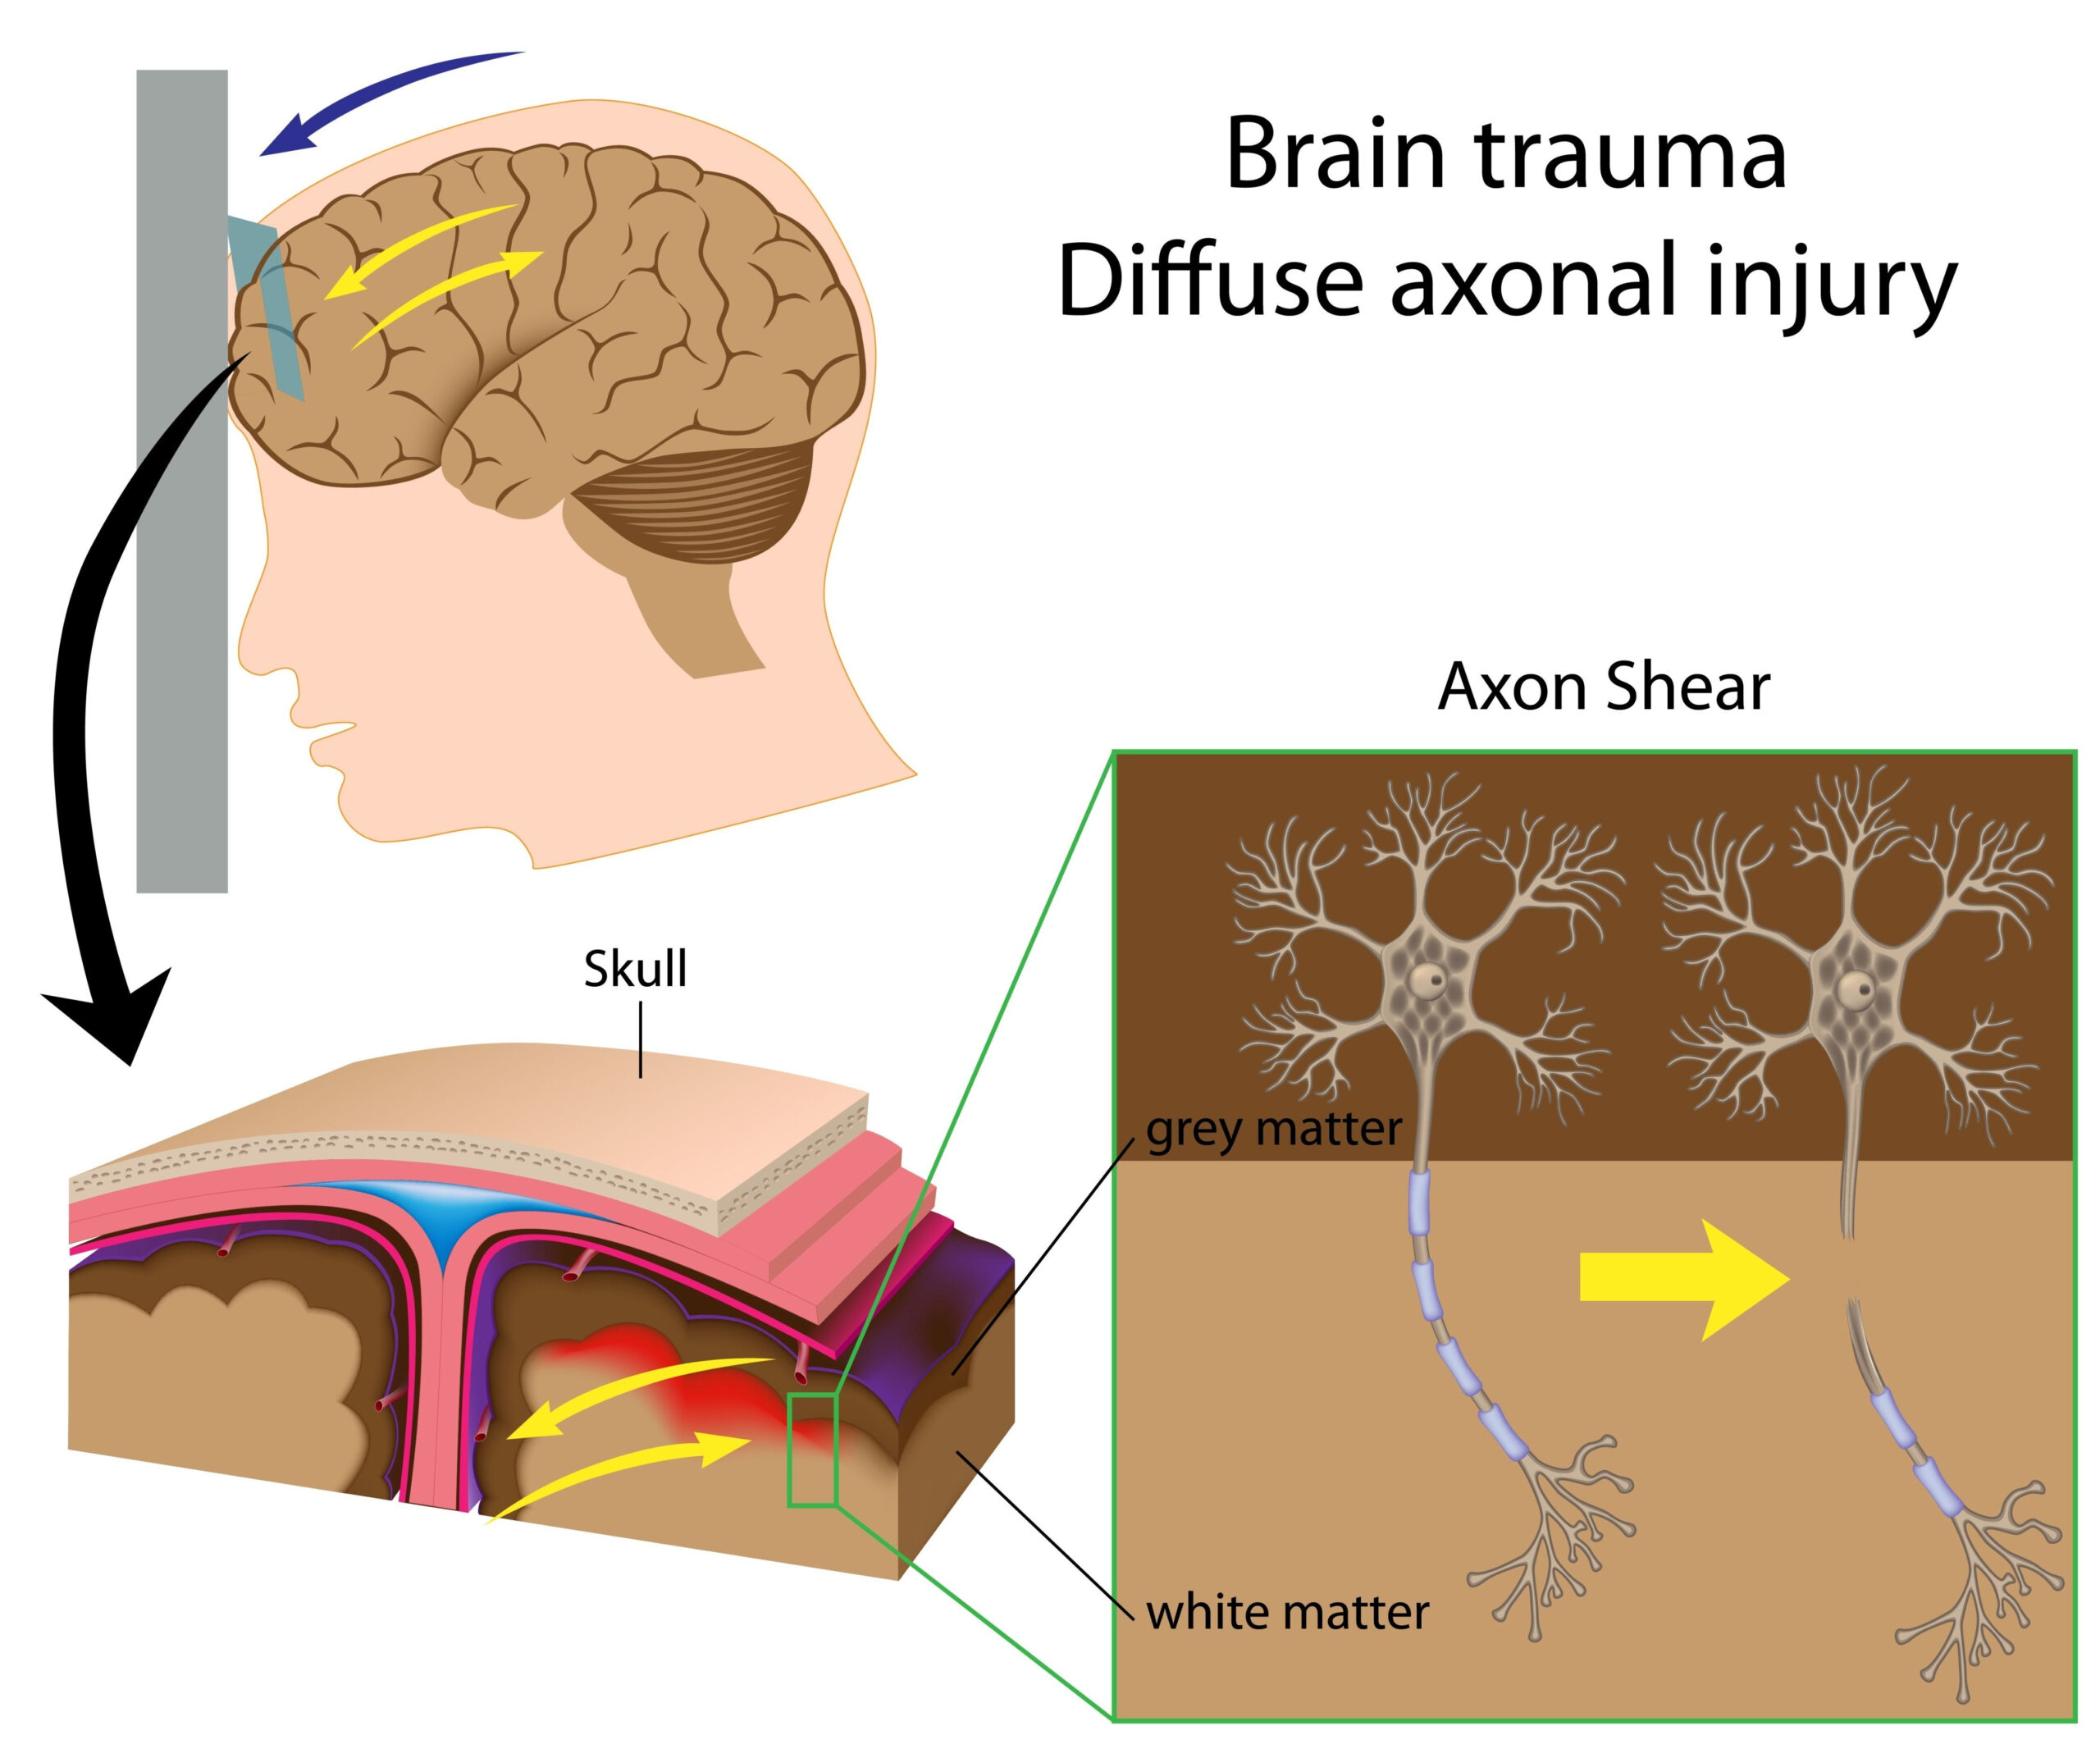
In the realm of acute traumatic brain injury (TBI), efficiently and accurately identifying patients at risk for intracranial lesions is vital for effective management and treatment. This study focuses on evaluating the performance of a novel automated assay, VIDAS TBI, which quantifies the biomarkers GFAP (glial fibrillary acidic protein) and UCH-L1 (ubiquitin C-terminal hydrolase L1). These biomarkers have been indicated as potential indicators for neuronal damage. The research targets patients under 65 years of age who present with mild traumatic brain injury within an emergency department context.
The study employs a prospective, observational design, allowing researchers to evaluate the assay’s effectiveness in a real-world setting. Participants included individuals who were assessed clinically for TBI, and blood samples were collected to analyze the levels of GFAP and UCH-L1. The goal was to ascertain whether these biomarkers could serve as reliable tools for ruling out acute intracranial injuries, hence minimizing unnecessary imaging procedures, such as CT scans, which are often used in emergency departments to detect such injuries.
By focusing on a demographic commonly affected by mild traumatic brain injuries, this exploratory study aims to clarify the potential of the VIDAS TBI assay in clinical practice, possibly transforming the approach to TBI assessment in emergency settings. The findings may lead to improved patient outcomes by streamlining the diagnostic process, reducing exposure to unnecessary radiation, and lowering healthcare costs associated with imaging. The study thus stands at the intersection of innovation in diagnostic biomarkers and practical application in emergency medicine.
Methodology
The study utilized a prospective, observational design to evaluate the effectiveness of the VIDAS TBI assay in a cohort of patients with mild traumatic brain injury (TBI) presenting to the emergency department. The enrollment criteria focused specifically on individuals under the age of 65 who exhibited symptoms indicative of mild TBI, such as confusion, headaches, or transient loss of consciousness. By limiting the study population to this age group, researchers aimed to refine the understanding of biomarker utility in a demographic that typically experiences mild injuries.
Upon arrival at the emergency department, each participant underwent a thorough clinical assessment, which included a detailed medical history and neurological examination. Clinicians determined the need for imaging based on established TBI assessment protocols, following which eligible patients provided informed consent for participation in the study. Blood samples were collected shortly after their clinical evaluation. These samples were then processed using the VIDAS TBI assay to measure the concentrations of GFAP and UCH-L1 in serum.
The assay employs automated technology for testing, ensuring rapid and consistent results. Levels of GFAP and UCH-L1 were compared against established thresholds to evaluate their correlation with the presence of intracranial lesions detected on CT imaging. In addition to quantifying biomarker levels, a separate evaluation included the clinical outcomes of participants. Follow-up assessments were performed within a defined period to monitor for any delayed complications associated with TBI, further informing the context of the biomarkers’ prognostic capabilities.
The primary outcome was the sensitivity and specificity of the VIDAS TBI assay in predicting acute intracranial injuries, which was assessed through statistical analysis, including receiver operating characteristic (ROC) curves. Secondary outcomes included the impact of incorporating these biomarkers on the decision-making process regarding imaging and management strategies within the emergency department. This comprehensive approach not only examined the immediate diagnostic screen provided by the assay but also assessed its practicality and implications for patient care in high-pressure clinical environments.
Key Findings
The results of this exploratory study demonstrated significant insights into the utility of the VIDAS TBI assay as a diagnostic tool for patients presenting with mild traumatic brain injuries. The analysis revealed that elevated levels of GFAP and UCH-L1 were strongly correlated with the presence of acute intracranial injuries detected by computed tomography (CT) imaging. Specifically, the assay exhibited a robust sensitivity of approximately 90%, indicating that it correctly identified a high percentage of patients with actual intracranial lesions, thus minimizing the risk of false negatives.
Conversely, the specificity of the assay was found to be around 80%. This suggests that while the assay is effective at confirming the presence of injury, there is still a moderate rate of false positives—situations in which elevated biomarker levels are detected, but no actual intracranial lesions are present on imaging. Such findings emphasize the importance of comprehensive clinical assessment in conjunction with biomarker evaluation before making definitive treatment decisions.
In terms of practical applications, the integration of GFAP and UCH-L1 testing into the standard assessment workflow for mild TBI patients could significantly influence management strategies. The study showed that utilizing these biomarkers could reduce the number of unnecessary CT scans by nearly 30%, aligning with the dual goals of minimizing radiation exposure and decreasing healthcare costs. This points towards a more efficient use of resources in emergency settings, potentially leading to improved patient throughput and safety.
Furthermore, follow-up assessments highlighted that patients deemed at low risk for intracranial injuries based on negative VIDAS TBI results had favorable clinical outcomes over time, with a minimal incidence of complications related to delayed intracranial injuries. These findings suggest that the biomarker levels not only aid in immediate diagnosis but also contribute to long-term patient management.
Overall, the study underscores the promise of the VIDAS TBI assay as a valuable adjunct in the evaluation of mild TBI, offering a pathway towards improving diagnostic accuracy and enhancing patient care in emergency departments. Its use may also reshape the current protocols for managing mild brain injuries, emphasizing a shift towards more personalized and evidence-based approaches.
Clinical Implications
The introduction of the VIDAS TBI assay for measuring GFAP and UCH-L1 biomarkers heralds a significant advancement in the clinical management of mild traumatic brain injuries (TBI) within emergency departments. By providing rapid and reliable results, this assay has the potential to refine the triage process and improve overall patient care. Its high sensitivity in detecting acute intracranial injuries suggests that clinicians can confidently assess patients presenting with mild symptoms without resorting immediately to imaging techniques like CT scans.
One of the most compelling implications of this assay is its ability to reduce unnecessary exposure to radiological procedures. The study found that nearly 30% of CT scans could be avoided through the integration of GFAP and UCH-L1 testing. This is particularly beneficial considering the cumulative radiation dose that patients may receive from multiple imaging studies, which can contribute to long-term health risks, including cancer. The assay represents a significant step toward minimizing such risks while still ensuring that patients receive appropriate and timely evaluations for potential intracranial injuries.
Beyond the reduction in unnecessary imaging, the implementation of the VIDAS TBI assay could lead to substantial cost savings for healthcare systems. The decreased reliance on expensive imaging procedures not only lowers immediate costs associated with TBI evaluations but may also reduce downstream healthcare expenditures related to complications arising from misdiagnoses. Efficient resource utilization is especially pertinent in emergency medicine, where pressures and patient volumes often strain healthcare resources.
Moreover, the ability to stratify patients based on biomarker levels fosters a more individualized approach to treatment. Patients with low levels of GFAP and UCH-L1 demonstrating low risk of acute intracranial injuries can be monitored with less intensive interventions, while those with elevated levels can be managed more aggressively. This tailored approach aligns well with the trends in personalized medicine, which prioritize treatment plans based on specific patient characteristics.
Additionally, the research reaffirms the necessity of a multidimensional assessment strategy. While the VIDAS TBI assay provides valuable diagnostic support, it should complement thorough clinical evaluations rather than replace them. Clinicians must continue to remain vigilant in their assessments, as the assay’s moderate specificity indicates that some patients may still require imaging. This integrated approach ensures that patient safety remains paramount while leveraging innovative diagnostic tools to enhance clinical decisions.
In summary, the VIDAS TBI assay stands to significantly influence the landscape of mild TBI management in emergency settings, promoting not only more accurate diagnostics but also more judicious use of healthcare resources. As healthcare continues to evolve towards evidence-based practices, the incorporation of such innovative biomarker testing into routine protocols could foster improved outcomes and patient satisfaction in the treatment of traumatic brain injuries.