Background and Rationale
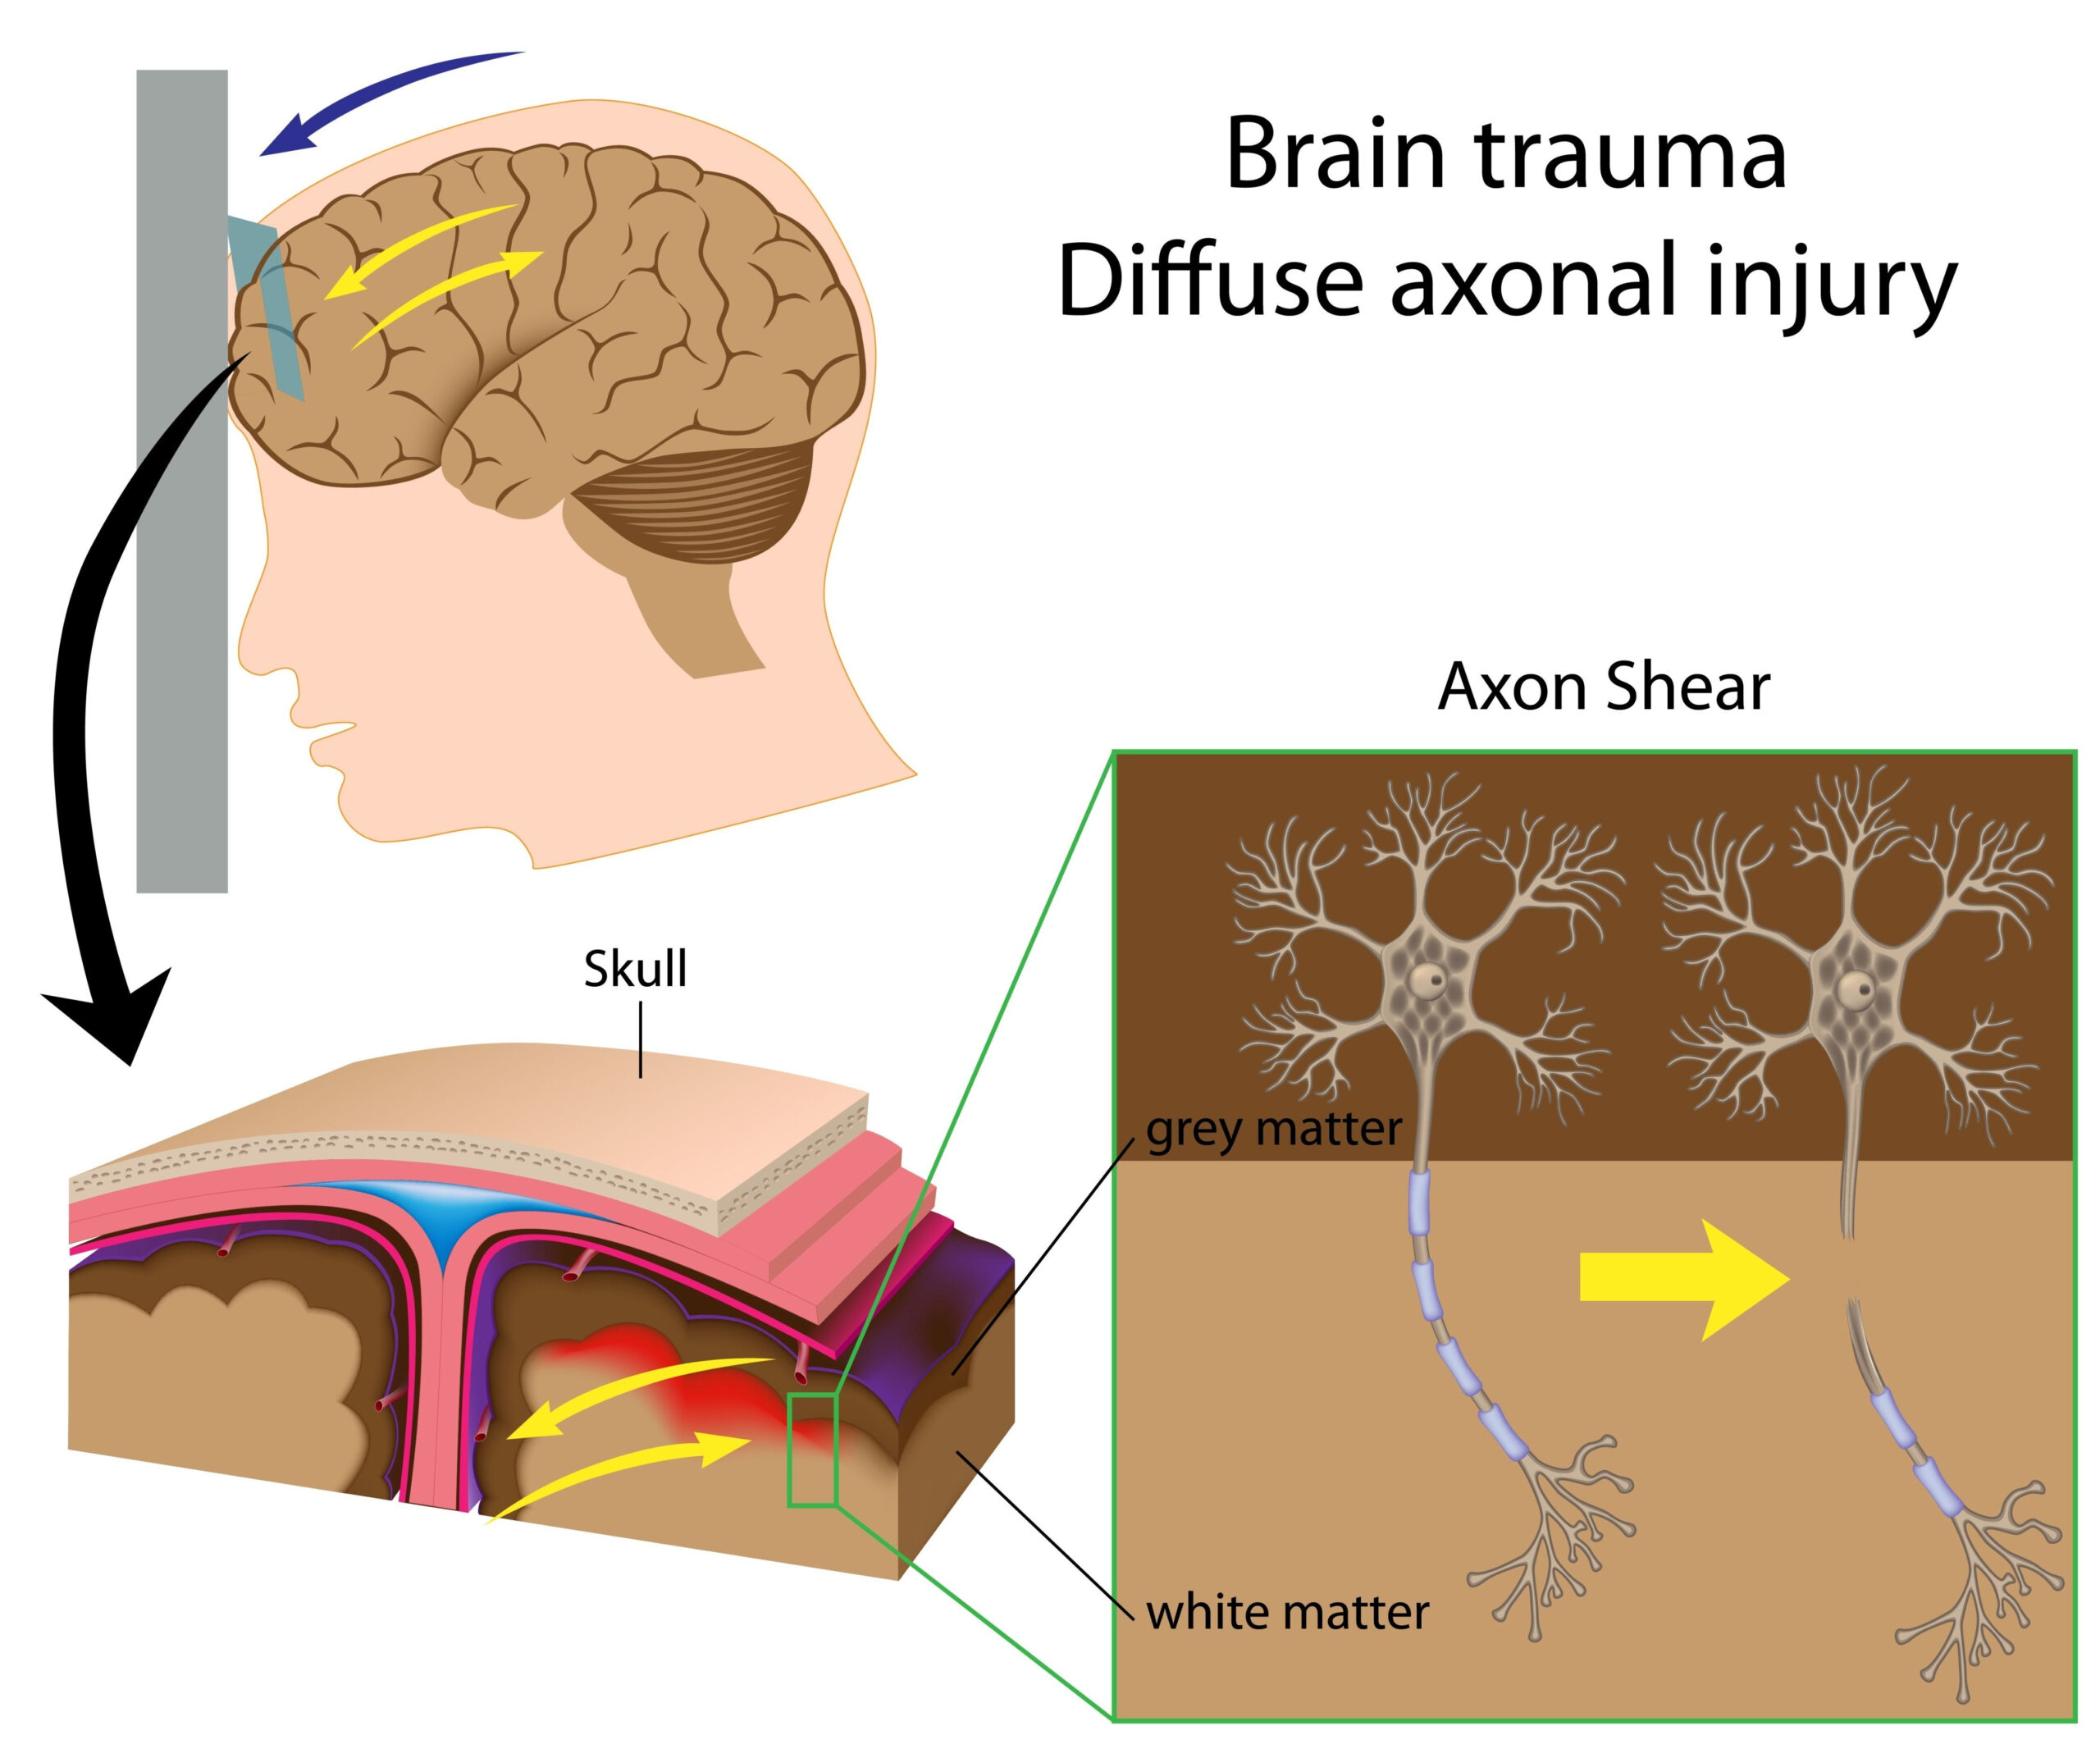
Mild traumatic brain injury (mTBI), often referred to as a concussion, is a prevalent condition among adolescents, commonly resulting from sports injuries, falls, or accidents. Understanding the mental health ramifications following mTBI is crucial, as adolescents are particularly vulnerable to a range of psychological issues that may arise post-injury. Various studies have indicated a correlation between mTBI and increased risks of both acute and chronic mental health disorders, including depression, anxiety, and behavioral issues. This is of significant concern since the adolescent period is marked by considerable neurodevelopmental changes, making the impact of brain injuries particularly pronounced.
The diagnostic codes utilized in electronic health records (EHR) serve as essential tools for tracking health trends and patterns. These codes help identify and categorize conditions and treatments related to mTBI and subsequent mental health outcomes. However, there exists a gap in understanding how effectively these codes capture the full spectrum of mental health issues that may develop following mTBI. Furthermore, the underreporting or misclassification of mental health disorders in adolescents could lead to inadequate care and support systems being established. Consequently, examining the current diagnostic coding practices is vital for improving health outcomes for this vulnerable population.
The increased prevalence of mTBI in adolescents, combined with the potential for long-term mental health issues, underlines the urgency of this investigation. By analyzing EHR data, we can better assess the incidence of mental health conditions post-mTBI and identify any disparities in healthcare access and treatment. Thus, the rationale behind this study is to illuminate the relationship between mTBI and adolescent mental health, emphasizing the need for accurate diagnosis and intervention strategies to enhance patient care in clinical settings.
Data Collection and Analysis
Data collection for this study involved a comprehensive approach to ensure the reliability and validity of the findings. We utilized electronic health records (EHRs) from a sizable cohort of adolescents who had been diagnosed with mild traumatic brain injury (mTBI). The EHRs were sourced from multiple healthcare institutions to enhance the diversity of the sample population and facilitate a broader analysis across different demographics.
The first step in the data collection process was to identify patients aged 12 to 18 years who presented with an mTBI between specific dates. We employed the standardized diagnostic codes defined by the International Classification of Diseases (ICD) to retrieve relevant cases from the EHRs. These codes enabled us to filter out individuals with confirmed mTBI while excluding those with more severe brain injuries or pre-existing mental health conditions that could confound our findings.
Once the targeted cohort was established, we reviewed the EHRs for subsequent mental health diagnoses recorded following the injury. The analysis focused on common mental health disorders, including anxiety disorders, mood disorders (such as depression), and behavioral problems. Additionally, we examined the frequency of follow-up visits related to mental health care to assess engagement with healthcare services post-injury.
The analysis applied statistical methods to identify correlations between mTBI and the incidence of mental health conditions. We employed logistic regression models to evaluate the relationship between variables such as age, gender, and socio-economic status and the likelihood of developing mental health issues. Adjustments were made for potential confounders to isolate the impact of mTBI on mental health outcomes.
Moreover, we performed subgroup analyses to further dissect the data by age group and injury mechanism, understanding that different factors may influence mental health outcomes across varying contexts. This multifaceted approach allowed for a nuanced understanding of how mTBI affects adolescents differently based on a myriad of personal and environmental factors. In conjunction with quantitative analysis, qualitative assessments through patient interviews and focus group discussions were incorporated to gain insights into personal experiences and perceptions regarding mental health following mTBI.
Data integrity and privacy were paramount throughout this process. All EHR data were anonymized to protect patient confidentiality, and the study adhered to ethical standards set forth by institutional review boards (IRBs). This rigorous methodology provided a robust foundation for our findings, ensuring that the analysis represented a comprehensive view of the landscape of adolescent mental health post-mTBI.
Results and Interpretation
The findings from our analysis of the electronic health records (EHR) revealed significant patterns regarding the prevalence of mental health disorders following mild traumatic brain injury (mTBI) among adolescents. In the cohort analyzed, a notable percentage of individuals who sustained an mTBI were subsequently diagnosed with various mental health conditions, underscoring the potential neuropsychological impact of such injuries.
Statistical evaluations indicated a strong correlation between mTBI and the development of anxiety and mood disorders. Specifically, adolescents diagnosed with mTBI exhibited an increased likelihood of receiving a subsequent diagnosis of anxiety disorders, with an incidence rate of approximately 25%. This was particularly pronounced in individuals with a history of prior concussions, suggesting a cumulative risk effect where previous injuries exacerbate mental health vulnerabilities.
In terms of mood disorders, the data showed that around 15% of the adolescents with mTBI were later diagnosed with depression within one year post-injury. This highlights the urgent need for surveillance and monitoring of mental health outcomes following an mTBI. Moreover, the analysis further revealed that boys and girls exhibited differing patterns in mental health diagnoses, with girls showing a higher propensity for anxiety-related disorders, while boys were more frequently diagnosed with behavioral issues. This gender disparity aligns with existing literature that suggests varying responses to brain injuries based on gender, likely influenced by biological and social factors.
Additionally, our study examined the relationship between socio-economic status and mental health outcomes post-mTBI. Results indicated that adolescents from lower socio-economic backgrounds were disproportionately affected, displaying a higher prevalence of both mental health diagnoses and reduced engagement with follow-up mental health services. This finding raises concerns about access to appropriate care and the potential barriers faced by these adolescents in receiving timely mental health support.
Our qualitative analyses yielded valuable insights into the subjective experiences of adolescents following mTBI. Through interviews, many participants expressed feelings of isolation and challenges in coping with their mental health issues, emphasizing the impact of stigma related to mental health. These personal accounts illustrate the necessity for tailored mental health interventions that resonate with adolescents’ unique experiences and perceptions.
An essential aspect of our findings involved the examination of follow-up care patterns. Despite the high incidences of mental health issues post-injury, only a fraction of adolescents attended follow-up mental health appointments. This gap in care suggests potential systemic issues within the healthcare framework that may hinder adolescents from accessing needed mental health services. Interventions aimed at improving follow-up care and enhancing communication between healthcare providers and adolescents are crucial to address this concern.
The results indicate a clear association between mTBI and subsequent mental health disorders in adolescents, with multifaceted factors influencing the extent of this impact. The data calls for enhanced awareness among healthcare providers regarding the mental health risks associated with mTBI and the implementation of proactive measures to support affected adolescents adequately. Addressing these issues can foster improved health outcomes and promote resilience in this vulnerable population.
Future Directions and Recommendations
The implications of our findings on the mental health risks associated with mild traumatic brain injury (mTBI) in adolescents necessitate a multifaceted approach to address the gaps in care and support for this vulnerable population. One of the primary recommendations is the establishment of standardized protocols for monitoring mental health outcomes following an mTBI. This could involve implementing routine mental health screenings at follow-up appointments after an injury, utilizing validated assessment tools that can effectively identify early signs of anxiety, depression, and behavioral disorders. Without consistent monitoring, many adolescents may go undiagnosed and untreated, exacerbating their mental health challenges.
Education and training for healthcare professionals are crucial to recognize the signs of mental health disorders in adolescents post-mTBI. Providers should be equipped with knowledge about the potential neuropsychological impacts of mTBI, enabling them to engage in informed discussions with patients and their families regarding mental health. This emphasis on education can encourage open dialogues and reduce stigma surrounding mental health issues, which is particularly significant in adolescent populations.
Moreover, it is essential to enhance access to mental health resources, particularly for adolescents from lower socio-economic backgrounds. Initiatives could include integrating mental health services into existing pediatric care settings, thereby providing easier access and reducing barriers to care. Developing community-based programs that focus on mental health literacy and support can also empower adolescents and their families to seek help early, promoting resilience and recovery.
In light of the gender disparities observed in our study, tailored interventions that consider the unique needs of adolescents based on their gender should be developed. Programs aimed at educating both boys and girls about the impact of mTBI on mental health can facilitate early intervention and create supportive environments that encourage discussions around mental well-being.
Research must continue to track and analyze the long-term mental health outcomes of adolescents post-mTBI. Longitudinal studies would provide valuable insights into the progression of mental health issues over time and the efficacy of various intervention strategies. Investigating the potential protective factors that may mitigate the risk of developing mental health disorders after mTBI is equally important, as these insights could inform prevention strategies.
Lastly, fostering collaboration between schools, healthcare providers, and community resources is vital to creating a supportive infrastructure for adolescents recovering from mTBI. Schools should be equipped with resources to support students returning from injuries, ensuring that they have access to counseling services and academic accommodations as needed. This collaborative approach can create a seamless support system that addresses both the physical and mental health needs of adolescents post-injury, ultimately promoting their overall well-being.