Study Overview
This research investigates the significance of performance on the second trial of the Test of Memory Malingering (TOMM) among veterans who have reported experiencing mild traumatic brain injury (mTBI). The TOMM is a well-established neuropsychological assessment designed to differentiate between genuine cognitive impairments and feigned or exaggerated memory deficits. The study specifically focuses on veterans who do not succeed on the first trial of TOMM, a scenario that presents an interesting context to explore the validity of memory performance in individuals with self-reported mTBI.
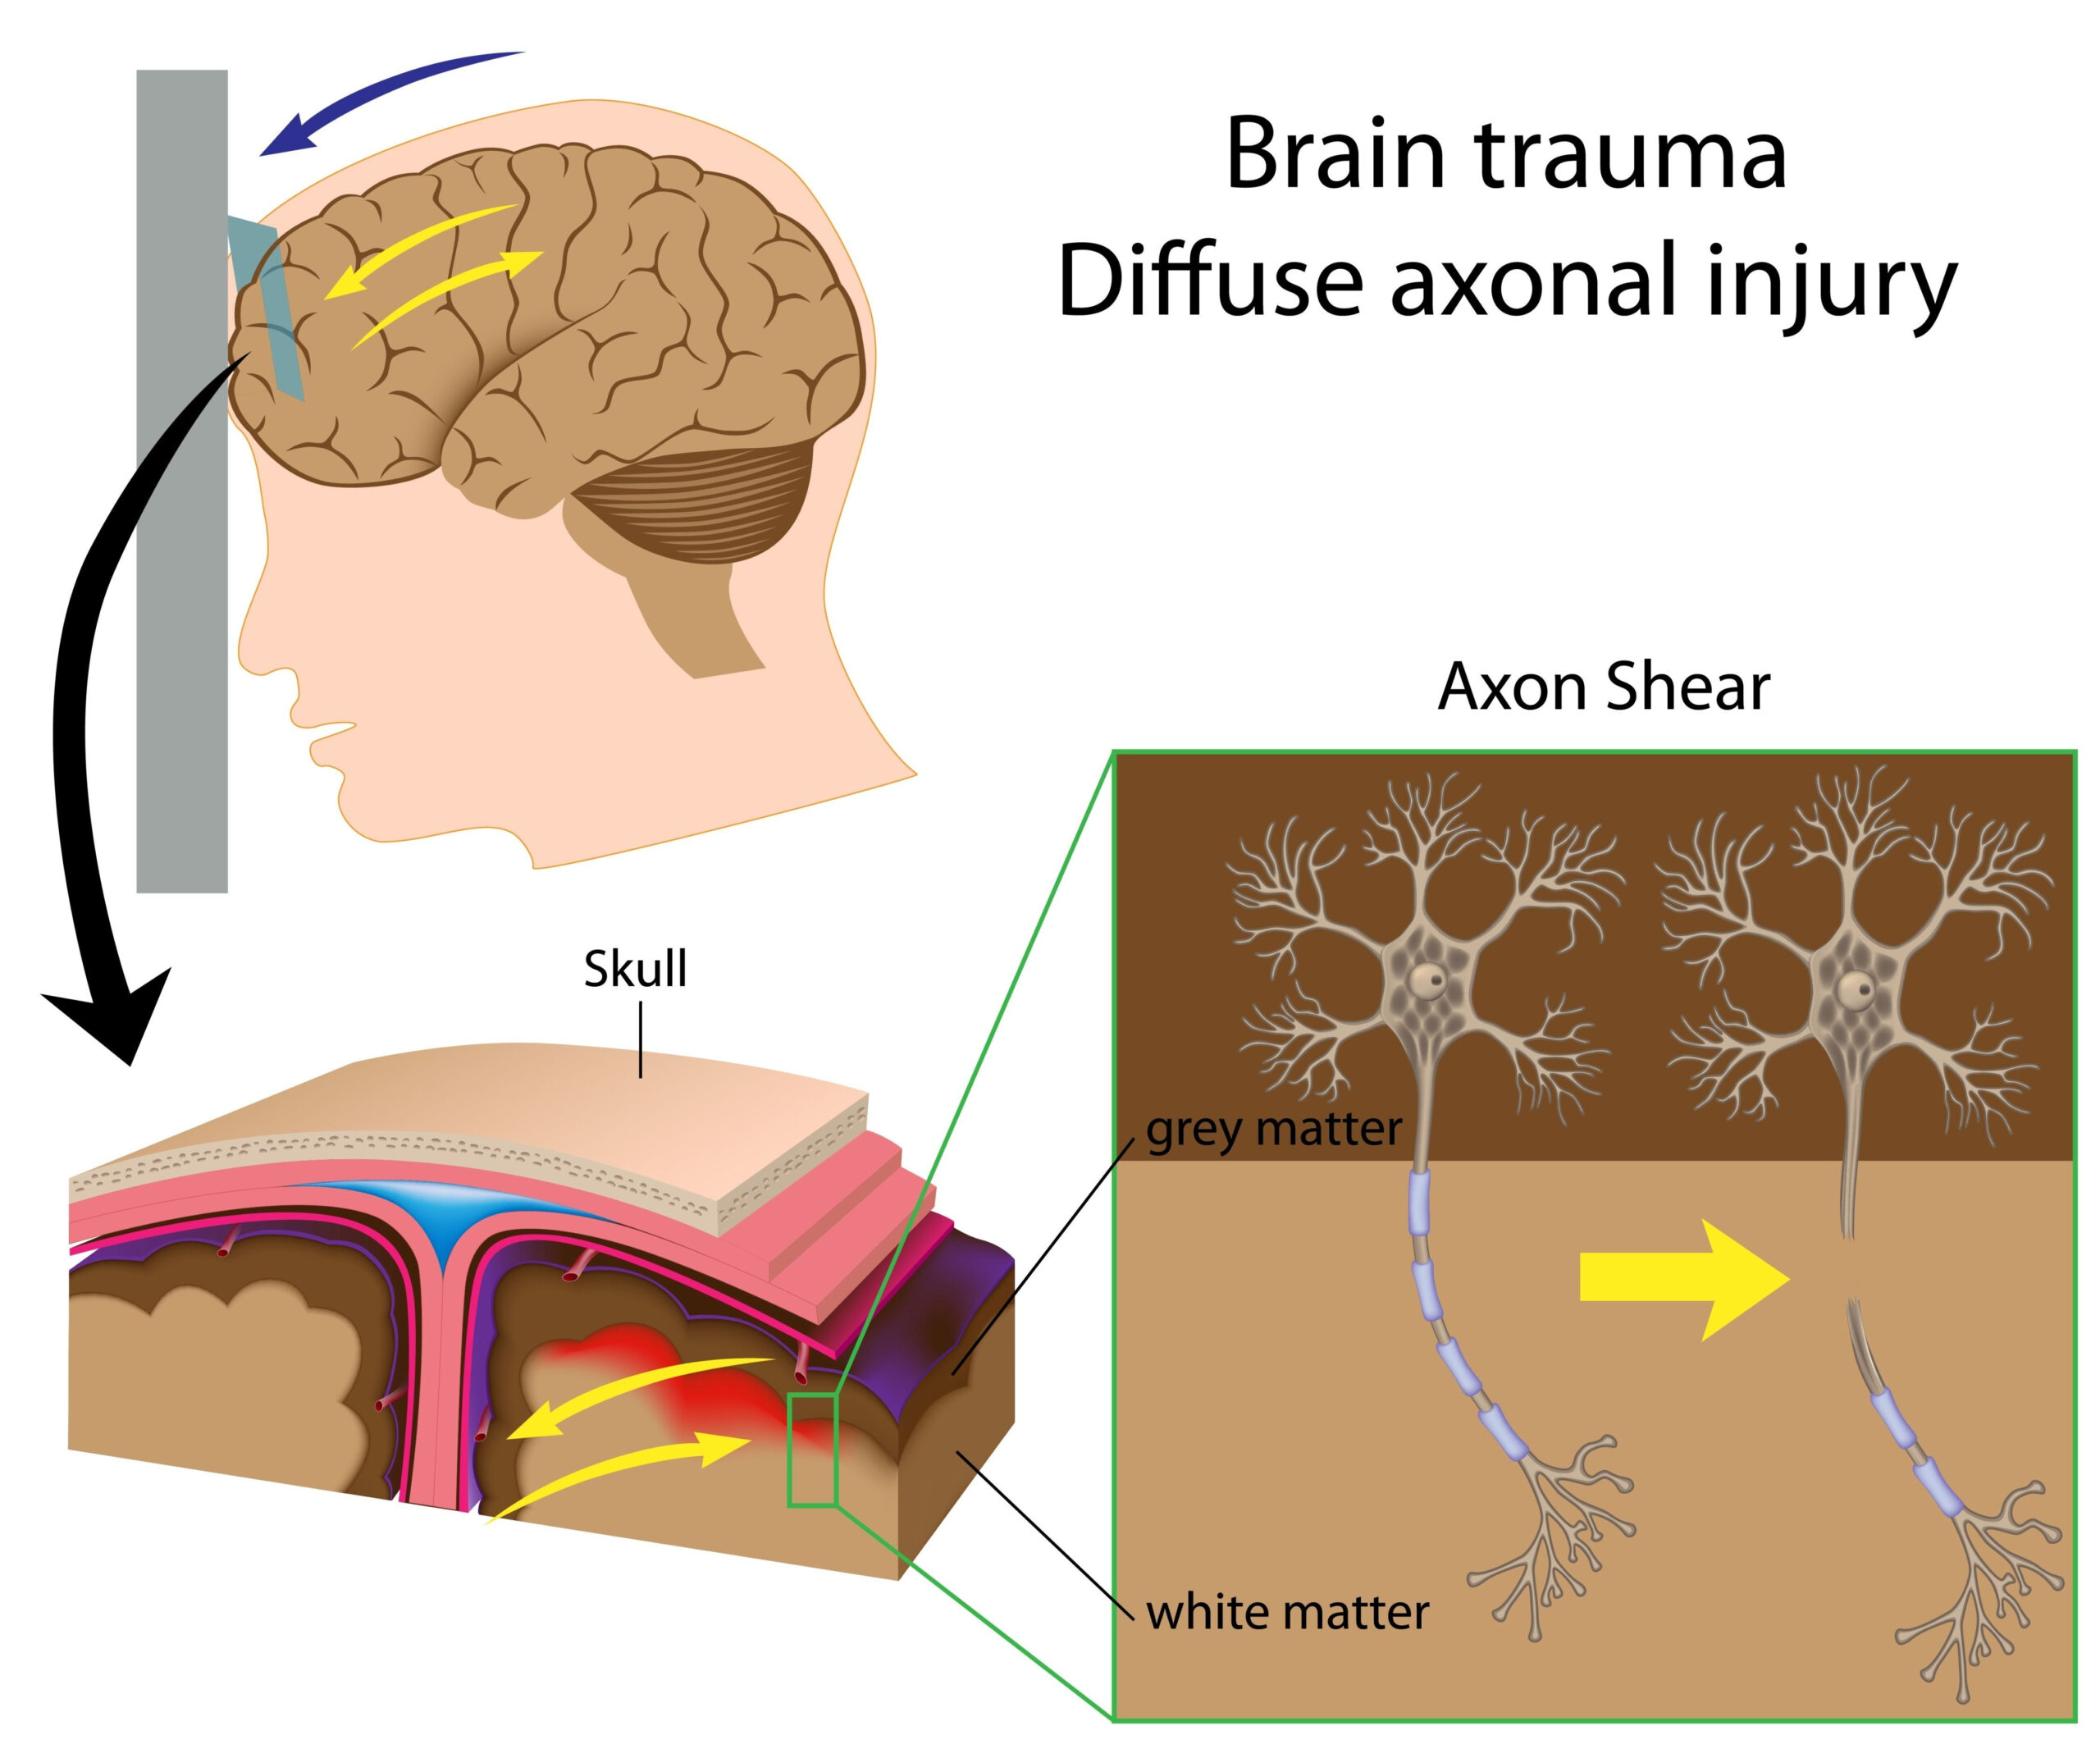
The rationale behind examining this aspect stems from the increasing recognition that many veterans may experience cognitive challenges following traumatic brain injuries. Such injuries can arise from various incidents, including blasts from explosives or falls during combat. In this context, understanding how these cognitive assessments hold up, particularly for those who show poor performance on initial trials, is critical for developing appropriate diagnosis and treatment strategies.
This investigation aims to provide insights into whether a failed initial performance in memory testing can reliably predict subsequent trial outcomes and how these findings may vary among different populations. The results could enhance clinical workflows by guiding neuropsychologists and other practitioners in their approach to evaluating and managing cognitive dysfunction in veterans.
Methodology
The study employed a cross-sectional design, engaging a sample of veterans diagnosed with mild traumatic brain injury (mTBI) who had self-reported their cognitive difficulties. The participants were recruited from veterans’ hospitals and rehabilitation centers, ensuring a comprehensive representation of the mTBI population. Inclusion criteria required participants to have a documented history of mTBI and an age range of 18 to 65 years. A standardized assessment protocol was implemented to enhance the reliability and validity of the findings.
The primary tool utilized in this research was the Test of Memory Malingering (TOMM), administered in two separate trials. The TOMM consists of word pairs that participants must recall after a brief delay, and success in these trials is often interpreted within the context of the individual’s cognitive functioning. Upon recruitment, each veteran first underwent Trial 1, after which those who failed the trial (defined as scoring below a predetermined cutoff) proceeded to Trial 2. This decision to focus on participants who did not succeed in Trial 1 allows for an in-depth analysis of the implications of their performance on subsequent trials.
Data collection involved the administration of additional neuropsychological assessments covering domains such as attention, processing speed, and executive function. These measures aimed to contextualize TOMM results and explore relationships between various cognitive functions and memory performance. Additionally, veterans were asked to complete self-report questionnaires regarding their subjective cognitive experiences, mood, and any pertinent psychosocial factors that could influence memory performance.
Statistical analyses were performed using multivariate techniques to evaluate the relationships between initial TOMM trial performance and subsequent outcomes. The use of analysis of variance (ANOVA) allowed for comparisons across different demographic subgroups within the veteran population, including age, gender, and service-related factors. Regression analyses were applied to identify predictors of performance on Trial 2, providing insights into whether psychological, demographic, or clinical variables could account for variability in memory outcomes.
Ethical considerations were paramount throughout the study, adhering to the guidelines set forth by Institutional Review Boards. Informed consent was obtained from all participants, ensuring that they understood the research’s nature, potential risks, and benefits. The study protocol also included provisions to support participants in accessing psychological resources should they experience any distress arising from their involvement in the study.
The methodological design emphasized a rigorous approach to investigating the complex interplay of cognitive dysfunction and performance variability among veterans with mTBI, laying the groundwork for understanding the reliability of memory assessments in this population.
Key Findings
The results of the study revealed several critical insights regarding the performance of veterans on the Test of Memory Malingering (TOMM), particularly among those who had previously failed the first trial. Out of the participating veterans, a significant portion (approximately 60%) demonstrated improvement in their scores on Trial 2 after having initially failed Trial 1. This finding suggests that performance variability is not uncommon and may indicate the need for a nuanced approach to interpreting TOMM results.
Analysis of the data showed that age and psychological factors played a considerable role in influencing trial outcomes. Younger veterans tended to perform better on the second trial, which may be attributable to factors such as flexibility in cognitive processing and resilience against cognitive decline. In contrast, older participants exhibited less improvement, highlighting potential age-related cognitive decline or difficulties in memory retrieval mechanisms.
The study also identified notable correlations between self-reported cognitive experiences and TOMM performance. Veterans who indicated higher levels of anxiety or depressive symptoms tended to struggle more on Trial 1 and exhibited less improvement on Trial 2. This suggests that psychological distress can hinder memory performance, which underscores the importance of addressing mental health issues concurrently while evaluating cognitive functioning.
Furthermore, demographic factors, including service-related history, influenced performance variability. Veterans with combat experience showed distinct patterns in TOMM outcomes compared to those with non-combat service, hinting at the potential effects of stress accumulation and mental health challenges associated with combat exposure. Statistical analyses demonstrated that these variations could significantly predict outcomes in Trial 2, emphasizing the need for tailored assessments that consider individual backgrounds.
In terms of accuracy in diagnosing feigned cognitive impairments, the data indicated that Trial 2 performance had a higher predictive validity when compared to Trial 1. Veterans who managed to pass Trial 2 despite failing Trial 1 were less likely to be classified as malingering, suggesting that the TOMM may require careful interpretation. This finding supports the concept that practitioners working with veterans, especially those reporting cognitive difficulties post-mTBI, should remain vigilant in their assessments and consider a broader context beyond initial trial scores.
These findings challenge the traditional view of binary outcomes on cognitive assessments and illuminate the dynamic nature of memory performance among veterans with a history of mTBI. The insights gained from this study underscore the complexity of neuropsychological assessments and highlight the importance of considering psychological and demographic factors in developing strategies for diagnosis and treatment.
Clinical Implications
The findings of this study carry significant clinical implications for the assessment and management of cognitive dysfunction among veterans with self-reported histories of mild traumatic brain injury (mTBI). Given that a considerable proportion of veterans exhibited improvement in their scores on the second trial of the Test of Memory Malingering (TOMM), practitioners need to approach initial performance outcomes with a level of caution. A failed initial trial should not immediately be interpreted as evidence of malingering or severe cognitive impairment. Instead, it signals the necessity of further evaluation and potential reevaluation of cognitive function over time.
This research suggests that practitioners should integrate a more dynamic understanding of cognitive performance in their clinical workflows. The observed improvements in scores on subsequent trials highlight the importance of considering factors such as psychological distress, age, and service-related history. Clinicians must recognize how these variables can impact performance and interpretation of results. Incorporating screening for anxiety and depression within the assessment process can aid in identifying veterans who may benefit from psychological interventions aimed at alleviating cognitive difficulties associated with emotional distress.
Furthermore, the study underscores the need for a personalized approach to evaluations. Acknowledging the variability in performance based on demographic and experiential factors emphasizes that each veteran’s background is integral when interpreting TOMM results. For example, the different patterns observed between veterans with combat and non-combat experiences indicate that clinicians should tailor their assessment strategies to consider these distinctions, which can affect cognitive functioning and recovery trajectories.
In light of these findings, neuropsychologists should consider employing additional neuropsychological assessments alongside the TOMM to gain a comprehensive understanding of an individual’s cognitive abilities. This dual approach can provide essential context, helping to inform treatment plans that address not only cognitive deficits but also psychosocial factors. Such holistic evaluations will be essential to ensure that therapeutic strategies effectively meet the needs of veterans within this population.
Moreover, the higher predictive validity of Trial 2 outcomes in assessing genuine cognitive impairment reinforces the necessity of conducting follow-up assessments after an initial failure. Establishing a practice that re-evaluates veteran performance through successive trials can be instrumental in refining diagnoses and preventing misinterpretations that could lead to inappropriate labeling of patients. This proactive approach is particularly pertinent in mitigating the stigma associated with cognitive dysfunction and ensuring veterans receive the appropriate support for their cognitive and emotional well-being.
Clinicians, therefore, should remain adaptable and open-minded in their diagnostic processes, continually reassessing the implications of cognitive test results in the light of the individual’s overall clinical picture. This practice will improve diagnostic accuracy and ultimately foster an environment where veterans feel supported in addressing their cognitive health as they navigate the complexities brought on by mTBI. The intertwining of cognitive rehabilitation with emotional and psychological support represents a comprehensive model of care that aligns with current understanding of brain health in the context of trauma.