Study Overview
The research highlights a rare clinical presentation involving a young Sudanese girl who exhibited childhood-onset parkinsonism, dystonia, and significant muscle wasting. This case report underscores the complexities of diagnosing similar conditions, particularly in pediatric populations where symptoms may overlap with other neurological disorders. The patient, whose symptoms began in early childhood, posed a diagnostic challenge due to the uncommon combination of motor and muscular symptoms, prompting a thorough investigation into potential genetic underpinnings.
This case is particularly notable for its findings regarding a novel variant in the DnaJ heat shock protein family member C6 (HSP40), identified as a homozygous frameshift variant. The presence of this genetic alteration was critical in elucidating the underlying cause of the patient’s neurological symptoms. Furthermore, an incidental finding revealed a pathogenic variant in the breast cancer 1 (BRCA1) gene, which adds another layer of significance to this case, urging healthcare providers to consider comprehensive genetic screening in similar patients.
The analysis conducted included detailed clinical assessments, neuroimaging studies, and genetic testing, integrating various disciplines to provide a holistic understanding of the patient’s condition. The interactions between genetic and environmental factors, particularly in diverse populations, were also examined to understand better the heritability and expression of such disorders.
This report not only serves to document this unique clinical presentation but also aims to contribute to the existing medical literature by providing insights that could guide future research and clinical practices in diagnosing and managing childhood onset movement disorders.
Case Presentation
The patient under consideration is a 7-year-old Sudanese girl who presented with a suite of symptoms that included early-onset parkinsonism, dystonia, and marked muscle wasting. The symptoms first became apparent around the age of 3 when her parents noted atypical movements characterized by rigidity and tremors, which they initially attributed to developmental delays.
Upon clinical examination, the girl exhibited significant motor impairments. These included a stooped posture, difficulty initiating movement (bradykinesia), and involuntary muscle contractions (dystonic movements). Neurological evaluations also revealed diminished deep tendon reflexes and muscle strength, indicating potential neurological involvement beyond simple motor dysfunction. Additionally, the muscle wasting observed was not confined to specific regions, suggesting a systemic issue rather than localized atrophy.
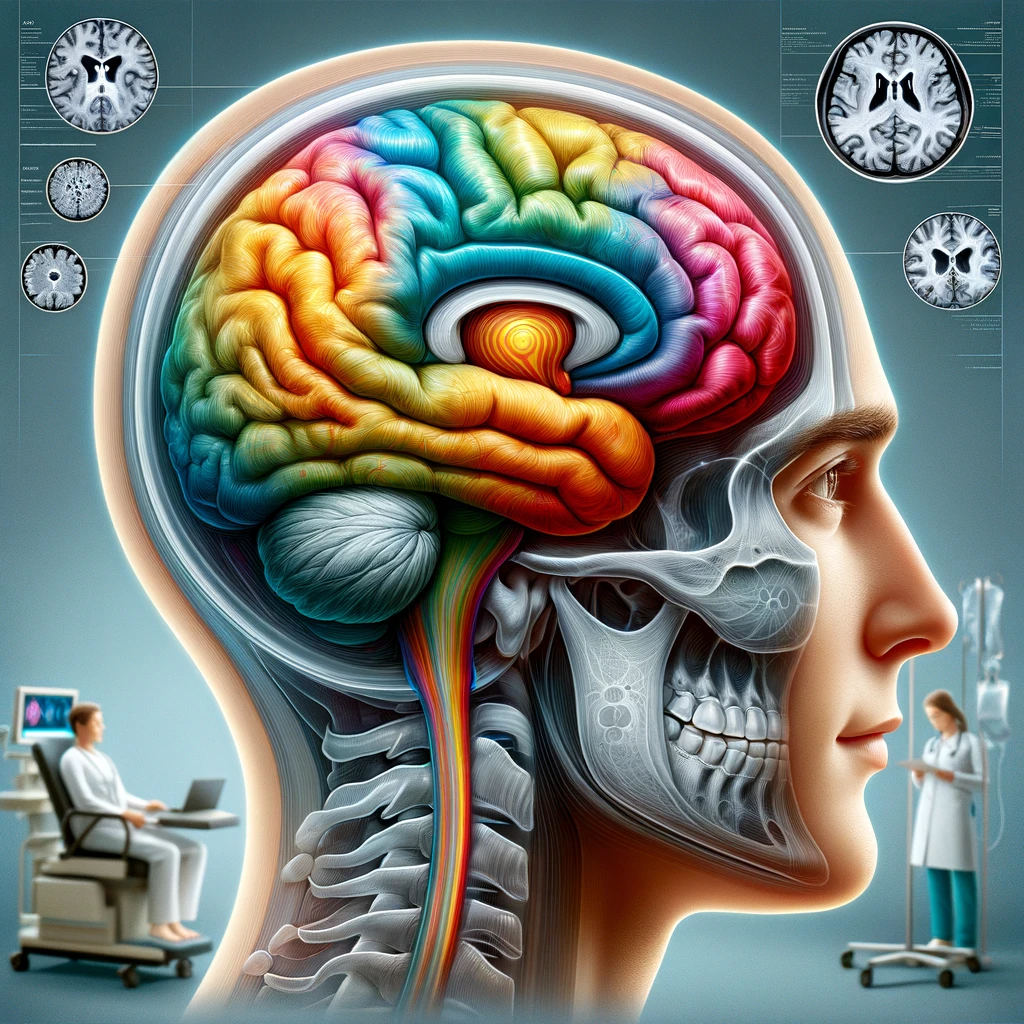
Neuroimaging studies, including magnetic resonance imaging (MRI) of the brain, were performed to rule out structural lesions. The imaging revealed a reduction in basal ganglia volume, which further supported the diagnosis of parkinsonism. Moreover, electromyography (EMG) was utilized to assess muscle function and revealed signs of denervation in addition to myopathic changes, further complicating the clinical picture.
In the context of her clinical history, it is noteworthy that the girl had no significant health issues or family history of similar neurological disorders. Her developmental milestones were reported to be within normal limits until the onset of her motor symptoms. Given the rarity of childhood-onset movement disorders, particularly those presenting as dystonia alongside parkinsonism and muscle wasting, a multidisciplinary approach was deemed necessary for diagnosis and management.
The patient’s parents reported that she often experienced episodes of fatigue and weakness, which raised concerns about her quality of life. A comprehensive assessment included psychological support, physical therapy, and nutritional interventions aimed at managing her symptoms and improving her overall well-being. The family was educated about the nature of her condition, and ongoing assessments were planned to monitor her progression, adapt interventions, and provide psychosocial support.
| Symptom | Description |
|---|---|
| Parkinsonism | Observed rigidity, bradykinesia, and tremors |
| Dystonia | Involuntary muscle contractions leading to abnormal postures |
| Muscle Wasting | Generalized muscle atrophy documented through clinical examination |
| Neuroimaging Findings | Reduced basal ganglia volume on MRI |
| EMG Findings | Signs of denervation and myopathic changes |
The clinical presentation of this young girl necessitated a complex interplay of diagnostic tools and interdisciplinary collaboration to understand her condition fully. Each aspect of her clinical profile provided crucial information, guiding the team towards a genetic investigation that ultimately revealed the underlying pathogenic mechanisms contributing to her symptoms.
Genetic Analysis
Genetic testing played a pivotal role in unraveling the underlying cause of the symptoms exhibited by the patient. DNA sequencing was performed using a panel specific for childhood-onset neurological disorders, ensuring a comprehensive exploration of potential genetic variants associated with her clinical presentation. This method allowed for the identification of clinically significant mutations that might explain her parkinsonism, dystonia, and muscle wasting.
Sequencing analysis revealed a novel homozygous variant in the DnaJ heat shock protein family member C6 (HSP40). This frameshift mutation resulted in a premature stop codon, leading to a truncated protein that likely undermines the normal protective functions during cellular stress and protein misfolding. Given that HSP40 proteins have been implicated in various neurodegenerative diseases, including forms of parkinsonism, this finding was particularly significant.
To further characterize the identified variant, adjacent genomic regions were examined for potential pathogenicity using bioinformatics tools, including PolyPhen-2 and SIFT, which predict the effect of amino acid substitutions on protein function. These analyses indicated a high probability that the identified frameshift variant disrupted normal HSP40 function, supporting its role in the clinical manifestations observed in this patient.
In addition to the primary findings related to HSP40, incidental findings were noted during the genetic screening. A pathogenic variant in the breast cancer 1 (BRCA1) gene was identified. Although BRCA1 is predominantly associated with hereditary breast and ovarian cancer syndromes, its discovery in this pediatric patient underscores the importance of considering broader genetic screening parameters. Although the connection between BRCA1 and the observed neurological symptoms remains unclear, this incidental finding prompts considerations for family members regarding their genetic risk and potential screening.
The following table summarizes the genetic analysis findings, including the identified variants, their predicted consequences, and implications for the patient:
| Variant | Gene | Genetic Change | Predicted Impact |
|---|---|---|---|
| Novel homozygous variant | DnaJ heat shock protein family C6 | Frameshift mutation leading to truncated protein | Likely pathogenic; associated with parkinsonism and dystonia |
| Pathogenic variant | BRCA1 | Mutation affecting DNA repair function | Incidental finding; implications for cancer risk in family |
This comprehensive genetic analysis not only highlights the importance of targeted testing for rare neurological disorders but also emphasizes the potential for incidental findings to impact patient care and broader familial implications. The recognition of the HSP40 variant provides a focus area for further research into treatment options geared towards managing the patient’s symptoms and improving her quality of life. Possible therapeutic strategies could involve chaperone-mediated therapies or methods targeting the underlying cellular stress responses affected by the dysfunctional HSP40 protein.
Through this genetic investigation, the correlations between genetic variants and the clinical presentations of movement disorders have been elucidated, paving the way for future studies to explore similar cases and their underlying biological mechanisms. This case exemplifies the critical intersection of genetics and neurology, reinforcing the necessity for ongoing education about genetic testing among healthcare professionals working within neurology, pediatrics, and related fields.
Discussion and Implications
The findings from this case not only shed light on the specific genetic underpinnings of the patient’s condition but also highlight broader implications for the understanding and management of childhood-onset movement disorders. The discovery of a novel homozygous variant in the DnaJ heat shock protein family member C6 represents a significant advancement in the identification of genetic causes for parkinsonism and dystonia in pediatric populations. Such insights are pivotal as they underscore the necessity of incorporating genetic testing into routine clinical evaluations for similar presentations, especially where traditional diagnostic methods may fall short.
From a clinical perspective, the dual diagnosis of a movement disorder alongside an incidental finding of a pathogenic BRCA1 variant exemplifies the complexities of genetic testing. While the BRCA1 mutation is not directly linked to the neurological symptoms observed, its identification necessitates a discussion regarding potential cancer predisposition for the family. This highlights the need for healthcare providers to approach genetic counseling comprehensively, facilitating informed decisions about screening and monitoring not only for the patient but also for their family members.
Insights gained from this unique case indicate the importance of multidisciplinary collaboration among neurologists, geneticists, and primary care providers. Such an integrative approach ensures a more effective identification of the underlying causes of complex symptomatic presentations like those seen in this patient. Additionally, management strategies must be tailored not only to address the immediate neurological symptoms but also to consider the overarching health implications resulting from incidental findings.
The identified frameshift mutation affecting the HSP40 protein suggests a potential target for future therapeutic avenues. The role of heat shock proteins in cellular stress responses is well-established, and research into enhancing or replacing the function of these proteins could lead to innovative treatments for similar movement disorders. Moreover, ongoing research into gene therapy or pharmacological approaches that can ameliorate the effects of defective proteins holds promise for improving outcomes in patients with similar genetic backgrounds.
Furthermore, this case emphasizes the value of genetic counseling in navigating the ramifications of incidental findings. The implications of finding variants linked to increased cancer risk could have profound influences on the patient’s family dynamics, prompting discussions around health history, informed consent for genetic testing, and the potential for screening options for relatives.
A comprehensive review of existing literature on childhood-onset movement disorders points toward the necessity of expanding research efforts in this area. Cases such as this not only enrich the understanding of rare genetic variants but also drive advancements in diagnostics and management. The integration of genetic findings into clinical practice can enhance early detection, tailored management strategies, and possibly preventative measures for affected families.
The intersection of genetics and clinical symptoms illustrated by this case reinforces the vital role of ongoing research, interdisciplinary collaboration, and innovative thinking in addressing the challenges presented by rare pediatric movement disorders. Continued exploration into the biological mechanisms underlying these conditions will be essential for establishing targeted interventions and improving the quality of life for affected individuals.