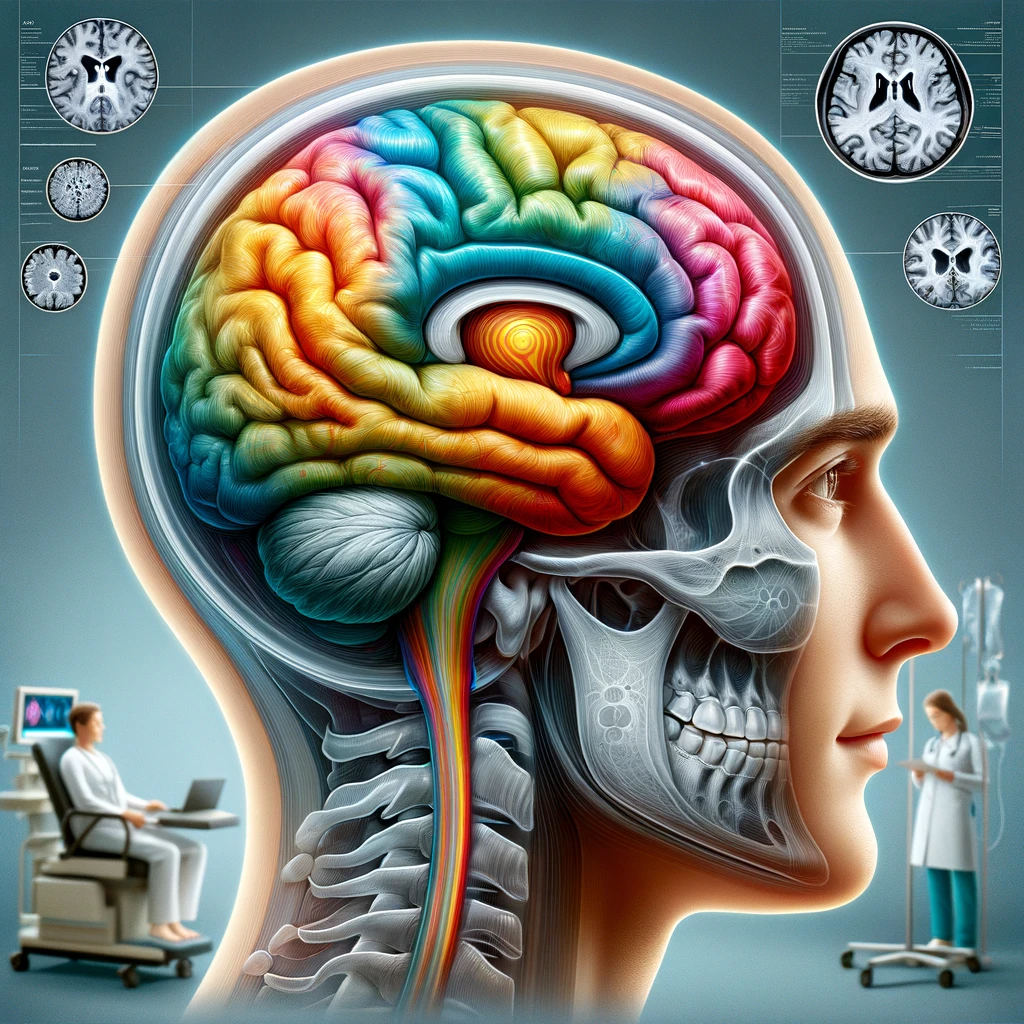
Clinical Characteristics of Focal Epilepsy
Focal epilepsy, characterized by seizures that originate in a localized region of the brain, presents with a variety of clinical features that can significantly differ among individuals. These seizures can manifest as simple focal seizures, where consciousness remains intact, or complex focal seizures, which can involve altered awareness. The clinical characteristics are not only essential for diagnosis but also play a crucial role in understanding the prognosis and treatment of the condition.
Common symptoms accompanying focal seizures include motor signs, sensory symptoms, and autonomic features. For instance, motor symptoms can range from jerking movements of a specific body part to more extensive motor involvement. Sensory symptoms might present as unusual sensations or perceptions, such as tingling or visual disturbances, which can also vary widely among patients. Furthermore, autonomic symptoms may involve changes in heart rate or respiratory patterns, indicating a more intricate interplay between the seizures and autonomic nervous system function.
Risk factors for developing focal epilepsy can include a history of head trauma, stroke, brain tumors, or cerebral infections. Additionally, comorbid conditions such as anxiety, depression, and cognitive impairments are frequently reported among patients with focal epilepsy, complicating the clinical picture. Understanding these associated features is vital for a comprehensive care approach.
| Clinical Feature | Symptoms | Comorbid Conditions |
|---|---|---|
| Motor Symptoms | Jerking movements, postictal weakness | None specifically associated |
| Sensory Symptoms | Tingling, auditory/visual hallucinations | Depression, anxiety |
| Autonomic Symptoms | Changes in heart rate, sweating | Cognitive impairments, anxiety |
The variability of symptoms highlights the necessity for careful clinical evaluation. Neurologists often rely on a thorough patient history and detailed seizure semiology to differentiate focal seizures from other seizure types and conditions, such as functional or dissociative seizures. Misdiagnosis can lead to inappropriate management strategies, underlining the importance of recognizing the nuanced features of focal epilepsy.
Diagnostic Methods and Comparison
The evaluation of patients suspected of having focal epilepsy encompasses a range of diagnostic methods, each contributing uniquely to understanding the condition. The primary tools include electroencephalogram (EEG) monitoring, advanced neuroimaging techniques such as magnetic resonance imaging (MRI), and clinical assessments based on seizure semiology. Each of these methodologies plays a vital role in confirming a diagnosis and distinguishing focal epilepsy from other seizure disorders, particularly functional and dissociative seizures.
Electroencephalogram (EEG): EEG is pivotal in diagnosing epilepsy as it records electrical activity in the brain. In focal epilepsy, EEG can reveal localized epileptiform discharges, indicating the presence of abnormal electrical activity in specific brain regions. Different EEG patterns, such as interictal spikes and sharp waves, can provide crucial insights into the focal origin of seizures. Video EEG monitoring allows for the correlation of clinical symptoms with EEG findings, offering invaluable information during seizures.
Neuroimaging Techniques: The use of MRI is essential in identifying any structural brain abnormalities that may underlie focal epilepsy. Various findings such as mesial temporal sclerosis, cortical dysplasia, or tumors can often be detected through high-resolution imaging. These findings guide further management and treatment options. While conventional MRI techniques are standard, advanced imaging modalities such as functional MRI (fMRI) or positron emission tomography (PET) can also be employed to assess brain function and identify potential seizure foci.
Clinical Assessments: Comprehensive patient history and detailed accounts of seizure semiology are fundamental in formulating a diagnosis. Clinicians assess factors such as the duration, frequency, and characteristics of seizures to distinguish between focal seizures and other types, including functional seizures. This clinical examination is often augmented by input from families or witnesses to the seizure events, thus enriching the context of the patient’s experiences.
In making a comparative analysis, the effectiveness of these diagnostic methods has been documented in various studies. A review of EEG findings indicated that about 60-70% of patients with focal epilepsy present with abnormal EEGs, underscoring its relevance. Conversely, in cases of functional seizures, EEGs often appear normal even during episodes, causing potential diagnostic confusion. An analysis of MRI results showed that approximately 30-50% of patients with focal epilepsy have identifiable structural abnormalities, while such findings are rare in functional seizure disorders.
| Diagnostic Method | Utility in Focal Epilepsy | Utility in Functional Seizures |
|---|---|---|
| EEG | Identifies abnormal electrical activity; high accuracy in diagnosis. | Typically normal; may lead to misdiagnosis. |
| MRI | Reveals structural abnormalities associated with epilepsy. | Minimal to no findings, complicating diagnosis. |
| Clinical Assessment | Provides firsthand accounts; essential for accurate diagnosis. | Important in differentiating clinical features from focal seizures. |
The comparison of these methods further emphasizes the importance of a multidisciplinary approach, as clinicians often rely on a combination of EEG, MRI, and clinical insights to formulate an accurate diagnosis. Misdiagnosis remains a significant issue; hence, refining diagnostic protocols and increasing awareness about the nuanced presentation of focal epilepsy versus functional seizures is critical for improving patient outcomes. Tailored diagnostic pathways that consider individual patient histories and symptom profiles are necessary to enhance the specificity and sensitivity of the diagnostic process.
Analysis of Initial Diagnosis Accuracy
In assessing the accuracy of initial diagnoses among patients presenting with focal epilepsy and functional or dissociative seizures, several key elements warrant consideration. Understanding the discrepancies in diagnosis not only highlights potential pitfalls but also underscores the importance of a meticulous diagnostic approach. Studies reveal that the initial diagnosis can be significantly affected by various factors, including clinical presentation, the experience level of the diagnosing physician, and the availability of advanced diagnostic modalities.
A notable challenge arises from the overlapping clinical features of focal epilepsy and functional seizures. For example, seizures of both categories can feature similar semiologic elements such as altered awareness and motor symptoms. This overlap can lead to diagnostic confusion, particularly in emergency settings where rapid assessment is essential. A study examining the rates of misdiagnosis found that as many as 30% of patients with functional seizures were initially diagnosed with epilepsy, often due to the manifestation of episodic events resembling epileptic seizures.
The accuracy of diagnoses can vary significantly based on physician specialties. Neurologists, specializing in seizure disorders, tend to achieve higher diagnostic accuracy compared to general practitioners or non-specialized clinicians. In a comparative analysis, neurologists demonstrated an almost 85% accuracy rate in correctly diagnosing focal epilepsy when utilizing comprehensive histories and EEG evidence compared to a lower accuracy rate of around 55% reported among non-specialists.
Date demonstrates that specific clinical features are more indicative of one condition over the other. For instance, focal seizures are often associated with a clear postictal state characterized by confusion and lethargy, whereas functional seizures generally lack this clear postictal phenomenon. Additionally, while focal seizures usually present with abnormal EEG findings during ictal episodes, functional seizures typically do not show this electrical activity, further complicating differentiations.
| Aspect | Focal Epilepsy | Functional Seizures |
|---|---|---|
| Postictal State | Present; confusion and lethargy reported | Absent; less defined postictal experience |
| EEG Findings | Abnormal spikes or epileptiform discharges | Typically normal; may appear unchanged during episodes |
| Diagnostic Accuracy by Specialists | 85% accuracy in diagnosis | 55% accuracy among non-specialists |
Despite the advancements in diagnostic techniques, the initial misdiagnosis can lead to inappropriate treatments that may exacerbate the patient’s condition. The consequences of such misdiagnoses can range from unnecessary pharmacological interventions to prolonged suffering and decreased quality of life for patients who may not need antiepileptic medications at all. Thus, enhancing the diagnostic process is imperative. This can include increased training opportunities focusing on the differences between seizure types, implementing standardized evaluation protocols in clinical settings, and encouraging a more collaborative approach among healthcare providers.
It becomes evident that raising awareness and facilitating continuous education regarding the nuances of seizure semiology can dramatically improve diagnostic accuracy. The development of assessment tools that can aid non-specialist physicians in recognizing key characteristics of epileptic versus non-epileptic seizures could serve as a crucial step toward mitigating initial misdiagnoses. Additionally, improving access to EEG and neuroimaging, especially in less specialized care environments, will contribute to more informed and precise clinical practices.
Recommendations for Future Practice
In order to enhance the clinical management of patients presenting with focal epilepsy and functional seizures, several strategic recommendations can be proposed. These suggestions aim to streamline diagnostic processes, improve accuracy, and ensure that patients receive appropriate care tailored to their specific conditions.
1. Multidisciplinary Approach: Forming a multidisciplinary team involving neurologists, psychiatrists, psychologists, and specialized nurses can facilitate a comprehensive evaluation of patients with complex presentations. This collaboration ensures the inclusion of various perspectives, which can aid in dissecting difficult cases where seizure semiology might overlap.
2. Continued Education and Training: It is essential to implement regular training sessions for healthcare professionals focusing on the differentiation between focal epilepsy and functional seizures. Incorporating updated research findings and advancements in diagnostic methods into educational programs can empower clinicians to recognize critical features that influence diagnosis.
3. Standardization of Diagnostic Protocols: Establishing standardized protocols for assessment can reduce variability in diagnostic accuracy across different healthcare settings. Protocols should include structured interviews, comprehensive assessments of seizure semiology, and consistent use of diagnostic tools like EEGs and MRIs to evaluate patients presenting with seizure activities.
4. Utilization of Technological Advances: Encouraging the adoption of emerging technologies such as advanced MRI features and machine learning algorithms in diagnostic imaging can enhance the detection of subtle abnormalities often overlooked in standard assessments. These advancements could help in distinguishing between epileptic and non-epileptic seizures, improving diagnostic outcomes.
5. Patient Education and Engagement: Educating patients about their condition and the differences between seizure types can empower them to take an active role in their healthcare. Involving patients in discussions about their symptoms and experiences is key in presenting a complete clinical picture, enabling more precise diagnosis and management.
6. Enhanced Access to Diagnostic Tools: Increasing accessibility to EEG and neuroimaging services in primary care settings, especially in under-resourced areas, may help reduce delays in diagnosis. Expanding access facilitates timely evaluations and decreases the likelihood of relying on less informed assessments.
7. Development of Clinical Guidelines: Establishing clear clinical guidelines that outline the steps for evaluating patients with seizure disorders can help standardize practices and improve diagnostic accuracy. These guidelines should incorporate best practices derived from both clinical evidence and expert consensus to guide healthcare providers effectively.
Implementing these recommendations not only enhances the quality of care for individuals with seizure disorders but also serves to alleviate the burden on healthcare systems by potentially reducing the incidence of misdiagnosis and inappropriate treatment. Continuous evaluation of the effectiveness of these strategies will be crucial in refining approaches to patient care in this complex area of neurology.