Clinical Features of Head Injuries
Head injuries in children are a significant concern due to the potential for severe outcomes. The clinical presentation of these injuries can vary widely, depending on several factors including the mechanism of injury, the age of the child, and the severity of the trauma. Common clinical features include altered consciousness, headache, vomiting, and signs of neurological deficits. It is essential to assess these symptoms carefully to guide appropriate management and intervention strategies.
One of the hallmark signs of a head injury is a change in the level of consciousness, which can range from confusion to complete unresponsiveness. This change is often quantitatively measured using the Glasgow Coma Scale (GCS), which assists clinicians in determining the severity of the brain injury. Children presenting with a low GCS score typically have a poorer prognosis and may require more intensive monitoring and intervention.
Head trauma can lead to a variety of specific symptoms based on the area of the brain that is affected. For instance, children may exhibit focal neurological deficits such as weakness in a limb, difficulty with speech, or issues with balance and coordination. These symptoms are critical indicators that can help guide diagnostics and treatment approaches. Other symptoms may include clear fluid leaking from the nose or ears, which can indicate a possible skull base fracture.
It is also important to note that children may not always display typical symptoms of head injury, particularly young children and infants who may be unable to verbally communicate their discomfort or symptoms. This necessitates a high index of suspicion and reliance on parental reports of behavioral changes, including increased irritability or lethargy, as well as physical examinations.
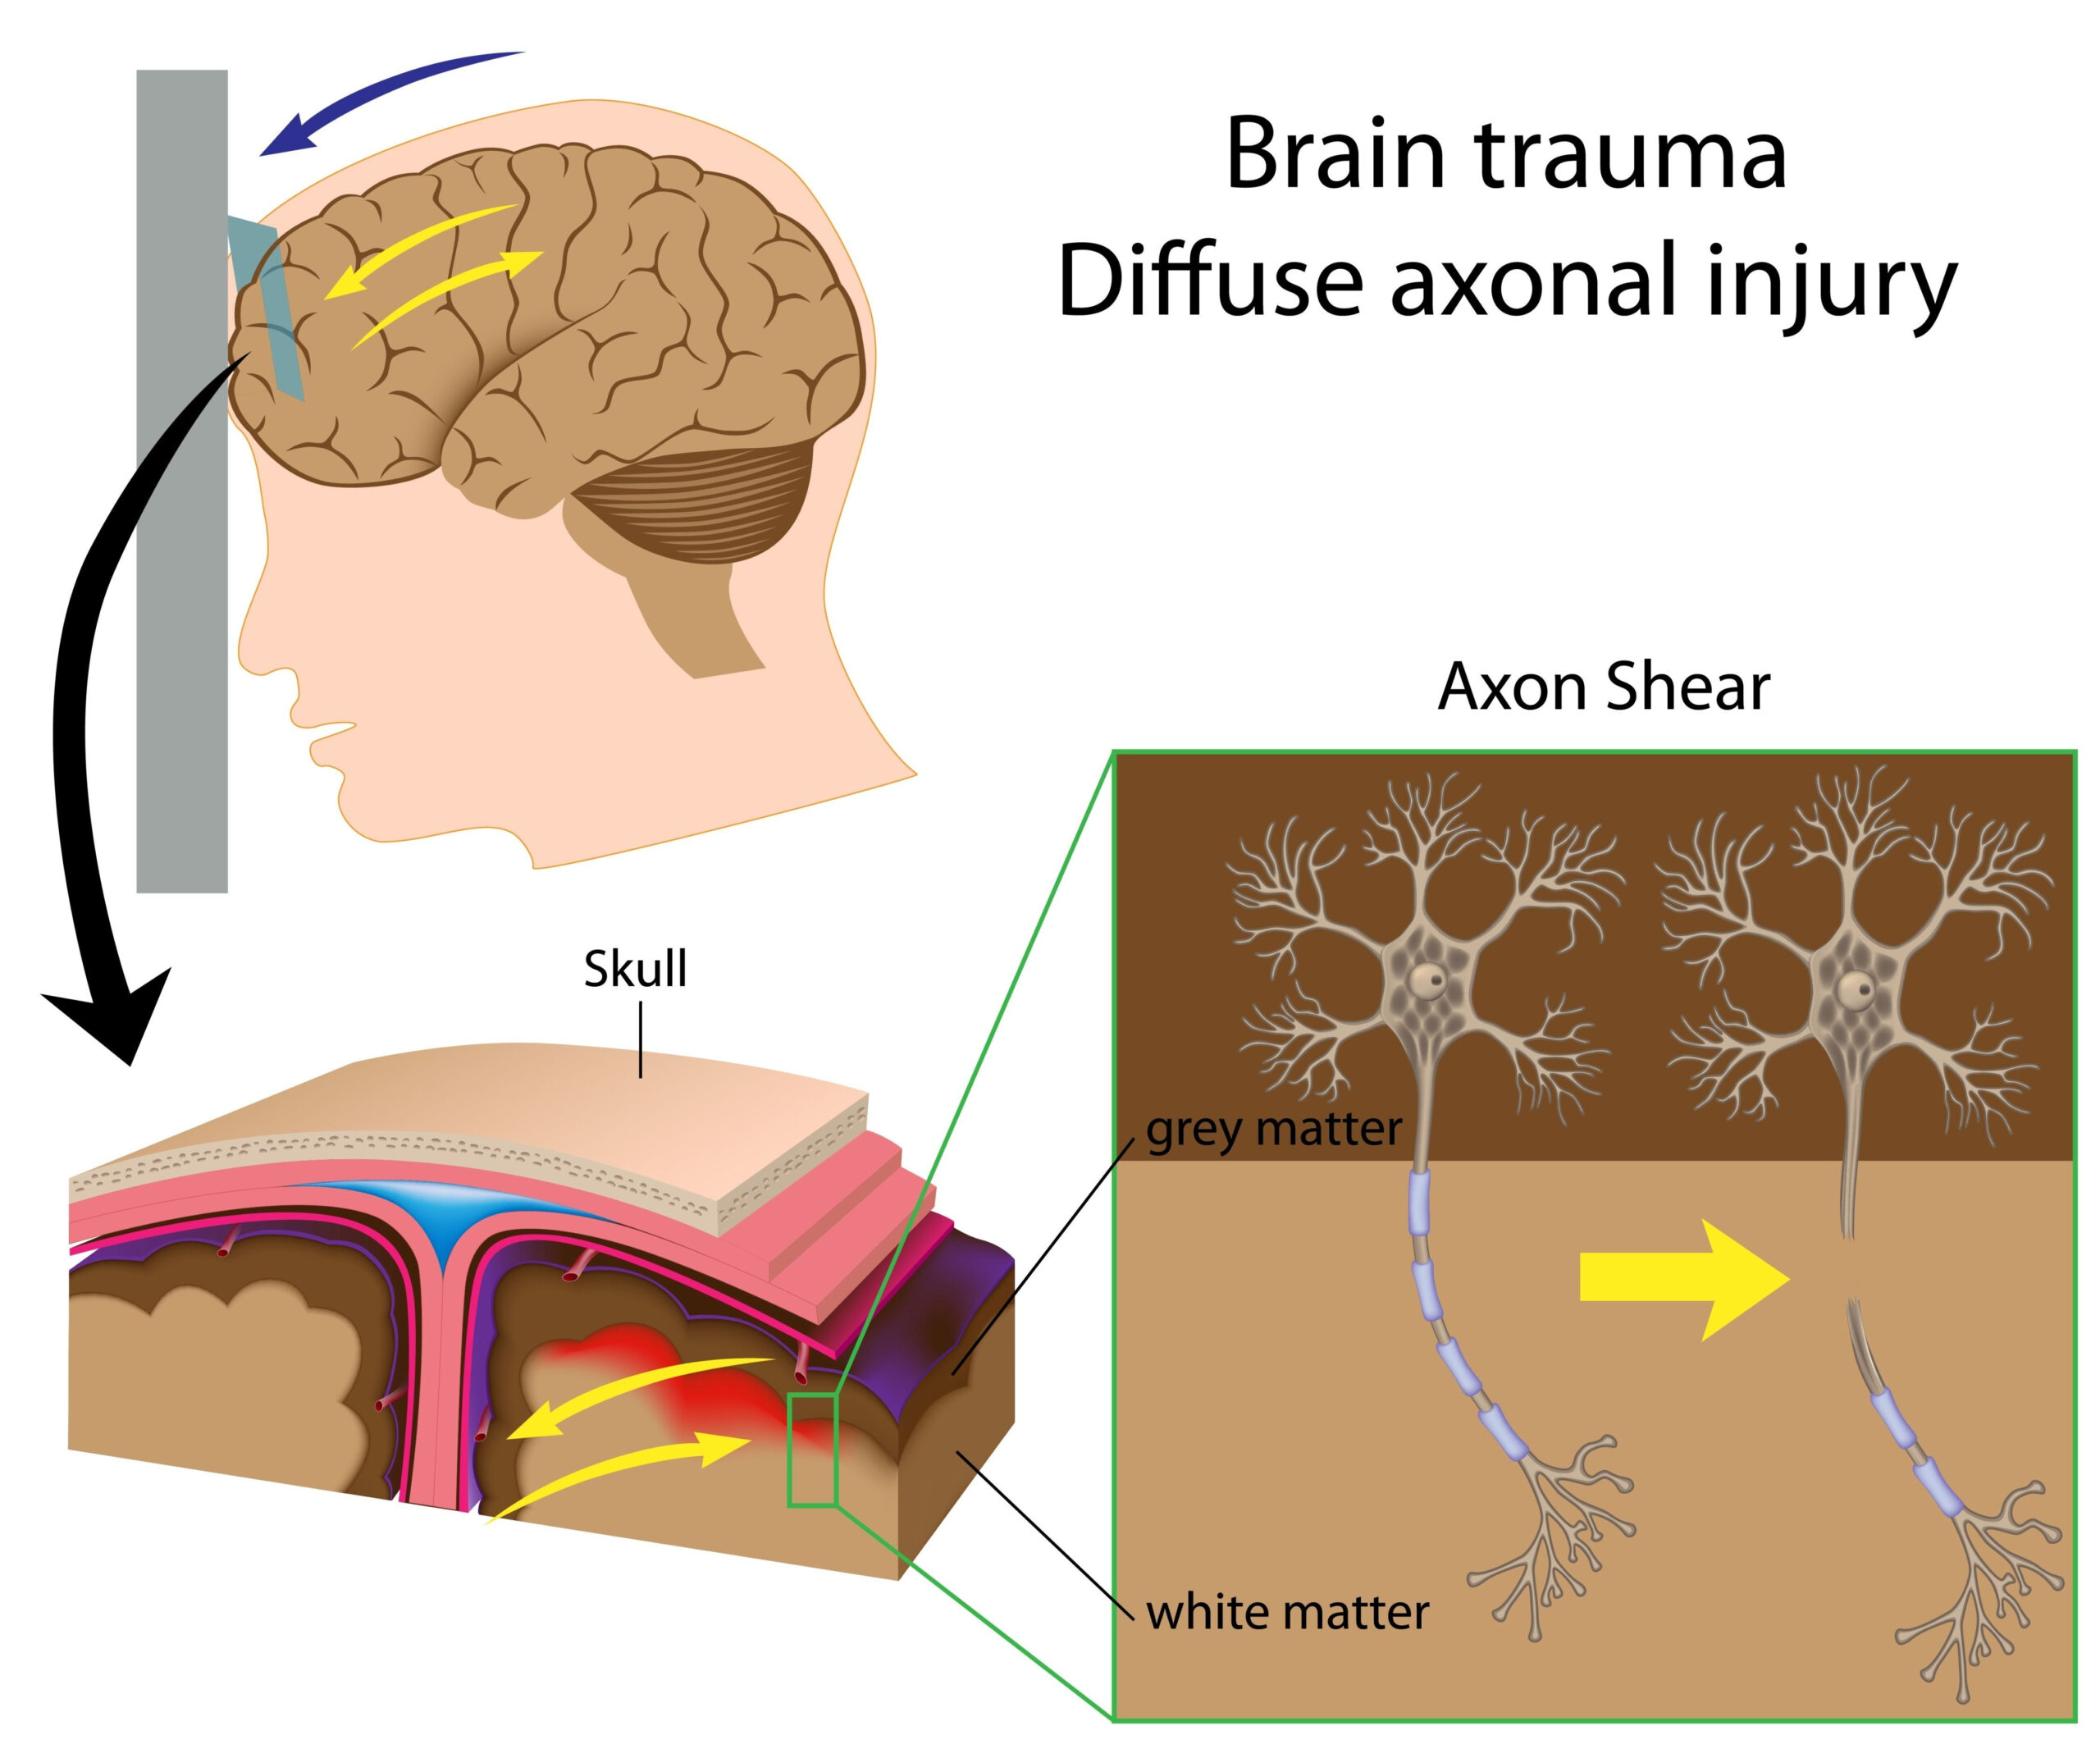
The clinical features of head injuries can further be influenced by the type of injury sustained, categorized broadly into two types: closed and open head injuries. Closed head injuries occur without an external wound, leading to potential brain swelling or bleeding, while open head injuries involve a breach in the skull and may result in higher risks of infection and more direct damage to brain tissue.
Evaluation protocols must involve a thorough history-taking and physical examination to ascertain the nature of the injury, followed by appropriate imaging studies—such as computed tomography (CT) scans—to assess for intracranial hemorrhages or structural damage. Understanding the clinical features of head injuries is pivotal for early identification and timely therapeutic measures to minimize the risk of long-term complications.
Study Design and Data Collection
This study employed a cross-sectional design to ascertain the relationship between the Glasgow Coma Scale (GCS) scores upon admission and in-hospital mortality rates among children admitted with head injuries at a tertiary care center in Central India. The study period spanned over six months, enabling a comprehensive analysis of cases within a defined timeframe.
The study population consisted of pediatric patients aged 0 to 18 years who presented to the emergency department with head injuries. Inclusion criteria were meticulously defined to ensure that only those children who received a formal evaluation and diagnosis of head injury were considered participants. Exclusion criteria encompassed patients with pre-existing neurological disorders, those who had non-traumatic causes for altered consciousness, and cases where parental consent could not be obtained.
Data collection was conducted through a systematic approach. Initially, all eligible patients and their guardians were approached for informed consent. Following consent, relevant demographic information, including age, sex, and socio-economic status, was gathered. The GCS assessed their level of consciousness upon admission, segmented into three categories: eye response, verbal response, and motor response, each scored accordingly to determine the overall GCS score, which can range from 3 (deep coma) to 15 (fully alert).
Detailed clinical information was recorded, including the mechanism of injury, presenting symptoms, and any comorbid conditions. To ensure accuracy, data were meticulously cross-verified with medical records, including notes from the emergency department and pediatric intensive care unit, if applicable. Furthermore, imaging results from CT scans were reviewed to document the presence of intracranial hemorrhages or other traumatic brain injuries.
Outcomes were defined as either survival or mortality during the hospital stay. Data was subsequently coded and entered into a statistical software package for analysis. Statistical methods, primarily univariate and multivariate analyses, facilitated the examination of potential associations between the GCS score at admission and the risk of in-hospital mortality. Additionally, confounding variables such as age, sex, and injury mechanism were controlled for to yield more reliable conclusions about the link between initial GCS and mortality rates.
This meticulous approach to study design and data collection aimed to provide robust and clinically significant findings, enhancing the understanding of head injury management in pediatric populations and guiding future treatment protocols.
Results and Statistical Analysis
The analysis focused on the association between the Glasgow Coma Scale (GCS) scores at admission and the in-hospital mortality of pediatric patients with head injuries. A total of 200 children were enrolled during the six-month study period. The cohort included a diverse demographic, with a slight male predominance (60%) compared to females (40%). The age distribution revealed that the majority of cases were concentrated in children aged 6 to 12 years, reflecting typical patterns of head trauma in this population due to increased physical activity and risk behaviors.
Upon admission, GCS scores ranged from 3 to 15. The cohort was categorized into three groups based on their GCS score: mild (GCS 13-15), moderate (GCS 9-12), and severe (GCS 8 or less). In total, 120 patients (60%) fell into the mild category, 50 patients (25%) were classified as moderate, and 30 patients (15%) were recorded with severe head injuries. Mortality rates corresponded closely with these classifications, highlighting the GCS’s predictive capability. Out of the total number of patients, 10 (5%) experienced in-hospital mortality.
In univariate analysis, a significant correlation was observed between GCS scores and mortality. Patients with severe GCS scores (8 or below) had an alarming mortality rate of 50%, whereas those with moderate and mild injuries had mortality rates of 20% and 1% respectively. These findings suggest a direct relationship where declining GCS scores indicate an increased risk of mortality. Statistical significance was achieved with a p-value of <0.01, underscoring the robustness of the association.
The multivariate analysis further adjusted for potential confounding factors such as age, sex, and mechanism of injury. Results confirmed that GCS scores remained an independent predictor of mortality after controlling for these variables. The odds ratio for mortality in patients with a GCS of 8 or less was determined to be 18.5 (95% CI: 6.3-54.5), indicating that these children were significantly more likely to succumb during their hospital stay compared to those with higher GCS scores.
Additional insights were derived from examining the mechanisms of injury. Road traffic accidents were the leading cause of head injuries, contributing to 70% of cases, followed by falls (20%) and sports injuries (10%). Notably, children involved in road traffic accidents and presenting with a low GCS score tended to have higher mortality rates. Brain imaging results revealed that intracranial hemorrhages were often observed in cases with severe GCS scores, correlating strongly with adverse outcomes.
The study effectively underscores the value of the GCS as a tool for initial assessment and prognostication in pediatric head injury cases. These findings advocate for the importance of rapid assessment strategies in the emergency setting to facilitate timely intervention and optimize clinical outcomes in children sustaining head trauma.
Impact on Patient Management
Effective management of pediatric head injuries is heavily influenced by initial assessments and the subsequent treatment strategies employed based on the Glasgow Coma Scale (GCS) scores. The ability to quickly evaluate a child’s level of consciousness upon admission can significantly dictate the course of intervention, influencing both immediate care and longer-term rehabilitation efforts.
When a child presents with head trauma, the GCS serves as a critical tool in triaging patients according to severity. Those categorized with a GCS of 13-15 are generally at a lower risk for complications and can often be safely monitored with conservative management. Conversely, children with moderate or severe scores (GCS of 9-12 or 8 and below) warrant immediate and possibly aggressive intervention strategies. For instance, patients with severe scores may necessitate advanced imaging studies such as CT scans to detect intracranial hemorrhage, followed by neurosurgical consultations if hemorrhagic events are identified.
The recognition of the GCS score’s predictive value encourages a protocol-driven response among healthcare providers. For patients presenting with severe GCS scores, rapid responses—such as intubation to secure the airway or intensive monitoring within a pediatric intensive care unit—are often warranted to mitigate the risks associated with brain injury. These strategies are aimed not only at immediate stabilization but also at minimizing potential sequelae, which can significantly affect the child’s long-term quality of life.
Furthermore, understanding the mechanisms of injury is pertinent to tailoring management strategies. For instance, roads traffic accidents—identified as a predominant cause of head injuries in the study cohort—often present unique challenges, necessitating a multi-disciplinary approach that includes trauma surgery, neurology, and rehabilitation services. Children involved in such accidents may also present with concomitant injuries, making comprehensive assessment even more crucial.
Long-term management plans are developed based on the initial GCS scores and subsequent findings. Patients demonstrating a favorable GCS score may benefit from typical outpatient follow-up and rehabilitation services. In contrast, those exhibiting lower scores may require more extensive rehabilitative services, including occupational and physical therapy, to address any deficits resulting from the injury.
Continual training and updates in GCS-based assessment protocols for health care professionals can be instrumental in improving patient outcomes. Such training fosters a deeper understanding of the implications of varying GCS scores and their corresponding management pathways, ultimately leading to more optimized care delivery.
The initial evaluation using the GCS not only plays a vital role in determining immediate clinical interventions but also shapes the overall management approach of pediatric head injuries, underscoring the necessity for accurate and timely assessments to improve patient outcomes and reduce mortality risk in this vulnerable population.