Defining Hyperkinetic Movement Disorders
Hyperkinetic movement disorders encompass a range of neurological conditions characterized by excessive, uncontrolled movements. These disorders can manifest as tics, dystonic movements, chorea, athetosis, or myoclonus, significantly impacting an individual’s quality of life. The movements may vary in intensity and frequency, and they can be classified based on their underlying etiologies and clinical characteristics.
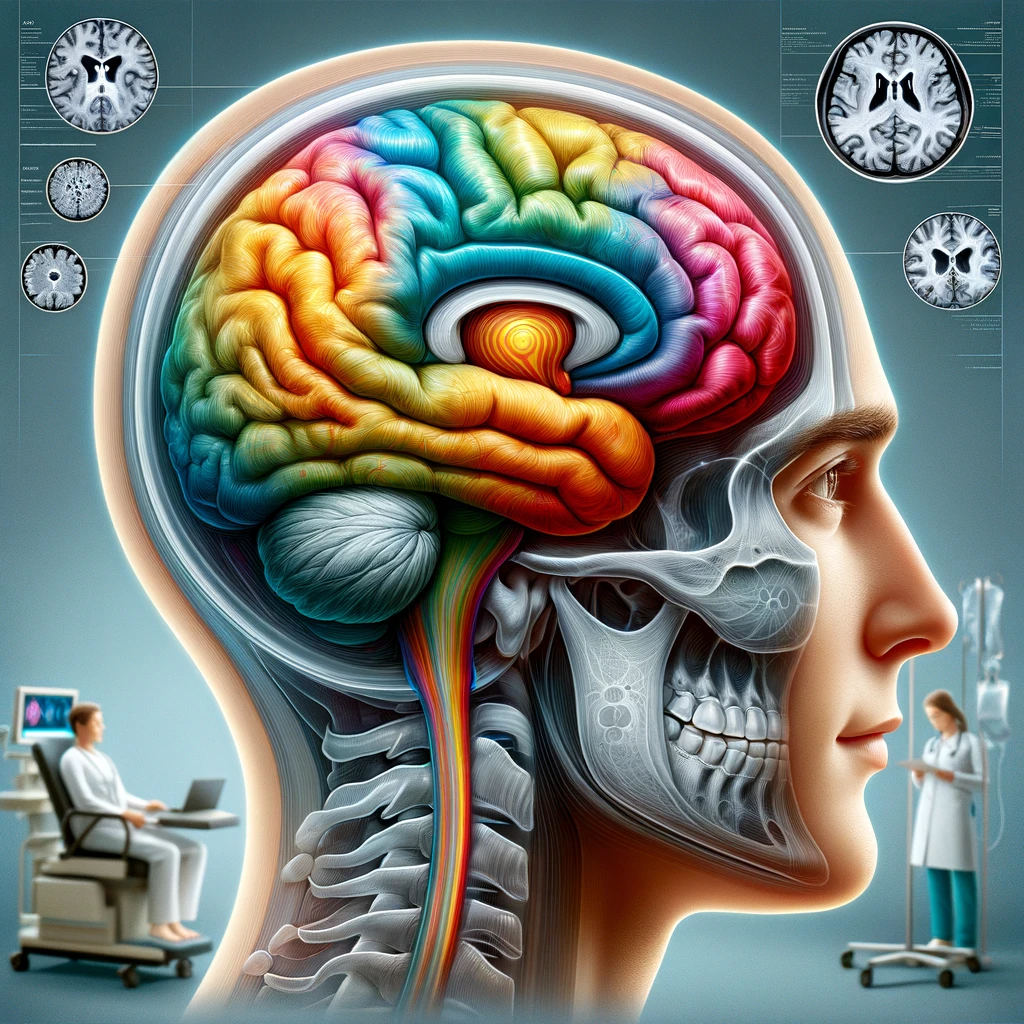
The pathophysiology of hyperkinetic movement disorders often involves dysfunction in the basal ganglia, a group of nuclei in the brain that are crucial for movement regulation. Conditions such as Huntington’s disease and Tourette syndrome serve as examples of hyperkinetic disorders, each with distinct movement patterns. For instance, Huntington’s disease primarily involves chorea, while Tourette syndrome is characterized by motor and vocal tics.
Diagnosis relies heavily on clinical observation and patient history, with particular attention paid to the variety of movements exhibited and their contextual triggers. It is essential for clinicians to differentiate between primary movement disorders and secondary forms caused by factors such as medications, metabolic disturbances, or other neurological conditions.
Recent advancements emphasize the importance of a systematic approach to classify and evaluate hyperkinetic movement disorders. Various standardized scales and diagnostic criteria have been proposed to enhance interrater reliability among healthcare professionals, fostering a more accurate understanding of each patient’s unique presentation. This leads to improved treatment strategies tailored to individual needs.
The following table summarizes common types of hyperkinetic movement disorders along with their key characteristics:
| Movement Disorder | Characteristics | Common Causes |
|---|---|---|
| Chorea | Irregular, non-repetitive movements that are often fluid and unpredictable. | Huntington’s disease, Sydenham’s chorea. |
| Dystonia | Involuntary muscle contractions leading to abnormal postures or twisted movements. | Primary dystonia, cerebral palsy. |
| Myoclonus | Sudden, brief, shock-like jerks of a muscle or muscle group. | Epileptic myoclonus, metabolic disorders. |
| Tourette Syndrome | Characterized by repetitive motor and vocal tics. | Genetic factors, environmental triggers. |
Recognizing and defining hyperkinetic movement disorders accurately is vital for advancing research and clinical practice. Establishing a robust framework for evaluation will enhance the consistency of assessments and ensure that patients receive appropriate care, ultimately improving therapeutic outcomes.
Study Design and Participants
This study utilized a cross-sectional design to assess interrater agreement among experts when diagnosing hyperkinetic movement disorders. A sample of 50 participants was recruited, comprising both males and females within the age range of 5 to 70 years. These individuals were selected from a specialized neurology clinic and were diagnosed with various forms of hyperkinetic movement disorders, including chorea, dystonia, tics, and myoclonus.
To ensure a diverse representation, participants were stratified by age, gender, and the specific type of hyperkinetic disorder. This stratification allows for a comprehensive analysis of how these factors might influence clinical assessments and the subsequent interrater reliability among different examiners.
The inclusion criteria required that participants were diagnosed by a neurologist and had displayed symptoms for a minimum duration of six months prior to participation. Participants with secondary hyperkinetic disorders due to medication or other neurological conditions were excluded to maintain focus on primary forms of the movement disorders.
Expert reviewers included ten neurologists specializing in movement disorders, each with varying years of clinical experience ranging from 5 to over 20 years. The neurologists underwent training sessions to familiarize them with the standardized assessment tools and diagnostic criteria employed in the study.
The assessment process involved the following steps:
1. **Clinical Evaluation**: Each expert independently evaluated the participants using a structured examination that included standardized movement disorder scales and assessment protocols.
2. **Video Recordings**: To enhance reliability, each assessment was recorded on video. This allowed reviewers to analyze the same set of movements outside the clinical environment, which can sometimes influence diagnosis due to stress or unfamiliarity.
3. **Data Collection**: The data collected from each examination included demographic information, clinical history, and the standardized score from diagnostic scales, alongside an overall clinical diagnosis for each participant.
The inclusion of video recordings introduces an innovative aspect to the traditional evaluation, minimizing the potential bias that may stem from in-person assessments. It ensures that all participating neurologists base their judgments on the same visual information, supporting an objective evaluation of interrater agreement.
A key aspect of the study design was the statistical analysis used to measure interrater agreement. The Fleiss’ kappa statistic was employed to determine the level of agreement among the clinicians regarding their diagnoses. This statistical measure helps to quantify how consistently different raters classify the data, accounting for the agreement that could occur by chance.
The following table presents demographic and clinical characteristics of the study participants:
| Demographic Characteristic | Value |
|---|---|
| Total Participants | 50 |
| Gender (Male:Female) | 24:26 |
| Age Range | 5-70 years |
| Types of Disorders | Chorea, Dystonia, Tics, Myoclonus |
| Average Duration of Symptoms | 3 years |
This structured approach to participant selection and study design was essential for evaluating the interrater agreement effectively. It not only elucidates the complexity of diagnosing hyperkinetic movement disorders but also sheds light on the necessity for consensus among healthcare professionals in establishing a reliable clinical framework. The results of this assessment are anticipated to inform both clinical practice and future research endeavors in the field.
Assessment and Interrater Agreement
To accurately evaluate hyperkinetic movement disorders, it is crucial to have a comprehensive assessment strategy that promotes consistency among clinicians. In this study, specialized assessment tools were employed to ensure that movement disorder diagnoses were made uniformly across differing expert evaluations. This process involved both subjective observations and standardized scoring systems tailored to capture the nuances of hyperkinetic movements.
The evaluation involved using established clinical scales, such as the Abnormal Involuntary Movement Scale (AIMS) and the Unified Huntington’s Disease Rating Scale (UHDRS), which provide a systematic way of measuring the severity and frequency of movement disorders. By utilizing these scales, clinicians were better positioned to quantify the specific characteristics of each disorder, including the type, duration, and triggers of movements, which are vital for accurate diagnosis.
Interrater agreement is a crucial component in ensuring that the diagnostic approaches yield reliable results. To quantify this agreement quantitatively, the study employed Fleiss’ kappa statistic, offering a robust method for assessing consistency among multiple raters. Fleiss’ kappa ranges from -1 to 1, where values closer to 1 indicate almost perfect agreement among the experts, values around 0 suggest no agreement beyond chance, and negative values signify disagreement.
Preliminary analyses revealed varying degrees of agreement across different types of hyperkinetic movement disorders, highlighting areas where clinician familiarity played a significant role. For instance, disorders with more defined clinical presentations, such as Tourette syndrome, typically yielded higher interrater agreement compared to more subtle disorders like myoclonus. The following table illustrates the interrater agreement results for selected hyperkinetic movement disorders:
| Disorder Type | Fleiss’ Kappa Value | Agreement Level |
|---|---|---|
| Tourette Syndrome | 0.85 | Almost perfect agreement |
| Chorea | 0.70 | Substantial agreement |
| Dystonia | 0.65 | Moderate agreement |
| Myoclonus | 0.45 | Fair agreement |
While these findings indicate a valuable level of consensus among experts, they also reveal areas needing further attention to enhance diagnostic reliability. Differences in familiarity with specific disorders and variations in individual assessment styles can contribute to discrepancies in diagnosis. Consequently, ongoing education and training are crucial for clinicians to maintain and improve their diagnostic skills, particularly in more complex cases.
The study’s outcomes emphasize the importance of consensus-building in clinical practice. Standardized assessment protocols and collaborative reviews of cases are recommended strategies to strengthen interrater agreement. Moreover, engaging in case discussions and sharing insights through platforms such as interdisciplinary meetings can further improve understanding and approach to diagnosing hyperkinetic movement disorders.
As healthcare professionals strive to refine their diagnostic capabilities, fostering an environment that values continued education and the sharing of best practices will ultimately benefit patient care. Ensuring that interrater agreement in these complex cases remains high is vital for tailoring effective treatment plans and achieving better long-term outcomes for individuals suffering from hyperkinetic movement disorders.
Recommendations for Clinical Practice
To enhance clinical practice in the assessment and management of hyperkinetic movement disorders, several recommendations emerge based on the findings of this study. Emphasizing standardized diagnostic protocols, continuous education, and a collaborative approach among healthcare professionals can significantly contribute to improved patient outcomes.
Firstly, it is imperative for clinicians to adopt and consistently utilize standardized assessment tools such as the Abnormal Involuntary Movement Scale (AIMS) and the Unified Huntington’s Disease Rating Scale (UHDRS). These tools offer structured frameworks that quantify movement characteristics, allowing for more precise diagnoses. As evidenced by the study, the use of standardized scales is linked to higher interrater agreement, particularly in well-defined disorders like Tourette syndrome. Therefore, training sessions focused on these scales should be integrated into the continuous professional development curriculum for neurologists and related specialists.
Secondly, fostering environments that support interprofessional collaboration and case discussions can greatly enhance diagnostic reliability. Encouraging neurologists, psychiatrists, and occupational therapists to engage in multidisciplinary team meetings allows for the exchange of diverse insights into complex cases. Such collaborative sessions not only serve to improve interrater agreement but also facilitate holistic approaches to treatment planning.
Additionally, continuous education should focus on the nuances of less common hyperkinetic disorders, such as myoclonus. The study indicated lower agreement levels in diagnosing these conditions, which underscores the importance of specialized training and resources. Online workshops, case study analyses, and access to comprehensive databases on movement disorders can equip clinicians with the tools necessary to improve their diagnostic accuracy.
Implementing regular audits of clinical practices is also recommended. These audits should involve reviewing diagnostic decisions and corresponding patient outcomes to identify trends and inconsistencies in assessments. Feedback from these audits can be instrumental in honing diagnostic skills and enhancing the overall understanding of hyperkinetic movement disorders within the clinical team.
Incorporating patient and family education into the care process is another crucial component. For patients diagnosed with hyperkinetic movement disorders, understanding their condition can significantly impact treatment adherence and overall quality of life. Providing clear, accessible information about their diagnosis, treatment options, and potential coping strategies empowers patients and their families, aligning them as active partners in healthcare.
Lastly, as new research emerges and the understanding of hyperkinetic movement disorders evolves, clinicians are encouraged to participate in clinical trials and research initiatives. Such involvement not only contributes to the broader scientific community but also keeps clinicians abreast of the latest advancements within the field, allowing them to apply cutting-edge practices to patient care.
By embracing these recommendations, healthcare professionals can enhance their diagnostic practices, thereby ensuring that individuals with hyperkinetic movement disorders receive timely and appropriate interventions, which are essential for effective management of their condition.