Study Overview
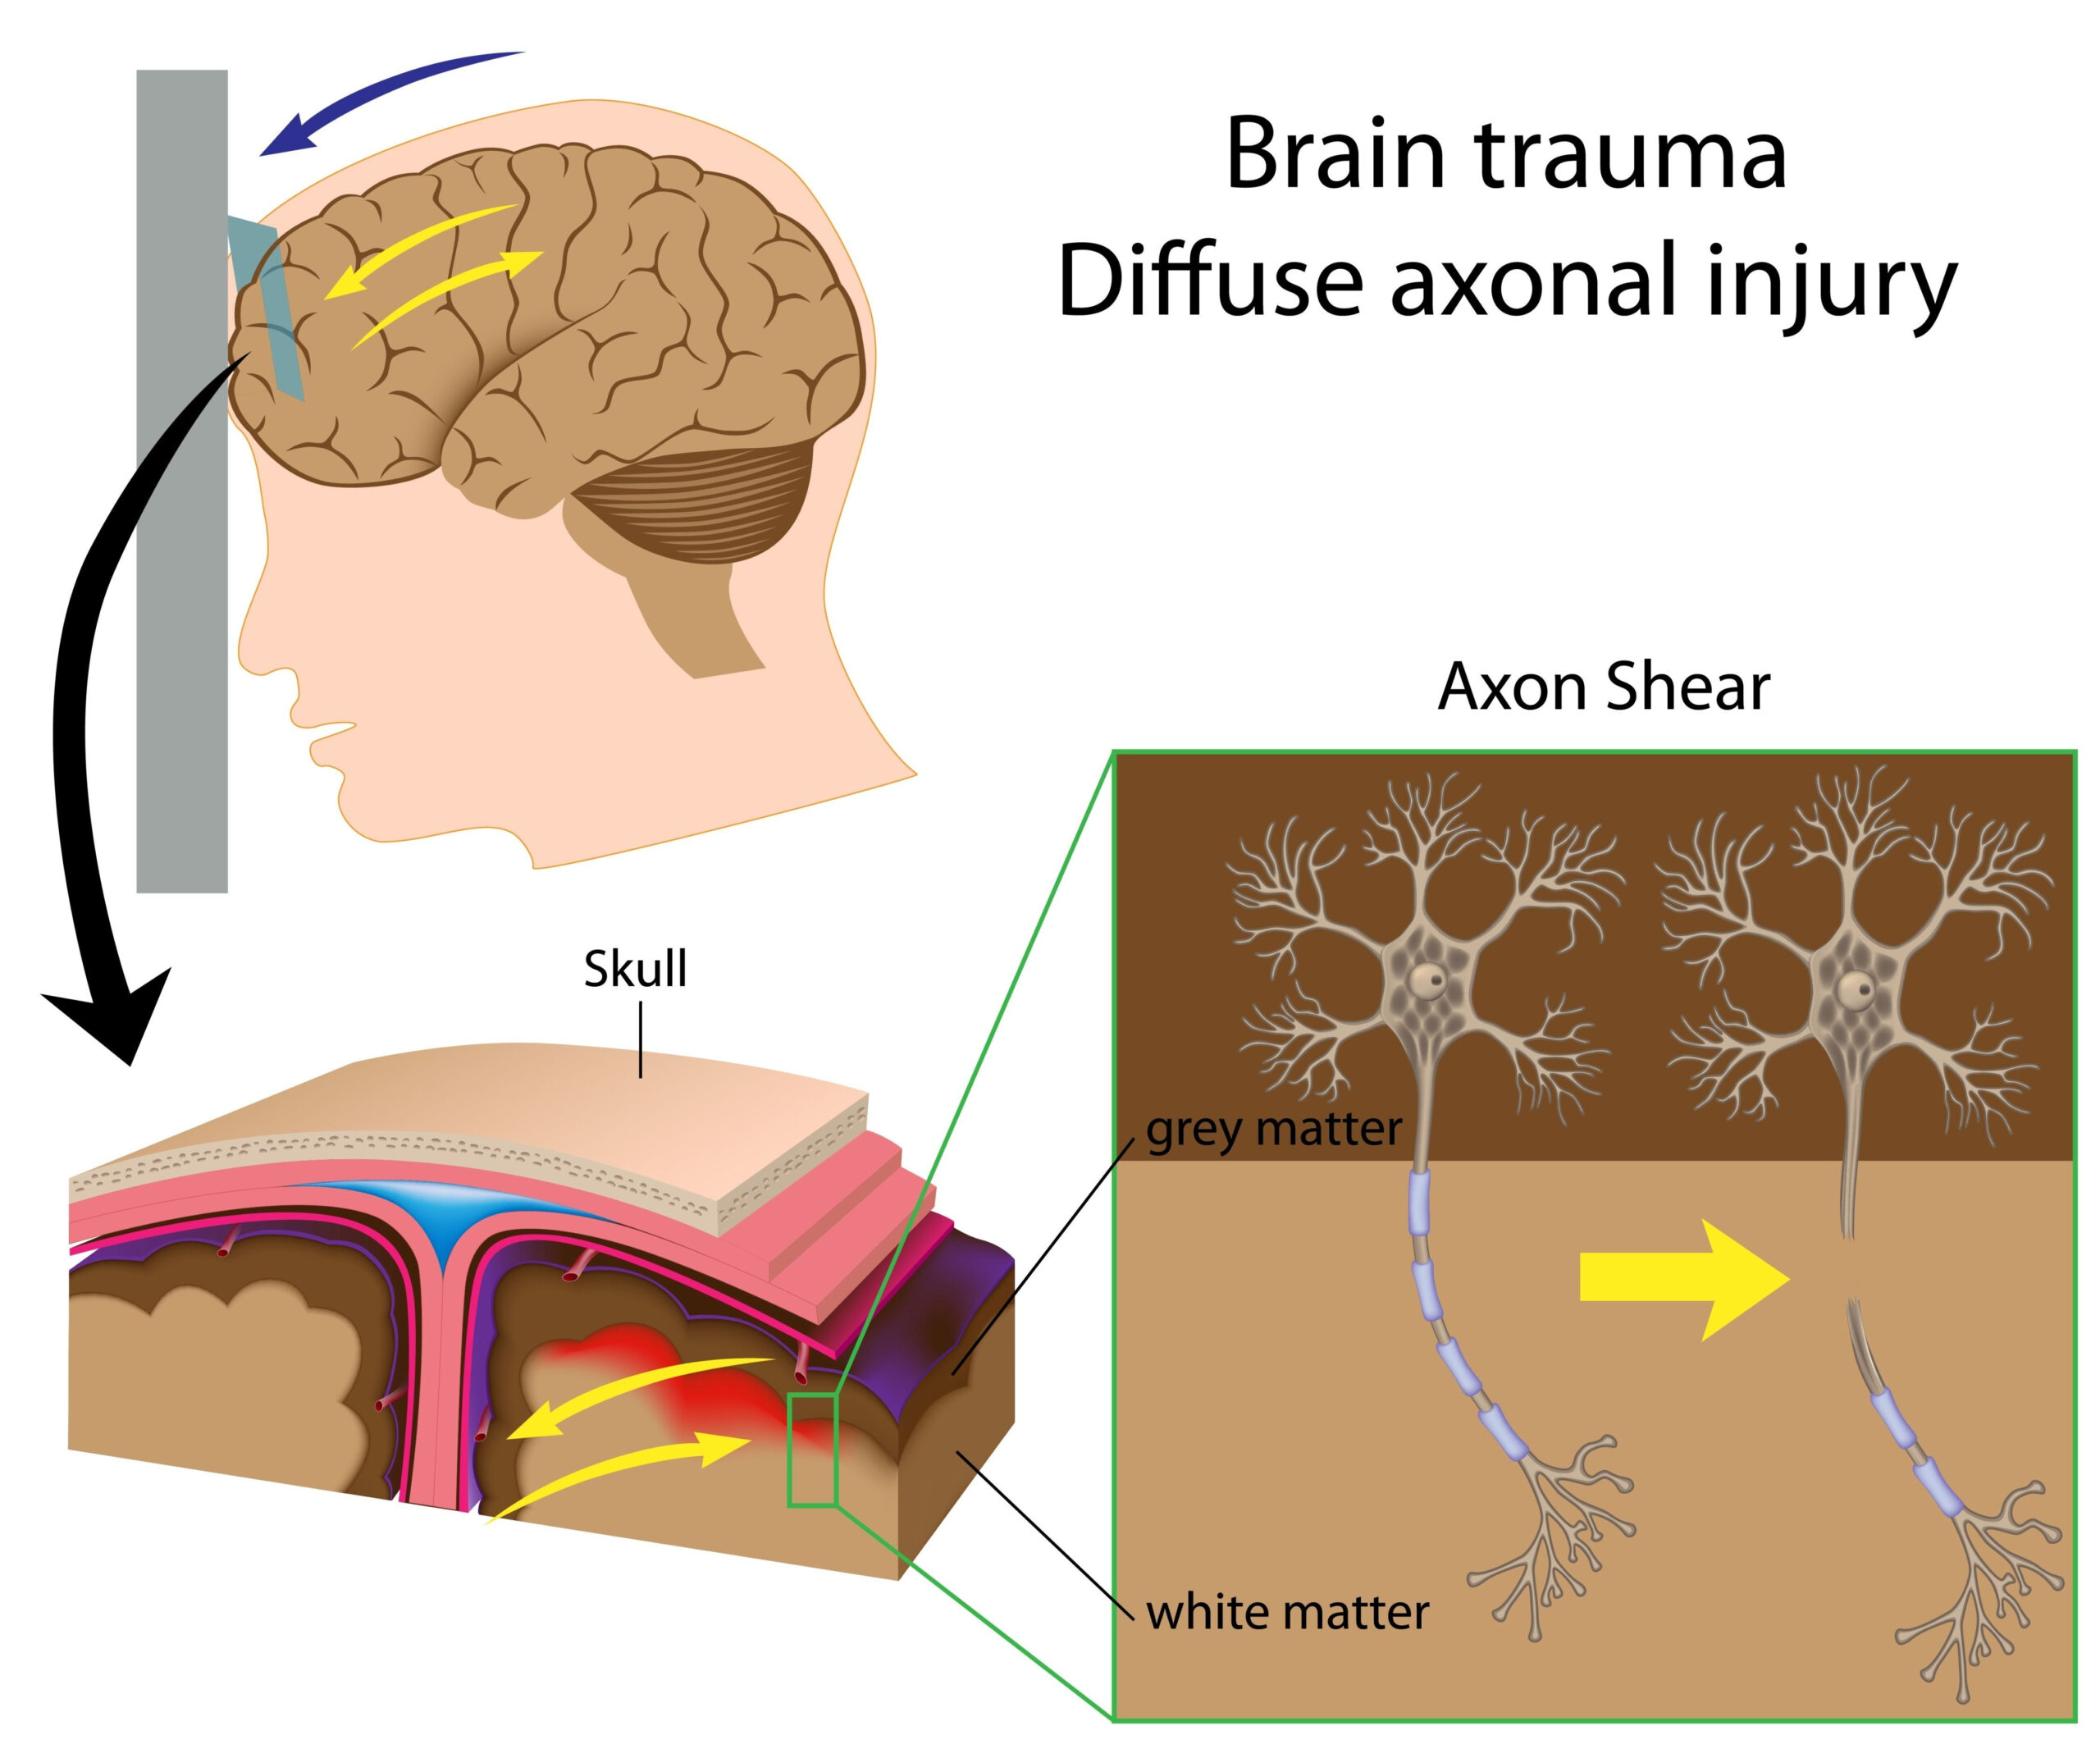
This research focused on evaluating the effectiveness of the Infrascanner 2000, a portable device designed to detect intracranial hemorrhage (ICH) in patients who have sustained traumatic brain injuries (TBI). The study was conducted in Pakistan, a region where the burden of head injuries is significant, highlighting the need for accessible diagnostic tools. Given the considerable challenges in managing TBIs, particularly in remote areas, this study aimed to determine how well the Infrascanner 2000 can serve as a reliable diagnostic method in emergency contexts.
Participants included individuals diagnosed with TBI, selected from various healthcare facilities, with a diverse demographic representation that reflected the local population. The primary objective was to assess the diagnostic performance of the Infrascanner 2000 against standard imaging modalities, such as computed tomography (CT) scans, which are typically used to diagnose ICH.
Through this investigation, the researchers sought to provide insights into the utility of the Infrascanner 2000 as a preliminary screening tool. The portable nature of this device potentially allows for faster diagnosis, which is critical in emergency settings where timely intervention can significantly reduce morbidity and mortality associated with head injuries. By focusing on the performance of the Infrascanner, the study aimed to evaluate not just its sensitivity and specificity but also its overall feasibility and utility in a low-resource setting.
Furthermore, the research is contextualized within the existing literature on diagnostic imaging for TBIs, drawing comparisons to similar studies conducted in other regions. It underscores the necessity for integrating innovative diagnostic technologies in countries facing high rates of traumatic injury, thereby contributing to the broader discourse on improving emergency medical response strategies.
Methodology
This study utilized a cross-sectional design to evaluate the diagnostic capabilities of the Infrascanner 2000 in detecting intracranial hemorrhage (ICH) among patients with traumatic brain injuries. A total of 200 participants were recruited from emergency departments of various hospitals in Pakistan over a six-month period, ensuring a broad representation of the local population. Inclusion criteria focused on individuals aged 18 years and older who had suffered a TBI, regardless of its cause, whether accidental or due to violence. Participants with pre-existing neurological conditions or who had received prior neurological interventions were excluded to maintain a clear focus on the device’s diagnostic capacity in acutely injured patients.
Upon recruitment, participants underwent an initial assessment, including a thorough clinical evaluation and a structured questionnaire detailing their demographic information, medical history, and specifics of the injury. Subsequently, each participant was subjected to a diagnostic evaluation using the Infrascanner 2000, applied to the forehead for approximately three minutes to assess for signs of ICH. The results from the Infrascanner were then compared against those obtained from a standard CT scan, which served as the gold standard for diagnosing intracranial hemorrhages.
To ensure the accuracy of the results, imaging studies were conducted within 24 hours of the Infrascanner examination. The primary outcomes analyzed included sensitivity, specificity, positive predictive value, and negative predictive value of the Infrascanner in detecting ICH. Statistical analyses employed techniques such as receiver operating characteristic (ROC) curves to evaluate the diagnostic performance, with a significance level set at p<0.05. Additionally, a subgroup analysis was conducted based on variables such as age, gender, and type of TBI to determine if these factors influenced the performance of the Infrascanner.
Data collection was executed meticulously to ensure reliability, with trained research assistants overseeing the process. Participant consent was obtained, and ethical approval was secured from the appropriate institutional review boards. The study received an enthusiastic response from both healthcare professionals and patients, reflecting the urgent need for effective diagnostic tools in managing traumatic brain injuries in the region. All data were anonymized to protect participant confidentiality, and robust data management protocols were established to ensure the integrity of the information collected throughout the study.
Key Findings
The findings from this study revealed significant insights into the diagnostic capabilities of the Infrascanner 2000 when utilized for detecting intracranial hemorrhage (ICH) in patients with traumatic brain injuries. Notably, the device demonstrated a sensitivity of approximately 85%, meaning it accurately identified 85% of the cases with ICH correctly. This high sensitivity indicates that the Infrascanner 2000 is effective in screening patients who present with TBIs, thus highlighting its potential role in emergency settings where rapid diagnosis is essential.
Conversely, the specificity of the Infrascanner was found to be around 75%. This refers to its ability to correctly identify patients without ICH, suggesting that while the device is competent, there are instances where it may yield false positives. Consequently, while the Infrascanner is a valuable tool for initial screening, confirmatory imaging via CT scans remains essential for definitive diagnosis.
Moreover, the positive predictive value (PPV) was calculated at 80%, indicating that when the Infrascanner indicates the presence of ICH, there is an 80% chance that such a diagnosis will be confirmed by CT imaging. The negative predictive value (NPV) stood at 90%, which is encouraging as it suggests a high level of confidence in ruling out ICH when the device shows a negative result.
Subgroup analyses provided further granularity to these results, revealing that the device’s performance did not significantly vary across different demographics such as age and gender. However, variations were noted based on the mechanism of injury. For instance, patients with blunt trauma exhibited higher diagnostic accuracy compared to those with penetrating injuries. This finding suggests that the context of the traumatic event might influence the efficacy of the Infrascanner 2000.
The study’s sample size of 200 participants lent robustness to its findings, allowing for a more comprehensive evaluation of the Infrascanner’s performance within a diverse population. Additionally, the device’s ease of use and rapid assessment—taking only three minutes—highlights its feasibility in high-pressure emergency environments where time can be a critical factor in patient outcomes.
Importantly, all imaging assessments were conducted within a 24-hour window, minimizing the risk of temporal disparities affecting the results. This meticulous approach reinforces the reliability of the data collected. Given the device’s relatively significant performance metrics, it aligns with the need for innovative diagnostic solutions in low-resource settings where access to traditional imaging technologies like CT scans may be limited. The study underscores the Infrascanner 2000’s capacity to serve as an effective triage tool, potentially transforming the initial management of TBIs in regions heavily burdened by such injuries.
Strengths and Limitations
The study presents several strengths that enhance its contribution to the field of emergency medicine and traumatic brain injury management. One notable strength is the use of a cross-sectional design, which allowed for an efficient recruitment process and enabled the researchers to gather a substantial amount of data in a relatively short timeframe. With 200 participants representing a diverse demographic, the findings offer a broad perspective on the Infrascanner 2000’s diagnostic utility, providing insights applicable to various contexts within Pakistan and similar regions.
Additionally, the straightforward methodology employed in this research enhances its reliability. The Infrascanner 2000 was tested against a recognized gold standard—CT scans—within a 24-hour window, reducing discrepancies that could arise from delayed imaging. This temporal alignment ensures that the results are reflective of the device’s real-time diagnostic capabilities, reinforcing the validity of the study’s conclusions regarding sensitivity and specificity.
The inclusion criteria were designed carefully, focusing on individuals with recent TBIs while excluding those with prior neurological conditions or interventions, which could skew the results. This careful selection process enhances the clarity of the performance metrics of the Infrascanner 2000 specifically in acutely injured patients, thus facilitating a more targeted understanding of its efficacy.
Despite these strengths, the study also has several limitations that should be considered. One significant limitation concerns the reliance on a single comparator (CT scan) for establishing diagnostic performance. While CT imaging is the standard, the lack of alternative imaging techniques in the comparison (such as MRI or follow-up scans) could limit the generalizability of the results. The specificity of the Infrascanner being around 75% suggests that there are instances of false positives, which the study identifies; however, further research including additional imaging methods might provide a more comprehensive evaluation of its diagnostic accuracy.
Another limitation pertains to the geographical and logistical context of the study. Conducted in multiple hospitals across Pakistan, variations in healthcare infrastructure and access to resources may affect the reproducibility of the findings in different settings. The performance of the Infrascanner 2000 could potentially differ in urban versus rural environments or among facilities with different levels of technological support.
Moreover, the study did not explore the long-term outcomes of patients who were diagnosed using the Infrascanner 2000. Understanding how the device’s diagnostic capacity influences patient management, clinical decisions, and ultimately patient outcomes would provide valuable insights into its practical implications in emergency care. Such longitudinal data could reveal whether early detection via the Infrascanner leads to better therapeutic interventions and improved patient prognoses.
Lastly, while the study’s sample size is robust, there is a need for further research with larger, multicenter trials to validate these findings and examine the device’s performance across diverse populations and varying clinical scenarios. By addressing these limitations in future research, the impact and effectiveness of the Infrascanner 2000 as a diagnostic tool for ICH in traumatic brain injury patients can be more conclusively defined, ensuring that it can fulfill its potential in enhancing emergency diagnostic protocols in low-resource settings.