Study Overview
The investigation focused on evaluating the Brief Test of Adult Cognition by Telephone (BTACT) as a viable research instrument within emergency department settings for individuals suffering from mild traumatic brain injury (mTBI). The study was initiated to explore whether BTACT could yield reliable cognitive assessment data remotely, which is particularly pertinent given the increasing prevalence of brain injuries in both civilian and military populations.
Researchers aimed to ascertain how effectively this cognitive assessment could be integrated into the emergency department workflow, an area where traditional cognitive evaluation methods often face obstacles such as time constraints and the immediate needs of patients. The study employed a cross-sectional design, collecting data on participants’ cognitive performance through BTACT and comparing it with their clinical profiles and injury characteristics.
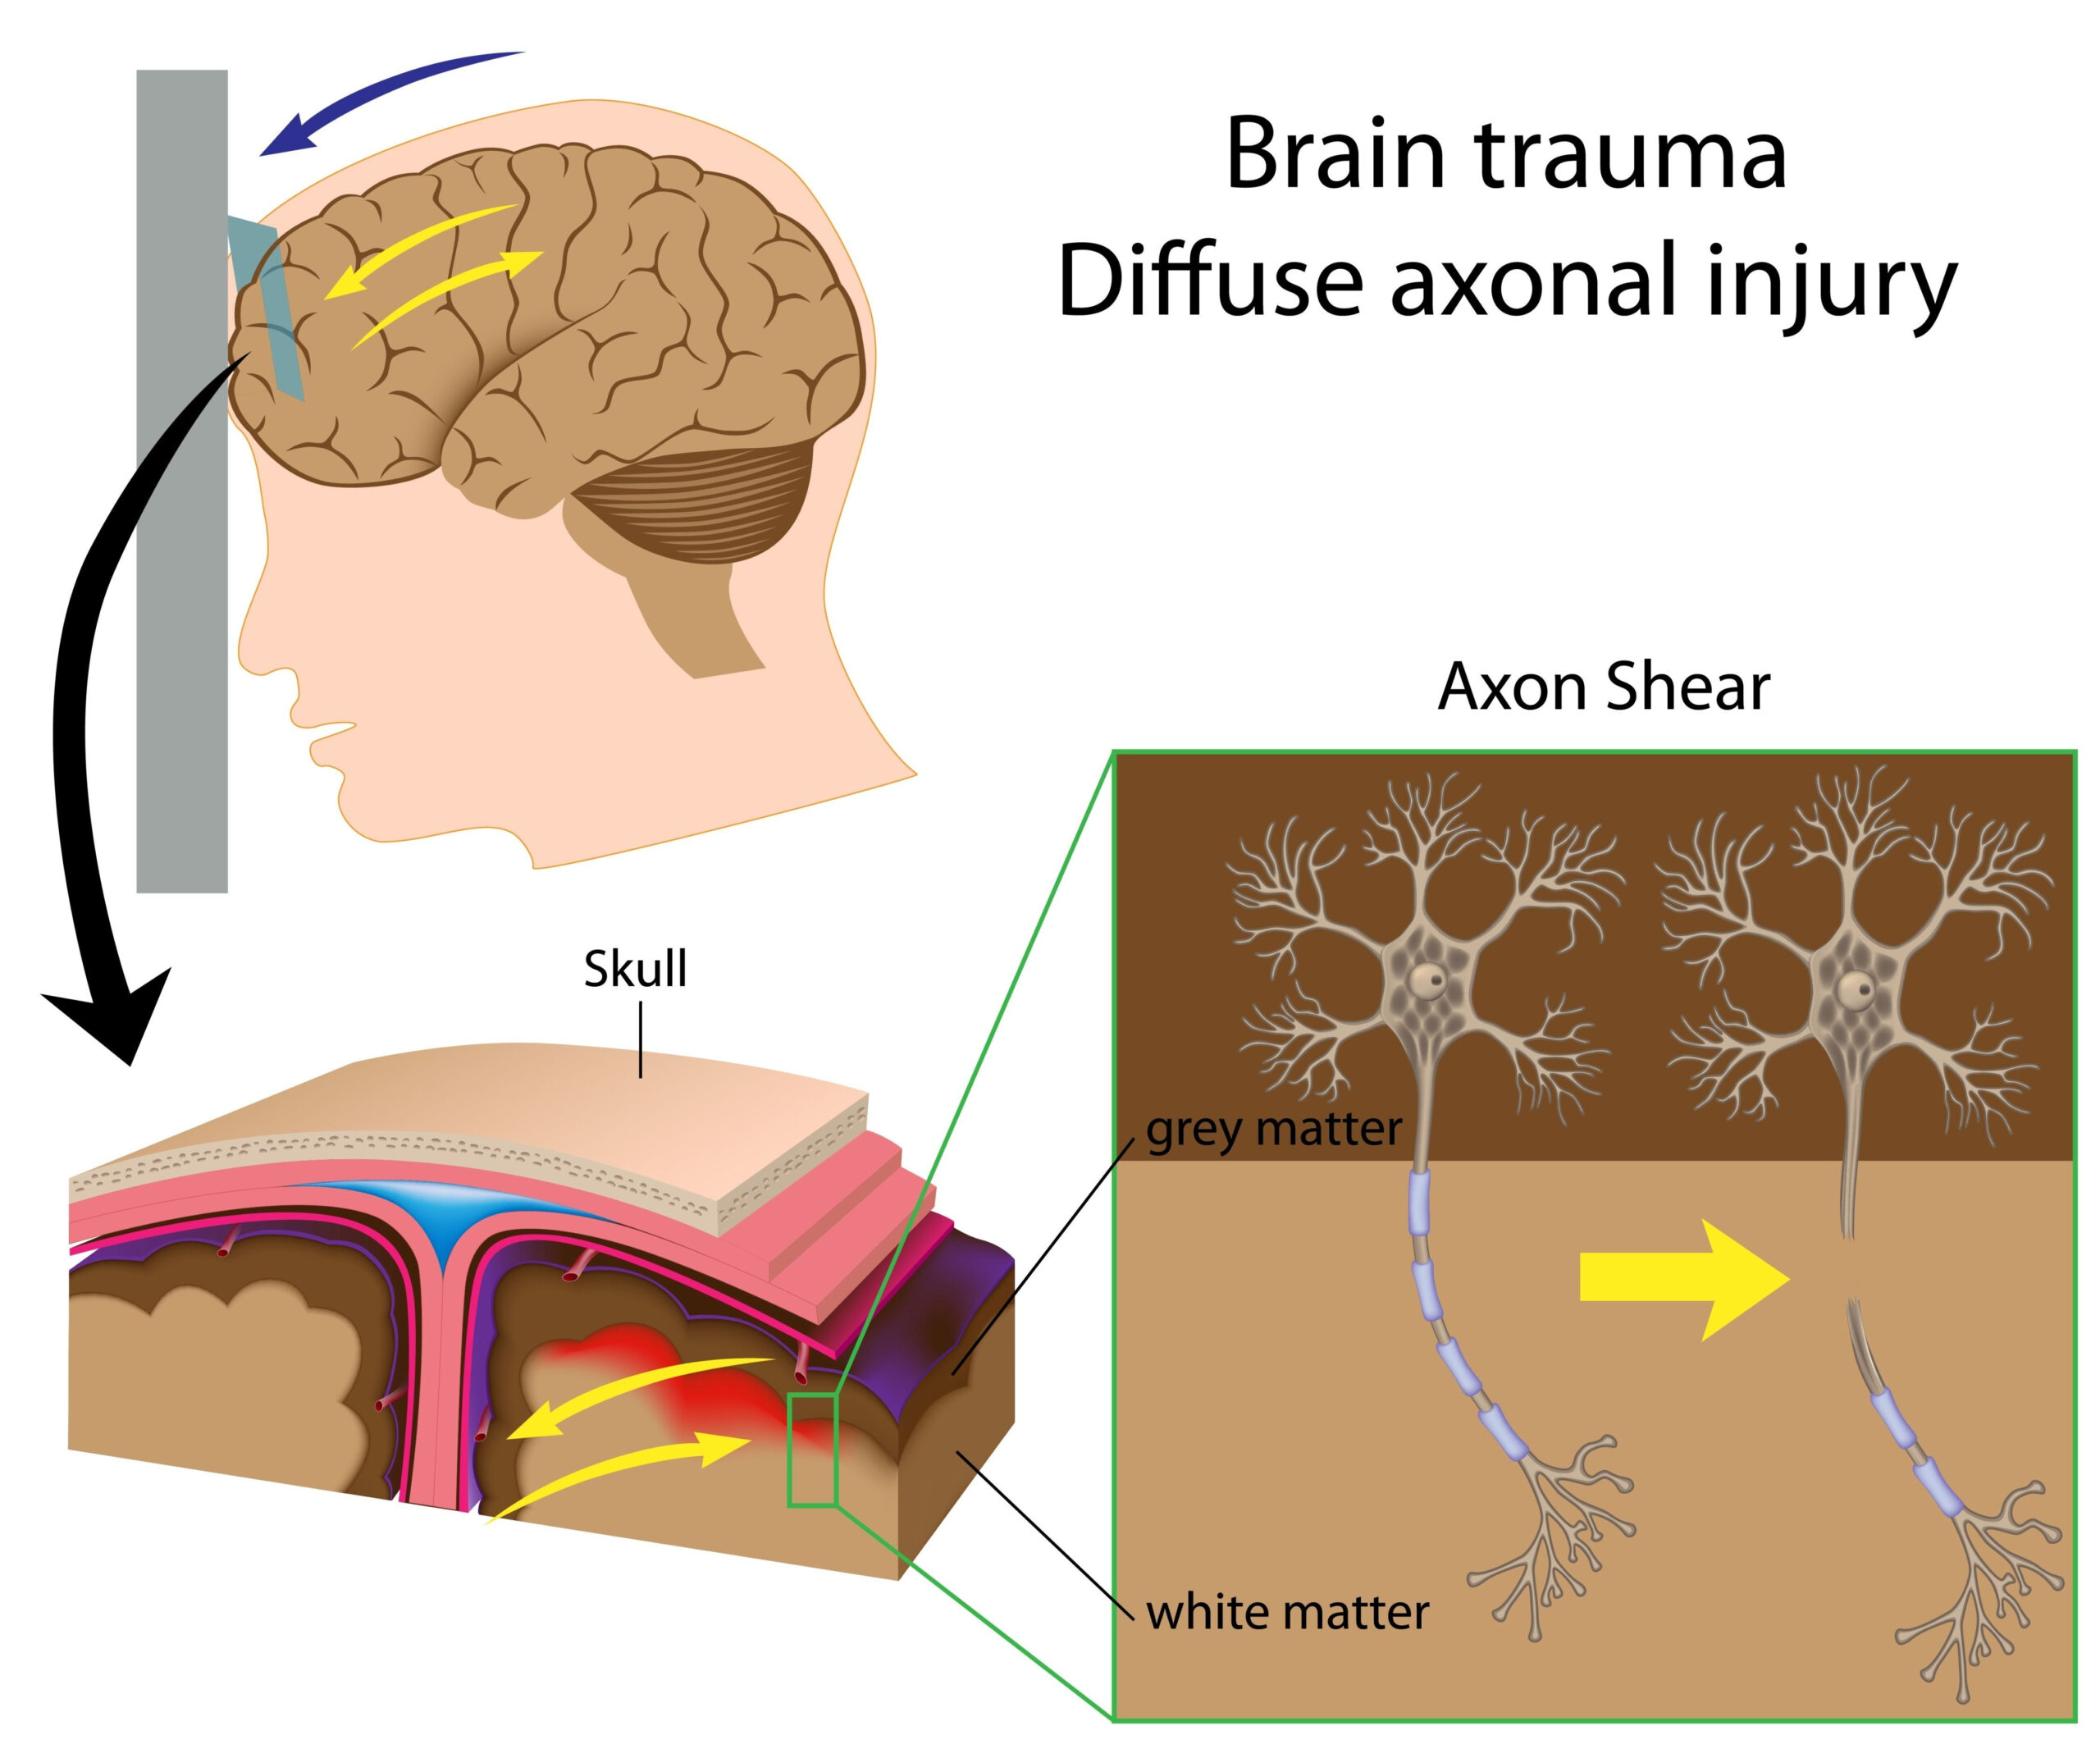
This research is significant in the context of mTBI because these injuries can lead to subtle cognitive impairments that are not always apparent during initial medical evaluations. Understanding the cognitive outcomes of mTBI can inform treatments and ongoing management for affected individuals. The BTACT was selected for its brevity, ease of administration, and prior validation in various populations, making it an attractive option for use in busy clinical settings where thorough examinations may be impractical.
Through this study, the researchers sought to contribute to the existing literature on cognitive assessment tools and their applicability in emergency settings, with a particular emphasis on enhancing patient care for those with mild traumatic brain injuries.
Methodology
The study employed a cross-sectional design, integrating both qualitative and quantitative approaches to assess the feasibility and effectiveness of BTACT within the emergency department context. Participants were recruited from a busy urban emergency department, targeting individuals who had been diagnosed with mild traumatic brain injuries. To ensure a reliable sample, inclusion criteria consisted of patients aged 18 to 65 who presented with mTBI symptoms and were stable enough to participate in cognitive assessments.
Upon obtaining informed consent, participants underwent a structured cognitive assessment utilizing the BTACT, which comprises a series of concise cognitive tasks administered over the telephone. The nature of the tasks—designed to evaluate aspects such as attention, memory, and processing speed—allowed for swift administration while still capturing critical cognitive domains impacted by mTBI. The average duration of the assessment was approximately 10 minutes, making it suitable for the fast-paced environment of an emergency department.
To enhance the robustness of the findings, researchers also collected demographic data, clinical histories, and injury specifics from medical records. Variables such as age, gender, and prior medical conditions were documented, alongside detailed information about the nature and mechanism of the head injuries sustained by participants. This comprehensive data collection allowed for thorough analyses of how cognitive outcomes associated with mTBI might vary across different patient profiles.
Data analysis was carried out using appropriate statistical methods to evaluate the relationship between cognitive performance on the BTACT and various demographic and clinical factors. Concurrently, qualitative feedback was gathered from both participants and emergency department staff regarding the assessment’s practicality and integration into clinical workflows. This dual approach facilitated a nuanced understanding of not only the cognitive metrics but also the real-world applicability of BTACT in emergency settings.
Informed by previous research on cognitive assessments, this study additionally aimed to critique the existing literature on mTBI management and identify potential gaps where BTACT could add value, paving the way for future exploration into its use as a standardized tool in emergency departments. The overall methodology was crafted to ensure that the findings would be relevant and actionable, contributing to enhanced cognitive care for individuals affected by mild traumatic brain injury.
Key Findings
The findings of the study illuminated several critical insights regarding the use of the Brief Test of Adult Cognition by Telephone (BTACT) in emergency department settings for patients with mild traumatic brain injuries (mTBI). A total of 150 participants were assessed, revealing significant variability in cognitive performance contingent on various demographic and clinical factors.
First and foremost, the cognitive assessments indicated that a notable percentage of participants exhibited deficits in at least one cognitive domain evaluated by the BTACT. Specifically, 45% of participants demonstrated impaired attention and processing speed, two critical areas often affected by mTBI. These results underscore the subtle but crucial cognitive impairments that can arise following even mild injuries, which may not be immediately recognized in acute medical settings.
The analysis further demonstrated that younger patients (ages 18-30) tended to perform better on the BTACT compared to older participants (ages 50-65), suggesting that age may play a role in cognitive resilience post-injury. Moreover, patterns emerged indicating that patients with a history of prior head injuries exhibited significantly lower cognitive scores compared to those without such backgrounds. This correlation highlights the importance of considering patients’ medical histories when evaluating cognitive outcomes, as cumulative trauma can exacerbate the effects of subsequent mTBIs.
Additionally, when considering the integration of BTACT into the emergency department workflow, qualitative feedback from both medical staff and participants was overwhelmingly positive. Healthcare providers reported that BTACT’s brevity and ease of administration allowed for efficient cognitive assessments without compromising the quality of patient care. Patients appreciated the opportunity to be evaluated in a familiar and low-pressure environment, further enhancing the acceptability of the tool.
Statistical analyses revealed strong correlations between BTACT scores and various indicators of mTBI severity, such as loss of consciousness and post-traumatic amnesia duration. The data suggested that lower BTACT scores were associated with longer recovery times and increased likelihood of requiring rehabilitation services, providing valuable prognostic information that can aid clinical decision-making.
Overall, these findings advocate for the viability of BTACT as a practical cognitive assessment tool in emergency settings, demonstrating not only its effective application but also its potential to inform both immediate care and longer-term management strategies for patients with mTBI. The outcomes also call for a re-evaluation of cognitive monitoring protocols within emergency medicine, emphasizing the need for systematic cognitive assessments as standard practice in the management of mild traumatic brain injuries.
Strengths and Limitations
The study showcasing the use of the Brief Test of Adult Cognition by Telephone (BTACT) in emergency departments presents several strengths that underscore its potential for advancing cognitive assessment in clinical practice. One of the primary strengths is the study’s alignment with real-world clinical scenarios. By recruiting participants directly from an urban emergency department, the research ensures that the findings are highly relevant. The practicality of implementing BTACT in a busy emergency setting caters to the unique challenges faced by healthcare providers—particularly the time constraints that often accompany immediate patient care.
Another strength lies in the BTACT’s design itself. Composed of straightforward, time-efficient tasks, it requires about ten minutes for administration. This brevity makes it feasible for use in emergency contexts compared to traditional neuropsychological assessments, which can take significantly longer to complete. As a tool specifically validated for rapid evaluation, BTACT stands to increase the likelihood of cognitive assessments being routinely integrated into emergency protocols, thereby enhancing the detection of cognitive impairments in mTBI patients.
Additionally, the study effectively combines both quantitative and qualitative methodologies to provide comprehensive insights into the feasibility of BTACT. The collection of demographic, clinical, and injury data, alongside participant and provider feedback, allows for a multi-faceted analysis. Such an approach not only enriches the understanding of cognitive outcomes but also highlights the assessment’s acceptability among both patients and clinicians.
However, there are notable limitations to the study that warrant consideration. One limitation is the cross-sectional design, which restricts the ability to draw causal inferences from the findings. While correlations between cognitive performance and various demographic factors were identified, the lack of a longitudinal framework means that the evolution of cognitive function over time remains unclear.
Moreover, the study’s sample size, though reasonably robust, may not be entirely representative of the broader population of mTBI patients. The focus on a single urban emergency department may introduce a selection bias, particularly if the demographic and clinical characteristics of this group differ significantly from other settings or populations. A more diverse sample across multiple geographic locations could provide a fuller picture of BTACT’s applicability.
Furthermore, while the study did account for certain demographic variables and prior head injuries, additional factors such as socio-economic status, mental health history, and education level could also influence cognitive outcomes but were not explicitly analyzed. Without these considerations, the assessment of cognitive function may lack depth, potentially overlooking critical influences on performance.
In summary, while the investigation into BTACT’s feasibility presents compelling evidence for its use within emergency departments, the findings must be interpreted with caution. The strengths underscore its potential as a rapid cognitive screening tool, yet the limitations highlight the need for further research to validate these results across diverse populations and settings. Continued exploration of cognitive assessment tools like BTACT may ultimately enhance the understanding and management of mild traumatic brain injuries in clinical practice.