Clinical Characteristics
Patients diagnosed with PCDH19-clustering epilepsy often present with a distinct array of clinical features that can vary widely among individuals. One of the hallmark symptoms is the occurrence of seizures, which exhibit a fluctuating spectrum ranging from focal seizures to generalized tonic-clonic seizures. The age of onset typically occurs in early childhood, usually between the ages of 1 to 5 years, marking a critical developmental stage. These seizures may evolve over time, with some patients experiencing an escalation in seizure frequency and severity as they grow older.
A significant characteristic seen in many patients is the co-occurrence of developmental delays and cognitive impairment. Notably, intellectual disability tends to be more prevalent in females compared to males due to the X-linked nature of the PCDH19 gene. This leads to a spectrum of neurodevelopmental outcomes, and around 70-80% of individuals may face learning difficulties. Social interactions and communication skills can also be adversely affected, compounding the challenges faced by these patients and their families.
Additional clinical features include behavioral problems, ranging from anxiety disorders to more severe psychiatric conditions, which can arise as secondary complications of living with a chronic seizure disorder and its associated challenges. In some cases, patients may exhibit features akin to autism spectrum disorders, further complicating their behavioral profile.
| Clinical Feature | Percentage of Patients Affected |
|---|---|
| Seizures | 100% |
| Developmental Delays | 70-80% |
| Intellectual Disability | Variable (more common in females) |
| Behavioral Problems | Common |
The clinical characteristics associated with PCDH19-clustering epilepsy are multi-faceted, with seizures being the most evident symptom. However, the accompanying developmental, cognitive, and behavioral issues significantly impact the quality of life for affected individuals and their families, necessitating a comprehensive approach to care and management.
Diagnostic Challenges
Diagnosing functional (dissociative) seizures in the context of PCDH19-clustering epilepsy presents unique challenges, largely due to the overlapping clinical features seen in both disorders. Distinguishing between these types of seizures and other forms of epilepsy is paramount, yet can be particularly difficult when symptoms manifest in varying degrees of severity and frequency. Clinicians often rely on a detailed history and specific clinical observations to guide their assessments.
One of the principal diagnostic challenges arises from the fact that patients with PCDH19-clustering epilepsy may exhibit both epileptic and non-epileptic seizures. This dual presentation can lead to misdiagnosis, especially in patients with complex seizure profiles. For instance, dissociative seizures might mimic the clinical symptoms of epileptic seizures, including loss of consciousness and uncontrolled movements, complicating the clinical picture further.
Current diagnostic criteria and tools, such as video EEG monitoring, are essential for differentiating between these seizure types, yet they are not universally available. As a result, some patients may remain undiagnosed or misdiagnosed for extended periods. Additionally, the stigma surrounding psychiatric conditions can impede appropriate diagnosis, as presenting symptoms may contribute to biases in clinical judgment. For many physicians, the lack of awareness about the intersection of psychiatric and neurological disorders may lead to underrecognition of functional seizures.
Healthcare providers often need to utilize a multidisciplinary approach, involving neurologists, psychiatrists, and psychologists, to achieve a comprehensive evaluation. Collaboration among specialists can provide a more holistic view of the patient’s health, interpretation of symptoms, and lead to better treatment plans. However, the absence of standardized diagnostic protocols can result in variability of care across different medical facilities.
The following table summarizes some of the key variables that contribute to the diagnostic challenges faced in identifying functional seizures among patients with PCDH19-clustering epilepsy:
| Diagnostic Challenge | Description |
|---|---|
| Overlap of Symptoms | Functional seizures can mimic epileptic seizures, leading to misdiagnosis. |
| Access to Testing | Not all facilities offer video EEG monitoring, which is crucial for accurate diagnosis. |
| Stigma and Bias | Judgments about psychiatric symptoms may affect the diagnostic process. |
| Lack of Standardization | Difference in care standards and protocols across facilities can hinder diagnosis. |
Thus, the complexity surrounding the diagnosis of functional seizures in PCDH19-clustering epilepsy necessitates a thorough and collaborative approach to improve diagnostic accuracy and patient outcomes. Addressing these challenges is crucial in enabling timely and effective management of both seizure types, helping to enhance the overall well-being of affected individuals.
Management Strategies
Effective management of PCDH19-clustering epilepsy, particularly when functional (dissociative) seizures are involved, demands a multi-faceted and individualized approach. Given the complexity of symptoms and the overlapping features between different seizure types, treatment plans must be tailored to meet the unique needs of each patient. This section discusses various management strategies that encompass pharmacological treatments, psychotherapeutic interventions, lifestyle modifications, and comprehensive multidisciplinary care.
Pharmacological management primarily focuses on the control of seizures. First-line antiepileptic drugs (AEDs) are often prescribed, and the choice of medication hinges on the specific seizure types present. Commonly used AEDs include:
| Antiepileptic Drug | Mechanism of Action | Commonly Used For |
|---|---|---|
| Levetiracetam | Modulates neurotransmitter release | Partial and generalized seizures |
| Topiramate | Inhibits excitatory neurotransmission | Broad-spectrum seizures |
| Lacosamide | Enhances slow inactivation of sodium channels | Partial-onset seizures |
In cases where patients experience functional seizures alongside epileptic seizures, it is critical to consider the use of psychotropic medications that manage underlying psychiatric conditions, such as anxiety or mood disorders. Antidepressants or anxiolytics may be indicated based on the individual’s symptoms, providing a dual benefit of supporting mental health while addressing seizure frequency.
In addition to pharmacotherapy, psychotherapeutic interventions play a crucial role in managing functional seizures. Cognitive Behavioral Therapy (CBT) has gained recognition for its efficacy in helping patients understand and cope with their conditions, thereby reducing the frequency of dissociative seizures. Engaging in therapy can also improve emotional well-being and enhance coping mechanisms, as patients learn to recognize triggers and develop strategies for managing stress and anxiety.
Furthermore, lifestyle modifications are essential in supporting overall health and possibly mitigating seizures. Recommendations may include:
- Maintaining a regular sleep schedule to prevent sleep deprivation, which can exacerbate seizures.
- Adopting a balanced diet rich in nutrients that support brain health.
- Incorporating regular physical activity, which is beneficial for both physical and mental health.
- Implementing stress-reduction techniques such as mindfulness, yoga, or meditation.
Collaboration among healthcare providers including neurologists, psychiatrists, psychologists, and primary care physicians is vital to ensure comprehensive care. Regular follow-up appointments facilitate adjustments in treatment plans as necessary based on the patient’s evolving clinical picture. This multidisciplinary approach allows for a thorough assessment of both the neurological and psychological aspects of the condition, enhancing the efficacy of management strategies and improving patient outcomes.
Managing PCDH19-clustering epilepsy and accompanying functional seizures requires a comprehensive and individualized approach. By combining pharmacological interventions, psychotherapy, lifestyle modifications, and multidisciplinary collaboration, healthcare providers can better address the complexities of this condition, thereby improving the quality of life for affected individuals and their families.
Future Research Directions
The landscape of understanding and managing PCDH19-clustering epilepsy, especially in relation to functional (dissociative) seizures, is continually evolving. Future research is essential to uncover more precise mechanisms of this condition, enhance diagnostic protocols, and develop targeted treatments. Key areas for exploration include genetic studies, advances in neuroimaging, and prospective clinical trials to assess therapeutic interventions.
Enhancing our grasp of the genetic underpinnings of PCDH19-clustering epilepsy is paramount. As the condition is linked to mutations in the PCDH19 gene, further genetic analysis could reveal hitherto unidentified variants and their associated phenotypes. Studies involving larger sample sizes along with diverse populations may facilitate the identification of genotype-phenotype correlations, ultimately leading to improved personalized healthcare strategies. Furthermore, this research could aid in predicting which patients are at higher risk for developing more severe symptoms, including functional seizures.
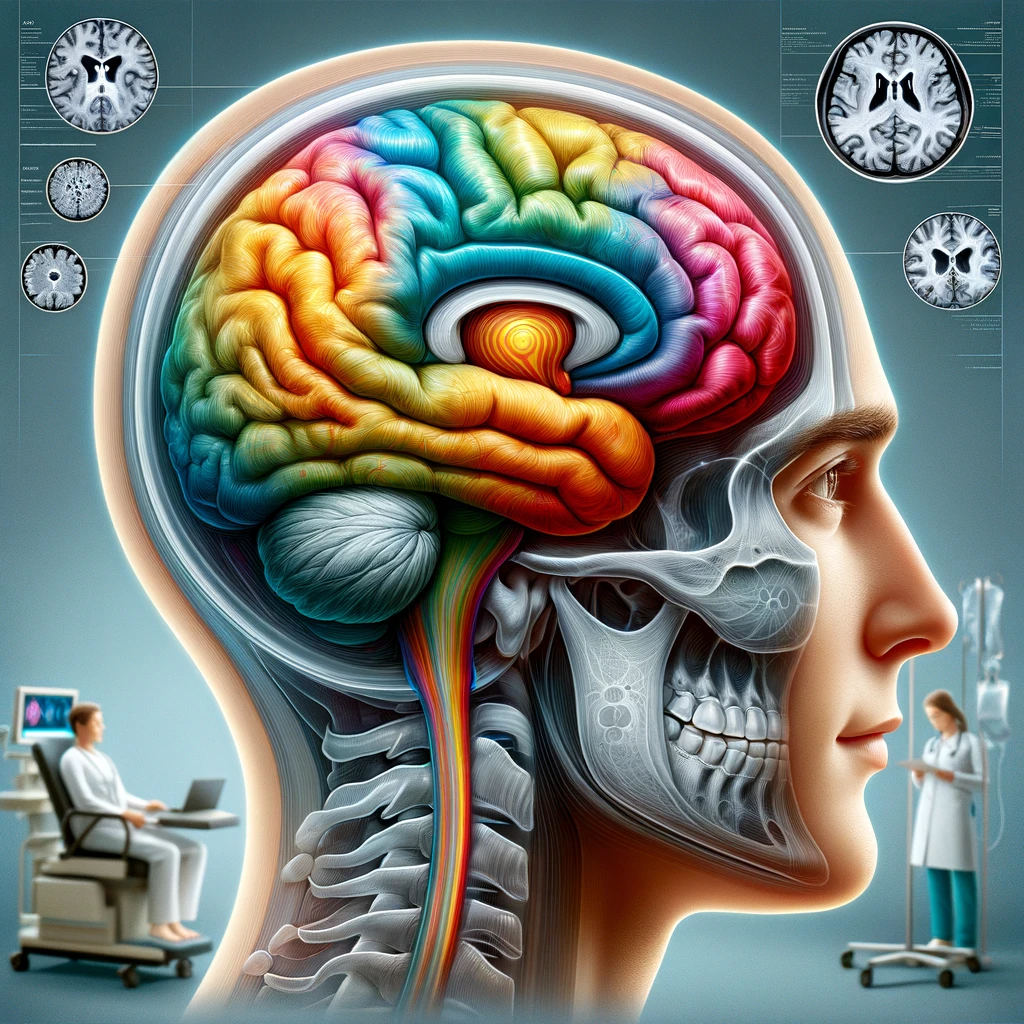
Neuroimaging techniques, particularly functional MRI (fMRI) and diffusion tensor imaging (DTI), also present opportunities for advancement. By exploring how brain connectivity and activity patterns differ in patients with PCDH19-clustering epilepsy compared to those with other epilepsy forms, researchers may gain insights into the specific neural pathways implicated in both epileptic and dissociative seizures. Such knowledge could guide the development of neurobiological markers for better diagnostic accuracy, aiding in the differentiation of seizure types, which is a current clinical challenge.
Investigations into the psychosocial dimensions and their interplay with seizure activity warrant attention as well. Understanding how factors such as stress, trauma, and social support influence both the frequency and severity of functional seizures can provide a more holistic view of patient care. This could further inform trauma-informed care approaches in clinical practice, which are essential for addressing the psychological comorbidities associated with chronic epilepsy.
Additionally, the exploration of novel therapeutic approaches is crucial. Current pharmacotherapy options can be augmented by investigating the efficacy of integrative treatment models, such as combined cognitive-behavioral therapies, mindfulness-based stress reduction, and potentially even neuromodulation techniques like transcranial magnetic stimulation (TMS). Clinical trials investigating these modalities could clarify their role in managing not just seizures, but also the emotional and psychological dimensions of the disorder.
Finally, the implementation of longitudinal studies will be vital. Following cohorts over time will not only help understand the natural progression of PCDH19-clustering epilepsy but also capture the long-term effects of various management strategies. Such data will enhance evidence-based approaches to care and inform clinical practice guidelines.
The future of research in PCDH19-clustering epilepsy is directed towards a multidisciplinary approach that combines genetics, neuroimaging, psychosocial understanding, and innovative therapies. Prioritizing these aspects will enhance diagnostic rigor and treatment outcomes, ultimately leading to improved quality of life for patients suffering from this complex condition.