Understanding Functional Neurological Disorder
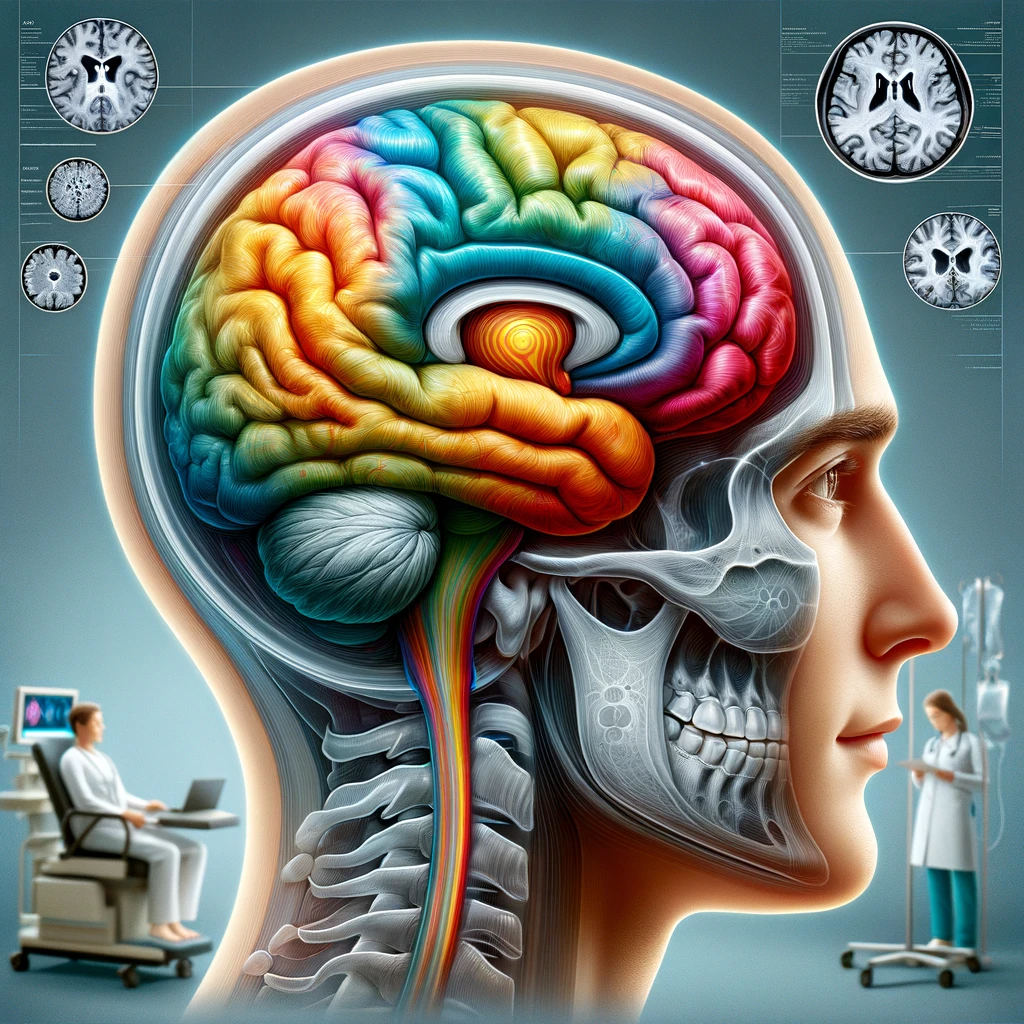
Functional Neurological Disorder (FND) is a condition characterized by neurological symptoms that do not have a clear organic cause. These symptoms can include motor dysfunctions, sensory disturbances, and seizures, often referred to as psychogenic non-epileptic seizures (PNES). FND represents a complex interplay between neurological function and psychological factors, making it uniquely challenging to diagnose and treat.
Patients with FND often present with symptoms that mimic traditional neurological disorders such as epilepsy, movement disorders, or even stroke. However, unlike these conditions, FND does not show abnormal findings on standard neurological tests like MRI or EEG. The symptoms can be as varied as weakness, abnormal movements, and loss of consciousness, which may lead to significant impairment in quality of life.
Research indicates that FND may arise from various factors, including psychological trauma, stress, and underlying psychological conditions. It’s believed that these factors can disrupt normal brain function, leading to the manifestation of neurological symptoms. A common theme in many FND cases is the presence of psychological distress, although the specific relationship between psychological issues and the neurological symptoms can be intricate and multifaceted.
A key aspect of understanding FND is recognizing that it is not a voluntary condition. Patients do not consciously choose to exhibit these symptoms, and they often seek medical help due to the distress caused by their experiences. This highlights the need for empathy and careful communication during the diagnostic process to ensure patients feel supported rather than stigmatized.
The clinical presentation of FND can often lead to misdiagnosis. In many instances, patients may undergo extensive testing and treatment for conditions they do not have, which can exacerbate feelings of frustration and helplessness. Therefore, improving awareness and education among healthcare professionals regarding FND is essential for timely and accurate diagnosis.
A comprehensive analysis of studies involving FND patients provides valuable insights into the disorder’s prevalence and characteristics. For instance, a recent survey might highlight the following key aspects of FND:
| Aspect | Findings |
|---|---|
| Prevalence in Neurology Clinics | Approximately 10-30% of patients presenting with seizures may have FND. |
| Demographics | Predominantly affects younger women, typically between ages 20-40. |
| Comorbid Conditions | High comorbidity with anxiety disorders, depression, and PTSD observed in a substantial number of cases. |
| Diagnostic Delay | Average time from symptom onset to correct diagnosis may exceed 5 years. |
Understanding Functional Neurological Disorder is crucial for developing effective diagnostic strategies and treatment plans. This condition emphasizes the importance of a biopsychosocial approach, integrating both neurological and psychological perspectives to improve patient care and outcomes.
Diagnostic Approach and Challenges
Diagnosing Functional Neurological Disorder (FND), particularly when it presents as psychogenic non-epileptic seizures (PNES), poses substantial challenges. Clinicians must navigate a labyrinth of symptoms that often overlap with other neurological conditions while working to exclude organic causes. The first step in this diagnostic journey involves a thorough clinical assessment which integrates history-taking, physical examinations, and the interpretation of diagnostic tests.
During the clinical evaluation, it is crucial to obtain a comprehensive patient history that includes details about the onset of symptoms, their variability, and any associated psychological or emotional stressors. The description of the episodes, such as triggers, duration, and witnessing reports from bystanders, is essential in differentiating between epileptic seizures and PNES. Notably, patients experiencing PNES typically display movements that are different in nature from those observed during true epileptic episodes, offering critical clues for differential diagnosis.
To substantiate the diagnosis of FND, neurophysiological tests like EEG are employed to evaluate electrical activity in the brain. In cases of true epilepsy, an EEG will generally reveal abnormal waveforms. However, EEG findings in patients with PNES often remain normal or show inconsistencies with ictal patterns, supporting a diagnosis of FND rather than epilepsy.
A significant hurdle is the potential for misinterpretation of the results. For instance, patients might inadvertently undergo extensive testing such as repeated MRIs or EEGs despite the absence of organic pathology. This not only prolongs the diagnostic process but may also reinforce the patient’s anxiety and despair. Reports indicate that delays in diagnosis can extend beyond five years, further magnifying the difficulties faced by both patients and healthcare providers.
Table 1 summarizes the diagnostic process for FND, highlighting key components:
| Step | Description |
|---|---|
| Clinical History | Gathering comprehensive details including symptom onset, triggers, and psychological background. |
| Physical Examination | Conducting a neurological assessment to explore motor functions, reflexes, and sensory responses. |
| Neurophysiological Testing | Using EEG to identify patterns characteristic of seizures or to confirm absence of epilepsy. |
| Multidisciplinary Evaluation | Involvement of neurologists, psychiatrists, and psychologists can enhance understanding and treatment options. |
| Feedback and Education | Communicating findings to the patient sensitively to foster understanding and reduce stigma. |
Moreover, the interdisciplinary approach in evaluating FND underscores the necessity for collaboration between neurologists, psychologists, and other specialists. This team perspective helps clinicians better interpret complex cases and identify comorbid psychiatric disorders that often accompany FND. Mental health evaluations can be crucial, as patients frequently have histories of trauma, anxiety, or stress-related disorders, all of which can impact the presentation and progression of FND symptoms.
Effective communication with patients is paramount during the diagnostic process. Educating patients about FND helps reduce feelings of isolation and stigma associated with their symptoms. Furthermore, creating a supportive environment enhances trust and may encourage more transparent discussions about their psychological well-being, which can be pivotal in guiding treatment strategies.
In summary, diagnosing FND requires a thoughtful and patient-centered approach that carefully considers both neurological and psychological aspects. Enhanced awareness and thorough training for medical professionals about the nuances of FND could lead to better diagnostic accuracy, reduced delays, and overall improved outcomes for patients navigating this challenging condition.
Case Presentation and Analysis
A 32-year-old woman was referred to our neurology department after experiencing recurrent episodes of hemoptysis, which were accompanied by apparent seizures. Her medical history was notable for anxiety and a previous diagnosis of depression, particularly following a traumatic event five years prior. Despite extensive prior evaluations, including bronchoscopies and imaging studies of the chest, no obvious pulmonary or cardiovascular abnormalities were identified that could explain the hemoptysis or the seizure-like episodes, suggesting a more complex underlying condition.
Upon presentation, the patient described her episodes as sudden onset without any preceding aura. Witnesses reported that she would slump to the ground, exhibit jerking movements, and moments of unresponsiveness. Initially, these features suggested the possibility of epilepsy. However, simultaneous video-electroencephalography (EEG) monitoring during one of her episodes showed a normal EEG without the classical spiking patterns associated with seizures. This finding raised the suspicion of psychogenic non-epileptic seizures (PNES) rather than true epileptic activity.
Further investigation involved a multidisciplinary approach, including input from a psychologist. An in-depth interview revealed that the patient had been under significant stress due to personal circumstances, which included the recent loss of a close family member and ongoing work-related pressures. These emotional triggers correlated closely with the onset of her symptoms, aligning with the hypothesis of FND.
To better elucidate the relationship between her psychological state and neurological symptoms, we categorized her clinical presentation and findings in the following table:
| Feature | Description |
|---|---|
| Neurological Symptoms | Seizure-like episodes with movement disorders; no EEG abnormalities noted. |
| Psychological Background | History of anxiety, depression, and significant recent stressors. |
| Triggers | Episodes coincided with high-stress events in her personal life. |
| Comorbid Conditions | Anxiety disorder and depression diagnosed prior to observation. |
| Diagnostic Tests | Normal neuroimaging and EEG; no organic pathology found. |
The interplay between her psychological status and neurological symptoms was evident, highlighting the critical need for clinicians to consider psychological factors that may manifest as neurological symptoms. Given her diagnosis of FND with PNES, a comprehensive treatment plan was initiated that included cognitive behavioral therapy (CBT) to address her anxiety and coping mechanisms for managing stress. This psychological intervention was complemented by physical therapy to help mitigate the performance anxiety surrounding her episodes.
Regular follow-up appointments were scheduled to monitor her progress and assess the efficacy of the multidisciplinary management approach. Within a few months, the patient reported a notable reduction in the frequency of her episodes, along with improvements in her mental health and daily functioning. The supportive environment fostered during therapy sessions encouraged her to openly discuss her experiences and underlying emotional difficulties, reinforcing the idea that understanding the psychological context was critical in her recovery.
In analyzing this case, it becomes increasingly clear that a unified approach involving neurologists, psychologists, and therapists forms the cornerstone of effective treatment for patients with FND. Initially perceived as purely neurological, her symptoms were eventually recognized as being closely linked to psychological trauma and emotional distress. This illustrates the complexity of diagnosing and treating FND, where collaboration among different specialties allows for a more holistic understanding and effective management of the condition.
Treatment Strategies and Outcomes
In managing Functional Neurological Disorder (FND), particularly in cases presenting as psychogenic non-epileptic seizures (PNES), the adoption of a comprehensive and individualized treatment approach is essential. Such a strategy often requires the integration of both psychological interventions and physical rehabilitative therapies, reflecting the complex biopsychosocial nature of FND.
Cognitive Behavioral Therapy (CBT) has emerged as a vital component of treatment for patients diagnosed with FND, especially those experiencing PNES. CBT aims to enhance the patient’s understanding of the relationship between thoughts, emotions, and behaviors, which can significantly affect their symptoms. By addressing cognitive patterns and modifying irrational beliefs, patients can learn effective coping mechanisms to manage stress and emotional challenges. This therapeutic approach encourages self-reflection and promotes healthier ways of thinking, ultimately leading to an improvement in both psychological and neurological symptoms.
Physiotherapy also plays a crucial role in the rehabilitation of FND patients. Techniques such as movement re-education, relaxation exercises, and functional training can help restore physical function and alleviate associated symptoms. For patients grappling with movement disorders related to FND, physical therapists can design tailored programs aimed at increasing mobility and reducing anxiety about physical performance, thereby fostering confidence in their physical capabilities.
The multidisciplinary framework for treating FND often includes collaboration between neurologists, psychologists, psychiatrists, and physiotherapists. This integrated care model ensures that all aspects of the patient’s condition are addressed. Frequent and open communication among healthcare providers is crucial for monitoring progress and adjusting treatment plans as needed.
An important consideration in developing treatment strategies is the recognition of acute episodes, such as those experienced in PNES. For some patients, strategies such as mindfulness and grounding techniques may be employed during episodes to help the individual regain a sense of control and reduce distress. Educating patients about their condition fosters empowerment and may alleviate fears associated with their symptoms.
The administration of pharmacological treatments remains controversial, as there is no specific medication for FND. However, antidepressants or anxiolytics may be considered in cases where patients exhibit significant comorbid psychiatric conditions such as anxiety or depression. The primary goal of medication, when used, should be to enhance the overall therapeutic efficacy of psychotherapy and supportive interventions rather than to serve as a standalone solution.
Monitoring treatment outcomes is essential. Assessments can include self-reported measures of symptom frequency, intensity, and quality of life, alongside objective evaluations from healthcare professionals. In the case of our previously discussed patient, follow-up indicated a significant decline in the frequency of episodes over six months of treatment, with a corresponding enhancement in her mental health. The data presented in a comparative format underscores these findings:
| Outcome Measure | Before Treatment | After Six Months |
|---|---|---|
| Frequency of Episodes | 4 episodes per week | 1 episode every two weeks |
| Self-reported Anxiety Levels (1-10 scale) | 8 | 4 |
| Quality of Life Assessment | Lower than average | Average or above average |
The notable improvements observed in this patient resonate with findings across various studies reflecting that patients who receive a multidisciplinary and empathetic approach often experience better outcomes. Persistent follow-up and adaptive treatment plans based on the evolving needs of the patient form the cornerstone of effective management strategies for FND.
Collectively, these treatment strategies underscore the importance of approaching FND as a complex interplay of neurological and psychological factors, necessitating a personalized and compassionate response to enhance both the quality of life and functionality of affected individuals.