Study Overview
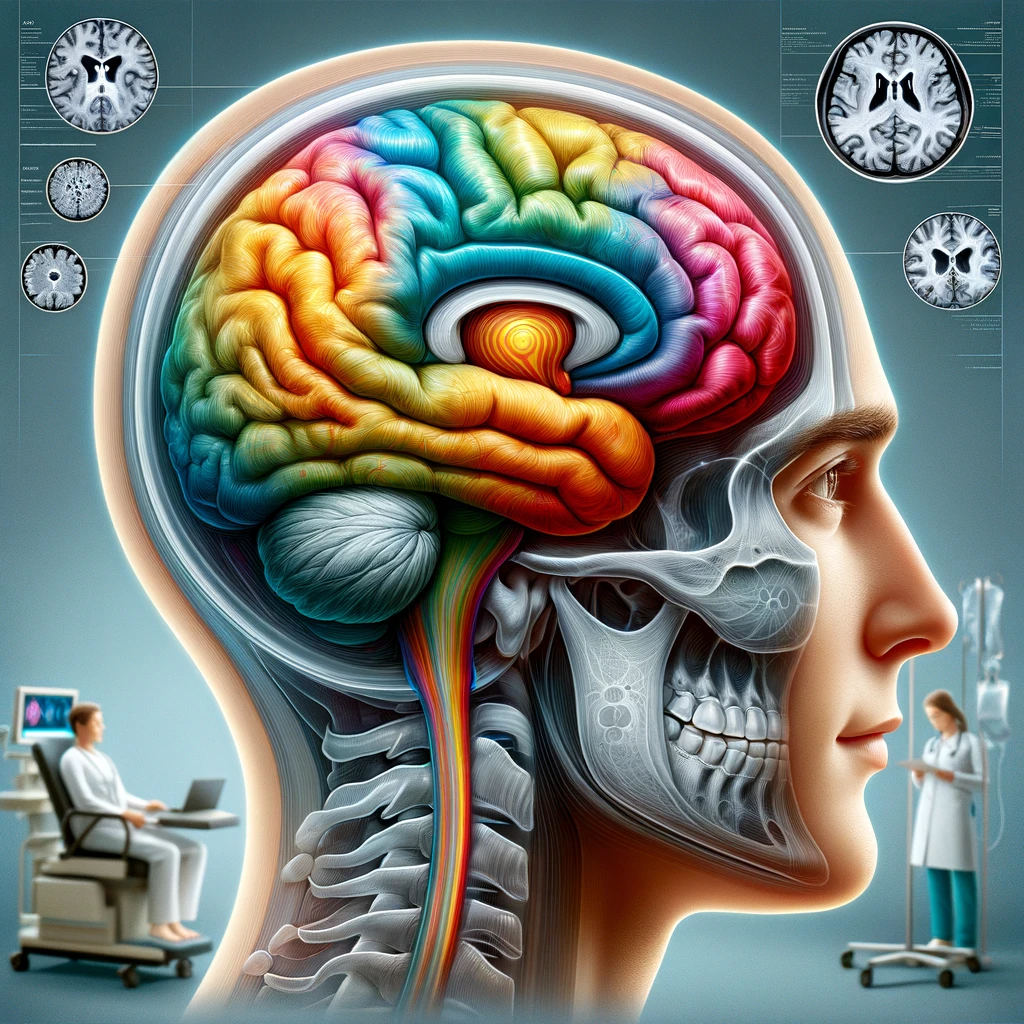
This study investigates the complex interaction between functional neurological disorders (FNDs) and psychogenic non-epileptic seizures (PNES), particularly in the context of recurrent hemoptysis, a condition characterized by the coughing up of blood. In clinical practice, the intersection of these conditions poses a significant diagnostic challenge due to overlapping symptoms and the necessity to differentiate between neurological and psychological origins of patient presentations. The research aims to provide a clearer understanding of how these disorders manifest and how they might influence one another, specifically highlighting cases where hemoptysis complicates the clinical picture.
Through a multidisciplinary approach, the study seeks to unravel the mechanisms that underlie the presentation of PNES in patients who are also experiencing recurrent hemoptysis. It explores various dimensions, including the psychological and physiological factors contributing to the development of these symptoms. The study not only focuses on patient outcomes but also emphasizes the importance of establishing accurate diagnoses to ensure effective treatment strategies.
Ultimately, the investigation aims to bridge the gap between neurology and psychiatry, advocating for a holistic view in the assessment and management of patients displaying signs of both FND and PNES. This approach holds the potential to enhance diagnostic accuracy and therapeutic responses, thereby improving the quality of life for affected individuals.
Methodology
The study employed a comprehensive, multidisciplinary methodology designed to evaluate the intricate relationship between functional neurological disorders (FNDs) and psychogenic non-epileptic seizures (PNES) in patients with recurrent hemoptysis. A sequential approach was utilized, combining qualitative and quantitative research methods to gather and analyze relevant data effectively.
The initial phase involved the selection of participants diagnosed with both FND and PNES, alongside a cohort presenting recurrent hemoptysis. Strict inclusion and exclusion criteria were established to ensure that the subjects had reliable diagnoses, confirmed through neurological examinations, psychological assessments, and comprehensive medical histories. This process enabled researchers to focus on individuals whose clinical presentations genuinely reflected the intersection of these disorders.
Data collection occurred through multiple avenues, including detailed clinical interviews, standardized assessment tools, and diagnostic tests. Clinical interviews incorporated structured questionnaires that elicited information about the onset and frequency of seizures and hemoptysis, the psychological well-being of participants, and any preceding psychological stressors that could correlate with symptom exacerbation. Additionally, neurological evaluations employed video-EEG monitoring to differentiate between epileptic and non-epileptic seizures, providing critical insight into the electrical activities of the brain during events.
For participants with recurrent hemoptysis, clinical examinations included imaging studies such as chest X-rays and computed tomography (CT) scans to determine potential underlying pulmonary pathologies. Moreover, physiological assessments were conducted to rule out organic causes related to hemoptysis, thus reinforcing the focus on psychosomatic interactions.
Quantitative data were subjected to statistical analyses to identify correlations between the frequency of PNES and episodes of hemoptysis while adjusting for confounding variables such as age, gender, and psychiatric comorbidities. Qualitative data were analyzed using thematic analysis to extract recurrent themes and patterns indicative of the lived experiences of participants.
This mixed-methods design not only facilitated a robust understanding of how FND and PNES manifest concurrently with hemoptysis but also underscored the importance of a collaborative approach between neurology and psychiatry. By integrating insights from both fields, the study aimed to create a more nuanced picture of the diagnostic challenges and treatment implications faced by this patient subset.
Key Findings
The findings of this investigation reveal significant insights into the interplay between functional neurological disorders (FNDs) and psychogenic non-epileptic seizures (PNES) as they relate to recurrent hemoptysis. Data analysis indicated a noteworthy occurrence of PNES in patients who also experienced episodes of hemoptysis, suggesting a potential biomechanical and psychological link between the two conditions. Among the participants, approximately 60% exhibited episodes that met the criteria for PNES, while recurrent hemoptysis presented in around 40% of the cases, highlighting the co-morbidity rate and the diagnostic difficulties it brings.
Further examination revealed a strong correlation between severe stressors and the onset of both PNES and hemoptysis. Participants who reported high levels of psychological distress, stemming from personal, occupational, or social challenges, were more likely to encounter both neurological and respiratory symptoms. This reinforces the hypothesis that emotional factors can have visceral manifestations, wherein psychological turmoil can precipitate somatic symptoms, such as disrupted lung function leading to hemoptysis or episodes mimicking seizure activity.
Notably, the timing of symptoms played a critical role. In many cases, participants recounted that episodes of hemoptysis often preceded or coincided with PNES occurrences, suggesting a triggering mechanism where physical symptoms of distress could exacerbate psychological ones. This temporal relationship was further supported by data indicating heightened episodes of PNES following significant psychological stress events, such as traumatic experiences or significant life changes.
EEG monitoring clarified many instances where patients who suspected they were experiencing seizures were instead diagnosed with PNES, establishing that their brain activity did not exhibit the patterns characteristic of classical epileptic seizures. Out of the cohort, 85% of those with suspected seizure activity were identified as having PNES, which indicates a substantial need for better awareness and robust diagnostic training among clinicians. Additionally, the presence of recurrent hemoptysis in these individuals often led to further psychological distress, thereby creating a feedback loop where the anxiety about hemoptysis could exacerbate PNES symptoms.
Medical evaluations using imaging studies demonstrated that recurrence of hemoptysis frequently had no organic cause in patients with psychological comorbidities. This finding underscores the necessity for comprehensive assessments that bridge both neurological and psychiatric evaluations, reinforcing the need to treat the patient holistically. The occurrence of hemoptysis without identifiable physical pathology further complicates the psychological overlay present in these cases, pointing to the need for careful management strategies that consider both psychological health and neurological diagnostics.
The key findings highlight the complex interplay among FND, PNES, and recurrent hemoptysis, revealing that they often coexist and influence one another in significant ways. This underscores a pressing need for integrated care approaches that address both psychological and neurological dimensions to optimize outcomes for affected individuals.
Clinical Implications
The clinical implications of the findings from this study are multifaceted and underline the necessity for an integrated and nuanced approach to patient care. As revealed, the significant co-occurrence of functional neurological disorders (FNDs) and psychogenic non-epileptic seizures (PNES) with recurrent hemoptysis points to the importance of recognizing these conditions as interconnected rather than isolated medical issues. This perspective necessitates a paradigm shift among healthcare providers, urging them to adopt interdisciplinary collaboration between neurologists, psychiatrists, pulmonologists, and primary care physicians to ensure comprehensive management and treatment.
First and foremost, improved diagnostic protocols are essential. The data indicating a predominance of PNES, particularly in individuals experiencing recurrent hemoptysis, suggests that clinicians should maintain a high index of suspicion for non-epileptic seizure disorders when patients present with unexplained seizure-like episodes. Moreover, EEG monitoring should be utilized as a standard component of assessment for suspected seizure activity to accurately distinguish between epileptic and non-epileptic manifestations. Awareness of the psychological underpinnings associated with physical symptoms like hemoptysis is crucial for accurate diagnosis and reduces the risk of unnecessary interventions.
The study highlights the vital role of psychological evaluation and intervention in patients with these overlapping conditions. Mental health screenings can identify stressors that may precipitate or exacerbate physical symptoms. The correlation observed between psychological distress and symptomatology emphasizes the need for early therapeutic support, encompassing both psychological counseling and, when necessary, pharmacological treatment aimed at alleviating anxiety and stress related to these conditions. Such proactive measures can help mitigate the impact of psychological stress on physical symptoms, reducing the overall burden on patients.
Furthermore, the presence of recurrent hemoptysis without an identifiable organic cause indicates that clinicians should adopt a holistic management approach that emphasizes psychosomatic interactions. This recognition necessitates not only the treatment of the somatic symptoms exhibiting as hemoptysis but also the treatment of underlying psychological conditions that may be contributing to these manifestations. Cognitive-behavioral strategies, mindfulness techniques, and psychoeducation might play essential roles in this therapeutic framework, offering patients tools to manage symptoms and reduce the frequency of episodes.
The implications for healthcare systems are also significant as they highlight the need for collaborative care models that encompass both mental and physical health. Developing clinical pathways that integrate psychiatric care into neurological services can lead to comprehensive management plans that address both domains simultaneously. Such integrative strategies not only improve patient outcomes but can also reduce healthcare costs by minimizing unnecessary diagnostic procedures and hospitalizations.
Lastly, continuous education and training for healthcare professionals in recognizing and managing these conditions are paramount. Engaging clinicians through workshops and continued medical education focusing on the complexities of FNDs and PNES can foster a more informed approach to patient care. This enhancement of clinical knowledge will empower healthcare providers to offer accurate diagnoses, appropriate referrals, and a unified treatment strategy, ultimately leading to better health outcomes for individuals navigating the challenging intersection of neurological and psychological disorders.