Understanding Coprolalia
Coprolalia is a complex neurological phenomenon often associated with Tourette Syndrome (TS) and characterized by involuntary utterances of socially inappropriate or obscene words and phrases. It is important to note that not all individuals with TS exhibit coprolalia; in fact, it only affects a subset of the population. The term derives from the Greek roots “copro,” meaning waste, and “lalia,” meaning speech, effectively describing the often taboo nature of the words involved.
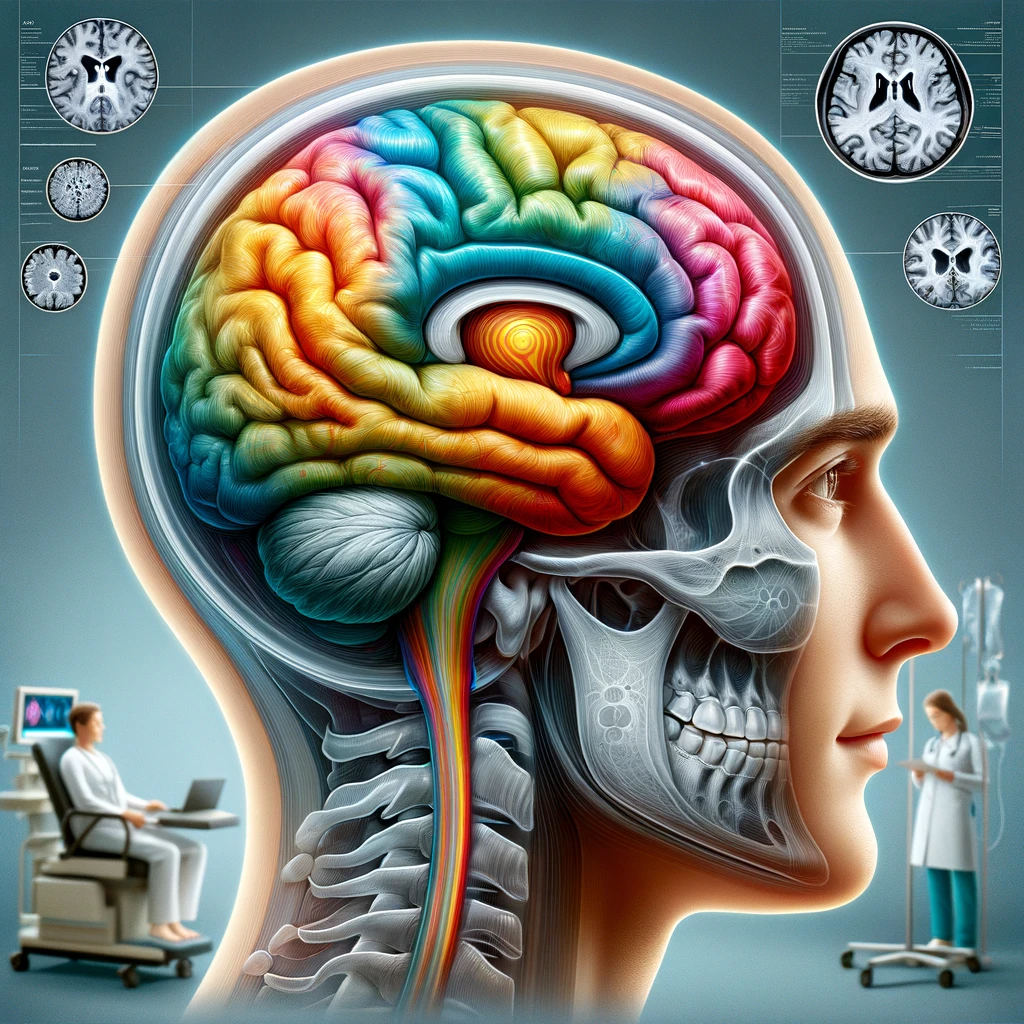
Understanding coprolalia requires a multifaceted approach that takes into account both neurological and psychological factors. This involuntary vocalization is thought to be a result of heightened activity in specific brain areas linked to speech production and impulse control. The basal ganglia, which play a significant role in motor control and behavior regulation, are believed to contribute to the manifestation of coprolalia. Overactivity in these regions can lead to the inappropriate verbalizations that characterize the condition.
Furthermore, the nature and content of coprolalic utterances can vary significantly among individuals. Some may display a preference for certain types of words, such as curse words or slurs, while others might utter nonsensical phrases or even words that are contextually inappropriate but not overtly offensive. This variability suggests underlying differences in individual neurobiology and psychological processing.
Additionally, cultural and environmental factors can influence the perception and expression of coprolalia. The social stigma associated with such utterances can lead to significant emotional distress for individuals affected by TS, compelling some to suppress their vocalizations, which can further exacerbate anxiety and behavioral issues. This complexity makes it essential to adopt a nuanced perspective when examining coprolalia within the broader context of Tourette Syndrome.
To facilitate a more comprehensive understanding, the following table summarizes key characteristics of coprolalia:
| Characteristic | Description |
|---|---|
| Definition | Involuntary utterance of socially inappropriate or obscene words. |
| Prevalence | Affects approximately 10-15% of individuals with Tourette Syndrome. |
| Neural Basis | Involvement of the basal ganglia and related circuits. |
| Variability | Content of utterances can vary widely individual to individual. |
| Psychosocial Impact | Can lead to social stigma and emotional distress. |
Coprolalia represents a unique intersection of neurological, psychological, and social dimensions that necessitates further exploration to improve the understanding and management of this symptom within the context of Tourette Syndrome.
Prevalence and Characteristics
The prevalence of coprolalia in individuals diagnosed with Tourette Syndrome is notably lower than commonly perceived. Studies indicate that only a small percentage of people with TS exhibit this symptom, with estimates ranging from about 10% to 15%. This subgroup can experience coprolalia as one of several tics, which may include other involuntary movements or sounds. It’s essential to acknowledge that this specific symptom can create a stark contrast in experiences among those living with TS, leading to a further misunderstanding of the condition as a whole.
The characteristics of coprolalia encompass a variety of verbal expressions that may be offensive, nonsensical, or contextually inappropriate. The utterances often bear no reflection of the individual’s personal beliefs or language norms, emphasizing the involuntary nature of this phenomenon. Some individuals with coprolalia may primarily use explicit language, while others might resort to obscure phrases or socially benign words that are uttered inappropriately. This variability in vocalization reflects the unique neurophysiological profiles and psychological configurations of those affected.
In addition to the types of words spoken, the intensity and frequency of coprolalia can vary widely among individuals. Some may experience frequent outbursts, whereas others may speak less often or find themselves able to suppress the behavior in certain environments. Such variations can be influenced by factors such as stress levels, social situations, or overall emotional state.
Understanding the prevalence and characteristics of coprolalia through data can help illuminate the phenomenon further. The following table summarizes key findings related to the characteristics and manifestations of coprolalia:
| Characteristic | Description |
|---|---|
| Prevalence in TS | Coprolalia occurs in 10-15% of individuals with Tourette Syndrome. |
| Types of Utterances | Includes curse words, socially inappropriate phrases, and nonsensical speech. |
| Frequency | Varies from frequent outbursts to occasional utterances, influenced by situational stressors. |
| Contextual Influence | Individuals may suppress utterances in certain settings, affecting expression. |
| Emotional Impact | The expression can lead to feelings of embarrassment, isolation, and stigma. |
Consequently, the experience of coprolalia extends beyond mere vocalizations; it intertwines with the complexities of social environment, individual variability, and psychological well-being, highlighting the need for a comprehensive understanding of this condition in the context of Tourette Syndrome.
Mechanisms Behind Coprolalia
The origins of coprolalia lie in the intricate neural networks responsible for language production and motor control. Research indicates that dysregulation within the basal ganglia, a group of nuclei in the brain essential for voluntary motor control, plays a pivotal role in this phenomenon. In particular, disruptions in the striatum, a core component of the basal ganglia, may lead to the involuntary vocalization that characterizes coprolalia. This region interacts with other parts of the brain, including the cortex and thalamus, facilitating a complex dialogue that governs speech and movement.
Studies utilizing neuroimaging techniques such as functional MRI (fMRI) have demonstrated heightened activity in these regions during coprolalic episodes. This overactivity suggests that individuals with coprolalia may have neural pathways that are hyper-responsive, leading to an inability to control or inhibit certain verbal impulses. The precise mechanisms are not entirely understood; however, it is clear that the condition does not simply reflect learned behavior but rather a neurological dysfunction.
Additionally, the role of dopamine in Tourette Syndrome is significant. Dopaminergic pathways are implicated in the modulation of tics and coprolalia. Fluctuations in dopamine levels can affect impulse control and may precipitate the verbal outbursts associated with coprolalia. Evidence suggests that medications aimed at regulating dopamine transmission can alleviate symptoms for some individuals, providing insight into the potential biochemical contributors to the condition.
Another layer to consider is the psychological dimension of coprolalia. Stress, anxiety, and environmental triggers can exacerbate symptoms, leading to increased frequency and intensity of verbal outbursts. This underscores the need for a comprehensive understanding that incorporates both the neurological underpinnings and the psychological context in which coprolalia manifests. Individuals who experience heightened emotional states may find it even more challenging to manage their symptoms, often leading to a cycle of increased stress and further tics.
The variability in the expression of coprolalia emphasizes the need for a personalized approach to management. Factors such as individual background, contextual understanding, and family dynamics can significantly influence how coprolalia presents in each person. Understanding these mechanisms can inform tailored therapeutic interventions aimed not only at reducing the frequency of coprolalic episodes but also at mitigating the psychological impact they have on affected individuals.
The interplay of neurological, biochemical, and psychological factors contributes to the complex nature of coprolalia in individuals with Tourette Syndrome. Further research into these mechanisms is crucial for developing effective treatment strategies and enhancing the quality of life for those affected.
Rethinking Treatment Approaches
Current treatment approaches for coprolalia within the context of Tourette Syndrome demand a reevaluation to enhance their effectiveness and address the multifaceted nature of the condition. Traditional treatment modalities have primarily focused on pharmacological interventions, behavioral therapies, and a combination of both, but these methods might not fully cater to the diverse needs of individuals affected by coprolalia.
Pharmacotherapy remains a cornerstone of treatment, particularly with medications that target dopamine pathways, such as antipsychotics and selective serotonin reuptake inhibitors (SSRIs). These medications have shown varying levels of effectiveness; some individuals report significant reductions in the frequency and intensity of their coprolalic utterances. However, the side effects associated with these drugs can be considerable, including weight gain, sedation, and a potential exacerbation of tics. Consequently, it is critical to adopt a careful and individualized approach to medication, considering both the benefits and drawbacks for each patient.
Table 1 below summarizes common pharmacological treatments for coprolalia and their efficacy:
| Medication Class | Efficacy | Potential Side Effects |
|---|---|---|
| Antipsychotics (e.g., Haloperidol) | Moderate efficacy in reducing tics and coprolalia. | Sedation, weight gain, possible movement disorders. |
| SSRIs (e.g., Fluoxetine) | Some efficacy in managing anxiety, which may indirectly reduce tics. | Gastrointestinal disturbance, insomnia, sexual dysfunction. |
| Dopamine Depleters (e.g., Tetrabenazine) | Can reduce tics but may not specifically target coprolalia. | Depression, sedation, potential parkinsonism. |
On the other hand, behavioral therapies, particularly Comprehensive Behavioral Intervention for Tourette syndrome (CBIT), have gained recognition for their role in managing tics and associated behaviors, including coprolalia. Techniques employed in CBIT focus on increasing awareness of tics and providing individuals with strategies to manage their verbal expressions. These training sessions not only empower patients but also foster a supportive environment, which can be crucial for emotional well-being.
Psychological interventions further emphasize the integration of cognitive-behavioral therapy (CBT) and mindfulness techniques. These approaches seek to equip individuals with coping strategies that can mitigate the effects of stressors known to exacerbate coprolalia. For example, by teaching relaxation techniques and mindfulness practices, individuals may become better able to manage their emotional responses and thereby reduce the likelihood of involuntary vocalizations.
Moreover, family involvement and education are essential components of any treatment plan. By fostering a supportive family environment and promoting understanding within the household, tensions related to coprolalia can be alleviated. This environment can ultimately contribute to improved mental health outcomes for individuals with TS.
Exploring alternative therapies may also provide new avenues for treatment. Approaches such as occupational therapy, art therapy, and support groups can complement traditional treatments and offer a more holistic framework. Engaging with various therapies allows for expression, which can be empowering for those experiencing coprolalia, further promoting mental health and well-being.
The dynamic nature of coprolalia necessitates a personalized and comprehensive treatment strategy that encompasses pharmacological, behavioral, and psychological interventions. Ongoing research to discover new therapies and refine existing approaches will significantly enhance the treatment landscape, offering hope to individuals dealing with this complex condition.