Clinical Characteristics of Autonomic Movement Disorders
Patients with autonomic movement disorders (AMD) often present a complex clinical picture that can complicate diagnosis and treatment. These disorders encompass a wide range of motor symptoms that can be mistaken for other movement disorders or even psychiatric conditions. The hallmark features of AMD include abnormal autonomic dysregulation that manifests through motor symptoms, such as tremors, abnormal gait, or postural instability.
One notable characteristic of AMD is the presence of non-epileptiform spells, which are episodes where patients may display abnormal movements that can resemble seizure activity but do not have a neurological basis associated with epilepsy. These episodes can occur in the absence of convulsive activity and are often triggered by stress, emotional upheaval, or environmental stimuli. Patients might report these spells as sudden episodes where they feel as though their body is not responding as expected, often feeling lightheaded or faint.
Additionally, these patients frequently exhibit symptoms of autonomic instability, including but not limited to cardiovascular abnormalities such as orthostatic hypotension, gastrointestinal dysregulation, and changes in perspiration. These symptoms often co-occur with motor manifestations, leading to significant distress and impairment in daily functioning for affected individuals.
The severity and type of motor symptoms can vary widely across patients. Some may experience episodes that last for seconds, while others may endure prolonged disturbances, which can affect their mobility and quality of life. Studies suggest that there is often an overlap between AMD and other psychiatric or neurodegenerative disorders, complicating the clinical picture further.
Table 1 summarizes the key clinical characteristics observed in patients with AMD:
| Characteristic | Description |
|---|---|
| Non-epileptiform spells | Episodes resembling seizures without epileptic origin, often triggered by stress or emotional factors. |
| Autonomic dysregulation | Symptoms include orthostatic hypotension, gastrointestinal issues, and sweating abnormalities. |
| Motor symptoms | Motor manifestations may include tremors, impaired gait, and postural instability. |
| Symptom variability | Symptoms differ in duration, severity, and type among affected individuals. |
Understanding these clinical characteristics is essential for healthcare providers to differentiate AMD from other conditions and to devise appropriate treatment plans. A multidisciplinary approach often involving neurologists, psychiatrists, and movement disorder specialists is crucial for optimal patient outcomes.
Evaluation Methods and Diagnostic Criteria
The complexity of diagnosing autonomic movement disorders (AMD) necessitates a thorough evaluation process that integrates clinical assessments, diagnostic tests, and patient history to establish an accurate diagnosis. Given the overlap of AMD features with other movement disorders and psychiatric conditions, precise evaluation methods are essential for differentiation and subsequent treatment.
Initially, a comprehensive clinical history is gathered through patient interviews, focusing on the onset, frequency, and duration of symptoms, as well as any potential triggers. A detailed neurological examination is conducted to assess motor functions, including strength, coordination, and reflexes. During this stage, healthcare providers may utilize standardized rating scales designed to quantify the severity of movement abnormalities.
To enhance diagnostic accuracy, neurophysiological tests such as electromyography (EMG) and electroencephalography (EEG) may be utilized. EMG helps assess the electrical activity of muscles, while EEG monitors brain activity to rule out epilepsy or other neurological conditions contributing to abnormal movements. Furthermore, autonomic function tests can evaluate symptoms related to autonomic dysregulation, such as heart rate variability and blood pressure response to postural changes, providing additional insight into the patient’s condition.
In some cases, video recordings of the patient during spell episodes can be useful for comparison with recognized movement disorders. This aspect of evaluation not only aids in classification but also assists in educating both the patient and healthcare team about the disorder’s nature and behavior over time.
A multistage approach to diagnosing AMD is recommended, which may include adhering to specific diagnostic criteria established for movement disorders. For instance, the presence of features characteristic of spinal dysautonomia or reflex sympathetic dystrophy could serve as indicative markers. These criteria often encompass the following:
- Episodes of involuntary movements manifesting in the absence of identifiable neurological cause.
- Clear documentation of episodes correlating with stress, anxiety, or other psychosocial triggers.
- Autonomic symptoms coexisting with motor manifestations.
Table 2 outlines the recommended evaluation methods and diagnostic criteria applicable in distinguishing AMD from other disorders:
| Evaluation Method | Description |
|---|---|
| Clinical history and physical examination | Gathering detailed patient history and performing a neurological exam to identify symptom patterns. |
| Neurophysiological testing | EMG and EEG to review electrical activity and exclude epilepsy or other neurological disorders. |
| Autonomic function tests | Assessment of autonomic responses such as blood pressure and heart rate variability. |
| Video monitoring | Recording spells to visually compare symptoms with established movement disorder guidelines. |
Attention to the nuanced symptoms and their interrelation is paramount in the diagnostic process for AMD. Collaboration among a multidisciplinary team, including neurologists, psychiatrists, and autonomic specialists, enhances the diagnostic accuracy and helps formulate effective treatment strategies tailored to individual patient needs. By adhering to structured evaluation methods and criteria, healthcare providers can improve the identification of AMD, establishing a pathway to better management and patient care.
Outcomes of Treatment Interventions
Efforts to treat autonomic movement disorders (AMD) have evolved significantly as our understanding of these conditions deepens. Treatment outcomes can vary widely among individuals, primarily influenced by the underlying etiology of their symptoms and the specific interventions employed. A multimodal approach combining pharmacologic, non-pharmacologic, and rehabilitative strategies has shown promise in improving patient outcomes.
Pharmacological interventions often target both the motor symptoms and associated autonomic dysfunction. Medications such as beta-blockers and antidepressants (e.g., selective serotonin reuptake inhibitors) may alleviate symptoms by addressing autonomic dysregulation and reducing anxiety, which can trigger episodes. In particular, studies have reported beneficial effects of propranolol in controlling tremors and reducing the incidence of non-epileptiform spells in some patients. Antidepressants, on the other hand, may help manage psychological comorbidities that exacerbate motor symptoms. However, the response to these medications can be variable, necessitating careful monitoring and adjustment of doses.
Table 1 highlights common pharmacologic interventions and their observed outcomes:
| Medication | Target Symptoms | Reported Outcomes |
|---|---|---|
| Propranolol | Tremors, autonomic dysregulation | Reported reduction in tremor frequency and severity; fewer non-epileptiform spells. |
| SSRIs (e.g., Fluoxetine) | Anxiety, mood instability | Improved mood and reduced anxiety correlated with better overall symptom control. |
| Clonazepam | Severe motor symptoms | Decreased frequency of motor disturbances in select patients. |
Non-pharmacologic strategies are equally important in managing AMD. Cognitive-behavioral therapy (CBT) has emerged as an effective adjunct treatment, assisting patients in coping with the emotional and psychological aspects of their disorder. CBT may help reduce the perception of spells and constructive engagement in life activities, fostering improved quality of life. Additionally, personalized physical therapy aimed at enhancing motor control and strength can lead to improved functional outcomes for these patients.
Another key component in the treatment of AMD is the utilization of lifestyle modifications. Encouraging patients to adopt stress management techniques, including mindfulness and relaxation exercises, can significantly help minimize episodes triggered by stressors. Dietary changes and hydration strategies may also be crucial for managing symptoms related to autonomic instability, such as orthostatic hypotension and gastrointestinal problems.
Clinical studies assessing the effectiveness of these treatment modalities often employ standardized scales, such as the textit{Movement Disorder Society Unified Parkinson’s Disease Rating Scale} (MDS-UPDRS) or the textit{Beck Anxiety Inventory} (BAI), to quantify symptom severity before and after interventions. The longitudinal aspect of patient outcomes reveals considerable variability, underlining the importance of individualized treatment plans crafted within a multidisciplinary team setting.
Successful outcomes also hinge on patient education and involvement in their care plans. Encouraging patients to maintain a symptom diary can facilitate tracking of triggers and responses to treatment, empowering them to become active participants in their management. Ultimately, the combination of pharmacologic and non-pharmacologic interventions, tailored to the unique presentation of each patient, aims to improve not only motor function but also the overall quality of life.
Future Directions for Research
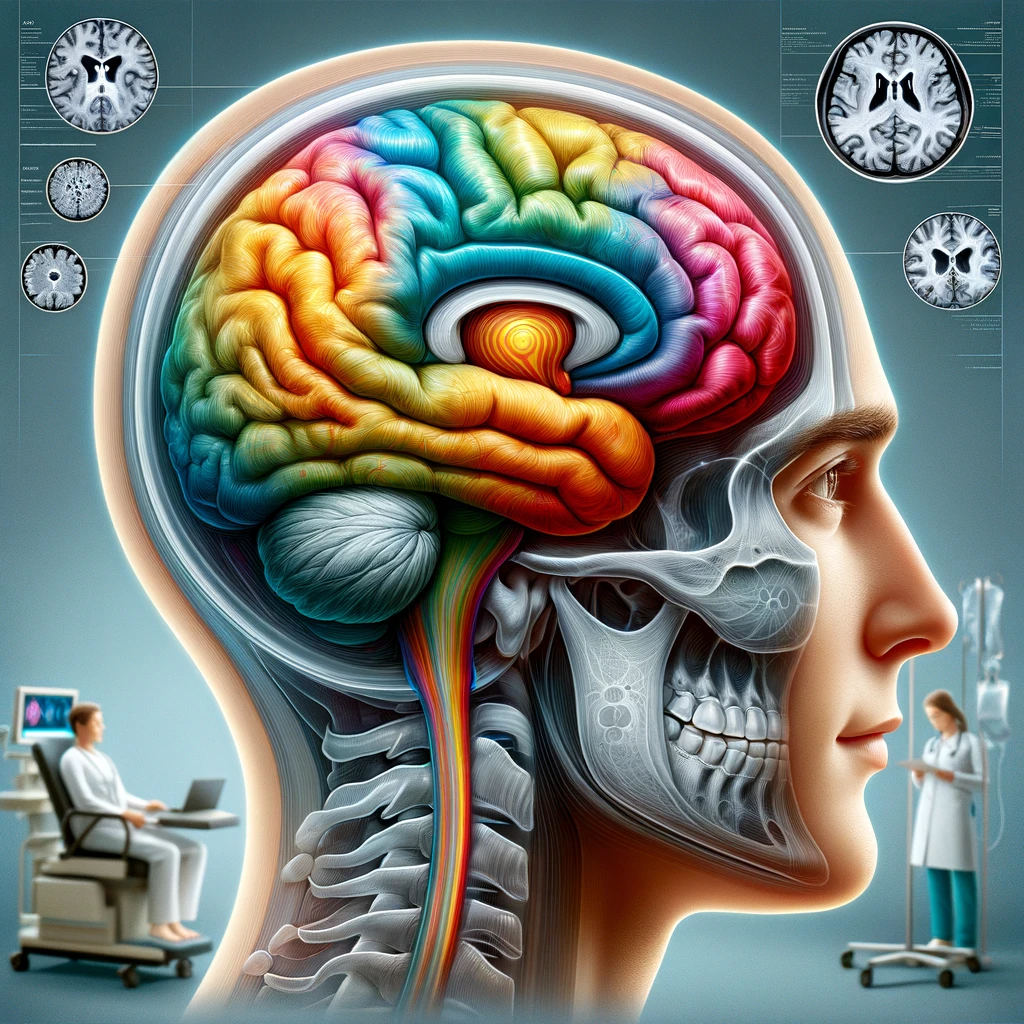
The study of autonomic movement disorders is evolving, and several future research directions warrant attention to enhance understanding and improve patient outcomes. One promising area is the exploration of the underlying pathophysiology of these disorders. Investigating the neurobiological mechanisms responsible for the development of motor symptoms and autonomic dysregulation could lead to targeted therapeutic interventions. Advanced neuroimaging techniques and biomarkers may provide insights into the neuroanatomical changes associated with AMD, offering potential for the identification of specific subtypes within the disorder.
Additionally, there is a critical need for longitudinal studies that follow patients over extended periods. This would help to elucidate the natural progression of AMD and the long-term effectiveness of various treatment modalities. Such studies could also explore the impact of early intervention strategies on symptom severity and quality of life for patients. The development of standardized protocols for data collection would facilitate comparability across different research settings and populations.
Another vital aspect of future research is the assessment of novel therapeutic approaches. For instance, emerging treatments such as neuromodulation techniques—including transcranial magnetic stimulation (TMS) and deep brain stimulation (DBS)—present intriguing possibilities. Investigating the efficacy, safety, and appropriateness of these interventions could expand treatment options available for patients with AMD, particularly those resistant to conventional therapies.
Furthermore, patient-reported outcomes should be integrated into research agendas to better align treatment strategies with the subjective experiences of affected individuals. Understanding patient priorities regarding symptom management, functional abilities, and overall quality of life can guide the development of more personalized treatment approaches.
Collaboration between clinical researchers, academic institutions, and patient advocacy groups will be essential to drive comprehensive studies. Annual conferences and symposiums focusing specifically on AMD could foster discussions and collaborations across different specialties, promoting a multidisciplinary approach to research.
The incorporation of advanced data analytics and artificial intelligence (AI) into research methodologies holds promise for enhancing diagnostic accuracy and predicting treatment responses. Machine learning algorithms could analyze large datasets to identify patterns that may not be readily apparent through traditional analytic methods. Such technological advancements could revolutionize how AMD is understood and managed.
Exploring health disparities in the management of AMD is crucial. Research focused on access to care, regional variations in treatment practices, and socioeconomic factors influencing patient outcomes can inform healthcare policies to ensure equitable treatment access for all individuals affected by these disorders.