Study Overview
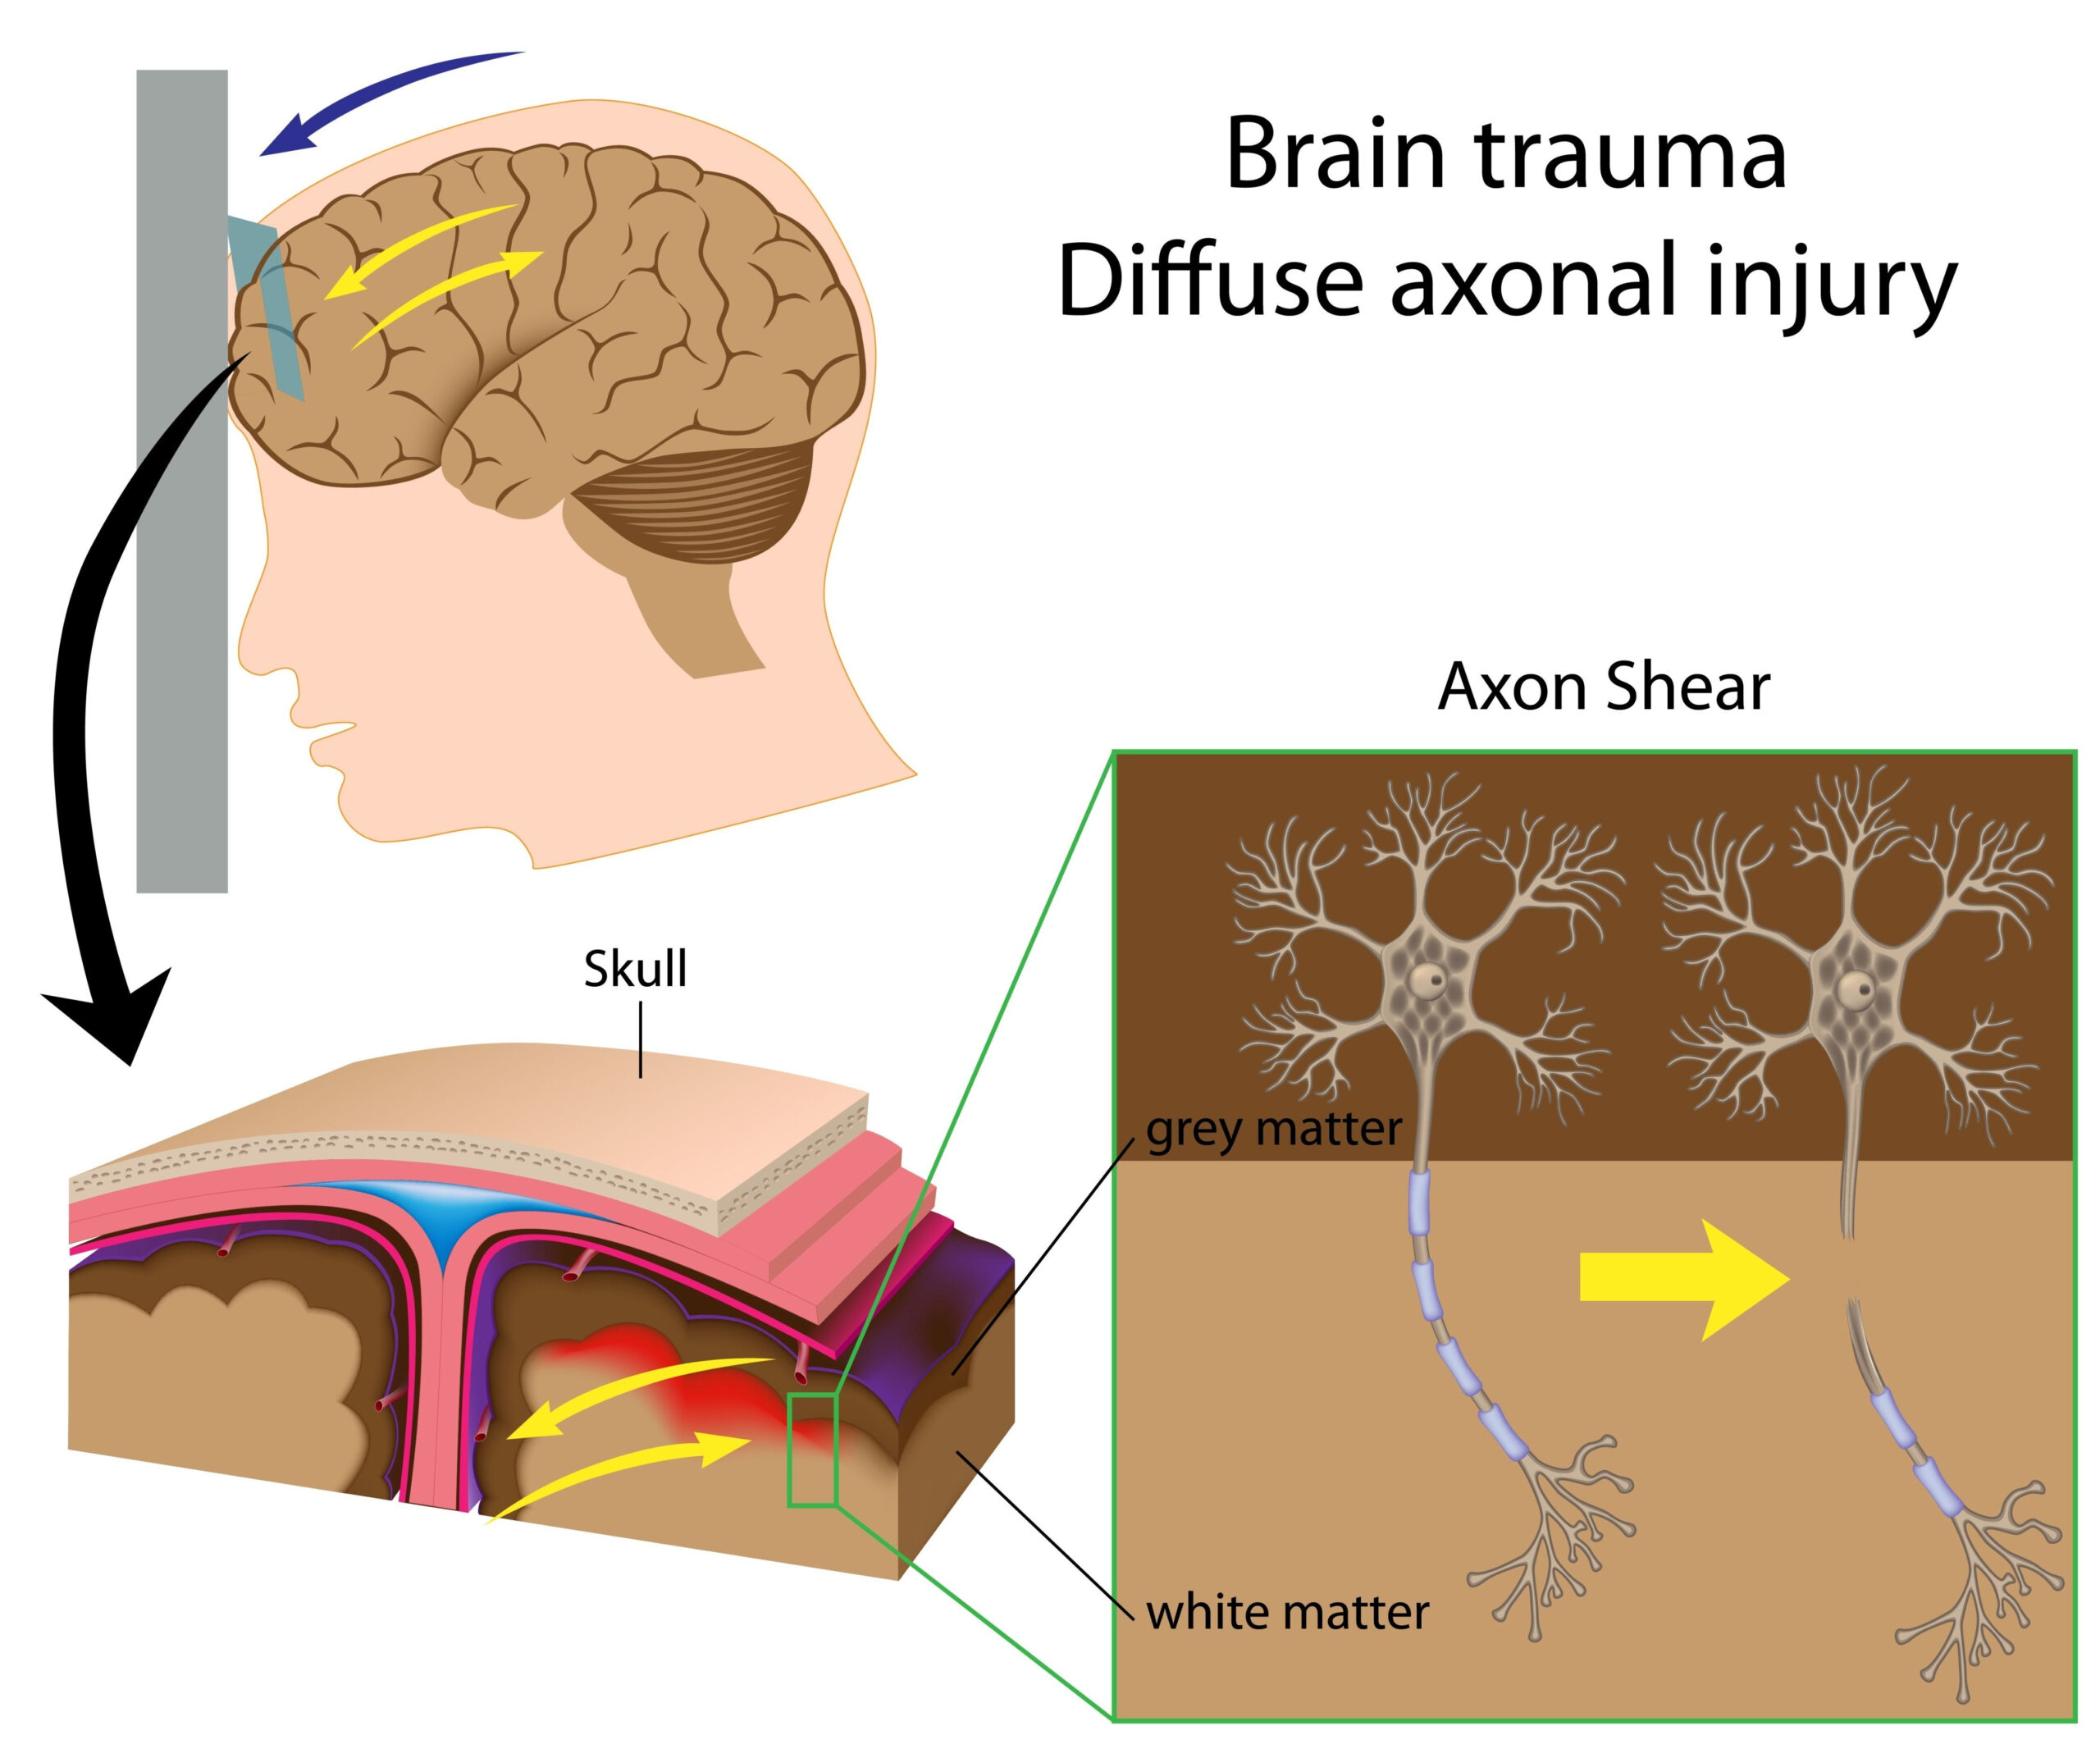
The research investigates the outcomes of older adults who experienced mild traumatic brain injury (TBI) and presented with acute subdural hematoma. This condition is characterized by bleeding on the surface of the brain, which can complicate recovery and significantly impact patient health. The study involved a comprehensive analysis of data collected from 1,157 patients across multiple centers, providing a broad perspective on the risks associated with mild TBI in this demographic.
Researchers sought to challenge the prevailing assumption that a “mild” classification based on the Glasgow Coma Scale (GCS) implies a low risk for serious complications. The GCS is a neurological scale designed to assess a patient’s level of consciousness following head injury, with higher scores indicating better responsiveness. However, the study combined clinical observations, imaging results, and outcome measures to thoroughly evaluate how mild GCS readings correlate with the severity of subdural hematomas and subsequent patient prognosis.
This work emphasizes the growing recognition that older adults may not conform to the typical injury patterns observed in younger populations. The findings highlight the need for heightened vigilance and a re-evaluation of treatment protocols, especially for older patients with mild TBI to ensure they receive appropriate care and monitoring.
Methodology
The research utilized a multicenter, retrospective cohort design to evaluate a significant number of cases involving older adults diagnosed with mild TBI associated with acute subdural hematoma. Data were meticulously gathered from a variety of facilities, ensuring a robust and diverse sample that reflects real-world clinical settings.
Inclusion criteria centered on individuals aged 65 years and older who were admitted to participating centers due to presenting symptoms indicative of TBI, specifically those who recorded a Glasgow Coma Scale (GCS) score of 13 to 15, which denotes a mild injury. Patients were further scrutinized for the presence of acute subdural hematoma diagnosed via computed tomography (CT) scans within 24 hours of admission.
The study employed thorough data collection methodologies where clinical records were analyzed to extract crucial information, including patient demographics, GCS at presentation, imaging findings, intervention criteria, and subsequent outcomes. The severity of subdural hematomas was classified based on radiological assessments, primarily evaluating the volume and midline shift of the hematomas, which can significantly influence clinical outcomes.
Moreover, researchers implemented statistical analyses to explore correlations between initial GCS scores and patient outcomes, including mortality rates, functional status at discharge, and the necessity for surgical intervention. Advanced statistical models were utilized to adjust for potential confounding factors such as age, sex, comorbidities, and other relevant clinical variables, thereby enhancing the credibility of the findings.
Patient follow-ups were critical, involving assessments during hospital stay and thereafter, allowing researchers to track recovery trajectories and long-term implications of mild TBI in this vulnerable population. The methodology was designed not only to identify immediate complications but also to understand the long-term care needs of older adults following such incidents. Thus, the comprehensive nature of the study’s methodology aims to yield insights that could inform clinical practice and improve patient-centered outcomes for older adults who suffer from seemingly mild TBI with accompanying acute subdural hematoma.
Key Findings
The analysis yielded significant insights into the outcomes for older adults with mild traumatic brain injury and acute subdural hematoma. The data indicated that among the 1,157 patients studied, a notable proportion exhibited serious complications that deviated from the anticipated outcomes dictated by their GCS scores. Specifically, even those classified as having a “mild” injury—demonstrated by GCS scores of 13 to 15—were at a concerning risk of adverse outcomes including severe neurological deterioration and increased mortality.
One of the critical findings of the study revealed that the presence of acute subdural hematoma was a more serious indicator than previously assumed. Approximately 30% of the patients diagnosed with mild TBI and subdural hematomas required urgent surgical intervention, contradicting the assumption that low GCS scores guarantee minimal treatment needs. This surgical necessity points to a critical gap in the management of older adults presenting with mild TBI, as many healthcare professionals may underestimate the seriousness of their condition based solely on GCS readings.
The study also highlighted the long-term implications of injuries sustained in this demographic. Among those patients who survived hospitalization, many experienced enduring deficits in functional abilities. Follow-up assessments reported that over 40% of patients had poor functional outcomes at discharge, which suggests that recovery from mild TBI is not uniform and often results in a significant burden on cognitive and physical abilities. Advanced statistical analyses underscored that factors such as age, pre-existing comorbidities, and the extent of the hematoma played pivotal roles in predicting these outcomes.
Interestingly, mortality rates were higher in older adults than younger populations who suffered similar injuries. The study recorded a 10% in-hospital mortality rate, with older patients facing increased vulnerability due to factors like frailty and cognitive resilience, which compound the effects of their brain injuries. These findings strongly advocate for a paradigm shift in treating mild TBI in this population, signaling the need for comprehensive evaluations that go beyond GCS scores alone.
Overall, the results emphasize the importance of elevating the standard of care for older adults with mild TBI. There is a clear necessity for healthcare practitioners to consider a lower threshold for intervention and monitoring among older patients, given the potential for severe outcomes that can arise despite a seemingly benign presentation. Thus, recognition of the intricate relationship between age, injury type, and clinical outcomes becomes crucial in reshaping treatment strategies to improve prognostic accuracy and patient care in this vulnerable population.
Clinical Implications
The findings from this study present significant implications for clinical practice, particularly in how healthcare providers approach older adults presenting with mild traumatic brain injury (TBI) and acute subdural hematoma. Given the observed relationship between Glasgow Coma Scale (GCS) scores and actual clinical outcomes, this research necessitates a reevaluation of existing protocols that may not adequately account for the nuanced responses seen in older patients.
First and foremost, it is essential for clinicians to acknowledge that a GCS score classified as “mild” does not equate to a low-risk categorization for older adults. The substantial percentage of patients demonstrating severe complications despite high GCS scores indicates that reliance solely on these scores can lead to underestimation of the severity of their condition. Therefore, healthcare practitioners must integrate a more comprehensive assessment strategy that includes detailed clinical evaluations and advanced imaging, such as computed tomography (CT) scans, as part of their initial assessment.
Moreover, the seriousness of acute subdural hematomas in this population demands immediate and proactive management. The study found that a significant proportion of patients required urgent surgical intervention, which underscores the necessity for timely decision-making and intervention. This may involve establishing lower thresholds for interventions based on clinical signs and imaging findings rather than GCS scores alone. Regular training and updates for medical staff on the latest evidence regarding TBI management in older adults could improve outcomes by ensuring that the appropriate level of care is provided as soon as possible.
The long-term functional consequences identified in the patient cohort highlight another critical area for clinical focus. With over 40% of patients facing poor functional outcomes at discharge, it becomes imperative for facilities to implement structured follow-up care and rehabilitation programs tailored specifically for older adults recovering from mild TBI. Such programs could focus on cognitive rehabilitation, physical therapy, and regular monitoring of patients’ recovery trajectories.
Additionally, optimizing communication among multidisciplinary teams involved in the care of these patients is paramount. Family engagement should also be part of the roadmap for post-discharge care, as caregivers play a crucial role in supporting recovery. Enhanced education for families regarding the potential for unexpected complications stemming from mild injuries can help in ensuring closer observation at home and thus may facilitate earlier detection of deterioration.
Importantly, the findings suggest a pressing need to rethink the educational framework for healthcare providers regarding the treatment of older adults with mild TBI. Utilizing case studies and real-world evidence like that presented in this study can aid in raising awareness of the complexities involved in managing these patients. Ongoing professional development opportunities that emphasize trauma patterns, risk factors associated with aging, and the importance of a holistic approach to patient care are vital in transforming current practices.
Ultimately, the dramatic differences seen in outcomes for older adults with mild TBI necessitate a significant shift in clinical thinking and practice. Integrating these insights into clinical frameworks will not only enhance immediate patient care but also improve long-term quality of life for this vulnerable population. Adopting a more proactive, nuanced, and multidisciplinary approach will play a critical role in safeguarding the health and well-being of older adults following mild TBIs, facilitating better outcomes and minimizing risks associated with this complex clinical scenario.