Integration of Biomarkers and PECARN Rule
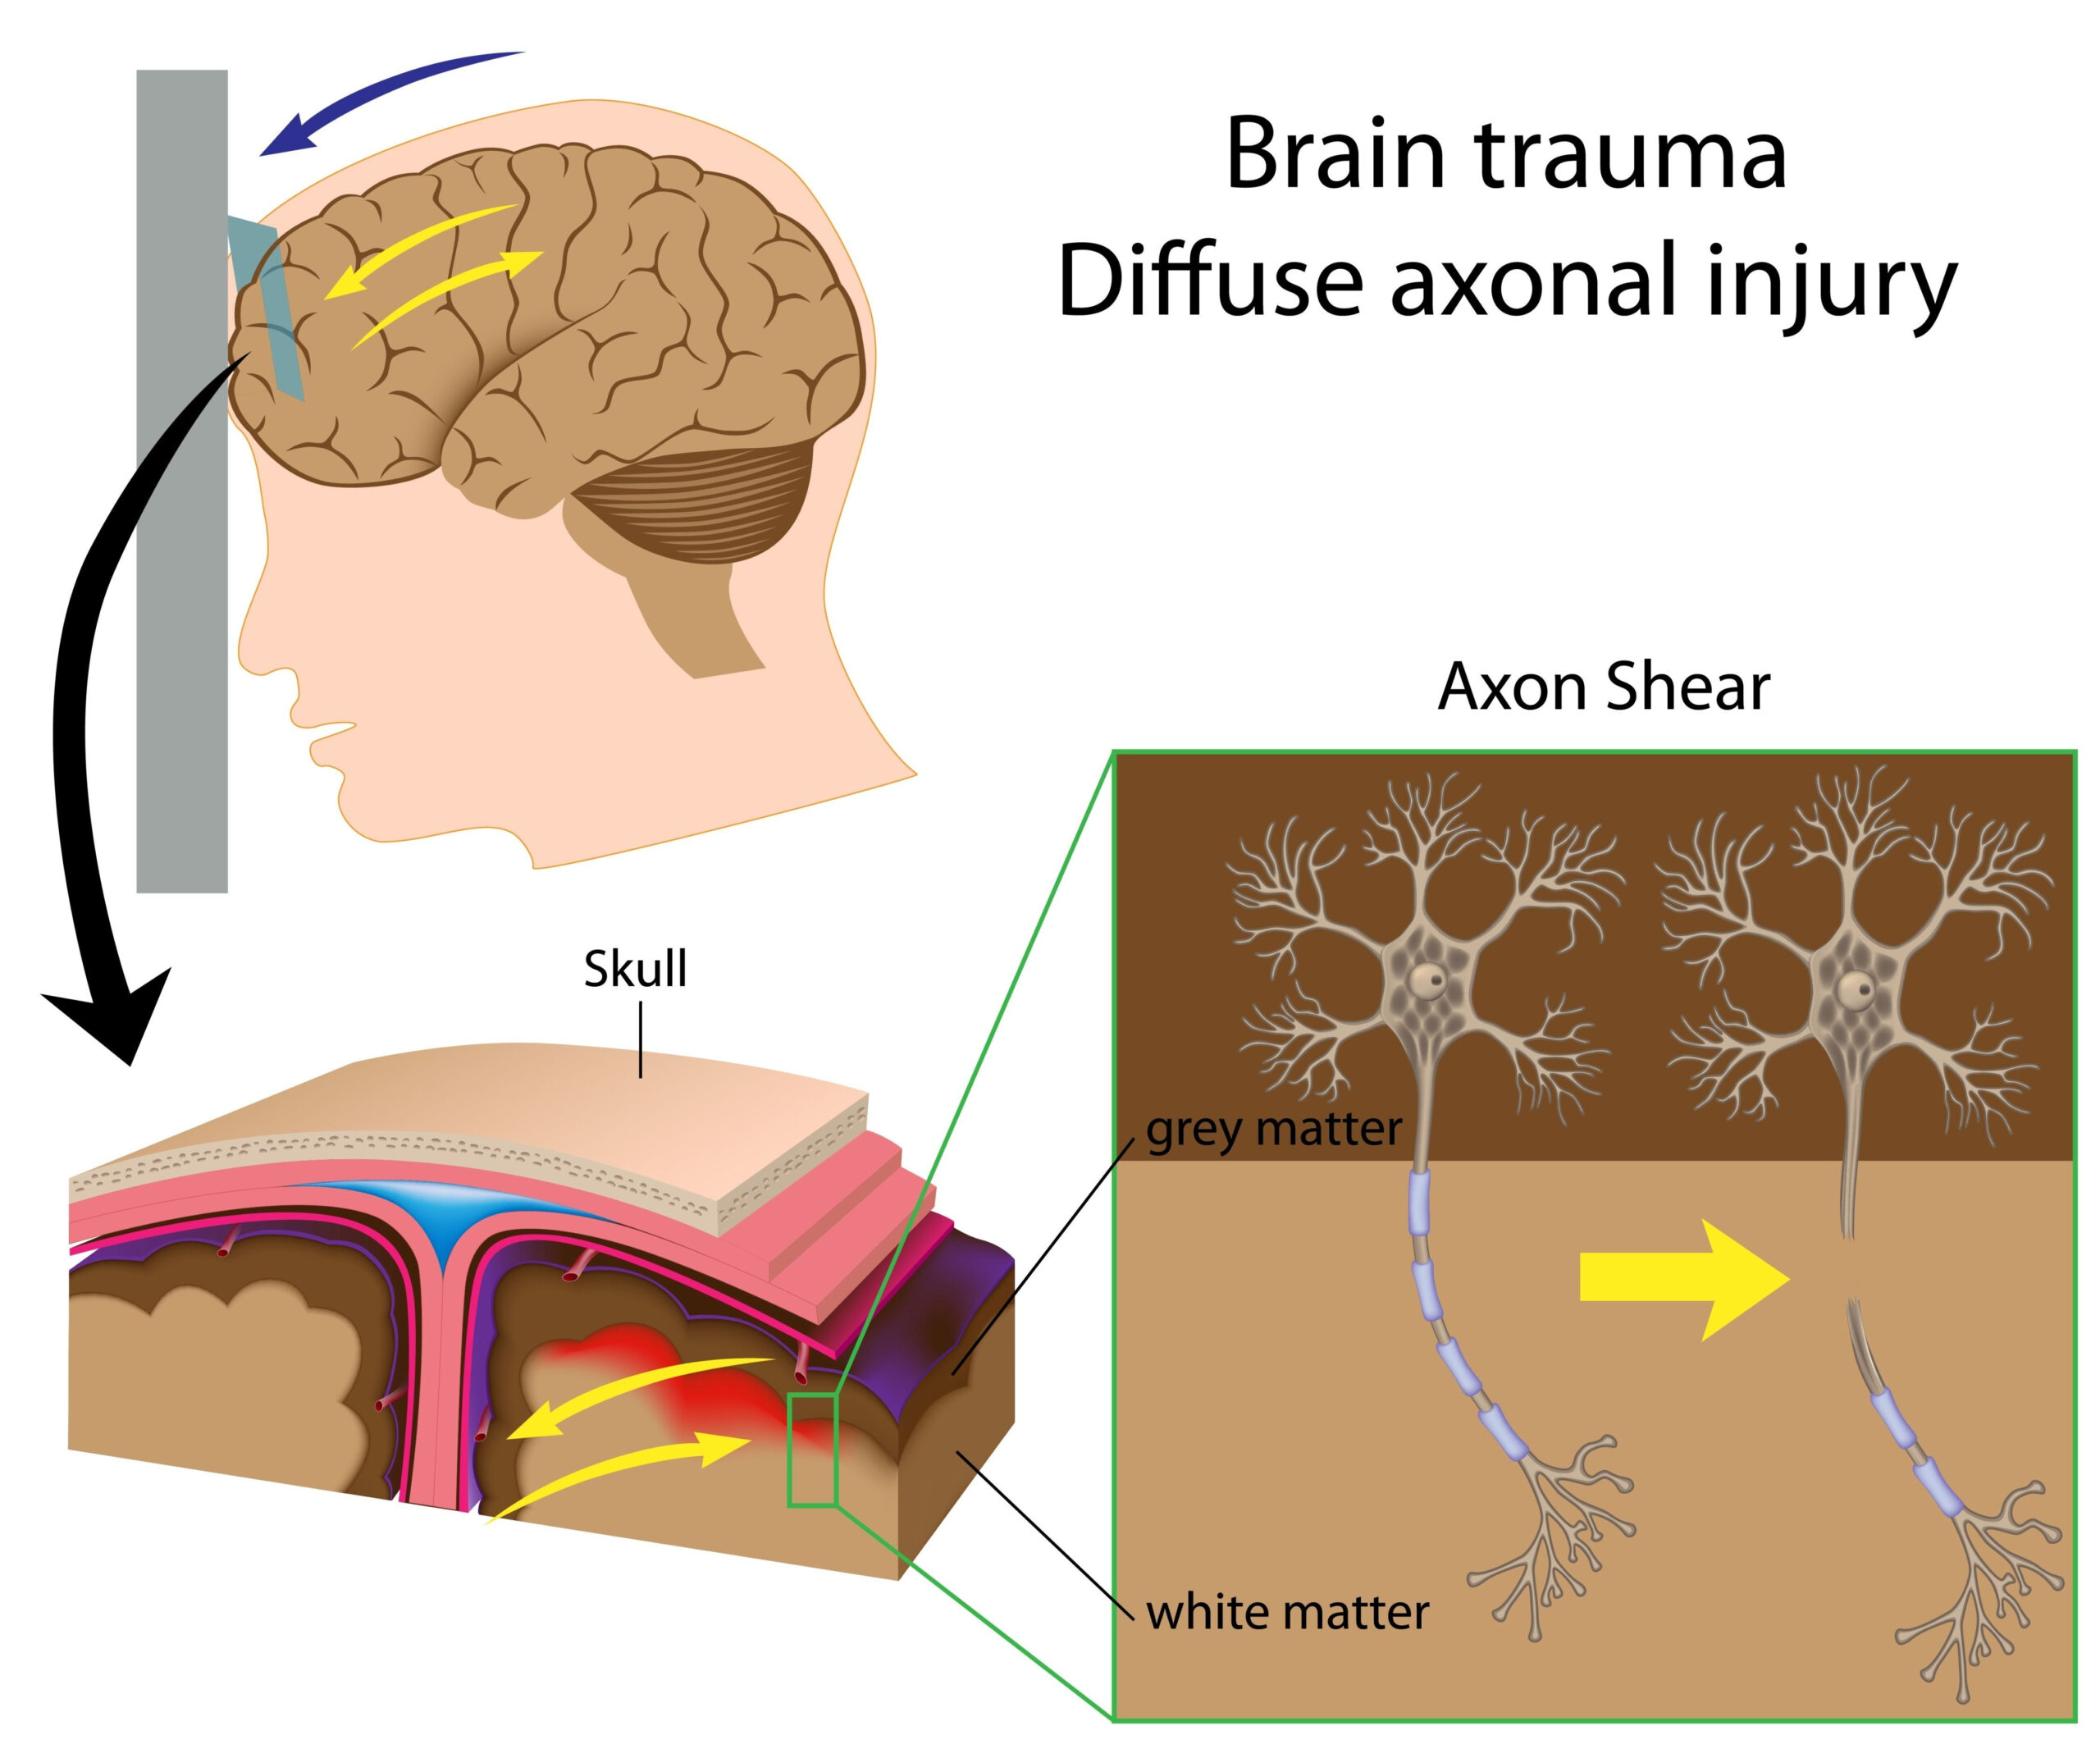
In pediatric healthcare, particularly in cases of mild traumatic brain injury (mTBI), accurate decision-making regarding the necessity of computed tomography (CT) scans is critical. The PECARN (Pediatric Emergency Care Applied Research Network) rule has emerged as a widely utilized clinical tool that aids in assessing whether a pediatric patient with mTBI requires a CT scan to evaluate potential cerebral injuries. However, its conventional use can be enhanced by integrating specific biomarkers, namely S100B and GFAP (glial fibrillary acidic protein), which have been significantly implicated in brain injury assessment.
S100B is a calcium-binding protein primarily found in astrocytes, and its elevated levels in serum can indicate neuronal damage. Likewise, GFAP serves as an essential structural protein in the central nervous system, and its presence in serum can signify astrocytic injury. Research has shown that measuring these biomarkers can provide additional information beyond clinical symptoms and the PECARN rule itself, potentially leading to more targeted and effective imaging decisions.
Integrating these biomarkers into the PECARN protocol involves a multiparametric approach to assess mTBI in children. By implementing a combined analysis of clinical indicators, age, history of loss of consciousness, and the aforementioned biomarkers’ levels, clinicians can refine their risk stratification methods. This integrated model aims to enhance diagnostic accuracy while minimizing unnecessary radiation exposure from CT scans, thereby adhering to safety protocols in pediatric care.
Furthermore, the use of these biomarkers can assist in identifying children who are at high risk for significant intracranial injuries despite not meeting the conventional PECARN criteria for imaging. This stratification is particularly valuable because it allows for individualized patient management, ensuring that those who may require further intervention are not overlooked.
As more evidence emerges regarding the efficacy of this biomarker integration, it may pave the way for new guidelines that can be incorporated into clinical practice, ultimately improving patient outcomes and optimizing resource utilization in emergency departments. Continued research is essential to validate the effectiveness of this combined approach in broader pediatric populations and various clinical settings.
Study Design and Participant Selection
This study adopted a multicenter, observational design, enrolling pediatric patients with mild traumatic brain injury who presented at emergency departments across participating hospitals. The selection criteria included children aged 0 to 18 years with a history of mTBI as defined by either a mechanism of injury suggestive of head trauma or clinical symptoms such as altered mental status, vomiting, or loss of consciousness.
Eligible participants were divided into two groups based on their PECARN criteria scores. Group 1 consisted of children considered low-risk who did not meet any high-risk PECARN criteria for CT imaging, while Group 2 comprised those deemed high-risk needing immediate CT evaluation according to the PECARN guidelines. Additionally, detailed demographic information was collected, including age, gender, and the nature of the incident leading to the injury.
Upon arrival at the emergency department, subjects underwent a thorough clinical assessment that involved standardized neurological examinations and the collection of baseline blood samples for biomarker analysis. The levels of S100B and GFAP were quantified using enzyme-linked immunosorbent assays (ELISAs), which are sensitive methods capable of detecting trace amounts of these proteins in serum samples.
Parental consent was obtained prior to participation, with comprehensive information provided regarding the study’s purpose, methodology, and potential risks and benefits. Ethical approval was acquired from relevant institutional review boards to ensure compliance with regulations governing human subject research.
The study aimed to recruit a diverse cohort that mirrors the general pediatric population to promote generalizability of the findings. Every effort was made to include patients across various demographics to better understand how different factors might influence the relevance and impact of biomarker integration with the PECARN rule.
Follow-up assessments were conducted to track clinical outcomes over a specified period, allowing researchers to evaluate the predictive validity of the combined biomarker approach when compared to standard clinical evaluation methods alone. This longitudinal aspect of the study aimed to ascertain the clinical implications of using S100B and GFAP levels not only for CT decision-making but also for subsequent management and treatment pathways for pediatric mTBI patients.
The outcomes of this study will provide pivotal insights into the feasibility and effectiveness of this integrated approach, with the potential to influence clinical practice guidelines in pediatric emergency care for mTBI cases.
Results and Interpretation
The analysis of the study outcomes reveals promising insights into the integration of S100B and GFAP biomarkers with the PECARN rule in clinical decision-making for pediatric patients suffering from mild traumatic brain injury (mTBI). Data were collected from both groups—low-risk and high-risk as defined by PECARN criteria—allowing for a comparative evaluation of the efficacy of biomarker incorporation into existing assessment protocols.
In Group 1, the low-risk cohort, biomarker levels were notably lower than in the high-risk group, with a significant fraction of these patients carrying non-elevated S100B and GFAP levels, which corresponded to low rates of clinically significant intracranial hemorrhage (ICH). This finding suggests that many children classified as low-risk indeed may not require CT imaging, reinforcing the non-invasive approach encouraged by PECARN guidelines. Conversely, within the high-risk Group 2, elevated biomarkers were more prevalent, directly correlating with a higher incidence of ICH detected through CT scans. This suggests that the biomarker levels may serve as a reliable additional prognostic tool to identify cases that necessitate more immediate imaging and intervention.
Furthermore, a striking observation was made regarding children who did not meet PECARN high-risk criteria but exhibited elevated levels of S100B and GFAP. Many of these patients were found to have injury mechanisms or clinical signs that warranted closer evaluation, prompting consideration for imaging that might have been otherwise overlooked. This correlates with prior studies suggesting that traditional clinical assessments may miss certain high-risk cases when used in isolation from biochemical markers. Therefore, the integration of biomarker assessment holds the potential to enhance diagnostic sensitivity and specificity, thereby aligning treatment with actual risk profiles.
Statistically, the integration model demonstrated a significant improvement in predictive validity for detecting ICH when S100B and GFAP levels were considered alongside clinical indicators. Using receiver operating characteristic (ROC) curve analysis, the area under the curve (AUC) for the combined approach surpassed the AUC for PECARN criteria alone, underscoring the added value of these biomarkers in refining risk stratification and decision-making processes. Moreover, the predictive power of the biomarkers offers a promising pathway for individualized patient management and tailored intervention strategies.
In terms of clinical outcomes tracked during the follow-up period, patients whose management strategies were informed by biomarker results exhibited reduced rates of unnecessary imaging and radiation exposure, with no adverse clinical consequences observed. This dual benefit—enhancing patient safety while also streamlining resource utilization—aligns well with current trends in pediatric emergency care that advocate for minimizing patient risk while ensuring comprehensive evaluation.
These results elucidate the critical role that S100B and GFAP can play in conjunction with established clinical guidelines like PECARN. As such, the study supports the hypothesis that including biomarker analysis could lead to significant improvements in clinical outcomes and it paves the way for future studies focused on optimizing management protocols for mTBI in pediatric populations.
Future Directions and Recommendations
The integration of biomarkers such as S100B and GFAP with the PECARN rule represents a promising evolution in the management of pediatric mild traumatic brain injury (mTBI). However, the next steps require careful consideration and further research to validate these findings across diverse clinical settings. One of the primary recommendations is to conduct larger-scale studies that encompass a more comprehensive range of demographics, including varied geographic, socioeconomic, and clinical backgrounds. This will help establish the generalizability of the biomarkers’ effectiveness and ensure the findings are robust across the diverse pediatric population.
In addition to expanding the size and scope of studies, it is crucial to explore the integration of these biomarkers within real-time clinical decision-making frameworks. Developing clinical pathways that systematically incorporate biomarker analysis alongside existing protocols, like the PECARN rule, can create structured approaches for emergency departments. Training healthcare providers on the significance of these biomarkers and how to interpret their levels in conjunction with clinical indicators will enhance the overall efficacy of the decision-making process.
Moreover, investigating the threshold values for S100B and GFAP that indicate the need for imaging will be essential. Establishing clear guidelines that define cut-off levels for these biomarkers can streamline processes in emergency care, aiding clinicians in quickly assessing risk and determining imaging necessity without excessive delays. Future research could also explore the temporal dynamics of these biomarkers; understanding how the levels change following injury may offer insights into the timing of imaging and intervention necessary for optimal patient outcomes.
Additionally, there is a need for multidimensional assessments that take into account not just the clinical outcomes from imaging but also long-term impacts on cognitive function and quality of life following mTBI. Implementing longitudinal follow-up studies will provide important data on the prognostic capabilities of these biomarkers in predicting not only immediate intracranial complications but also recovery trajectories over months or years post-injury.
From a policy perspective, the establishment of guidelines that advocate for the use of biomarkers alongside established clinical rules like PECARN could influence nationwide clinical practices in pediatric emergency medicine. Collaborative efforts between researchers, clinicians, and policymakers will be fundamental in shaping these standards, facilitating changes that prioritize patient safety and effective resource management.
While the preliminary integration of S100B and GFAP biomarkers with the PECARN rule shows significant potential for enhancing mTBI management in pediatric patients, it is essential to continue this line of inquiry. The future of pediatric emergency care will benefit from a more nuanced understanding of brain injury, one that leverages both clinical evaluation and innovative biomarker technologies.