Study Overview
The investigation aimed to explore the potential enhancement of the PECARN rule (Pediatric Emergency Care Applied Research Network) by integrating molecular biomarkers, specifically S100B and GFAP (Glial Fibrillary Acidic Protein), in the decision-making process for computed tomography (CT) imaging in pediatric patients presenting with mild traumatic brain injury (mTBI). Given the increasing complexity of diagnosing mTBI and the inherent challenges associated with determining the necessity of CT scans, this study sought to evaluate whether these biomarkers could provide additional insights that might refine clinical assessments and optimize patient care.
Participants in the study were children who had suffered from mild head trauma and presented to an emergency department. The research explored the correlation between the levels of S100B and GFAP in blood samples and conventional clinical findings, including those outlined in the PECARN rule, which serves as a guideline to assist clinicians in deciding the likelihood of significant brain injury in children.
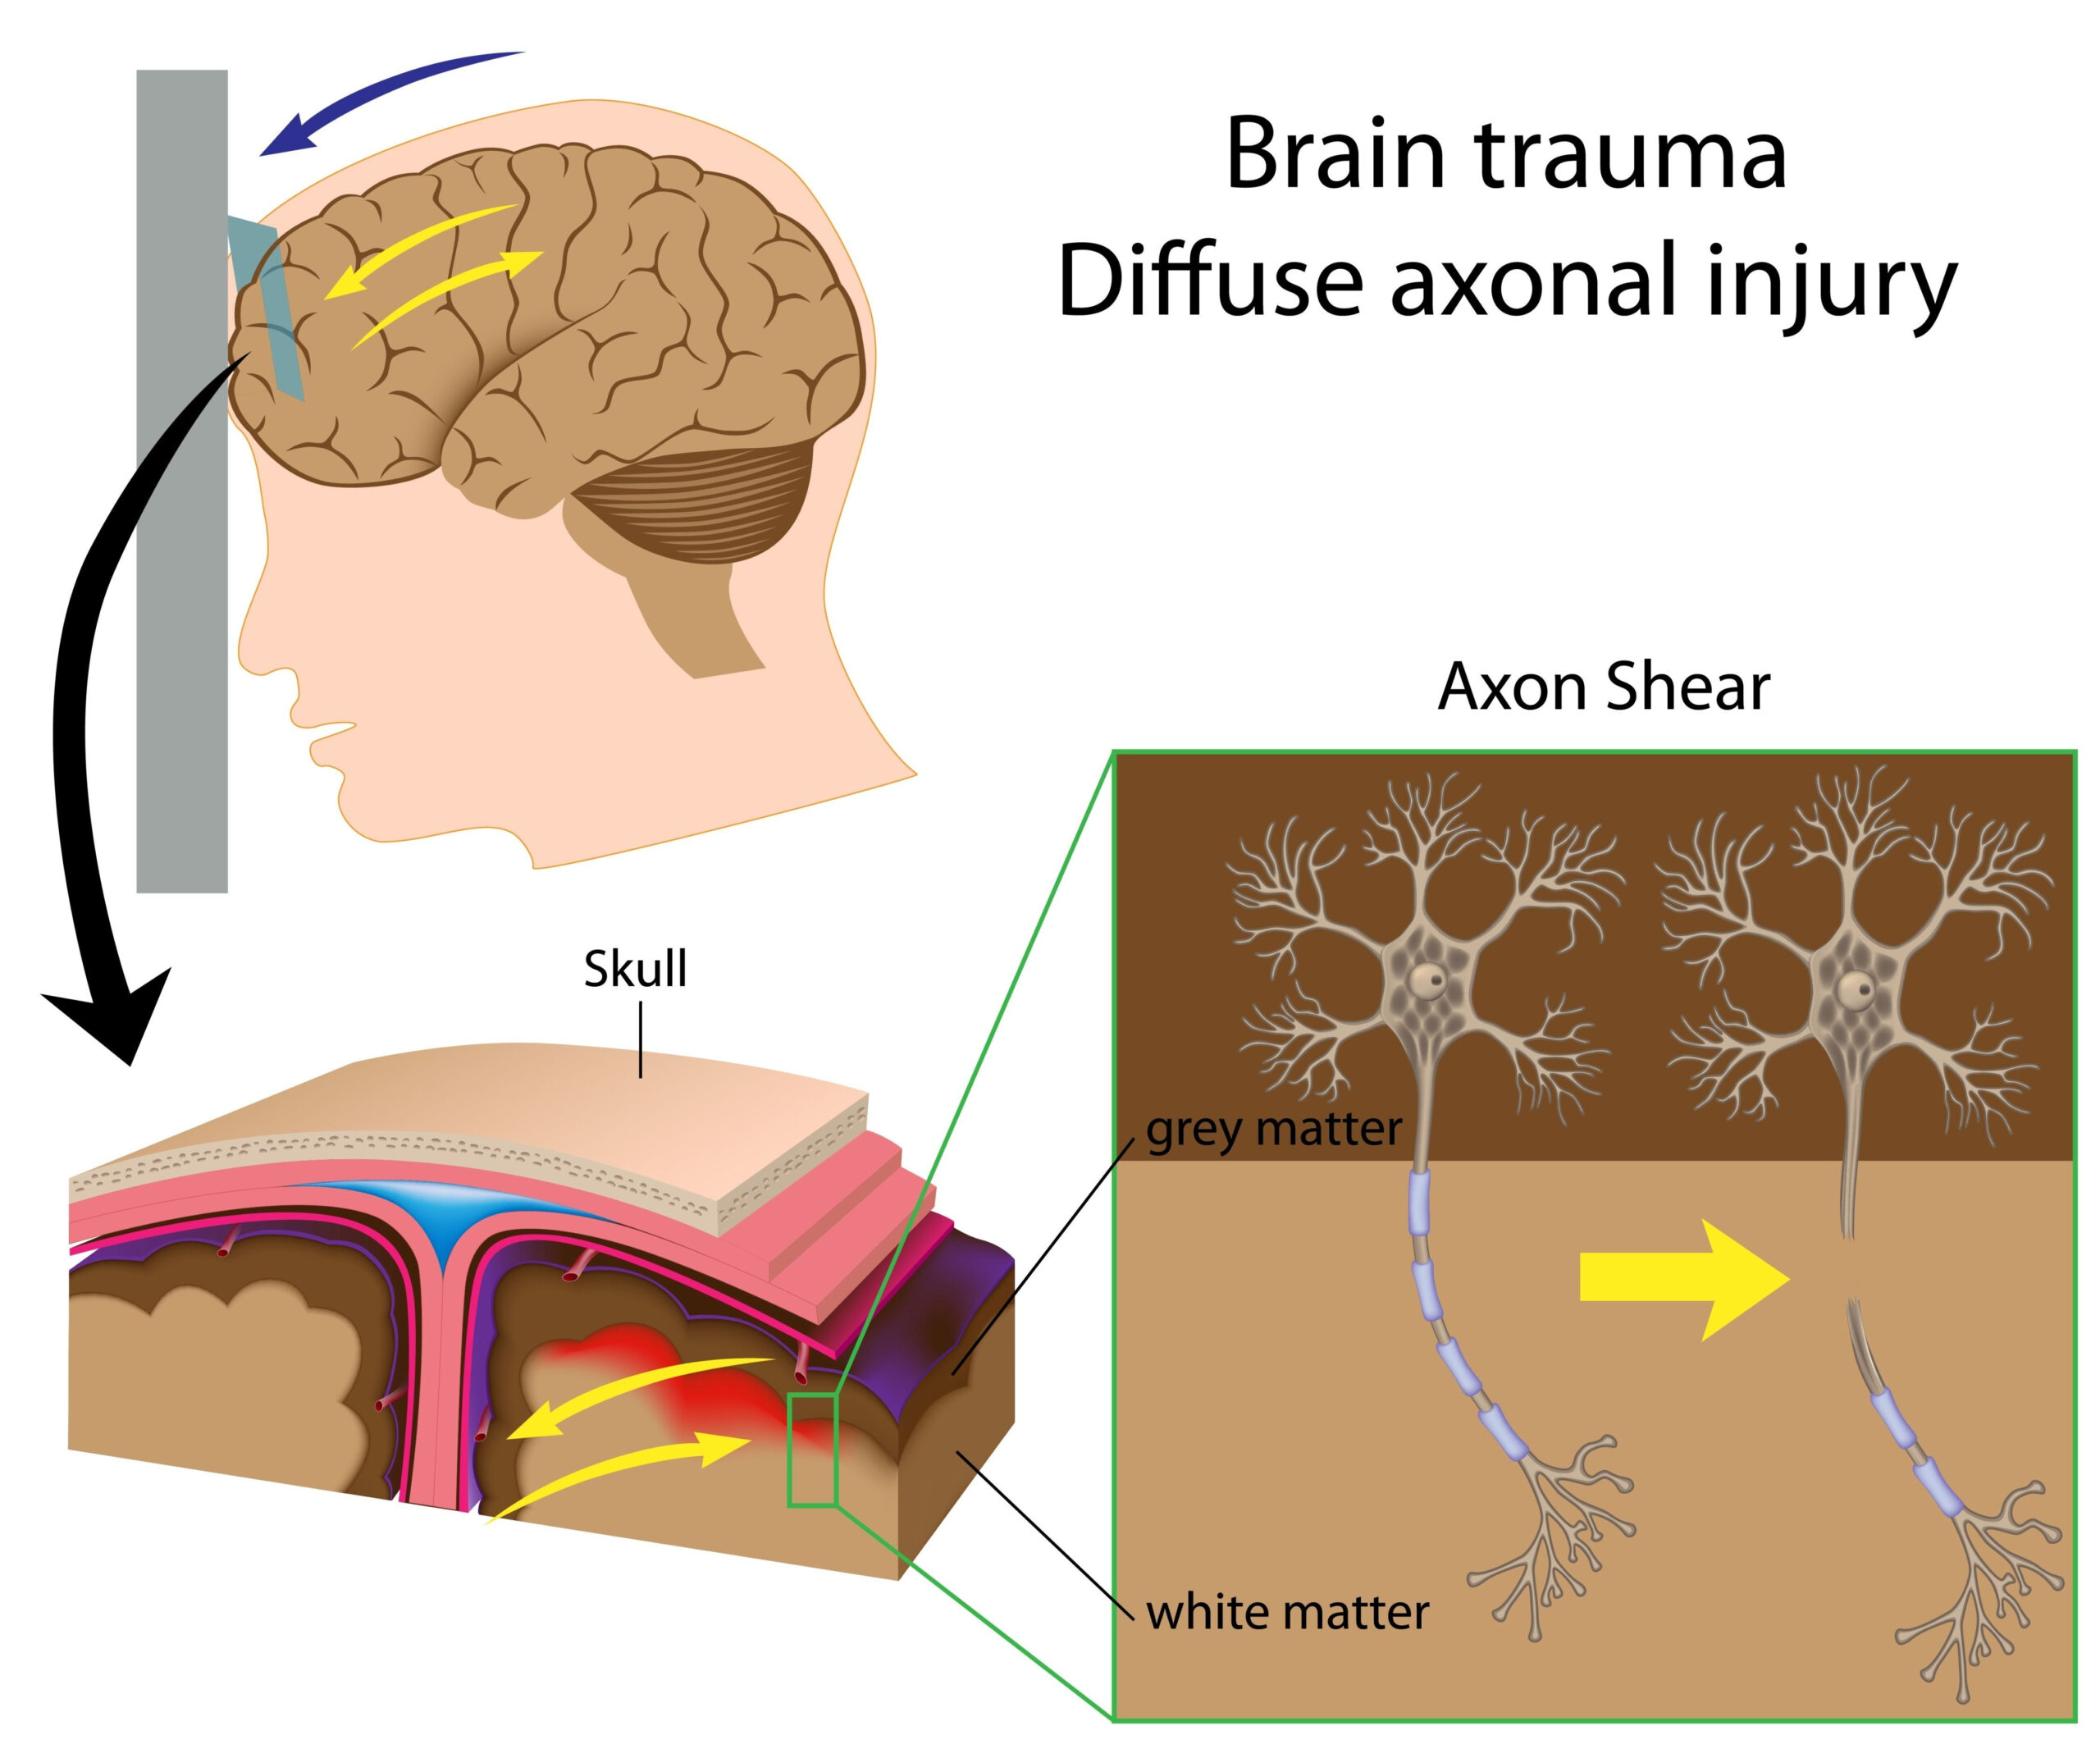
The rationale behind incorporating S100B and GFAP into clinical practice stems from their roles as indicators of brain injury. S100B, a calcium-binding protein found in glial cells, is known to leak into the bloodstream following neuronal injury. Similarly, GFAP, a key structural protein in astrocytes, reflects astrocytic activation after an insult to the brain. By measuring these biomarkers, researchers aimed to identify whether they could complement clinical criteria and imaging recommendations, thus potentially reducing unnecessary radiation exposure from CT scans while ensuring that significant injuries were not overlooked.
This preliminary study lays the groundwork for future investigations that could expand the understanding of how these biomarkers interact with established clinical protocols, ultimately influencing treatment decisions and improving outcomes for pediatric patients suffering from the consequences of mTBI.
Methodology
In conducting this study, a prospective observational design was utilized to evaluate the role of S100B and GFAP in conjunction with the PECARN rule for CT decision-making in pediatric patients with mild traumatic brain injury. The study enrolled participants aged between 1 and 18 years who presented to the emergency department within a defined time frame following an incident of mild head trauma. The inclusion criteria required the children to exhibit mild symptoms, which are classified as a Glasgow Coma Scale (GCS) score of 13 to 15.
Blood samples were collected from each participant upon admission for the assessment of S100B and GFAP levels. These biomarkers were measured using enzyme-linked immunosorbent assay (ELISA) techniques, which provide accurate quantification of protein concentrations within serum samples. To ensure high-quality data, samples were processed and analyzed immediately, maintaining proper handling techniques to prevent degradation of the biomarkers.
Clinical assessments were performed based on the PECARN guidelines. This tool takes into account specific clinical findings and history, such as age, mechanism of injury, and neurological examination, to stratify patients by their risk for clinically significant traumatic brain injury that would necessitate a CT scan. The doctors involved in the study documented physical examination findings and emergency department observations systematically, allowing for correlations between conventional clinical assessments and biomarker levels.
Statistical analyses were conducted to compare the levels of S100B and GFAP with the outcomes derived from the PECARN rule. The primary objective was to ascertain whether the addition of biomarker data could significantly alter the risk classification provided by the PECARN criteria. Additionally, multivariate analyses were employed to control for confounding variables, including demographic factors like age and sex, as well as the presence of symptoms such as vomiting or loss of consciousness.
This methodology not only facilitated a robust assessment of the biomarkers’ potential role in clinical decision-making but also aimed to address ethical concerns regarding unnecessary imaging in pediatric populations. A follow-up was scheduled for participants to monitor recovery and any subsequent complications, enhancing the study’s long-term reliability. This comprehensive approach was designed to contribute foundational insights that would support possible integration of S100B and GFAP into clinical practice for improved management of mild traumatic brain injuries in children.
Key Findings
The findings from this study highlight the potential utility of S100B and GFAP as adjunctive diagnostic tools in conjunction with the PECARN guidelines for assessing pediatric patients with mild traumatic brain injury. The analysis revealed notable correlations between elevated levels of these biomarkers and clinically significant brain injuries that necessitated CT imaging. Specifically, higher concentrations of S100B were consistently associated with an increased likelihood of detecting intracranial injuries, while GFAP levels showed a similar pattern, indicating that both markers could potentially enhance clinical decision-making.
Statistical evaluations demonstrated that adding biomarker data to the PECARN rule adjusted the risk classification for certain groups of patients. In particular, children with mild symptoms but elevated S100B levels were found to have a significantly higher risk of clinically important injuries compared to those with lower S100B values. These results suggest that S100B can provide a critical additional layer of risk stratification that may support clinicians in identifying patients who warrant further imaging despite initially being categorized as low-risk per standard PECARN criteria.
In contrast, GFAP levels, while also indicative of injury, offered complementary but distinct insights. The combination of S100B and GFAP levels allowed for a more nuanced interpretation of risk, emphasizing the potential for these biomarkers to act synergistically. Patients displaying simultaneous elevations in both markers demonstrated the highest likelihood of requiring further diagnostic evaluation. This underscores the complex interplay between multiple cellular responses to brain injury and the need for comprehensive biomarker assessments.
Moreover, the study found that demographic factors and clinical symptoms, such as age and loss of consciousness, also played a role in the interpretation of both biomarkers. For instance, younger patients tended to exhibit different biochemical responses compared to their older counterparts, which illuminated the necessity for age-appropriate clinical considerations when implementing biomarker-guided evaluations in this vulnerable population.
Beyond the immediate clinical insights, the results affirm the feasibility of integrating S100B and GFAP into existing diagnostic protocols. They offer a pathway to reducing unnecessary CT scans, thereby minimizing the exposure to radiation in pediatric populations, while still ensuring that significant injuries are not overlooked. The potential for these biomarkers to refine risk assessments could lead to more personalized care strategies, ultimately enhancing outcomes for children with mild traumatic brain injuries.
Finally, the follow-up assessments of participants demonstrated that the elevated levels of S100B and GFAP were not only predictive of initial injury severity but also correlated with longer-term recovery trajectories. These findings suggest that monitoring these biomarkers could facilitate ongoing clinical evaluations and guide rehabilitation processes, providing a comprehensive approach to managing the aftereffects of mTBI in pediatric patients.
Clinical Implications
The integration of S100B and GFAP into clinical decision-making processes has several significant implications for the management of pediatric mild traumatic brain injury (mTBI). By providing healthcare professionals with additional data points, these biomarkers can serve to refine risk stratification and enhance diagnostic accuracy, potentially reducing reliance on CT imaging. Notably, children presenting with mild symptoms but elevated levels of these markers may be at a higher risk for clinically significant injuries, which underscores the necessity for careful assessment beyond conventional guidelines.
The integration of these biomarkers into existing protocols, specifically alongside the PECARN rule, is particularly crucial given the risks associated with radiation exposure in the pediatric population. CT scans are valuable diagnostic tools but come with a non-negligible risk of radiation-induced harm, especially for children, whose developing tissues are more sensitive. By utilizing S100B and GFAP as adjuncts, clinicians can make more informed decisions, allowing for a tailored approach to imaging that prioritizes patient safety without compromising the quality of care.
Moreover, the potential for biomarkers to enhance the understanding of individual responses to brain injuries indicates a broader shift towards personalized medicine. The variability in biomarker expression among children of different ages or with different clinical histories suggests that tailored treatment protocols based on biomarker levels could be developed. For example, a child with a high GFAP level may require more vigilant monitoring and possibly earlier intervention compared to one with a lower level, even if both children have similar clinical presentations. This shift could lead to more proactive management strategies, ultimately improving patient outcomes and quality of life.
Additionally, monitoring S100B and GFAP levels could inform longitudinal treatment strategies. The correlation of elevated biomarker levels with longer-term recovery trajectories opens avenues for continuous evaluation and adjustment of rehabilitation strategies. Clinicians might leverage these biomarkers not only to assess initial injury severity but also to guide interventions and track recovery over time, allowing for a dynamic approach to the management of mTBI.
The implications of this study also extend to clinical practice guidelines and policymaking. As the evidence base supporting the utility of S100B and GFAP grows, it may prompt revisions in current guidelines to incorporate these biomarkers as essential components of assessment protocols. This evolution in standards could standardize practice across institutions, creating a more uniform approach to the assessment and management of pediatric mTBI.
Finally, broader implications might arise for research and development of new diagnostic tools or therapies. The findings of this preliminary study could spur further investigation into additional biomarkers of interest, as well as the mechanisms underlying their predictive capacities. Expanding the panel of biomarkers could provide even more nuanced insights into brain injury assessment and treatment, paving the way for advancements in pediatric neurotrauma management.
In conclusion, the integration of S100B and GFAP into clinical practice represents a promising frontier in enhancing the assessment and management of pediatric mTBI. These biomarkers not only have the potential to improve immediate clinical decision-making but also to foster a more comprehensive understanding of brain injury impact over time, ultimately shaping patient-centered care in this vulnerable population.