Study Overview
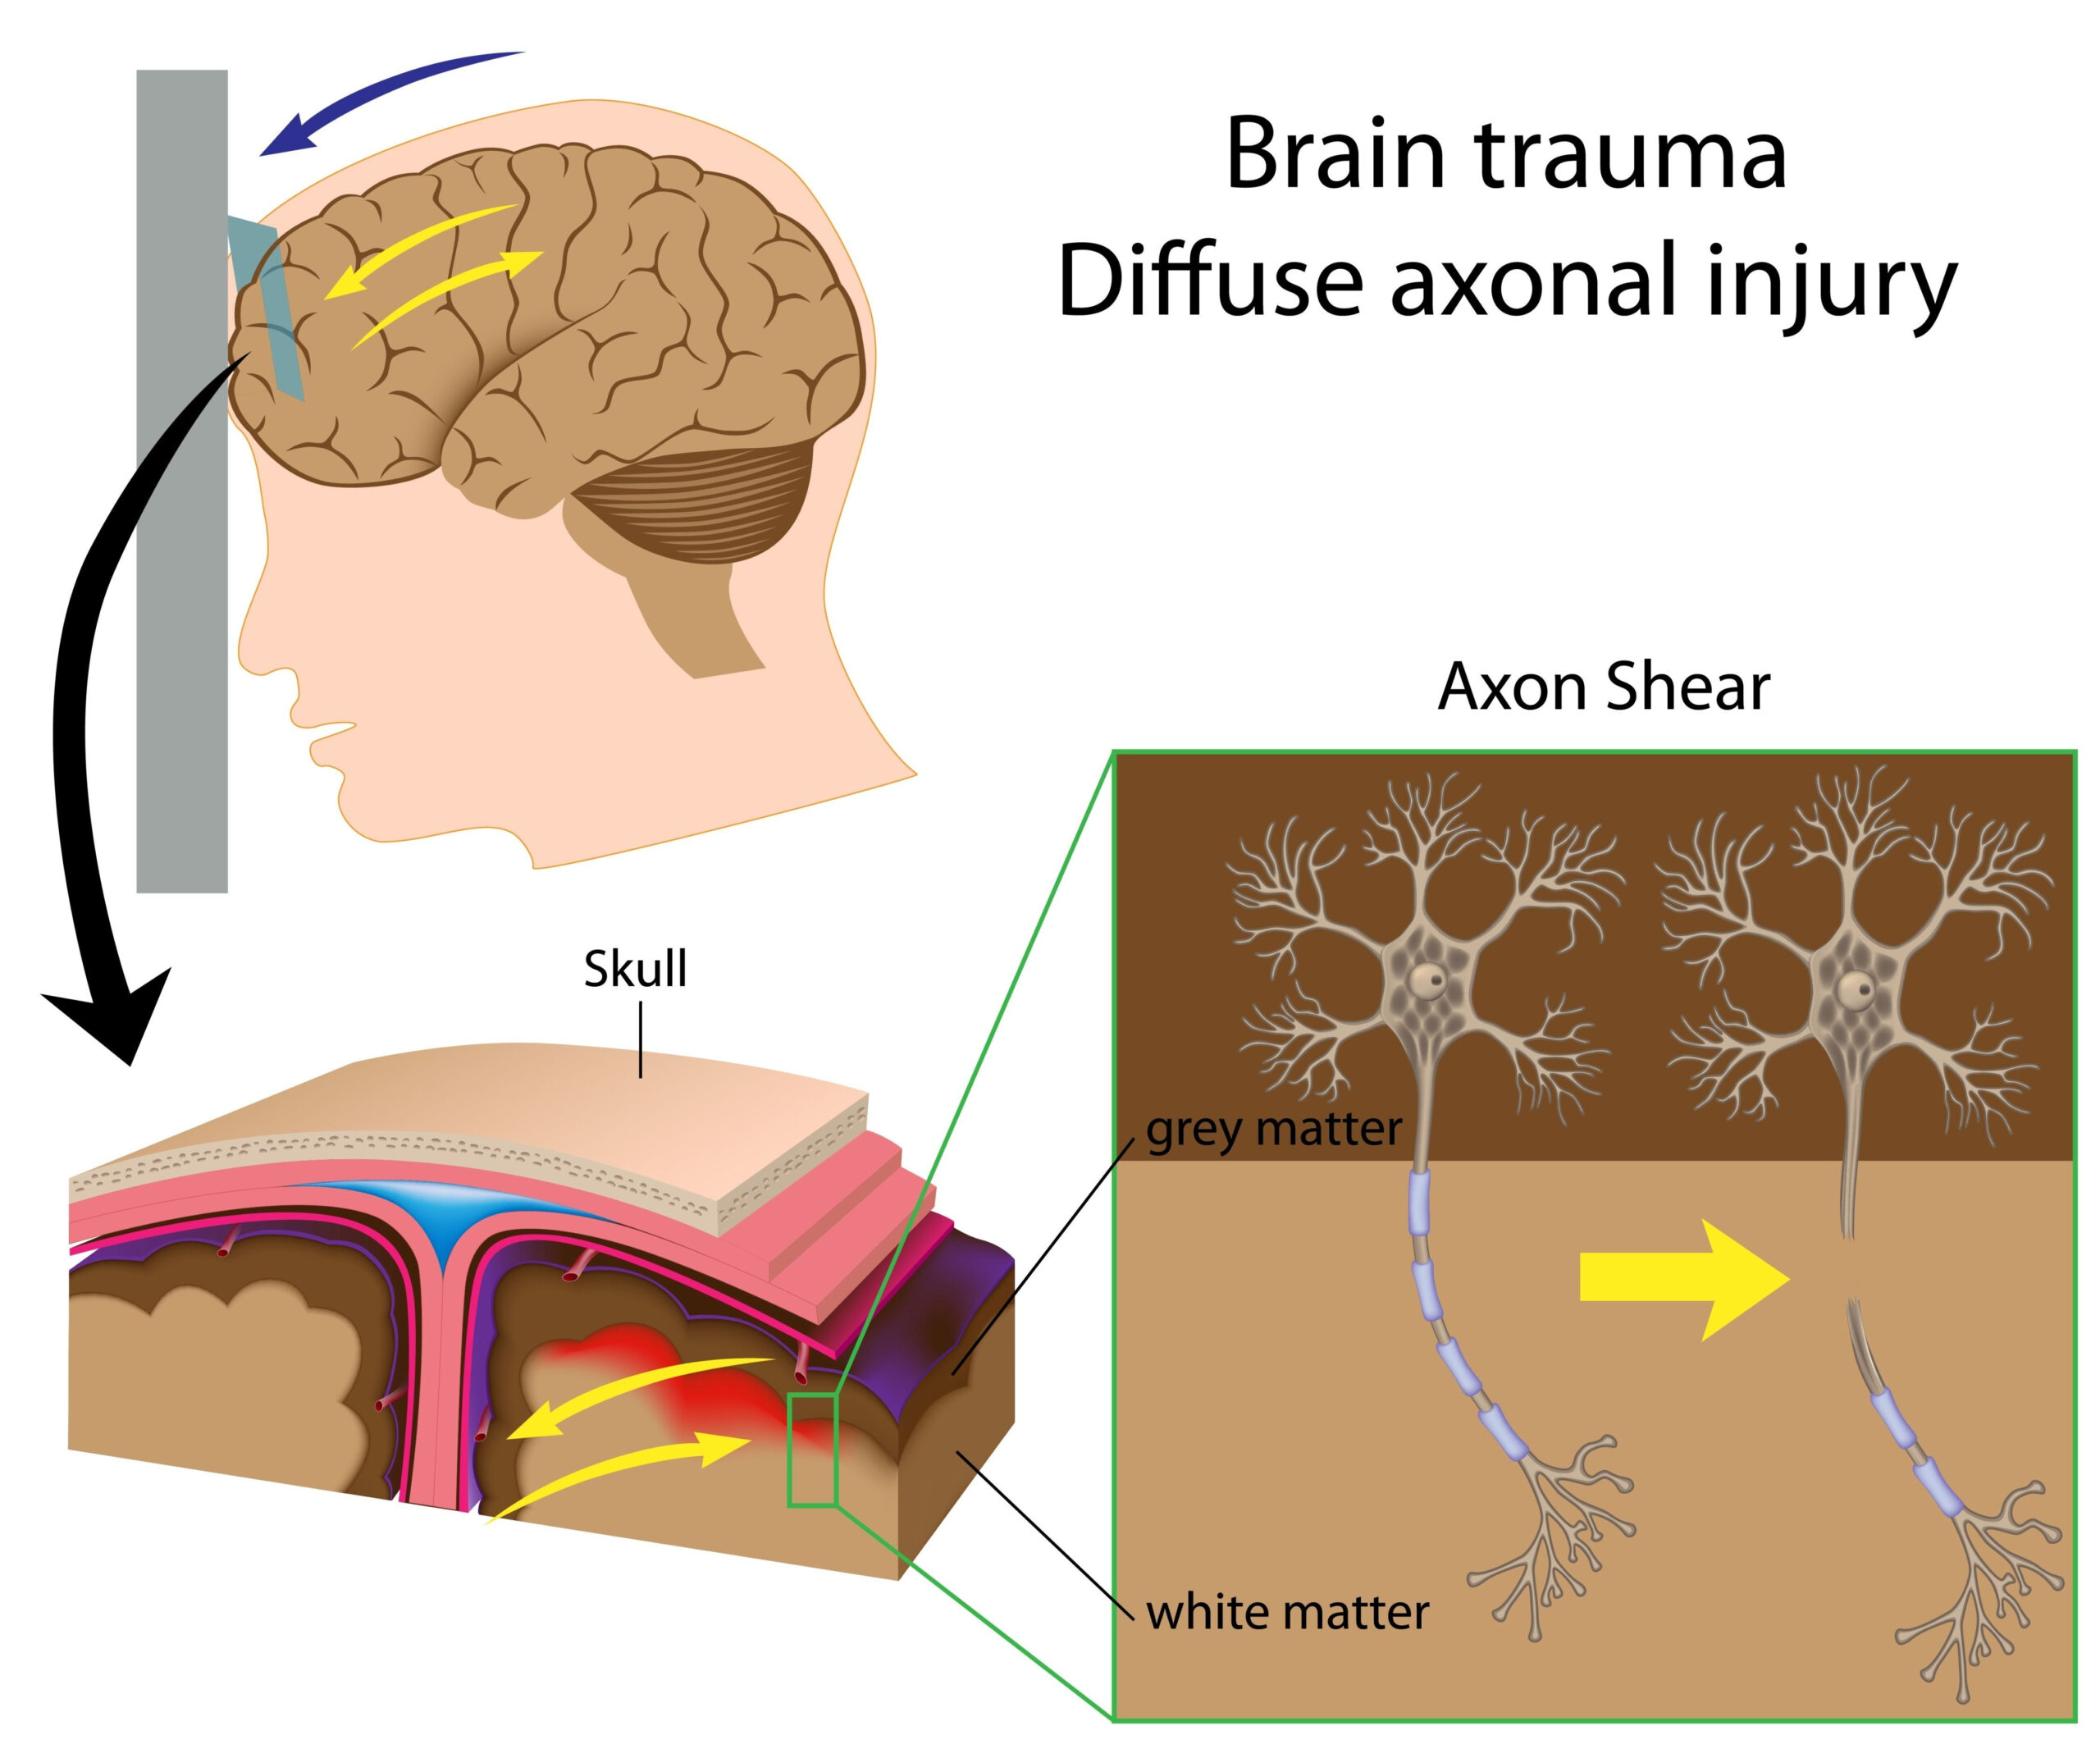
The Mobile Subthreshold Exercise Program (MSTEP) was designed as an innovative approach to support youth who experience prolonged recovery from concussion. Concussion recovery can be complex and protracted, particularly in adolescents, leading to not only physical challenges but also emotional and cognitive difficulties. This trial aimed to assess whether a structured exercise program delivered through a mobile platform could enhance recovery outcomes.
Participants included adolescents diagnosed with concussion who had not shown adequate improvement within expectations set by clinical guidelines. The program was designed to engage these individuals in subthreshold exercise—activities that do not exacerbate their symptoms—while providing them with the convenience of accessing the program on their mobile devices. This approach addressed two critical challenges: the need for safe, supervised physical activity during recovery and the incorporation of technology that resonates with the youth demographic.
Throughout the study, participants were monitored for various metrics, including symptom alleviation, physical fitness, and overall function. By implementing a randomized clinical trial methodology, the researchers aimed to produce robust, evidence-based results that could inform future clinical practices for managing concussions in youth.
The study setup allowed for a control group that did not engage in the MSTEP program, thus providing a comparative basis to glean insights about the effectiveness of the mobile exercise regimen. The overarching goal was not only to evaluate the physical outcomes of the program but also to deliver a comprehensive perspective on the ancillary benefits such as enhanced mood and mental well-being associated with exercise during recovery.
Methodology
The study utilized a randomized clinical trial design to evaluate the efficacy of the Mobile Subthreshold Exercise Program (MSTEP) for youth with prolonged concussion recovery. The participants, aged between 12 and 18 years, were recruited from various concussion clinics and educational institutions. All participants had been diagnosed with a concussion according to established clinical guidelines and were experiencing recovery symptoms that persisted beyond the expected timeline, typically defined as more than four weeks post-injury.
To ensure a diverse representation, the inclusion criteria were broad, encompassing various sports-related and non-sports-related concussions. Exclusion criteria included pre-existing medical conditions that could confound the results, such as severe psychiatric disorders, significant neurological impairments, or any medical contraindications to exercise.
After obtaining informed consent from both the participants and their guardians, eligible individuals were randomly assigned to either the intervention group, which participated in the MSTEP, or the control group, which continued with usual care lacking structured exercise intervention. Randomization was performed using a computerized random number generator to eliminate potential biases and ensure that each participant had an equal chance of being assigned to either group.
The MSTEP program was delivered via a mobile application designed specifically for this study, providing users with tailored exercise routines that adhered to subthreshold levels of exertion. These routines included light aerobic activities, such as walking or cycling, along with strength training exercises, all systematically generated based on the individual’s symptoms and recovery status. Participants had access to the program for 12 weeks, receiving weekly adjustments based on their ongoing assessment of symptoms.
The primary outcomes measured in this trial were symptom severity, assessed using the Post-Concussion Symptom Scale, and physical fitness improvements, evaluated through standardized tests including the 20-Meter Shuttle Run and the Functional Movement Screen. Secondary outcomes included assessments of emotional well-being, assessed via tools such as the Generalized Anxiety Disorder 7-item scale (GAD-7) and the Patient Health Questionnaire-9 (PHQ-9), as well as overall functional status captured through the Pediatric Quality of Life Inventory (PedsQL).
Data collection occurred at baseline, mid-intervention (weeks 6), and post-intervention (week 12), allowing for both longitudinal assessment of participant progress and comparison of outcomes between the intervention and control groups. Throughout the study, participants were encouraged to report daily symptoms and engage with the app to optimize adherence to the prescribed exercise regimen. The app also featured elements of gamification to enhance user engagement and motivation.
Statistical analyses were employed to determine the effectiveness of the intervention, with comparisons made using intention-to-treat principles to maintain the integrity of randomization. Data analyses included mixed-effects models to account for repeated measures, alongside descriptive statistics to provide context around the participant demographics and symptom profiles.
Moreover, the qualitative aspects of the intervention were explored through participant interviews conducted after the intervention period, offering rich insights into their experiences with the mobile program and perceived impact on recovery, motivation, and overall well-being.
Key Findings
The results of the Mobile Subthreshold Exercise Program (MSTEP) trial revealed several significant findings regarding the effectiveness of the intervention in promoting recovery for youth with prolonged concussion symptoms. Analyzing the primary outcomes, the data indicated a notable decrease in symptom severity among participants engaged in the MSTEP program compared to those in the control group. Specifically, the average reduction in scores on the Post-Concussion Symptom Scale showed a statistically significant difference, highlighting the potential of tailored exercise regimens in alleviating concussion-related symptoms.
In terms of physical fitness, improvements were also evident. Participants in the MSTEP group demonstrated enhanced performance on standardized fitness assessments, such as the 20-Meter Shuttle Run, which provides a measure of aerobic capacity and overall fitness. The findings showed a marked increase in distances covered and improved times, supporting the assertion that even low-impact exercise can yield beneficial effects on cardiovascular health during recovery periods.
Furthermore, secondary outcomes concerning mental health reflected encouraging trends as well. Assessments using the Generalized Anxiety Disorder 7-item scale (GAD-7) and the Patient Health Questionnaire-9 (PHQ-9) revealed lower levels of anxiety and depressive symptoms in those participating in the MSTEP compared to the control group. This underscores the idea that physical activity can contribute to both psychological resilience and emotional well-being, a perspective increasingly recognized in the field of sports medicine and adolescent health.
Participant feedback collected through qualitative interviews provided additional depth to the quantitative findings. Many noted an increase in motivation and engagement, directly attributing their recovery progress to the structured, guided approach that MSTEP offered. The mobile app’s gamified elements, which included challenges and rewards, were reported to enhance their experience, making the exercise routine feel less like a chore and more like an engaging activity that was easily integrated into their daily lives. This aspect of the intervention highlighted the value of technology in modern rehabilitation practices, especially for younger populations.
Moreover, adherence to the prescribed exercise routine was notably high, with participants frequently reporting their daily symptoms through the app. The structural support provided by MSTEP not only facilitated physical activity but also encouraged routine check-ins about their recovery process, creating a comprehensive feedback loop that allowed for personalized modifications to their exercise plans. This demonstrated the feasibility of remotely supervised, subthreshold exercise protocols as a mechanism for enhancing recovery in youth with concussions.
The results from this trial underscore the importance of integrating physical activity into recovery protocols for young individuals suffering from concussions. The findings lend weight to the notion that while traditional rest and monitoring are crucial post-injury, proactive engagement through adaptive exercise can lead to improved outcomes not just physically, but also cognitively and emotionally for adolescents navigating the complexities of prolonged concussion recovery.
Strengths and Limitations
The Mobile Subthreshold Exercise Program (MSTEP) trial presents several strengths that enhance the validity and applicability of its findings. One of the key strengths is the randomized control trial design, which minimizes selection bias and allows for a robust comparison between the intervention and control groups. This methodological rigor helps in establishing a clear causal relationship between the MSTEP program and the observed improvements in concussion recovery outcomes. Randomization was executed with a computerized number generator, ensuring an unbiased allocation of participants into the study groups.
Another notable strength is the comprehensive approach to participant experience and engagement fostered by the mobile platform. By utilizing an app that offered tailored exercise programs, MSTEP effectively addressed the need for personalized intervention based on individual recovery trajectories. The incorporation of gamification elements not only increased adherence rates but also provided motivation and a sense of achievement among participants. This aspect aligns well with the preferences of the youth demographic, making the intervention more relevant and accessible.
Furthermore, the variety in outcome measures enhances the study’s robustness. By assessing both primary outcomes, such as symptom severity and physical fitness, and secondary outcomes, including emotional well-being, the trial provides a multidimensional perspective on recovery. The use of validated assessment tools such as the Post-Concussion Symptom Scale and the GAD-7 further strengthens the reliability of the data collected, allowing for a thorough evaluation of the MSTEP’s impact.
However, despite these strengths, the study also bears certain limitations that warrant consideration. One limitation concerns the sample size, which while sufficient for initial findings, may not fully capture the broader population of youth with prolonged concussion recovery. A larger sample could enhance the generalizability of the results to diverse demographic groups, including varying socioeconomic backgrounds and injury contexts.
Additionally, adherence to the intervention, although reported as high, depends significantly on participant engagement with the app. The reliance on self-reported data regarding symptoms and exercise engagement may introduce response bias, affecting the overall reliability of the results. Future studies could benefit from more objective measures, such as wearable technology to track physical activity levels consistently.
Moreover, the focus on short-term outcomes is another limitation. The 12-week intervention period may not provide a comprehensive view of the long-term effects of the MSTEP program. Assessing participants beyond the intervention window could yield insights into the sustained impact of early exercise on long-term concussion recovery.
Finally, while participant interviews added qualitative depth to the findings, the subjective nature of these reports may limit the conclusions drawn. Future studies might incorporate mixed-method approaches that combine qualitative feedback with quantitative metrics over a more extended timeframe to provide a fuller picture of the intervention’s impact.
While the MSTEP trial showcases important strengths that contribute to the understanding of exercise as a rehabilitation tool for youth with concussions, it also highlights certain limitations that must be acknowledged. Addressing these limitations in future research will be essential to advance knowledge and improve recovery protocols for this vulnerable population.