Study Overview
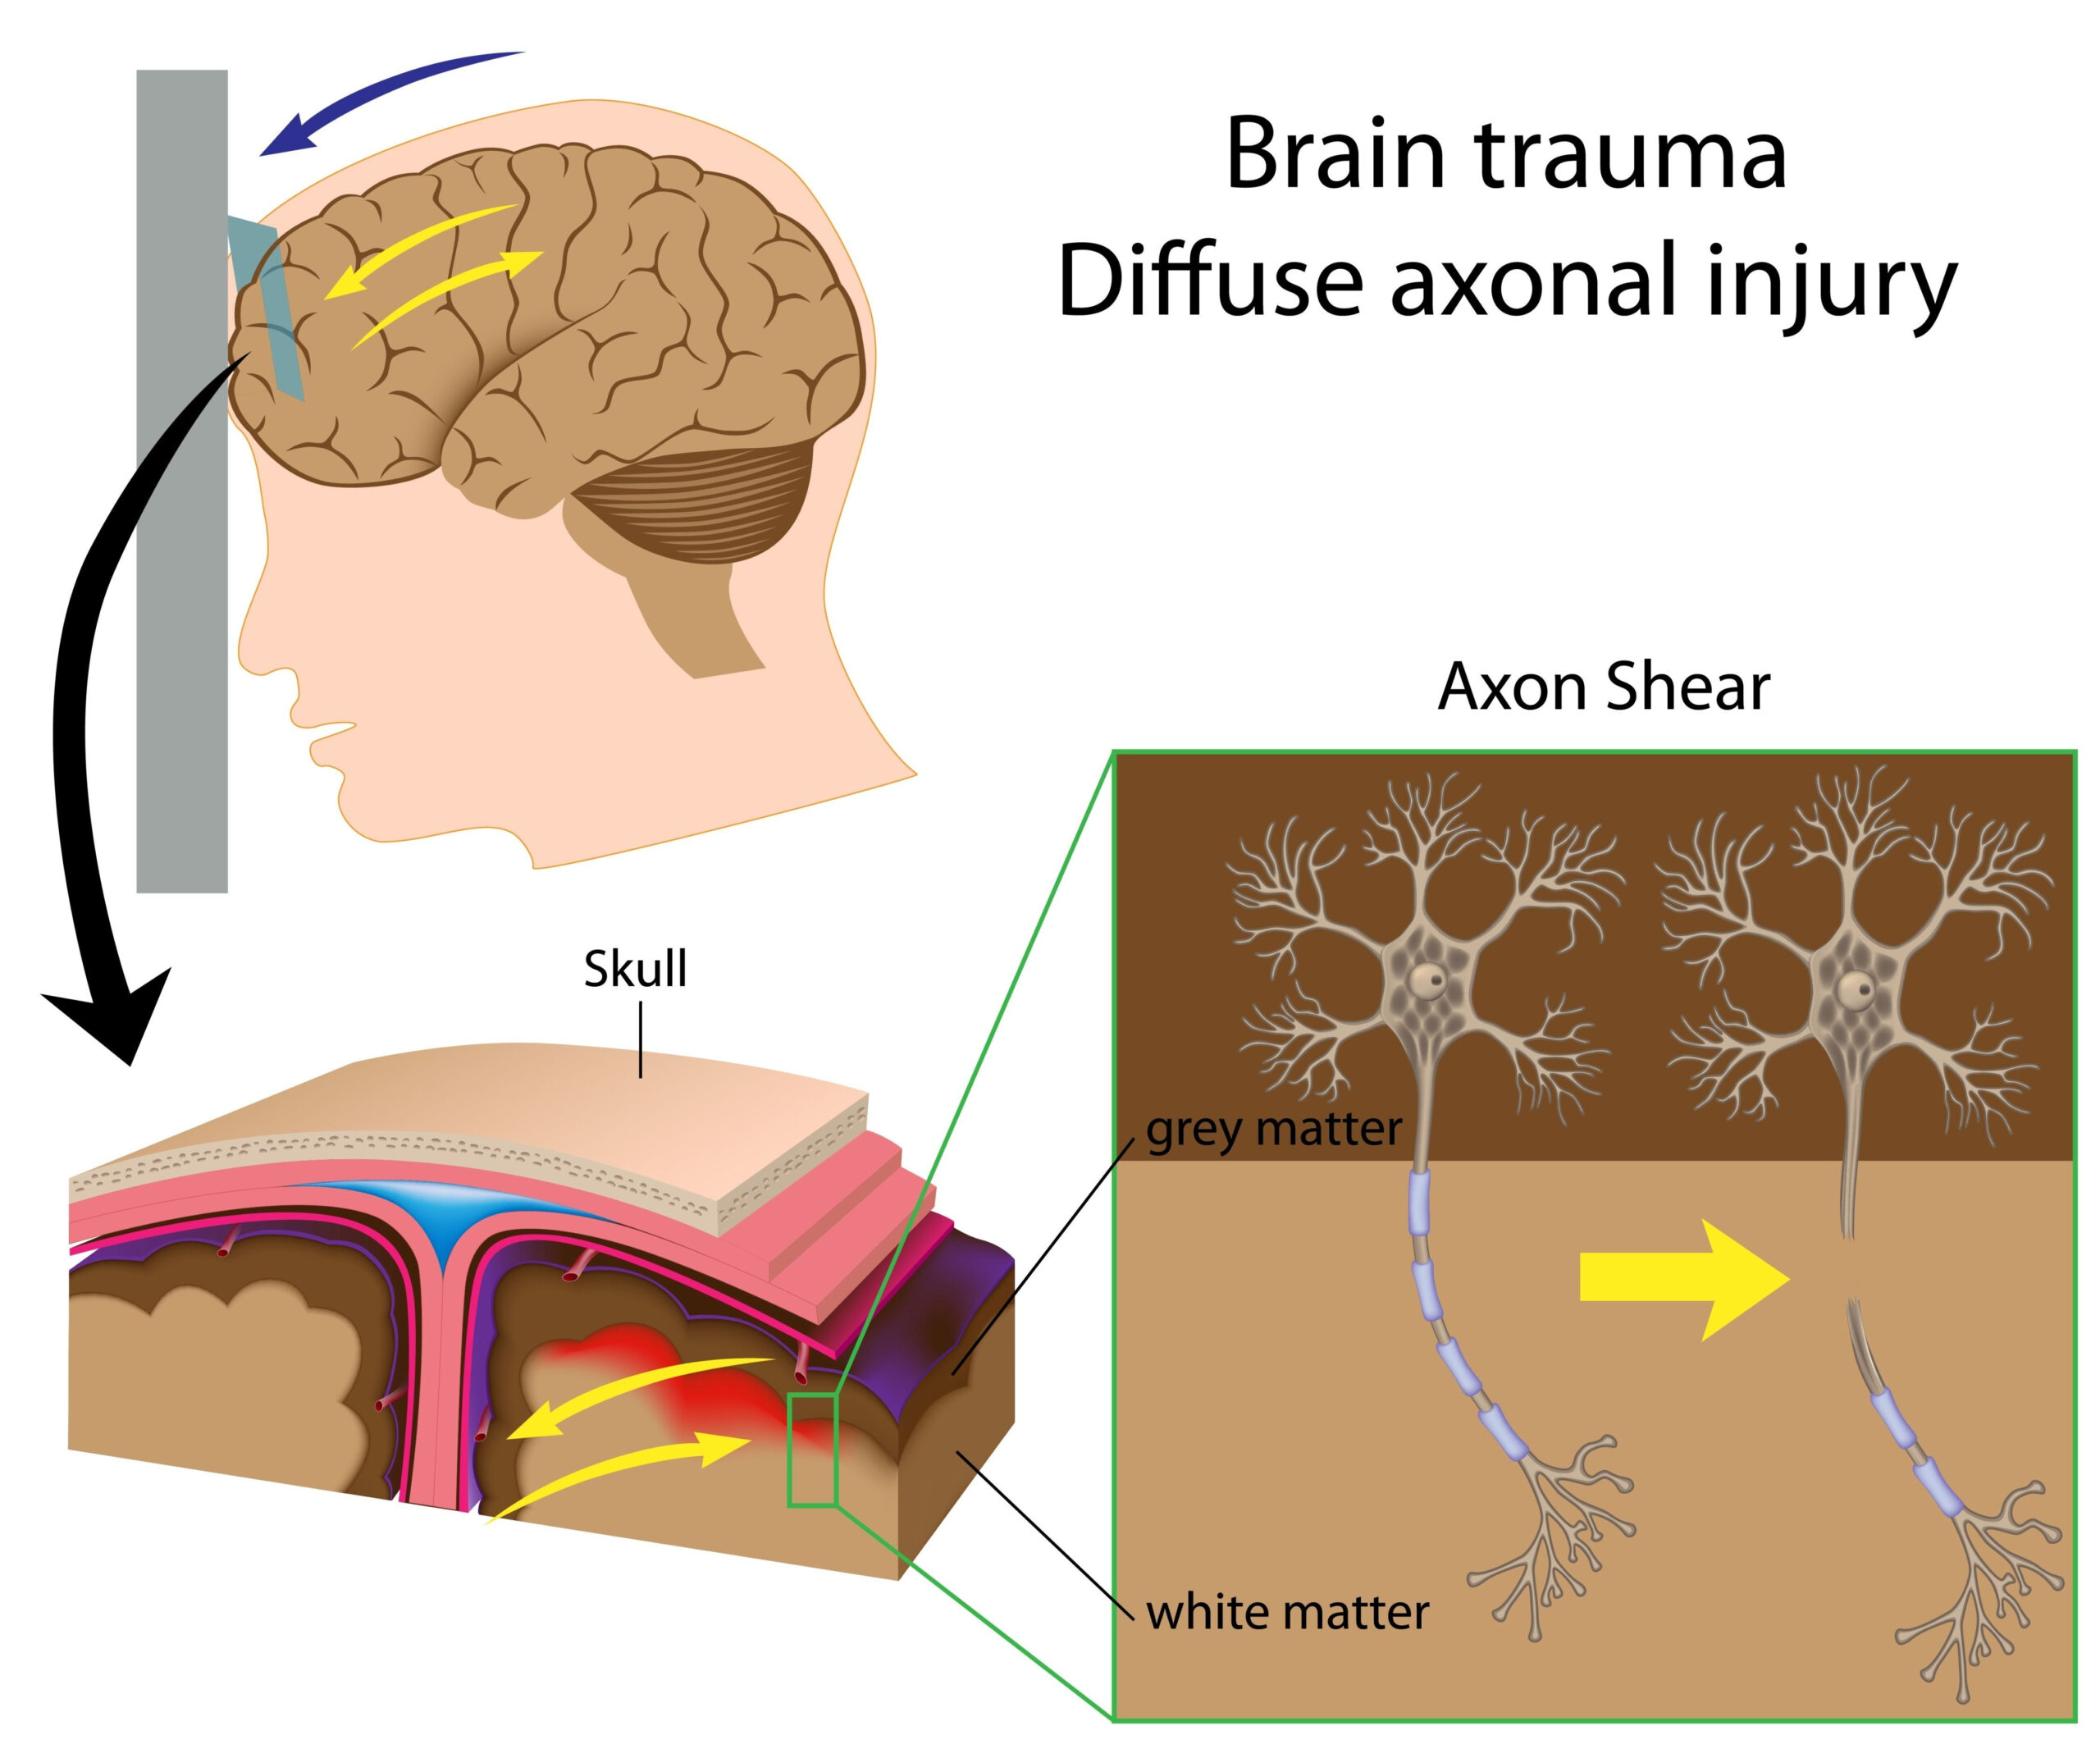
This research investigates the intricate relationship between pediatric traumatic brain injuries (TBIs) and the incidence of healthcare-associated infections (HAIs), focusing specifically on their combined impact on mortality rates in young patients. The study utilizes a prospective design, allowing researchers to collect data in real time while monitoring the health status of participants over a specified period, which enhances the reliability of the findings. By examining a population of children who have sustained TBIs, the study aims to identify relevant determinants that contribute to increased mortality, thereby addressing a critical issue in pediatric healthcare.
The significance of this research stems from the severity of TBIs in children, which can lead to long-term health complications, including cognitive deficits, physical disabilities, and increased susceptibility to infections. The risk of HAIs in this vulnerable population can be exacerbated by their compromised immune systems and the invasive procedures often required for their treatment. This study is distinguished by its application of the Least Absolute Shrinkage and Selection Operator (LASSO) regression technique, a statistical method that not only identifies but also quantifies the relative importance of numerous predictors that may influence patient outcomes.
In the context of pediatric medicine, understanding the interplay between TBIs and HAIs is vital for developing targeted interventions that can mitigate the associated risks. Through its detailed analysis, this study seeks to provide healthcare professionals with insights that can inform clinical practices and improve overall patient care. By focusing on a well-defined population and employing advanced statistical methods, the findings are anticipated to contribute significantly to the existing body of knowledge on pediatric critical care and infection management.
Importantly, this research underscores the necessity of vigilant monitoring and tailored care protocols for children suffering from TBIs, particularly regarding infection prevention strategies. The outcomes of this study may lead to the establishment of evidence-based guidelines that enhance survival rates and quality of life for affected children.
Methodology
The study employed a robust prospective design to accurately assess the correlation between pediatric traumatic brain injuries and healthcare-associated infections, while also investigating their collective impact on mortality. This methodological choice facilitated the acquisition of real-time data from a carefully selected cohort of pediatric patients diagnosed with TBIs. The subjects were recruited from a variety of healthcare facilities, ensuring a diverse sample representative of different demographics and medical histories.
Data collection involved meticulous monitoring throughout the participants’ hospital stay and beyond, tracking various clinical variables and outcomes. Essential data points included demographic information, clinical presentations at admission, details regarding the nature and severity of the TBIs, the type and duration of interventions administered, and the incidence of HAIs observed during the hospital course. This comprehensive dataset was critical in understanding the myriad factors that could influence patient outcomes.
The analytical approach was centered around the application of Least Absolute Shrinkage and Selection Operator (LASSO) regression, a sophisticated statistical tool adept at handling high-dimensional datasets with numerous predictors. This method enables researchers to distinguish the most influential variables impacting mortality rates while simultaneously reducing the potential for overfitting, thereby improving the reliability of the results. By applying LASSO, the study was able to refine its focus on key determinants of mortality in pediatric patients suffering from TBIs, including the presence of HAIs.
In addition to LASSO regression, the study incorporated rigorous quality control measures to ensure the accuracy and completeness of the data. Stringent inclusion and exclusion criteria were established, allowing for a homogeneous study population that minimized confounding factors. During the analysis, researchers performed sensitivity analyses to test the robustness of the findings under various conditions, further asserting the validity of the conclusions drawn.
Ethical considerations were paramount throughout the research process. Informed consent was obtained from the guardians of all participating children, aligning with ethical standards for conducting research involving vulnerable populations. The study protocols were approved by the institutional review board, safeguarding the rights and welfare of the participants while facilitating a transparent research environment.
By utilizing this thorough and ethically sound methodology, the research aims to unveil nuanced insights into the determinants of mortality in pediatric TBIs compounded by HAIs, ultimately guiding future clinical interventions and enhancing patient care frameworks.
Key Findings
The outcomes of this investigation reveal critical insights into the interplay between pediatric traumatic brain injuries (TBIs) and healthcare-associated infections (HAIs), illustrating their compounded effects on mortality rates in affected children. The analysis identified several key determinants that significantly influence the risk of mortality among this vulnerable population, providing actionable data for clinical practice and research.
One of the most striking findings of this study is the elevated mortality risk associated with the presence of HAIs in pediatric patients who have sustained TBIs. Data indicated that children who developed HAIs during their hospitalization had a mortality rate markedly higher than those who did not experience infections. Specifically, the study noted that the probability of death increased substantially with the number of HAIs diagnosed, underscoring the critical need for effective infection prevention strategies in pediatric wards. The correlation was particularly pronounced in patients with severe TBIs, where compromised health status and prolonged hospital stays heighten susceptibility to infections that could escalate into life-threatening complications.
Further analysis using the LASSO regression model revealed additional significant predictors of mortality that extend beyond the presence of HAIs. Factors such as the Glasgow Coma Scale (GCS) score at admission emerged as a vital indicator of initial injury severity. Lower GCS scores were consistently associated with higher mortality rates, emphasizing the necessity of prompt intervention and monitoring in cases of severe head trauma. Additionally, comorbidities were also highlighted as influential; children with pre-existing health issues faced an increased risk of mortality, further complicating their recovery trajectories.
The research also identified that prolonged mechanical ventilation and extended lengths of stay in intensive care units were linked to higher mortality rates. This finding suggests that optimizing critical care procedures, including timely extubation and efficient management of respiratory support, could have a positive impact on patient outcomes. Furthermore, the study highlighted the importance of nutrition and metabolic support in the recovery of pediatric TBI patients, revealing that malnutrition during hospitalization significantly correlated with adverse outcomes. Interventions targeting nutritional status could therefore be considered a vital component of care in this population.
Interestingly, the study discusses variations in mortality rates across different healthcare settings, hinting at possible institutional factors influencing patient outcomes. Facilities that implemented comprehensive infection control measures and offered multidisciplinary care exhibited improved survival rates. These findings suggest that institutional policies and practices play a crucial role in enhancing the quality of care delivered to children with TBIs, and point to the necessity of creating standardized protocols that could be broadly adopted.
Overall, the study contributes substantial evidence toward understanding the interconnected challenges posed by TBIs and HAIs in pediatric patients. By elucidating the multifactorial nature of mortality determinants, this research lays the groundwork for implementing targeted interventions aimed at improving survival and health outcomes in this at-risk population.
Clinical Implications
The findings of this study have profound implications for clinical practice in the management of pediatric traumatic brain injuries (TBIs) and the associated risk of healthcare-associated infections (HAIs). The elevated mortality risk linked to HAIs in TBI patients emphasizes the critical necessity for healthcare professionals to adopt proactive infection control measures. Given that the presence of HAIs significantly increases mortality rates, it is essential for pediatric care teams to rigorously implement and adhere to infection prevention protocols. This may include routine surveillance for signs of infection, employing aseptic techniques during invasive procedures, and the use of prophylactic antibiotics when appropriate.
Additionally, the results indicate that the initial severity of a TBI, as measured by the Glasgow Coma Scale (GCS), is a critical determinant of patient outcomes. This underscores the importance of rapid assessment and intervention for patients presenting with low GCS scores. Emergency departments and intensive care units must prioritize immediate and effective management of these patients to mitigate the potential for escalating complications and improve survival chances.
The role of comorbidities in influencing mortality rates suggests that a holistic approach to patient assessment is vital. Clinicians should consider the comprehensive health status of each pediatric patient upon admission, accounting for any pre-existing conditions that could adversely affect recovery. Tailoring treatment plans to address these comorbidities, while also managing the TBI, may enhance overall outcomes.
Moreover, the identification of prolonged mechanical ventilation and extended ICU stays as risk factors for increased mortality highlights the importance of optimizing critical care protocols. Clinicians should aim for timely weaning from mechanical ventilation and strive to minimize unnecessary extensions of ICU admissions. This not only refines resource utilization but may also reduce the risk of HAIs associated with prolonged hospitalization.
Nutritional status emerged as a significant factor influencing recovery, calling for enhanced focus on dietary and metabolic support for pediatric TBI patients. Healthcare providers should ensure that all children receive appropriate nutritional interventions tailored to their needs, as malnutrition can exacerbate overall health declines and hinder recovery.
Lastly, the study reveals notable variations in outcomes across different healthcare settings, suggesting that institutional practices play a substantial role in patient mortality. Creating standardized care protocols that encompass evidence-based best practices for managing TBIs and infections may bridge gaps and promote improved outcomes universally. Institutions could benefit from cross-facility collaborations that share successful strategies and foster a culture of quality improvement focused on pediatric trauma care.
In conclusion, the clinical implications derived from this research are significant and far-reaching. By embracing proactive infection control, addressing initial injury severity, managing comorbidities, optimizing intensive care, and ensuring proper nutrition, healthcare professionals can significantly enhance survival rates and quality of life for children suffering from traumatic brain injuries.