Clinical Phenotype Definitions
The clinical phenotypes associated with hyperkinetic movement disorders are characterized by a variety of involuntary movements that can significantly impact a patient’s daily functioning and quality of life. These disorders are typically categorized based on the specific movement patterns observed, which can include dystonia, chorea, myoclonus, and tics. Each of these disorders presents distinct clinical features that require precise definitions for effective diagnosis and treatment.
Dystonia, for instance, is noted for sustained muscle contractions, leading to twisting and repetitive movements, as well as abnormal postures. Patients may experience this in specific muscle groups or in a more generalized manner. In contrast, chorea is characterized by irregular, non-repetitive, and unpredictable movements that can appear to flow from one muscle group to another. Myoclonus, on the other hand, consists of sudden, brief jerking movements which may be triggered by sudden stimuli or may occur spontaneously. Tics are more complex, involving sudden, recurring movements or vocalizations that are often preceded by an urge to perform the movement.
Defining these clinical phenotypes accurately is crucial for research and clinical application, as they inform the choice of diagnostic tools, treatment strategies, and prognosis. The definitions not only help in identifying the disorder’s presence but also guide the clinician’s understanding of the disorder’s etiology and underlying mechanisms.
| Movement Disorder | Key Characteristics |
|---|---|
| Dystonia | Sustained muscle contractions, abnormal postures |
| Chorea | Irregular, unpredictable movements, flowing transitions between muscle groups |
| Myoclonus | Sudden, brief jerking movements, can be spontaneous or stimulus-induced |
| Tics | Sudden, recurrent movements or vocalizations preceded by urge |
Consensus among experts about these definitions helps standardize clinical assessments and enhances the comparability of research across different studies. Ongoing discussions in the medical community aim to refine these definitions further, taking into account the granularity of symptoms, variations across populations, and the interplay between genetics and environmental factors in the manifestation of these disorders.
Assessment Methods
Accurate assessment of hyperkinetic movement disorders is critical for tailoring effective treatment and improving patient outcomes. Various methods are employed to evaluate the clinical phenotype of these disorders, each with its strengths and limitations. This section explores the primary assessment techniques, focusing on observational clinical assessments, standardized rating scales, neuroimaging, and genetic testing.
Observational clinical assessments are the cornerstone of movement disorder evaluation. Trained clinicians use direct observation to identify and characterize involuntary movements. This method allows for real-time monitoring of the patient’s symptoms, revealing fluctuations in movement patterns that may not be captured in clinical ratings alone. However, this approach can be subjective and may vary considerably between different evaluators.
Standardized rating scales have been developed to provide a more objective framework for assessment. One widely used scale is the Abnormal Involuntary Movement Scale (AIMS), which quantifies involuntary movements by examining severity and frequency. Another common tool is the Unified Huntington’s Disease Rating Scale (UHDRS), which specifically addresses chorea and its impact on daily living. These tools help ensure consistency in how symptoms are assessed across different clinical settings, although interrater variability can still occur due to differing interpretations of the scale items.
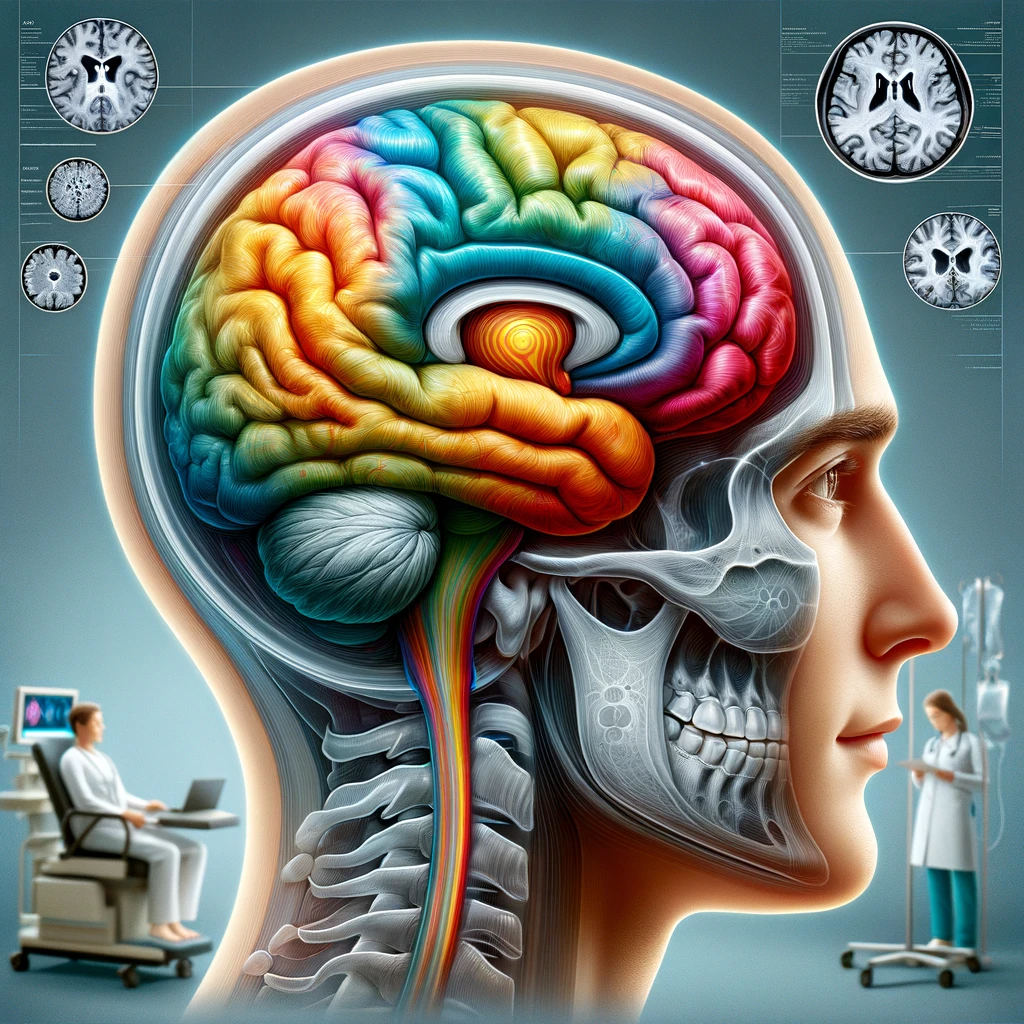
Neuroimaging techniques, such as magnetic resonance imaging (MRI) and functional MRI (fMRI), play a vital role in the assessment of underlying neurological changes associated with hyperkinetic movement disorders. These imaging modalities allow for visualization of anatomical and functional abnormalities in the brain, which can assist in diagnosing the specific type of movement disorder. While neuroimaging provides valuable insights, it is important to recognize that structural and functional changes do not always correlate directly with clinical symptoms.
Genetic testing is increasingly becoming a part of the assessment landscape, particularly with disorders known to have a genetic basis, such as Huntington’s disease and certain forms of dystonia. By identifying specific genetic mutations, clinicians can confirm diagnoses and predict disease progression, thereby informing treatment plans. However, the diversity of genetic factors involved in hyperkinetic disorders presents challenges in establishing a comprehensive genetic testing approach.
To summarize the various assessment methods, the following table outlines their key features and considerations:
| Assessment Method | Key Features | Limitations |
|---|---|---|
| Observational Clinical Assessments | Real-time monitoring, immediate symptom characterization | Subjective, variability between evaluators |
| Standardized Rating Scales | Objective frameworks (e.g., AIMS, UHDRS) | Interrater variability, potential for differing interpretations |
| Neuroimaging | Visualization of brain anomalies (MRI, fMRI) | No direct correlation with clinical symptoms, resource-intensive |
| Genetic Testing | Confirmation of genetic mutations, predictive capabilities | Complexity of genetic factors, not all disorders have identifiable mutations |
The multifaceted approach to assessing hyperkinetic movement disorders emphasizes the need for a comprehensive understanding of each individual’s clinical presentation. The integration of observational assessments, standardized scales, neuroimaging, and genetic testing contributes to more accurate diagnoses and the development of personalized treatment strategies. Continued research and collaborative efforts among clinicians will enhance these assessment methods, ultimately improving the management of patients with hyperkinetic movement disorders.
Interrater Agreement Results
Interrater agreement among clinicians evaluating hyperkinetic movement disorders is critical for achieving reliable diagnoses and treatment plans. This section presents findings on interrater reliability from various studies, which measured agreement levels among experts regarding the classification and assessment of movement disorders. High interrater agreement not only enhances confidence in clinical evaluations but also ensures that criteria for diagnosing conditions are uniformly applied across different settings.
Several recent studies have shown that the interrater agreement varies for different hyperkinetic movement disorders. To quantify this, researchers often use statistical measures such as Cohen’s kappa, which provides a standardized way to assess agreement beyond chance. For instance, studies focusing on dystonia reported a kappa value indicating substantial agreement among clinicians (κ = 0.78), suggesting that experienced evaluators are likely to arrive at similar diagnoses when confronted with patients exhibiting dystonic movements.
In contrast, chorea assessments demonstrated more variability in agreement, with kappa values around 0.55, which is interpreted as moderate agreement. The inherent complexity of chorea, characterized by rapid and unpredictable movements, may contribute to the difficulties in consistent assessments. Evaluators might differ in their interpretations of the severity and impact of the movements on daily living, leading to discrepancies in classification.
Myoclonus showed a kappa value of 0.65, which falls into the range of moderate to substantial agreement, indicating that while most clinicians can recognize and diagnose myoclonus reliably, some differences persist. Factors such as the specific type of myoclonus (e.g., cortical vs. subcortical) and context of the assessment (e.g., during functional tasks versus at rest) can alter diagnostic agreement.
Tic disorders demonstrated a high level of interrater agreement, with kappa values exceeding 0.80 for both simple and complex tics. This high agreement indicates that clinicians are generally consistent in recognizing the characteristics of tics, which often include specific motor or vocal manifestations identifiable by experienced practitioners. The relative clarity of tic symptoms may enhance agreement among clinicians.
The table below summarizes the interrater agreement results for various hyperkinetic movement disorders:
| Movement Disorder | Kappa Value (κ) | Agreement Level |
|---|---|---|
| Dystonia | 0.78 | Substantial Agreement |
| Chorea | 0.55 | Moderate Agreement |
| Myoclonus | 0.65 | Moderate to Substantial Agreement |
| Tic Disorders | 0.80+ | High Agreement |
In reviewing these findings, it becomes evident that while some disorders may yield high interrater reliability, variability exists for others, particularly in those with more complex movement patterns. This inconsistency can be influenced by several factors, including the training and experience of the evaluators, the protocols used for evaluation, and patient-related factors such as symptom severity and presentation context. Addressing these discrepancies through ongoing training and the development of more refined assessment tools could further enhance interrater agreement.
The presence of notable interrater variability underlines the importance of continued efforts within the clinical community to align diagnostic criteria and enhance evaluative training. By fostering greater consensus on how hyperkinetic movement disorders are classified and assessed, researchers and clinicians can facilitate better patient management and outcomes.
Future Directions
Future research in hyperkinetic movement disorders is poised to enhance both the understanding and management of these complex conditions. A key area of focus should be the creation and validation of standardized diagnostic criteria that not only account for the diversity of clinical presentations but also integrate objective assessment tools alongside clinical evaluations. The aim is to develop a universal framework that can be utilized across different clinical settings, ensuring that patients receive consistent diagnoses and treatment plans regardless of where they are evaluated.
Furthermore, the integration of technology such as machine learning and artificial intelligence into the assessment process holds immense potential. By analyzing large data sets derived from clinical observations and objective measurements, these technologies could aid in identifying patterns in hyperkinetic movement disorders that may not be readily apparent to human observers. This approach could lead to more precise phenotyping of disorders, ultimately guiding personalized treatment strategies tailored to individual patient profiles.
Another significant direction for future research involves exploring the genetic variations associated with hyperkinetic movement disorders. A deeper understanding of the genetic underpinnings of these conditions can illuminate their pathophysiology and potentially lead to targeted therapies that address the root causes rather than just managing symptoms. Collaborative studies across genetic, neurological, and clinical disciplines will be crucial in this endeavor.
Moreover, longitudinal studies that monitor patients over time can provide insights into the progression of these disorders and their response to various interventions. Such studies would allow researchers to gather comprehensive data on symptom evolution and treatment efficacy, ultimately contributing to evidence-based guidelines for clinical practice.
Patient-centered research is another vital area for future directions. Engaging patients and caregivers in the research process can ensure that studies consider the impact of hyperkinetic movement disorders on daily life from the patients’ perspective. This could lead to developments in supportive care that effectively address the psychosocial aspects of living with these disorders, thereby improving overall quality of life.
The collaboration between researchers, clinicians, and patients is essential for translating findings into clinical practice. Interdisciplinary efforts aimed at understanding the multifactorial nature of these disorders can help address gaps in knowledge and training. Sharing best practices, insights from clinical experiences, and innovations in care strategies through professional networks and forums can further enhance the collective capability to manage hyperkinetic movement disorders effectively.
Lastly, increased funding and resource allocation for hyperkinetic movement disorder research will be necessary to pursue these ambitious goals. By creating robust research infrastructures, fostering collaborations, and encouraging innovative approaches, the medical community can work towards better diagnostic and treatment paradigms that improve the lives of those affected by these challenging disorders.