Study Overview
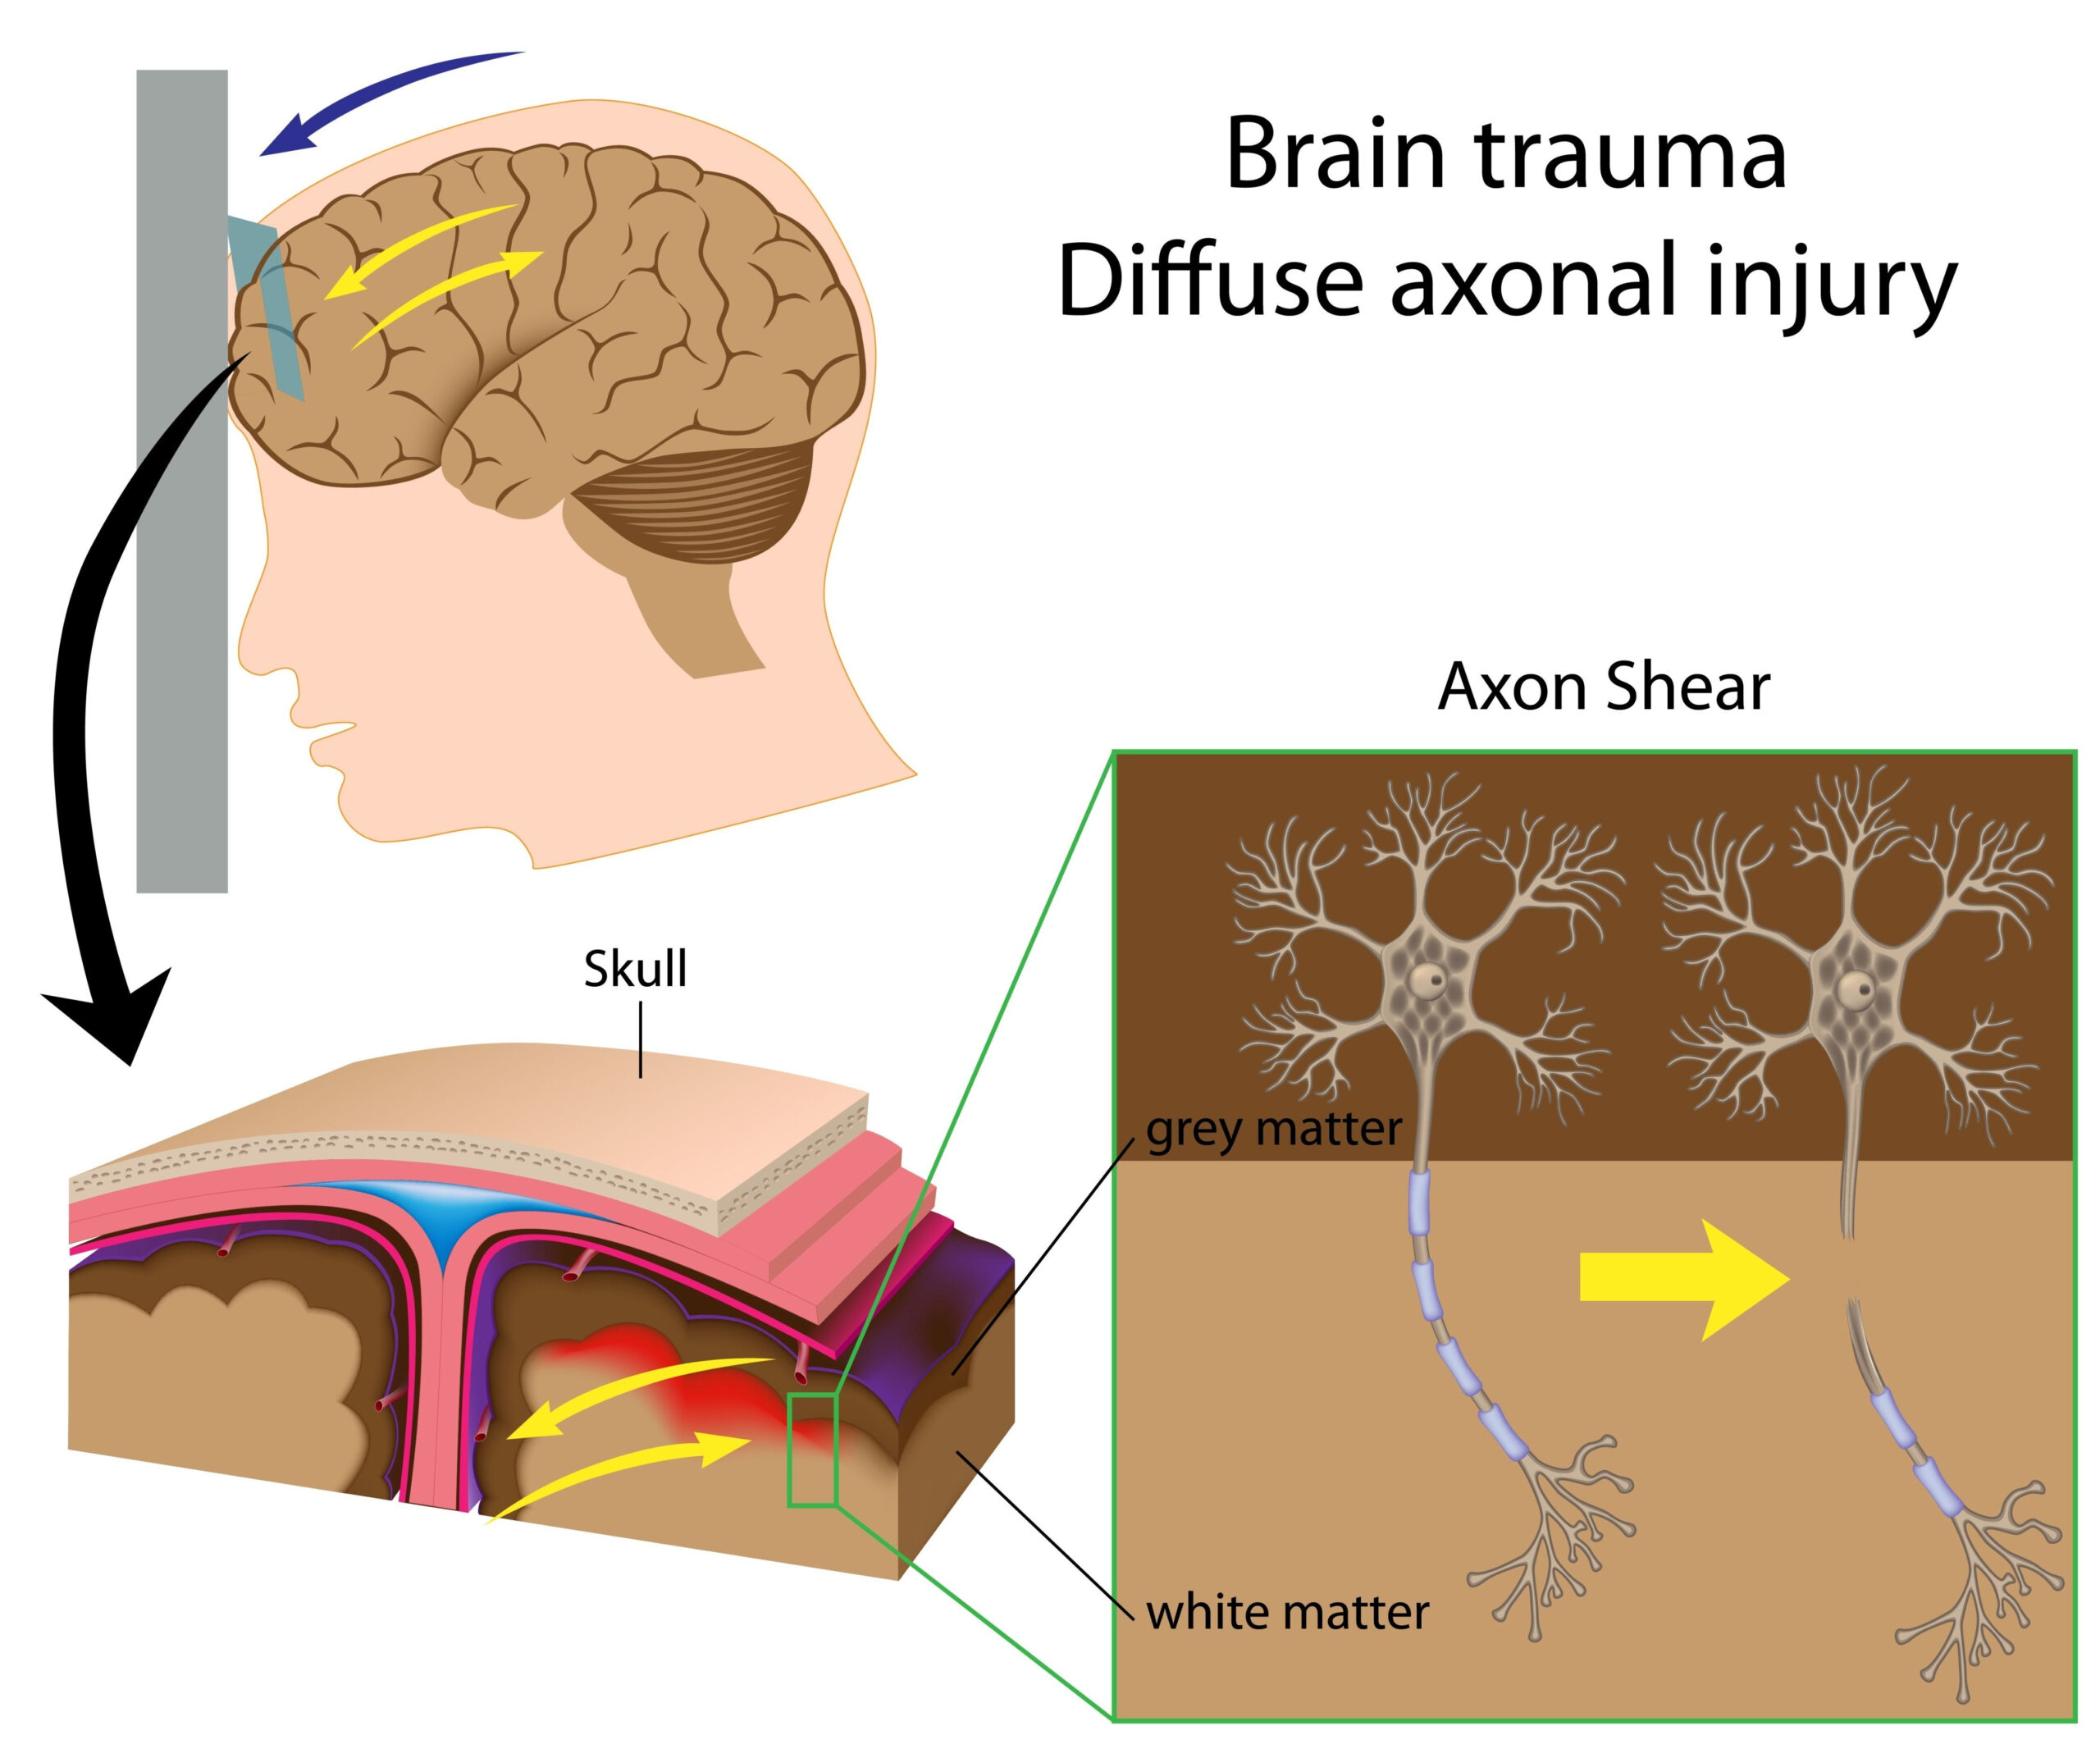
This research investigates the relationships between latent class phenotypes and the subsequent management of patients experiencing traumatic subdural hematoma (SDH) with midline shift. Traumatic SDH occurs when blood gathers between the brain’s surface and its outer covering, which can lead to increased intracranial pressure and severe neurological impairment. Midline shift refers to the displacement of the brain’s midline structures, indicating significant mass effect from the hematoma.
The study focuses on how different phenotypes, which represent distinct clusters of clinical characteristics and presentations among patients, can influence emergency department (ED) disposition decisions. Understanding these connections is crucial, as timely and appropriate disposition can greatly affect patient outcomes.
This research utilized a retrospective cohort design, systematically examining data from patients who presented to emergency departments with traumatic SDH. By applying latent class analysis, the researchers aimed to identify different subgroups within the patient population, characterized by various clinical features and risk factors. Identifying these subgroups helps in understanding the complexities of diagnosis and treatment in emergency settings.
Through this study, the authors seek to enhance the understanding of how clinical presentations correlate with emergency care decisions, potentially leading to more tailored approaches in managing patients with traumatic brain injuries. Ultimately, the insights gained from this research could contribute not just to individual patient care but also to broader strategies in emergency medicine that prioritize rapid and effective treatment of critical conditions.
Methodology
The present study employed a retrospective cohort design, examining medical records of patients diagnosed with traumatic subdural hematoma (SDH) complicated by midline shift across several emergency departments. The study focused on a defined timeframe to ensure consistency in the data collected, allowing for a thorough evaluation of clinical presentations and disposition outcomes.
Data collection involved reviewing electronic health records to extract relevant demographic information, clinical characteristics, imaging findings, treatment interventions, and final disposition outcomes from the emergency department. Key variables included age, sex, Glasgow Coma Scale scores upon admission, the presence of co-morbid conditions, and the specific imaging findings that indicated midline shift. The research team ensured comprehensive inclusion criteria to capture a wide spectrum of cases, offering a nuanced view of the patient population.
Latent class analysis (LCA) was utilized to uncover distinct phenotypes within the cohort. This statistical method enables the identification of unobserved subgroups within a population based on patterns of observed variables. By performing LCA, researchers could cluster patients not merely based on demographic factors but by clinical presentations and risk factors that significantly influence their outcomes in the emergency department. Each identified class was characterized by a unique set of symptoms and clinical histories, facilitating a more tailored understanding of each subgroup.
Furthermore, the study evaluated the emergency department disposition decisions—outcome categories that included admission to a neurosurgical unit, transfer to a tertiary care facility, or discharge. Disposition decisions were analyzed in relation to the identified latent classes to uncover any associations between specific clinical phenotypes and the subsequent management choices made by emergency physicians.
Statistical analyses were conducted to ascertain the strength and significance of relationships between the latent classes and patient outcomes. Adjustments for potential confounders were made using multivariable logistic regression models. The researchers ensured that their analyses maintained high methodological rigor and adhered to ethical guidelines, including obtaining necessary institutional review board approvals for the use of patient data.
The results from these analyses aimed to inform clinical practices by elucidating how different presentations of traumatic SDH might influence emergency department decision-making processes. By establishing these connections, the study aimed to enhance the standard of care delivered within emergency medicine settings for patients suffering from traumatic brain injuries.
Key Findings
The analysis revealed several critical insights regarding the relationship between latent class phenotypes and emergency department (ED) disposition for patients with traumatic subdural hematoma (SDH) presenting with midline shift. Among the patient cohort, distinct phenotypes emerged related to varying clinical presentations, demographic factors, and comorbidity profiles. Four primary latent classes were identified, each showcasing unique characteristics that influenced clinical outcomes and decision-making processes in the ED.
Class one, characterized by the youngest patients with higher Glasgow Coma Scale (GCS) scores, tended to manifest less severe neurological deficits. These patients often required less intensive interventions and frequently were discharged home after evaluation. In contrast, class two consisted of older patients who presented with more complex medical histories and significant co-morbidities such as hypertension and diabetes. This group was found to have a higher likelihood of being admitted to inpatient care due to the increased risk of complications associated with their condition.
Patients in class three exhibited severe neurological impairment upon admission, reflected by markedly low GCS scores. This group faced immediate emergency interventions, including possible surgical interventions, with a substantial rate of transfer to tertiary care facilities for neurosurgical evaluation. Lastly, class four included a heterogeneous group of patients whose clinical profiles aligned with moderate trajectories. They had intermediate GCS scores and presented diverse symptoms, which influenced variable treatment paths, with some requiring admission and others being discharged.
Statistical analysis demonstrated that the latent classes were significantly associated with emergency department disposition decisions. A logistic regression model indicated that patients in class one were 70% more likely to be discharged compared to those in class three, who had over 80% odds of requiring inpatient admission. Notably, patients in class two had a consistently higher probability of being transferred to specialized care than those in class four, underscoring the impact of initial clinical presentation on treatment pathways.
The presence of midline shift, a crucial imaging finding, correlated closely with the severity of clinical features observed across the identified phenotypes. Midline shift was predominantly noted in classes three and four, reinforcing the notion that greater displacement on imaging translates to more serious clinical implications. Moreover, analysis revealed that appropriate identification and classification of these latent classes could guide emergency physicians in making timely and informed decisions regarding the management of traumatic SDH.
The key findings of this research validate the hypothesis that distinct latent class phenotypes significantly influence emergency department disposition outcomes for patients with traumatic SDH. By recognizing these phenotypes, emergency departments can better stratify care and enhance patient management, promoting tailored approaches that align with individual patient needs and improving overall clinical outcomes.
Clinical Implications
Understanding the clinical implications of latent class phenotypes in patients with traumatic subdural hematoma (SDH) and midline shift is vital for enhancing emergency department (ED) practices. The identification of distinct phenotypes based on clinical presentations provides invaluable insights that can inform treatment protocols and patient management strategies in real-time. By recognizing the variations among patients, emergency physicians can make more nuanced decisions that ultimately affect patient outcomes.
Firstly, the establishment of four primary latent classes reveals the heterogeneity in presentations and the corresponding risk factors associated with each group. This stratification is crucial for tailoring interventions effectively. For instance, younger patients displaying less severe neurological impairment (class one) often require minimal intervention compared to older adults with significant comorbidities (class two), who may be at higher risk for complications. This information can streamline the triaging process within the ED, allowing clinicians to allocate resources efficiently based on the anticipated needs of different patient groups.
Moreover, patients presenting with severe neurological deficits (class three) warrant urgent attention, potentially accelerating the need for surgical evaluation or transfer to specialized care. Recognizing that these patients come with a high likelihood of necessitating immediate interventions emphasizes the importance of prompt assessment and decision-making. Implementing protocols that prioritize rapid imaging and evaluation for such high-risk groups could enhance survival rates and improve overall care quality.
The findings emphasize the role of midline shift as a significant imaging biomarker in assessing the severity of traumatic SDH. Clinicians should give due weight to this factor when making disposition decisions—elevated levels of midline shift correlate with severe clinical ramifications. This reinforces the necessity of integrating imaging findings with clinical assessments for a comprehensive understanding of patient urgency.
Furthermore, the insights derived from this study could facilitate the development of evidence-based guidelines and training programs for emergency department staff. Understanding the latent class phenotypes can result in better recognition of at-risk patients and promote a standardized approach to management that accounts for individual clinical profiles, ultimately leading to improved continuity of care when transitioning patients from the emergency setting to inpatient units or specialized services.
In addition, fostering an awareness of these phenotypes may also support participant-centered approaches in patient education and care planning. When patients and their families understand the implications of specific clinical presentations, they can engage more effectively in decision-making processes regarding care options, thereby enhancing patient satisfaction and compliance.
The clinical implications highlighted by this research call for an evolution in emergency medical practice, advocating for a holistic and personalized treatment framework that utilizes latent class identification to inform clinical decision-making. By transitioning toward more tailored approaches in managing traumatic SDH, we can optimize patient outcomes and refine the emergency care paradigm.